
- Health Conditions A-Z
- Health & Wellness
- Nutrition
- Fitness
- Health News
- Ayurveda
- Videos
- Medicine A-Z
- Parenting
The Life-Saving Surgery That Saved The Twin Brothers

Credits: King's College Hospital NHS Foundation Trust
Eight-month-old twins from Hayward Heath, West Sussex, recently met the surgeon who saved their lives even before they were born. The BBC reports how their mother, Katerina Ahouansou, at six months pregnant, during a routine scan, uncovered a serious issue with their development and blood supply.
Doctors diagnosed the twins with twin-to-twin transfusion syndrome or TTTS. It is a condition where one twin received more blood and nourishment than the other due to uneven blood vessel distribution in the placenta. In case there is no medical intervention, it could be fatal for both the twins.
A Specialist Steps In
This is when Ahouansou was referred to Professor Kypros Nicolaides at King’s College Hospital in London. Professor Nicolaides is a pioneer in fetal medicine and he specializes in a laser procedure that redistributes blood supply between twins in cases of TTTS.
When Ahouansou was scanned, Nicolaides observed that one of the twins were significantly smaller than the other. "There was a very high chance that if we did not intervene, both twins could die," he recalled.
An Operation No Less Than A Miracle
The life-saving laser surgery was performed and within a week the doctors saw an improvement with the twin who was smaller in size. When the twins were born, they weighed 1.5kg and 1.7kg. To recognize the efforts by the surgeon, Ahouansou named them Kai Kypros and Asher Nicolas after Professor Kypros Nicolaides.
Ahouansou also expressed deep gratitude for the professor's expertise and called him "proof that miracles can be performed by people who are devotees to their profession."
Professor Kypros Nicolaides has been at King’s College Hospital since 1980 and is widely regarded as a leader in fetal medicine. His groundbreaking research and development of screening and surgical techniques have saved countless lives.
Through his dedication, Professor Nicolaides has given many families hope, demonstrating how medical advancements continue to improve survival rates for complex fetal conditions like TTTS.
More about Twin-to-twin Transfusion Syndrome
As per the John Hopkins Medicine, TTTS is a rare pregnancy condition that affects identical twins or other multiples. It happens in pregnancies where twins share one placenta and a network of blood vessels that supply oxygen and nutrients essential for development in the womb. These pregnancies are known as monochorionic.
Sometimes, the blood vessels in the placenta are unevenly distributed, causing an imbalance in blood flow between the twins. The donor twin loses more blood than it receives, leading to malnutrition and potential organ failure. Meanwhile, the recipient twin gets an excess of blood, putting strain on the heart and increasing the risk of cardiac complications.
Impact on the Donor Twin
The donor twin loses blood volume (hypovolemia), reducing kidney function and urine production. This leads to low amniotic fluid levels (oligohydramnios) or, in severe cases, a complete absence (anhydramnios). Without proper blood circulation, the donor twin faces cardiovascular issues, increasing the risk of death.
Impact on the Recipient Twin
The recipient twin experiences excess blood volume (hypervolemia), causing increased urination and excessive amniotic fluid (polyhydramnios). The overworked heart struggles to handle the surplus blood, leading to cardiovascular dysfunction, heart failure, and, in extreme cases, death.
Heart Health In Women After Pregnancy: Why Pre-Eclampsia And Gestational Complications Matter Years Later

Credit: AI
For every woman pregnancy is a beautiful and dream journey, but from the perspective of heart-health , it acts as a “natural stress test” for the body. The best part is most women recover completely after childbirth. However, certain complications such as preeclampsia, high blood pressure, gestational diabetes, preterm delivery, or poor fetal growth can sometimes be early warning signs of future cardiovascular risk.
As a cardiologist, I want women to know that preeclampsia does not simply end when pregnancy ends. It can signal a higher risk of high blood pressure, diabetes, heart disease and stroke later in life. Gestational diabetes also increases future cardiometabolic risk.
This does not mean you will develop heart disease. It means you have an opportunity to be proactive.
Also read: Maternal Immunisation: The Forgotten Half of Protecting a Baby's Health
What should be your postpartum action plan?
1. Check your blood pressure regularly, especially after preeclampsia or gestational hypertension.
2. Check blood sugar after gestational diabetes and continue recommended long-term screening.
3. Know your numbers: monitor cholesterol, weight and other cardiovascular risk factors.
4. Rebuild healthy habits: gradually return to regular exercise, eat a heart-healthy diet, avoid smoking and prioritise sleep.
5. Tell your doctor your pregnancy history—it is an important part of your lifelong heart history.
Your pregnancy may be over, but not your heart health journey, it continues for life time. Early awareness gives you the power to prevent problems before they begin.
By Dr. Sunil Kumar Mandal, MBBS, MD , DM (Cardiology), Senior Consultant Interventional Cardiologist
Maternal Immunisation: The Forgotten Half of Protecting a Baby's Health
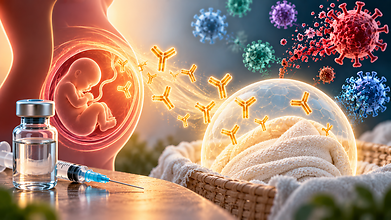
Credit: Ai
Vaccination during pregnancy protects more than just the mother. Vaccines such as Td, Tdap, and influenza (when recommended) help pass protective antibodies to the baby, providing valuable immunity during the first six months of life.
When people think about vaccination, they usually think about babies receiving their first vaccines after birth. However, an important part of a child's protection actually begins during pregnancy.
Maternal immunisation helps protect both the mother and her baby by allowing protective antibodies to pass through the placenta before birth. These antibodies provide the newborn with temporary immunity during the first few months of life, when the baby's immune system is still developing and routine childhood vaccines have not yet become fully effective.
Despite its importance, awareness about maternal immunisation remains low, with many women knowing only about the Td vaccine while being unaware of the benefits of Tdap and influenza vaccination when recommended.
What is maternal immunisation?
Maternal immunisation refers to vaccines that are recommended during pregnancy to protect the mother from certain infections while also passing protective antibodies to the unborn baby.
During the third trimester, these antibodies cross the placenta and help protect the newborn from serious illnesses during the first six months of life. This protection is especially important because young infants are more vulnerable to infections and cannot receive all vaccines immediately after birth.
Important vaccines during pregnancy
Td (Tetanus and Diphtheria): The Td vaccine is routinely recommended during pregnancy. It protects the mother against tetanus and diphtheria while also helping protect the newborn from neonatal tetanus.
Tdap (Tetanus, Diphtheria and Pertussis): In many situations, doctors may recommend the Tdap vaccine during pregnancy. It also protects against pertussis (whooping cough), a highly contagious infection that can be life-threatening for young babies. Vaccination during pregnancy allows antibodies to reach the baby before birth, reducing the risk of severe illness in early infancy.
Influenza (Flu) Vaccine: Pregnant women are at a higher risk of developing complications from influenza. When recommended by the treating doctor, the influenza vaccine helps protect both the mother and the baby during flu season.
Why it matters for the newborn
A newborn's immune system is still immature, making babies more susceptible to infections. The antibodies received from the mother act as the baby's first shield against disease until the infant starts receiving routine childhood vaccines and develops their own immunity. This early protection can reduce the risk of severe infections during one of the most vulnerable stages of life.
Tips for expectant mothers
• Discuss maternal vaccination during your first antenatal visit.
• Receive the Td vaccine according to your doctor's advice.
• Ask your obstetrician whether Tdap is recommended during your pregnancy.
• Take the influenza vaccine if advised by your doctor.
• Attend all scheduled antenatal check-ups.
• Maintain a healthy diet, adequate sleep, and good hydration during pregnancy.
• Encourage family members and caregivers to stay up to date with their vaccinations to help protect the newborn.
• Ensure your baby receives all routine childhood vaccines on time after birth.
By discussing vaccination early in pregnancy and following medical advice, expectant mothers can provide their newborn with valuable protection during the first six months of life, giving them a healthier and safer start.
Egg Freezing Is Rising, But Are We Freezing Fertility or Buying Time?

Credit: AI
Egg freezing, to be sure, sounds incredibly promising to a woman in her early 30s: freeze your current eggs and get more choices in the future. There is, however, a crucial distinction that is lost amid all the excitement about advances in reproductive technologies. Egg freezing is not fertility freezing; it is a freezing of part of your fertility at a specific age. The distinction is critical.
Not only do fertility and the chance of having a healthy baby decrease with age, but the decline in the biological quality of a woman's oocytes, as well as their number, contributes to fertility and genetic problems as well. To be more specific, if a woman gives birth at a very young age, she is more likely to have a miscarriage, or her baby will have a chromosomal disorder. Vitrification is the name of the technique of freezing cells ultra-rapidly to quite a bit reduce damage caused by ice crystals and this is the technique which has made egg preservation so reliable.
But the freezer cannot revert your 35-year-old eggs to 25-year-old ones and ovarian reserve testing cannot tell for sure if a certain frozen egg will ever lead to a pregnancy.
And that, perhaps, is the most important discussion that India must have.
Indian women are not postponing motherhood for just one reason
Also read: How Age Affects Fertility And The Chances Of Success With IVF
Rarely in the Indian context is the delay of motherhood something to do only with career. For some women, it is finishing higher education, gaining financial independence or getting a foothold in the professional world. For others, marriage may be postponed due to shifting notions of compatibility, financial security, or personal choice. Women may get married younger but delay pregnancy to 'set up house, ' to help ageing parents, or simply to feel 'ready' to be a parent.
The image is further complicated by the truth. India remains caught between two very different ideas of womanhood. For many women, motherhood, at least for married women, remains essentially goodwife-hood, and a woman's transition into it takes place with surprising proximity to her married life. For others, the younger generations, having children wants to be informed by new states of control that women desire over their bodies, over if, when and how they find themselves to be mothers.
An unmarried woman faced with egg freezing may in this way have been faced with something beyond a medical choice; she may have been confronted with issues of marriage, family and social morality. For such women, egg freezing may so have been an option that is seldom present in ordinary fertility choices: a space in which the decision to reproduce need not have been inextricably linked to the decision to marry, the decision to have children at once.
Yet, this kind of autonomy is not open to all. The technology might provide greater flexibility over when to reproduce, yet its expense, the requirement for specialised fertility treatment and the demand for frequent serum monitoring mean that class still shapes who can actually access it. Which in turn makes egg freezing about a great deal more than reproductive biology. It's a story about access, exclusivity and who is able to buy a few extra years.
The uncomfortable economics of reproductive choice
Also read: Before You Start IVF, 7 Critical Factors You Must Consider
Marketing around egg freezing often talks of how powerful this process can be, yet that very power hinges on affordability. In India, one cycle of egg freezing costs roughly 1 to 1.5 lakh, while storage fees amount, at minimum, from 30,000 to 40,000 a year, with considerable variations according to clinics.
Though this amount can be looked at as a big expense for a young, financially well-off professional working in cities like Bengaluru, Mumbai or Delhi, it is still an investment that can be handled. Still, to a schoolteacher or a junior doctor or researcher, small business owner or a woman who is helping her parents, the same egg freezing procedure can represent several months of savings.
This creates an overlooked paradox: the technology that gives women greater reproductive autonomy may initially be accessible mainly to women who already possess greater economic autonomy.
And there is another inequality. Women living outside India's major fertility hubs may have fewer opportunities for specialist counselling and high-volume reproductive medicine services. The question, therefore, should not simply be whether egg freezing is available in India, but who can realistically access informed egg freezing and who cannot.
Freezing eggs is not the same as freezing a future baby
Also read: IVF: What Is The Right Age To Start, How Many Times You Can Try And What To Expect
Perhaps the greatest misconception is that a box of frozen eggs represents a guaranteed future pregnancy. It does not.
Eggs must survive warming, be fertilised—usually through ICSI—develop into viable embryos, implant and ultimately result in a live birth. At every stage there is attrition. Age at freezing matters because younger eggs generally have better reproductive potential. The American Society for Reproductive Medicine notes that outcomes appear better when planned oocyte cryopreservation occurs at younger ages, while also emphasising that available evidence is insufficient to promise a specific live-birth probability for an individual woman.
A 2025 review from Indian fertility specialists similarly stresses that freezing more than 20 mature oocytes before age 38 has been associated with an estimated 70% chance of one live birth, but this should not be interpreted as a guarantee for every woman.
This is why the phrase "egg insurance" can be misleading. Insurance protects against a defined risk under defined conditions. Egg freezing provides an additional reproductive option; it does not insure motherhood.
The paradox of waiting
There is an even subtler problem.
A woman may freeze her eggs at 30 and feel that the fertility question has been "taken care of." She may then postpone pregnancy until 38, 40 or 42 because she believes her frozen eggs have removed the urgency.
But pregnancy at an older age still involves an older uterus and a body with age-related changes. Frozen eggs preserve the biological age of the eggs—not the biological age of the woman who will eventually carry the pregnancy.
That distinction deserves far more attention in advertisements and counselling rooms.
Interestingly, relatively few women who freeze eggs eventually return to use them, according to the available literature. Some marry and conceive naturally; some decide not to have children; others may encounter circumstances in which their frozen eggs are never used. So what is being purchased? Perhaps not fertility. Time. Time to finish medical residency. Time to build a company. Time to become financially independent. Time to find a partner without treating marriage as a biological deadline. Time to decide whether motherhood is actually wanted.
For Indian women, that may be the real revolution.
However, the medical dialogue needs to remain straightforward – egg freezing can increase the options for reproduction, yet it does not mean eliminating reproductive aging. So the objective here is not to encourage every young woman to go through the procedure of egg freezing. Rather, it is necessary to make sure that each woman who decides to undergo the procedure understands all the implications.
As far as the most empowering technology is concerned, it is not necessarily the one that promises a guaranteed future. Rather, it is the technology which provides more opportunities without hiding any of its limitations.
- Follow Us :


© $2026 Times Horizon Private Limited