
- Health Conditions A-Z
- Health & Wellness
- Nutrition
- Fitness
- Health News
- Ayurveda
- Videos
- Medicine A-Z
- Parenting
Speech And Communication Milestones For Babies From Birth To 12 Months

Image Credit: Canva
Babies' first words are often seen as a important and precious moment in their development, marking the beginning of their journey into verbal communication. For instance, when the baby looks at his or her parent and says "mama" for the first time, it brightens up the parent's face with joy but it is a meaningful connection in their bond that is growing. For parents, these are some sources of pride and joy. But how do you determine whether your child's speech and language are progressing?
Understanding the communication milestones will help monitor a child's development and spot potential issues before they become more serious. The milestones serve as benchmarks to guide health care providers on whether a child needs further assistance.
Importance of Communication Development in Early Years
The first five years of a child's life are the time of massive growth and brain development at an incredible speed. All domains of development find their roots within this period, including communication. From the day they were born, babies start crying to communicate, and within weeks or months, they begin to babble, imitate sounds, and eventually words. Communication is not only important to express needs but also for understanding the world and building relationships. It is an important tool that supports cognitive, emotional, and social development.
Speech Milestones by Age
Babies learn communication skills at their own pace. General milestones can, however serve as a guideline for typical development. Let's go through these milestones by age:
Newborn (0-3 Months)
At this point, the babies communicate mostly through crying. They give cues as to their needs by responding with actions like smacking the lips when hungry or arching the back when they feel overstimulated. At the end of three months, you may also observe:
- Smiles in response to your appearance.
- Cooing sounds.
- Quiets or smiles when spoken to.
- Your voice.
- Different cries for specific needs.
Upto 6 Months
By six months, babies start experimenting with sounds and use their voice to play. Major developments include:
- Making gurgling sounds during play.
- Babbling with different sounds.
- Vocalizing likes and dislikes.
- Responding to the change in tone of voice.
- Turning eyes toward sounds.
- Showing interest in music and sound-making toys.
Till 12 Months
By the first birthday, there are some significant communication milestones that have been achieved:
- Trying to imitate speech sounds.
- Speaking basic words like "mama," "dada," or "uh-oh."
- Responding to simple commands, such as "Come here."
- Recognizing common items by name, like "shoe."
- Turning toward sounds and voices.
Upto 18 Months
In this stage, children learn to understand and use words in a consistent manner. Some of the important milestones are:
- Knows the names of people, objects, and body parts.
- Responds to simple commands with gestures.
- The child says up to 10 words.
End of 24 Months
By two years of age, children usually have more developed communication skills:
- Using simple sentences, like "more milk."
- Asking one- to two-word questions, such as "Go bye-bye?"
- Following simple directions and answering simple questions.
- Saying 50 or more words.
- Being understood by family members at least half the time.
Ways Parents Can Support Development
Parents can be very supportive in developing the communication skills of their child. Here are some effective strategies:
1. Pay Attention to Hearing: Ensure your child responds to sounds and voices. Notice if they react to noise or look at you when spoken to. If you suspect hearing issues, consult your pediatrician promptly.
2. Engage in Conversation: Respond to your baby’s coos and babbles. Talk to them frequently about daily activities, like “Mommy is making breakfast,” or “We’re going to the park.”
3. Imitation Training: Teach your baby to imitate actions and gestures of others, such as clapping, waving, or peek-a-boo. These activities encourage her to understand turn-taking and even nonverbal communication.
4. Animals Sound: Learning time must be fun. Train your baby to imitate an animal's sound, "A cow says 'moo.'". This encourages sound production along with word association.
5. Read and Sing Together: Reading stories and singing songs expose your child to language patterns and rhythm. Make it a daily habit to promote vocabulary growth.
6. Use Your Native Language: Speak to your child in the language you’re most comfortable with. Early exposure to rich language environments helps babies learn effectively.
7. Strengthen Their Attempts: Cheer every time your child tries to speak. Repeat the words and sounds and gently correct as needed. A little "baby talk" is okay but clearly say simple words for them to imitate.
When to Seek Medical Attention
Though every child develops at his own rate, there are some delays that point toward professional intervention. Talk with your child's health care provider if:
- Doesn't turn toward sounds or his name.
- By 12 months, he isn't babbling, and by 18 months, he has not spoken a single word.
- Uses speech in a peculiar manner or shows delayed speech.
Your pediatrician can refer you to some specialist who could be an audiologist or speech-language pathologist for more extensive testing. In the case of a bilingual child, he will also be evaluated by a bilingual speech-language pathologist.
Communication milestones form a kind of roadmap in understanding how your baby develops. This means through conversation, play, and learning activities, you could be able to enhance language skills while promoting your child's development. When concerned about delay, consult professional help, as this might make all the difference by having communication skills set up to meet a great future for your child.
Communication Milestones: Birth to 1 Year. American Speech-Language-Hearing Association
Trying to Conceive After an Abortion? Key Physical and Emotional Factors to Consider
Credit: iStock
After an abortion, patients may endure mild pain in the initial days and vaginal bleeding resembling menstruation for 3-7 days. Abortion can bring mixed emotions. Deciding to try for a pregnancy after an abortion can bring a mix of emotions. Some women may feel ready to conceive again soon, while others may need more time physically or emotionally. No single timeline works for everyone. To understand when the body is ready and support emotional well-being, a few factors can help women make informed decisions before trying again.
What to avoid after an abortion
In most cases, fertility can return quite quickly after an abortion. Ovulation may resume within a few weeks, which means pregnancy is possible even before the next menstrual period. For women who had an uncomplicated abortion, there may not always be a medical need to wait for several months before trying to conceive. However, the right time can depend on the individual's health, how far along the pregnancy was, the type of abortion, and whether there were any complications. But it is always advised to abstain from sexual activities for at least a month to prevent unintended pregnancies and avoid damage to the cervix.
If you had a surgical abortion or a dilation and curettage (D&C) procedure, your doctor may advise abortion recovery; suggest waiting for 3 months for your uterus to heal and then plan pregnancy. If your miscarriage occurred in the second or third trimester, it may be recommended to wait for 3 to 6 months (depending on your physical and mental capacity) so that your body can rest well and recover from any deficiencies before the next pregnancy. Abortion can disrupt hormonal balance and alter the menstrual cycle, affecting reproductive health and leading to infection and inflammation.
Give your body time to recover
Although fertility may return quickly, the body still needs time to recover. Remember, the signs of pregnancy are the same whether you had or had not an abortion. Therefore, always look for certain signs, such as bleeding and cramping can occur after an abortion, and the menstrual cycle may take some time to return to its usual pattern.
But if they experience very heavy bleeding, persistent severe abdominal pain, fever, foul-smelling discharge, or other symptoms that could indicate an infection or complication, they should immediately consult a gynaecologist.
Mental health matters too
Physical recovery is only one part of the process; what mostly gets affected is mental health. Abortion or miscarriage comes from different emotions, including relief, sadness, guilt, anxiety, or a combination of these feelings.
There is no "right" way to feel. For some women, becoming pregnant again can bring happiness and reassurance, while for some it may trigger memories or fears related to the previous pregnancy. Emotional readiness weighs more than physical readiness. Therefore, during this phase, it becomes quite important for partners and family members to talk openly and take care of each other.
Also read: Why Is The Trump Administration Stopping Obamacare Health Plans For 760,000 Enrollees?
Diet plays an important role
Abortion leads to blood loss, and bleeding lasts up to a week. So, protein can be an ideal source for blood regeneration. Supplement with basic vitamins such as vitamin C, B1, B2, and vitamin E. For vitamins, consume fresh fruits and green vegetables such as spinach, tomatoes, bean sprouts, pumpkin, apples, and grapes contain extremely rich vitamin content, in addition to iron and phosphorus to help aid in blood replenishment.
Folic acid is a B vitamin that helps regenerate red blood cells. Intake of calcium can help prevent insomnia, lethargy, and aching limbs. Along with these, mild meditation and exercise can help you stay fit physically and mentally.
Does a previous abortion affect future fertility?
A previous abortion also does not necessarily increase the risk of problems in a future pregnancy. After an abortion, possible complications may include heavy bleeding, infection, incomplete abortion or retained tissue, cervical or uterine injury or perforation, uterine adhesions, and temporary menstrual irregularities. In rare cases, complications may affect future fertility; in such cases, immediate medical attention is needed if there is severe or worsening lower abdominal pain, fever or chills, very heavy or prolonged bleeding, foul-smelling vaginal discharge, dizziness, fainting, or significant weakness.
What if pregnancy doesn't happen immediately?
It is normal for conception to take some time. Not becoming pregnant in the first few months does not automatically mean there is a fertility problem. The key is to look beyond the question from "How soon can I get pregnant?" to "Am I physically and emotionally ready?” Every pregnancy creates its own stories.
Sedentary Lifestyle Linked To Rise In Back Pain Among Indian Schoolchildren, Say Experts
Credit: iStock
Musculoskeletal problems such as back pain, once more commonly associated with adulthood and old age, are increasingly being reported among schoolchildren, experts at the Indian Association of Physiotherapists (IAP) have warned.
Ahead of the World Physiotherapy Asia Western Pacific (WPAWP) Regional Conference 2026, IAP experts flagged a reported 40% rise in musculoskeletal problems among schoolchildren, citing sedentary lifestyles and poor movement habits as key concerns.
The experts called for greater focus on prevention, movement education and physical fitness from an early age.
“Back pain does not start in old age. We are seeing a concerning 40% rise in musculoskeletal problems among schoolchildren, and this should make us rethink how we approach preventive healthcare in schools,” Prof. Dr. Sanjiv K. Jha, President of the Indian Association of Physiotherapists (IAP), said.
He flagged concerns that long hours of studying and prolonged screen use are making children increasingly physically inactive. Reduced movement, along with inadequate strength, flexibility and fitness, may contribute to musculoskeletal problems and could have long-term consequences if not addressed.
“We need to shift from treating musculoskeletal problems after they appear to preventing them through early education, fitness and appropriate physiotherapy interventions,” Dr. Jha said.
Also Read: Gut Microbiome Linked To 3x Higher Type 1 Diabetes Risk In Children
Childhood Back Pain Is Already A Concern
Indian research indicates that musculoskeletal symptoms are a significant concern among school-going children.
A study of 934 children aged 8–15 years from four schools in Bhopal found that 55.9% reported pain during the previous 12 months, while 41.6% reported pain during the preceding 10 days and 21.3% had visited a doctor for the problem. The study also found that the average schoolbag weighed 16.5% of the students’ body weight.
Another study among schoolchildren aged 10–16 years in urban and rural areas of Khurda district, Odisha, found an 18.8% prevalence of musculoskeletal pain during the preceding year. The research examined factors including backpack weight, age, gender and body measurements.
Heavy Schoolbags Are Not The Whole Story
Read More: Are Children Breathing Clean Air Inside Classrooms? New European Study Raises Concern
Experts caution against attributing childhood back pain solely to heavy schoolbags. Scientific evidence suggests that musculoskeletal pain can have multiple contributing factors, including physical activity, movement habits, previous injuries, psychosocial factors, prolonged sitting and individual characteristics.
This points to the need for a broader approach to childhood musculoskeletal health rather than focusing exclusively on schoolbag weight.
“We should not totally link childhood back pain to a heavy-school-bag problem. Children need regular movement, physical fitness, strength, flexibility, good movement habits and awareness about how they use their bodies,” Dr. Ruchi Varshney, part of the IAP, said.
She added that physiotherapy can help schools introduce preventive programs focused on movement education, early identification of problems and healthy physical activity rather than waiting until pain becomes persistent.
Schools Can Play A Bigger Role
Physiotherapists believe schools can become important platforms for movement education, exercise, postural awareness, physical fitness, injury prevention, ergonomics, early screening and health promotion.
The larger message is that back pain should not be viewed as an inevitable problem of growing older.
Musculoskeletal health begins in childhood, and prevention should begin before pain becomes persistent.
Regular movement, physical fitness, strength and flexibility can help children develop healthy movement habits and support their musculoskeletal health as they grow.
Don’t Miss a Beat: Why Every Newborn Deserves a Heart Check
Credit: AI
Congenital heart disease (CHD) is not just a paediatric cardiac problem. It is a major public-health challenge. CHD is among the most common birth defects, affecting approximately 8–12 babies per 1,000 live births. In India, with a birth prevalence of around 9 per 1,000, this translates to approximately 2.4 lakh babies being born with CHD every year.
Indian consensus guidance has also estimated that CHDs may account for approximately 10% of infant mortality in the country. These numbers make one thing clear: we cannot treat congenital heart disease only after a child becomes sick. We need to find it earlier. And that is where newborn screening becomes a public-health priority.
The problem is not only CHD. It is missed CHD.
One of the biggest challenges is that a baby with a serious heart defect may look completely healthy at birth. Some critical congenital heart defects may have no obvious signs during the initial newborn examination. A baby may feed normally, have a normal colour and appear ready to go home—only to deteriorate days later when the circulation changes after birth.
By then, what could have been a planned referral can become an emergency. This is why “the baby looks fine” cannot be considered a heart check.
Every newborn needs more than a visual assessment
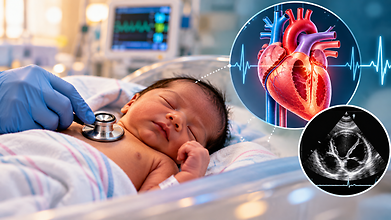
A careful newborn examination remains essential, but it cannot identify every critical heart defect. This is where pulse oximetry can add another layer of protection. Pulse oximetry is a simple, non-invasive test that measures oxygen saturation. When performed alongside clinical examination, it can help identify babies with critical congenital heart disease who may otherwise be missed.
Importantly, pulse oximetry does not diagnose every form of CHD and a normal reading does not rule out all heart defects. It is a screening tool—not a substitute for clinical assessment or echocardiography. Indian studies have demonstrated the potential value of combining clinical examination with pulse oximetry. In one study of asymptomatic newborns, pulse oximetry alone detected 80% of critical CHD cases, clinical examination detected 60%, while combining the two identified all cases in that study.
This is where public health policy matters
The question should no longer be: “Can we screen some babies?” The question should be: “How do we ensure that no baby is missed simply because screening was not available?”
India has already demonstrated that population-level screening can work. Kerala's state-wide newborn programme incorporated pulse oximetry screening into government delivery centres. By 2019, more than 157,000 newborns had been screened, with the programme identifying 134 cases of CHD, including 74 critical cases.
This is the kind of approach that needs to move from individual hospital initiatives towards standardised newborn-care pathways across the country. At Cloudnine Hospitals, we have screened more than 3 lakh babies so far. Through this screening, we identified 92 cases of Critical Cyanotic Congenital Heart Disease (CCCHD). These findings highlight the value and cost-effectiveness of routine pulse oximetry screening in newborns.
Screening without referral is not enough
However, screening is only the first step.
A public-health programme must connect the entire chain:
Screen → Confirm → Refer → Treat → Follow up
A baby who screens positive needs timely access to echocardiography, paediatric cardiology, neonatal stabilisation and, when required, cardiac intervention. This is one of India's biggest challenges. Paediatric cardiac services, specialists, diagnostic facilities and transport systems are unevenly distributed, particularly between urban and rural areas.
Indian literature has highlighted the gap between the enormous number of babies who may require cardiac care and the country's capacity to provide timely specialised treatment. Therefore, universal screening without a strong referral and treatment network cannot solve the problem.
Early diagnosis changes the equation
The good news is that the story of CHD is no longer one of inevitable poor outcomes. With timely diagnosis and access to appropriate treatment, more than 90% of people born with CHD can survive into adulthood with good long-term outcomes. Treatment may include monitoring, medicines, catheter-based procedures, surgery or staged interventions, depending on the defect.
The challenge, therefore, is increasingly about closing the gap between what modern medicine can achieve and what a child actually receives. A child cannot benefit from a life-saving cardiac intervention if the heart defect is never detected, if the diagnosis is delayed, or if the family cannot reach the right centre in time.
Also read: Stopping Ozempic, Wegovy, Mounjaro Linked To 22% Higher Heart Attack, Stroke Risk: Study
The message to parents is simple
Parents should know that congenital heart disease is not always visible at birth. During pregnancy, recommended antenatal scans can help identify several structural heart abnormalities. After birth, a thorough newborn examination and, where available and appropriate, pulse oximetry screening can provide additional opportunities to detect critical heart disease.
Parents should also seek prompt medical attention if their baby develops:
- Difficulty or rapid breathing
- Bluish or greyish lips or skin
- Poor feeding or tiring during feeds
- Excessive sweating while feeding
- Poor weight gain
- Unusual lethargy or recurrent episodes of illness
These signs do not necessarily mean that a baby has CHD, but they should never be ignored.
From awareness to action
For too long, congenital heart disease has been viewed primarily as a specialist problem. It is time to view it as a newborn-health priority. If approximately 2.4 lakh Indian babies are born with CHD every year, then early identification cannot remain dependent on whether a particular hospital has a screening protocol or whether a family happens to reach a cardiac centre in time.
We need standardised newborn screening, trained healthcare professionals, reliable referral pathways, accessible paediatric cardiac services and long-term follow-up.
This is what public-health action looks like.
Don’t Miss a Beat
“Use Heart for Action” should mean more than awareness on World Heart Day. For newborns, it should translate into action at the point where it can make the greatest difference—before a silent heart defect becomes a life-threatening emergency. Each can be an opportunity to detect a problem earlier.
We cannot prevent every congenital heart defect. But we can work towards preventing a missed diagnosis from becoming a missed opportunity to save a child's life. Because every newborn deserves a heart check—and when it comes to a baby's heart, we cannot afford to miss a beat.
- Follow Us :


© $2026 Times Horizon Private Limited