
- Health Conditions A-Z
- Health & Wellness
- Nutrition
- Fitness
- Health News
- Ayurveda
- Videos
- Medicine A-Z
- Parenting
Is There A Right Way To Bottle Feed Your Baby?

When mothers initially feed their babies, they make them lie on their laps, however, the same position may not be safe when the baby is feeding off the bottle.
It is important to feed your baby through the bottle in a semi-upright position and support their head. Do not feed them lying down, as formula or the milk from the bottle can flow into the middle ear, and cause infection. Also, unlike breast and its nipple, the bottle does not have the mechanism to ensure that milk is being overflowed. Also, in order to prevent your little ones from swallowing air as they suck, tilt the bottle so that the formula fills the neck of the bottles and covers the nipple.
How can you choose the right bottle for you?
While some babies happily drink from any bottle, some are much pickier. Yes, you read it right, babies need different bottles, based on how their bodies react after being fed.
If you have a baby with gas, it is best to try a bottle with a venting system. Now, this allows your baby to avoid air in the milk while feeding. Such bottles mimic the shape and feel of a breast or an actual nipple. Bottles with fewer parts are also easier to clean, which could be great during the middle-of-the-night feedings.
For new moms, it is also a great advice to start with a slow-flow nipple to avoid overwhelming your baby and switch to a faster flow when they seem to hold the bottle themselves and can finish milk in less time.
What should you follow when you bottle feed your baby?
As per the National Health Scheme (UK), NHS UK, it is important to be prepared to experiment well with the kind of bottles that suits your baby the best. Thee is no evidence that only one type of teat or bottle is better than any other.
It is always best to ensure that you screw the top tightly into the bottle before you feed your baby.
Bottle Feeding and The Right Positions
Bottle feeding is more than just feeding and nourishing your baby, it is also an opportunity to bond with your babies. Babies also feel secure when their caregivers are feeding. This is why it is important that even before you start bottle feeding, you first find a comfortable spot to sit with your baby close to you. Look at them and gently hold the and talk as you feed.
Hold your baby in a semi-upright position during bottle feeds, with their head supported. This ensures they can breathe and swallow comfortably. Brush the teat gently against their lips, and when they open their mouth wide, let them draw the teat in.
Take your time—babies feed at their own pace, so be patient and allow them plenty of time to enjoy their meal.
Do not leave your baby un-monitored
Always supervise your baby during feeding sessions. Do not prop the bottle or leave them alone with it. This can also cause choking hazard, or the milk could pool in their mouth which could increase ear infections.
The bottle's position matters as much as baby's position. When feeding, hold the bottle in a horizontal position, tipping it slightly. This helps the milk flow steadily and reduces the amount of air your baby may swallow. If the teat flattens, gently pull the corner of your baby’s mouth to release the suction. Should the teat become blocked, replace it with a fresh, sterile one.
Toddler’s Swollen Knee Turned Out To Be Juvenile Arthritis Diagnosis: Signs Parents Should Not Ignore
Credit: AI
When Emily Hughes saw that her 18-month-old daughter, Scarlett, had a swollen knee in late 2023, she initially thought it might be an injury from the toddler’s routine playtime. Scarlett was energetic and adventurous, and the swelling did not appear to cause her pain.
But the swelling did not improve, and further examinations eventually led to a diagnosis of juvenile idiopathic arthritis (JIA), a chronic inflammatory condition that affects children.
Hughes, who lives in Australia, told Mamamia that several doctors initially found no cause behind her daughter’s symptoms. The situation changed in February 2024, when Scarlett’s knee became hot, painful and more severely swollen. She could no longer bear weight on the affected leg. “She wouldn’t bear weight, and it was even more swollen,” Hughes said.
Scarlett was taken to the Royal Children’s Hospital in Melbourne, where doctors initially thought it was septic arthritis, a serious joint infection. Investigations failed but the family continued consulting specialists.
By May, after other possible explanations got investigated, Scarlett was referred to a rheumatologist and diagnosed with juvenile arthritis affecting three joints.
Now four years old, Scarlett is in remission and has returned to physical activities like climbing and doing cartwheels. Her experience highlights why stubborn joint swelling and changes in a young child’s movement deserve emergency medical attention, even when the child is not in pain.
What Is Juvenile Idiopathic Arthritis?
Also read: Women And Arthritis: Why Risk Increases After 40
Juvenile idiopathic arthritis is the most common form of chronic arthritis in children. It refers to a group of several conditions in which the immune system triggers inflammation in the joints by mistake. Although genetic and environmental factors may contribute, the exact cause is unknown.
The condition can affect children younger than 16 and may involve one or several joints. The knees, ankles, wrists and elbows are commonly affected.
Unlike arthritis, JIA can begin during toddlerhood. Its symptoms may also be difficult to recognise as young children cannot always describe pain, stiffness or discomfort accurately.
There is no single test that confirms JIA. Doctors start by assessing the child’s symptoms, medical history and physical examination, and may use blood tests and imaging to investigate inflammation and rule out other conditions.
Signs Of Juvenile Arthritis Parents Should Not Ignore
According to the US National Institute of Arthritis and Musculoskeletal and Skin Diseases and the American Academy of Pediatrics, parents should watch for the following symptoms:
1. Continued joint swelling
A knee, ankle, wrist or other joint that remains swollen should be assessed on priority. In JIA, painless swelling may occur even when the child seems comfortable.
2. Morning stiffness
Children may struggle to move a joint after waking up or after sitting still for a long time. Stiffness may improve as they become more active during the day.
3. Limping or reluctance to walk
A toddler who starts limping, avoids putting weight on one leg or has difficulty walking may be experiencing joint inflammation.
4. Difficulty bending or straightening a joint
Limited movement is also one of the signs. A child may struggle to straighten an elbow, bend a knee or move a limb as freely as before.
5. Changes in play and everyday activities
A child who suddenly avoids climbing, running or playing, or struggles with activities they previously dud easily, may have pain or stiffness.
Some children with JIA may also experience fatigue, fever, rash or reduced appetite, depending on the type of disease. Untreated inflammation can damage joints and interfere with a child’s movement and development. Early diagnosis and treatment aim to control inflammation, maintain joint function and help children maintain their usual activities.
JIA can also affect the eyes. Some children develop uveitis, inflammation inside the eye that may cause no obvious symptoms initially but can threaten vision if left untreated. Regular eye examinations are therefore an important part of JIA.
Heart Health In Women After Pregnancy: Why Pre-Eclampsia And Gestational Complications Matter Years Later

Credit: AI
For every woman pregnancy is a beautiful and dream journey, but from the perspective of heart-health , it acts as a “natural stress test” for the body. The best part is most women recover completely after childbirth. However, certain complications such as preeclampsia, high blood pressure, gestational diabetes, preterm delivery, or poor fetal growth can sometimes be early warning signs of future cardiovascular risk.
As a cardiologist, I want women to know that preeclampsia does not simply end when pregnancy ends. It can signal a higher risk of high blood pressure, diabetes, heart disease and stroke later in life. Gestational diabetes also increases future cardiometabolic risk.
This does not mean you will develop heart disease. It means you have an opportunity to be proactive.
Also read: Maternal Immunisation: The Forgotten Half of Protecting a Baby's Health
What should be your postpartum action plan?
1. Check your blood pressure regularly, especially after preeclampsia or gestational hypertension.
2. Check blood sugar after gestational diabetes and continue recommended long-term screening.
3. Know your numbers: monitor cholesterol, weight and other cardiovascular risk factors.
4. Rebuild healthy habits: gradually return to regular exercise, eat a heart-healthy diet, avoid smoking and prioritise sleep.
5. Tell your doctor your pregnancy history—it is an important part of your lifelong heart history.
Your pregnancy may be over, but not your heart health journey, it continues for life time. Early awareness gives you the power to prevent problems before they begin.
By Dr. Sunil Kumar Mandal, MBBS, MD , DM (Cardiology), Senior Consultant Interventional Cardiologist
Maternal Immunisation: The Forgotten Half of Protecting a Baby's Health
Credit: Ai
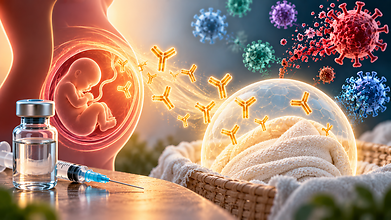
Vaccination during pregnancy protects more than just the mother. Vaccines such as Td, Tdap, and influenza (when recommended) help pass protective antibodies to the baby, providing valuable immunity during the first six months of life.
When people think about vaccination, they usually think about babies receiving their first vaccines after birth. However, an important part of a child's protection actually begins during pregnancy.
Maternal immunisation helps protect both the mother and her baby by allowing protective antibodies to pass through the placenta before birth. These antibodies provide the newborn with temporary immunity during the first few months of life, when the baby's immune system is still developing and routine childhood vaccines have not yet become fully effective.
Despite its importance, awareness about maternal immunisation remains low, with many women knowing only about the Td vaccine while being unaware of the benefits of Tdap and influenza vaccination when recommended.
What is maternal immunisation?
Maternal immunisation refers to vaccines that are recommended during pregnancy to protect the mother from certain infections while also passing protective antibodies to the unborn baby.
During the third trimester, these antibodies cross the placenta and help protect the newborn from serious illnesses during the first six months of life. This protection is especially important because young infants are more vulnerable to infections and cannot receive all vaccines immediately after birth.
Important vaccines during pregnancy
Td (Tetanus and Diphtheria): The Td vaccine is routinely recommended during pregnancy. It protects the mother against tetanus and diphtheria while also helping protect the newborn from neonatal tetanus.
Tdap (Tetanus, Diphtheria and Pertussis): In many situations, doctors may recommend the Tdap vaccine during pregnancy. It also protects against pertussis (whooping cough), a highly contagious infection that can be life-threatening for young babies. Vaccination during pregnancy allows antibodies to reach the baby before birth, reducing the risk of severe illness in early infancy.
Influenza (Flu) Vaccine: Pregnant women are at a higher risk of developing complications from influenza. When recommended by the treating doctor, the influenza vaccine helps protect both the mother and the baby during flu season.
Why it matters for the newborn
A newborn's immune system is still immature, making babies more susceptible to infections. The antibodies received from the mother act as the baby's first shield against disease until the infant starts receiving routine childhood vaccines and develops their own immunity. This early protection can reduce the risk of severe infections during one of the most vulnerable stages of life.
Tips for expectant mothers
• Discuss maternal vaccination during your first antenatal visit.
• Receive the Td vaccine according to your doctor's advice.
• Ask your obstetrician whether Tdap is recommended during your pregnancy.
• Take the influenza vaccine if advised by your doctor.
• Attend all scheduled antenatal check-ups.
• Maintain a healthy diet, adequate sleep, and good hydration during pregnancy.
• Encourage family members and caregivers to stay up to date with their vaccinations to help protect the newborn.
• Ensure your baby receives all routine childhood vaccines on time after birth.
By discussing vaccination early in pregnancy and following medical advice, expectant mothers can provide their newborn with valuable protection during the first six months of life, giving them a healthier and safer start.
- Follow Us :


© $2026 Times Horizon Private Limited