
- Health Conditions A-Z
- Health & Wellness
- Nutrition
- Fitness
- Health News
- Ayurveda
- Videos
- Medicine A-Z
- Parenting
How Antimicrobial Resistance Threatens Neonatal Mortality Rates Globally

How Antimicrobial Resistance Threatens Neonatal Mortality Rates Globally
Neonatal mortality remains a major health challenge across the world, which involves neonatal sepsis and other related factors of prematurity. Though many strides have been done in reducing NMR, there is a need for more appropriate interventions and strategies directed towards addressing the rise in the escalation of AMR. Combating AMR will be critical in improving neonatal survival rates while giving each newborn a healthier start into life globally.
The newborn period is the key period for infant health, and the first 28 days of life are critically important-both for survival and as a base to set lifetime health and development. Neonatal deaths globally have witnessed a significant decline over the past couple of decades. The neonatal mortality count has significantly reduced dropping from a high of 5 million in 1990 to as low as 2.3 million as of 2022. However, this decline notwithstanding, neonatal mortality is still staggeringly high across low-and middle-income nations.
Neonatal mortality rates are 22 per 1000 live births in India. Neonatal sepsis and prematurity are the main causes of neonatal deaths in these tragic events. Recognizing the gravity of the issue the Indian government started the Indian Newborn Action Plan (INAP) in 2014. The goal is to take NMR down to the single digits by 2030. This initiative has brought in several key interventions, including antenatal care (vaccines, micronutrient supplementation), skilled birth attendance, clean birth practices, and neonatal resuscitation techniques. More promisingly, postnatal interventions, including early initiation of breastfeeding and skin-to-skin contact, have been proven to work well in improving newborn survival rates.
Despite these improvements, one of the biggest concerns in neonatal care today is the growing problem of antimicrobial resistance (AMR) which seriously threatens efforts to reduce neonatal mortality.
What is Antimicrobial Resistance?
Antimicrobial resistance occurs when microorganisms such as bacteria, viruses and fungi evolve over time and become resistant to commonly used antibiotics and other medications. This resistance makes infections more difficult to treat, increasing the risk of mortality and complicating treatment options. The World Health Organization has classified AMR as one of the most urgent global health threats since it not only causes death and disability but also places immense pressure on healthcare systems, significantly raising the economic burden.
The sources of AMR are many, including poor hygiene and infection control in healthcare settings, overuse and misuse of antibiotics. Contributing factors to this rapidly growing problem are antibiotic prescriptions for patient needs that do not require them and failure to complete antibiotic courses, as prescribed.
AMR and Newborn Health
For neonates, the risk is much more vital for AMR. Neonates are particularly prone to developing infections due to their rather weak immune systems. Neonatal sepsis, severe bacterial infection, is one of the leading causes of neonate deaths and it often manifests complications when it is because of drug-resistant pathogens.
According to Dr. Apoorva Taduri, Consultant Neonatologist, "Neonatal sepsis accounts for a significant proportion of neonatal deaths, and AMR is making it worse. MDR pathogens cause around 30% of neonatal sepsis mortality globally.
Maternal health and care are also factors influencing AMR in neonates. Over-prescription of antibiotics during pregnancy increases the risk of neonatal sepsis and the development of multi-drug-resistant pathogens in newborns. This calls for prudent use of antibiotics during pregnancy and at the time of delivery. In fact, studies indicate that indiscriminate use of antibiotics in mothers has a direct impact on neonatal health, which may eventually lead to resistant infections in newborns.
One of the major issues is that the drug-resistant bacteria are causing an increasing number of healthcare-associated infections in the neonatal care settings, which include NICUs. Infections by such bacteria prove to be challenging to treat; they require more advanced, expensive interventions, and the period of risk of mortality and morbidity is extended.
Counteracting AMR in Neonatal Care
To combat AMR and reduce neonatal mortality a multifaceted approach is necessary. Dr. Taduri emphasizes the continuation of the strategies outlined by the Indian Newborn Action Plan (INAP), specifically in reducing neonatal sepsis and improving infection control. However, to combat AMR more must be done to ensure proper use of antibiotics in both maternal and neonatal care settings.
Key strategies for reducing AMR in neonatal care are:
1. Improving Infection Prevention Practice: This implies, therefore, that more efforts would be made regarding stricter hospital hygiene standards, strict equipment sterilization after its usage and even maintaining adequate hand hygiene. Enhanced infection control practices greatly impact minimizing AMR pathogens distribution.
2. Antibiotic Stewardship- Teaching the healthcare providers how not to use antibiotics is a crucial thing in preventing overuse prescription. Antibiotic stewardship programs are designed to promote use of antibiotics only when truly required; appropriate drug, dose and length of treatment should be taken.
3. Improved access to WASH: Access to clean water and sanitation is a fundamental aspect of preventing infections in mothers and newborns. WASH interventions such as clean birthing practices, can reduce the risk of neonatal sepsis due to unsanitary conditions.
4. Maternal Health Strengthening: Proper maternal care, such as proper vaccination, antenatal steroids, and supplementation of micronutrients, can reduce the risk of prematurity and neonatal infection. Prevention of infection in mothers is the first step towards prevention of infection in newborns.
5. Early Diagnosis and Treatment: Early identification and treatment of neonatal infections are very important. This includes proper screening for sepsis and the use of appropriate antibiotics based on the local resistance patterns. It also involves ensuring that infants receive adequate neonatal care, such as those provided in Special Newborn Care Units (SNCUs).
The rise of antimicrobial resistance is a global health challenge that requires urgent action. Combating AMR requires a coordinated effort from governments, healthcare systems and communities worldwide. In neonatal care, addressing AMR is essential to further reducing neonatal mortality rates and ensuring that every newborn has the opportunity to thrive.
As Dr. Taduri concludes, "While we have made substantial progress in reducing neonatal mortality, the emerging risk of antimicrobial resistance creates a major challenge for our efforts. Combating AMR requires a global collective effort, with priorities on infection prevention, responsible use of antibiotics, and enhancement of healthcare practices to ensure a healthier future for all newborns."
Dr Apoorva Taduri is a Consultant Neonatologist at Fernandez Hospital
Childhood Allergies: Why Different Symptoms May Share A Common Cause
Credit: AI
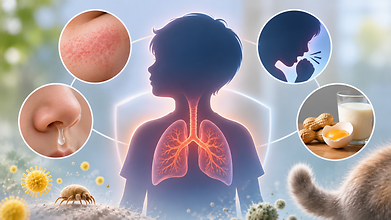
Childhood allergies rarely present as isolated issues. While one child may experience itchy skin and rashes, another may complain of a perennial runny nose and some wheeze a lot with infections, and yet others present with food-related symptoms. Although these are distinctly different manifestations, they could have a single root cause.
What Causes Allergies In Children?
Childhood allergies are basically an inappropriate immune response towards a substance that usually presents no harm, be it a food item or an allergen in the environment. However, it is not always easy to pick out what is causing the allergic response. The child's medical history as well as the nature and accompanying circumstances of the reaction, play a pertinent role in picking out what is precipitating the problem.
Two children may present with similar complaints but have different underlying allergic conditions. Understanding the pattern of the disease helps decide what investigations are needed and how best the condition can be managed.
Also read: In-Toeing In Children: When It Needs Assessment
How Allergies Can Affect Multiple Body Systems
Allergic diseases can affect multiple body systems. The most common are the skin, upper respiratory tract and the lower respiratory tract. Skin allergy manifests as atopic dermatitis or urticaria, upper respiratory tract can cause allergic rhinitis and conjunctivitis and lower respiratory tract can manifest as asthma.
There are also food allergies which could present with gastrointestinal symptoms or even more serious reactions. A child may also face multisystem involvement and this can sometimes be life-threatening like in a case of anaphylaxis.
Understanding The Role Of Type 2 Inflammation
Allergic disorders may present with multisystem involvement due to the fact that type 2 inflammation is a key driver in the pathology. Cytokines such as IL-31, IL-13 and IL-5 are integral to the formation of IgE antibodies and the activation of eosinophils. Genetic predisposition, skin barrier dysfunction, environmental exposure and the gut microbiota also contribute towards the development of allergies.
There is usually an evolution of allergic diseases as a child grows older. This is commonly referred to as the atopic march. It is common for a child to present with atopic dermatitis and then develop food allergies, allergic rhinitis or asthma later on in life. However, this is not always the case, and an allergic disorder cannot be extrapolated to the presence of any other based on this association alone.
Awareness to these associations can help parents and doctors to watch out for developing conditions and ensure early and appropriate intervention. For example, in a child presenting with persistent eczema, investigation for associated allergic disorders is vital if the history supports it. Early diagnosis and management can also help the parents identify red flags and seek help sooner.
How Are Childhood Allergies Diagnosed?
A thorough clinical history is an extremely valuable tool when it comes to diagnosing allergies. It is important for the doctor to know what the likely allergen was, how soon after exposure the symptoms cropped up, whether similar symptoms have occurred before, and what body systems are involved.
The timing of the reaction and whether it is a one-off or recurrent episode is important. A reaction occurring minutes after ingesting a certain food is very different from a food that causes symptoms after days of consumption.
Treatment And Management Of Allergies In Children
Skin prick tests and specific IgE blood tests are commonly used to screen for sensitisation to common allergens, but these are just pointers. A positive test does not necessarily signify a clinically relevant allergy. The symptoms and exposure history must always be taken into consideration.
Testing for specific IgE to a panel of foods without a clear indication is not only misleading but can also be harmful. Parents may unnecessarily eliminate food groups from the child's diet based on a positive test, thereby affecting nutrition. Similarly, total IgE levels are not helpful in diagnosing a specific allergy.
The treatment varies from managing acute symptoms (with antihistamines or steroids) to controlling chronic conditions (with regular inhaled steroids for asthma). Avoiding the allergen where possible, and treating flare-ups appropriately are the cornerstones of management. Immunotherapy with allergen extracts may be indicated in selected patients with respiratory allergies. Biologics may be considered in certain conditions under specialist supervision.
Why Childhood Allergies Need A Holistic Approach
Children at risk of anaphylaxis should have a personalised action plan and an epinephrine auto-injector available at all times.
Childhood allergies should not be managed in isolation. The focus should be on the child as a whole rather than a single presenting complaint. Awareness and management of any associated conditions can help prevent potentially serious complications.
By Dr Gargi Mathur, Senior Paediatrician, Shalby International Hospitals, Gurugram
In-Toeing In Children: When It Needs Assessment
Credit: AI
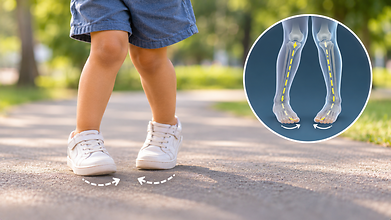
Parents may notice that a child’s feet point inward while walking or running. This is called in-toeing. It is common in young children and, in most cases, reflects normal development of the foot or leg bones. Many children improve naturally as they grow, without treatment.
However, it is not always helpful to dismiss a persistent or troublesome walking pattern as “just a growing phase.” The child’s age, the cause, whether the pattern is worsening, and its effect on movement all matter.
What can cause in-toeing?
In-toeing usually comes from one or more of three areas:
1)Foot: The front of the foot curves inward, a condition called metatarsus adductus. Flexible cases often improve naturally.
2)Shin: The shin bone turns inward, called internal tibial torsion. This is common in toddlers and usually improves with growth.
3)Thigh: The thigh bone turns inward, called femoral anteversion. It may become more noticeable when a child begins running or walking with the feet turned in.
The appearance of the feet alone does not always reveal the cause. A clinician can assess the child’s walking pattern and examine the hips, knees, shins and feet.
Also read: Hailey Bieber Opens Up About PMDD After Childbirth: What Is It And How Is It Different From PMS?
When should parents seek advice?
An occasional inward-pointing step, without pain or difficulty, usually needs observation rather than treatment. Arrange an assessment if the child:
- Trips or falls often, or has difficulty running, jumping or keeping up with peers.
- Avoids play or sports because of the way they walk.
- Has pain, swelling, a limp or difficulty bearing weight.
- Has a marked difference between the two legs.
- Develops a new or rapidly worsening walking pattern.
- Has a foot that is rigid or cannot be gently moved toward a straight position.
- Pain, limping, sudden onset, or marked asymmetry are reasons to look beyond a routine developmental variation.
What does assessment involve?
The clinician will ask when the in-toeing began, whether it is changing, and whether it affects daily activities. They will observe the child standing and walking, and assess foot flexibility, hip and leg rotation, balance and function.
X-rays are not routinely needed when the history and examination fit a typical developmental pattern. They may be considered if there is pain, trauma, unusual examination findings or concern for another condition.
Does every child need physiotherapy, special shoes or braces?
No. For typical, painless developmental in-toeing, reassurance and observation are usually appropriate. Special shoes, braces and orthotics do not correct the usual rotational causes. Physiotherapy may help when there is a separate issue—such as weakness, balance difficulty or impaired coordination—but it does not generally change the underlying bone rotation.
If in-toeing is severe, persistent and causing substantial functional difficulty, a paediatric orthopaedic specialist can advise whether further evaluation or treatment is appropriate. Surgery is rarely needed and is generally considered only for older children with severe deformity and significant functional problems.
A practical message for parents: Most children with in-toeing walk and play normally, and their alignment improves as they grow. The aim is not to make every child’s walking look identical; it is to ensure the child moves comfortably and safely. Seek an assessment for pain, limping, sudden change, pronounced asymmetry or meaningful difficulty with everyday activities.
Hailey Bieber Opens Up About PMDD After Childbirth: What Is It And How Is It Different From PMS?

Credit: Instagram
Model and entrepreneur Hailey Bieber recently opened up about her postpartum journey, shifting focus on one of the least-discussed aspects of women’s health: premenstrual dysphoric disorder (PMDD).
Hailey said that she experienced PMDD after the birth of her son, Jack Blues Bieber. It is a menstrual health condition that can cause intense emotional and physical symptoms.
In an interview with Women's Wear Daily, Bieber spoke about how motherhood drew her towards women's health, especially considering the challenges she faced after childbirth.
"After I had my son, I struggled with [PMDD] a bit, and there's just not a lot of conversation or research around it," she said.
Bieber, who welcomed her son with husband Justin Bieber in August 2024, had previously discussed her diagnosis during an appearance on the SHE MD podcast in March 2026. She said she was diagnosed approximately six months after giving birth.
Although she had experienced premenstrual syndrome (PMS) before pregnancy, she noticed that the emotional symptoms leading up to her period had become much more intense.
"I was like, 'This just feels way more intense than before,' like, the lead-up to getting your period," she said.
She said she experienced overwhelming emotions, adding, “Why does it feel like my whole entire life is gonna end? Like, I don't understand.”
Bieber said her symptoms gradually improved over time. She also highlighted how speaking about her experience helped her feel less isolated. "Conversation, for me personally, makes me feel less alone," she said.
What Is Premenstrual Dysphoric Disorder (PMDD)?
Also read: 8 Signs Of 'Pregnancy' That Are Likely PMS
Premenstrual dysphoric disorder is a severe form of premenstrual syndrome (PMS) that causes intense emotional, mental and physical symptoms during the days leading up to menstruation.
By Dr Sushma K, Obstetrics, Gynecology and Reproductive Medicine, Apollo Hospitals, Seshadripuram, Bangalore told HealthandMe, "It is a chronic medical condition related to the menstrual cycle. It affects approximately around 3 to 8 percent of the women who are menstruating. So it not only causes physical symptoms, like premenstrual syndrome, it also causes emotional and psychological symptoms. It typically occurs one or two weeks before menstruation starts."
Unlike premenstrual syndrome, PMDD can significantly interfere with a person's ability to work, relationships, social life and other daily activities. When it comes to symptoms, patients can have sudden onset of sadness, increased sensitivity, or tearfulness, sudden spells of crying, severe irritability, anger, depressed mood and anxiety.
Dr Sushma said, "These emotional symptoms can also have physical manifestations. For example, decreased interest in going to school, office, and difficulty concentrating. Some may resort to overeating. Some may have excessive sleepiness or some may face insomnia. Some also experience restlessness, discomfort, joint swelling, muscle pain, and abdominal bloating.”
PMDD Vs PMS
Also read: The Menstrual Cycle and Nutrition: Does Your Body Really Need Different Foods at Different Times?
PMS and PMDD are both caused due to hormonal changes in the menstrual cycle. However, the intensity of symptoms and their effects on daily life distinguish the two conditions.
Dr Sushma said, "PMS is a mild to moderate condition and it can be easily managed. It comes with physical symptoms like bloating, breast pain, tiredness, and mood changes. It also does not interfere with people’s daily routine and relationships. It occurs in almost around 75% of the people who are menstruating."
PMDD symptoms can be more severe, especially depression, anxiety, irritability and emotional distress. These symptoms can disrupt work, relationships and everyday functioning.
She added, "But PMDD is more severe. It will impair daily life. It also causes more intense psychological and emotional symptoms than physical symptoms."
So PMDD is not just an extreme version of a bad premenstrual week. It is a recognised health condition that may require medical treatment.
Why Does PMDD Happen?
Experts say that the exact cause of PMDD is not fully understood yet. But they believe it may be due to an increased sensitivity to normal hormonal changes during the menstrual cycle.
After ovulation, levels of hormones like oestrogen and progesterone fluctuate. In some individuals, the brain may respond differently to these hormonal changes, affecting mood regulation and other bodily functions. Serotonin, a neurotransmitter involved in regulating mood, sleep and appetite, may also play a role.
Dr Sushma explained, "PMDD is a very severe depressive disorder. Patients may have panic attacks, depression, and thoughts of self-harming. So these are the key main important differences. PMDD may happen because of disrupted dysfunctions in the central nervous system during the menstrual cycle. That is because of how the central nervous system reacts to the normal estrogen and progesterone levels during the menstrual cycle.”
PMDD In New Mothers
Hailey Bieber's experience has sparked conversation about PMDD risk after childbirth. Pregnancy, childbirth and the postpartum period involve significant hormonal and physical changes.
However, PMDD is linked to the menstrual cycle and its recurring hormonal fluctuations. The return of menstrual cycles after childbirth may make premenstrual symptoms intense. However, there is limited evidence establishing that childbirth directly causes PMDD.
Dr Sushma said, "New mothers may not face premenstrual dysphoric disorder because there is no ovulation. The lady is not menstruating because she is lactating. But once the ovulation starts, the symptoms of PMDD will return. These symptoms can worsen because the mother is sleep deprived or she faces a lot of hormonal changes. There is also a newborn. So the baby’s care-giving also adds to the stress. So PMDD may get aggravated in new mothers."
PMDD should also not be confused with postpartum depression. Postpartum depression can occur after childbirth and is not restricted to the days before menstruation.
The doctor explained, "Postpartum depression is not cyclical. Whereas PMDD will come in a cyclical manner, mostly 10-12 days before periods, which is usually in the luteal phase. Also, it may resolve after the bleeding starts.
Whereas postpartum depression is not related to the menstrual cycle."
- Follow Us :


© $2026 Times Horizon Private Limited