
- Health Conditions A-Z
- Health & Wellness
- Nutrition
- Fitness
- Health News
- Ayurveda
- Videos
- Medicine A-Z
- Parenting
11 Ways To Know If Your Baby Is Hungry?

Credits: Canva
You have just changed your baby's diaper, and went to bed, to finally rest. Suddenly, you hear a loud wail. Your baby is crying, again! This time, it is the hungry cry.
But what if we tell you that you no longer have to disrupt your rest with your baby's cry for hunger? This is only possible when you already know when to feed your baby. Babies cannot tell when they are hungry, so more often than not, parents may miss to understand they are hungry, until the hunger cry starts. But there are some cues you can look for to feed your baby!
Hunger Cues In Your Baby
Increased Activity
Your baby might become more alert and active. Thinking about food can make babies excited, so you may notice them moving around more than usual.
Head-Turning
Babies often turn their heads from side to side as if searching for food.
Mouth Movements
Look for signs like opening and closing their mouth, resembling a tiny bird waiting to be fed.
Rooting Reflex
Turning their head toward the breast, chest, or bottle is a classic hunger cue.
Sucking Motions
Babies may make sucking motions with their mouths, even if they don’t have a pacifier or bottle nearby.
Lip Smacking or Drooling
Increased drooling, lip-smacking, or sticking out their tongue are all signals they’re getting ready for a meal.
Sucking on Hands or Clothing
Your baby might start sucking on their fingers, hands, or even their clothes as a sign of hunger.
Clenched Fists
Watch for little fists clenching in frustration and impatience.
Focused Eye Contact
Babies who recognize their primary feeder might stare and follow you around the room with their eyes.
Facial Expressions
A furrowed brow or a distressed look might be your baby’s way of saying, “When’s the next meal?”
The “Neh” Sound
According to Dunstan baby language, the sound “neh” just before crying often means hunger.
Also remember that hunger pangs are strong enough to wake most babies, even from deep sleep. However, if your baby consistently sleeps for extended periods, it’s important to ensure they’re feeding frequently enough for their age.
For newborns, it’s generally recommended that they don’t regularly sleep longer than 4 hours at a stretch. Occasional long naps are fine—especially if they give you a much-needed rest! However, if your baby frequently sleeps through feeding times, consult your pediatrician to determine if gentle wake-ups for feeding are necessary.
How do you know your baby is feeding well enough?
It can be difficult to ensure that your baby is well fed, especially if you are breastfeeding, or when your baby is not of the age when he can talk. However, there are signals too for this, in fact your baby also learns how to signal that they need more milk or food.
It also depends on the age. For instance, a newborn will feed often, usually every 2 to 3 hours and sometime smore often. They feed up to 12 times every 24 hours. As your baby grows, their tummies grow too, in fact the tummy grows form a size of cherry at birth to walnut in 3 days. In a week, it is at the size of plum and in a month, it is of the size of a large chicken egg.
The "I am not hungry right now" signs for babies are:
- releasing or pushing away the breast or bottle
- closing their mouth and not responding to encouragement to latch on or suck again
- open and relaxed hands (instead of clenched)
- relaxing their body and even going a little limp
- looking around and showing interest in playing or other things
- looking content and maybe even smiling
- appearing happily drowsy and ready to go back to sleep
Pertussis Vaccine Cuts Whooping Cough Risk By 96% In Young Children: US CDC Study
Credit: iStock
The pertussis vaccine, which protects against whooping cough (Bordetella pertussis), a highly contagious bacterial respiratory infection, offers strong protection in young children, according to a new study led by the US Centers for Disease Control and Prevention (CDC).
Published in the CDC’s Morbidity and Mortality Weekly Report (MMWR), the study found that children who received three or more doses of the diphtheria, tetanus, and acellular pertussis (DTaP) vaccine had 96.2% protection against laboratory-confirmed pertussis.
Pertussis Vaccine Offers Strong Protection
The DTaP vaccine is administered in a five-dose childhood series. The first dose is given at 2 months of age, followed by doses during infancy and early childhood. The final dose is recommended between ages 4 and 6 years.
The MMWR study compared children in Alaska who had received three or more DTaP doses with those who were unvaccinated or had received fewer doses than recommended.
Unvaccinated children had approximately 26 times the odds of developing laboratory-confirmed whooping cough compared with vaccinated children.
Overall, adjusted vaccine effectiveness against pertussis was 96.2% among children who had received three or more DTaP doses. Partial vaccination also offered protection, with effectiveness reaching 85.3% among children who had received one or two doses.
“Pertussis vaccination is effective in preventing laboratory-confirmed pertussis in young children,” said corresponding author Joseph McLaughlin of the Section of Epidemiology, Alaska Department of Health, Anchorage.
Also read: RSV Warning: Welsh Mum Urges Pregnant Women To Get Vaccine After Baby Nearly Dies
Whooping Cough Can Cause Severe Complications
Pertussis can cause serious complications in young children, including pneumonia, pauses in breathing (apnea), seizures, brain damage, and death. Severe coughing fits can also trigger vomiting and, in some cases, fractured ribs.
Infants younger than 6 months are particularly vulnerable because their immune systems are still developing. Babies may not develop the characteristic “whoop” sound and can instead experience feeding difficulties or pauses in breathing, making the infection harder to recognize.
According to a provisional CDC report, 16 people died from pertussis in the United States in 2025, including 10 infants.
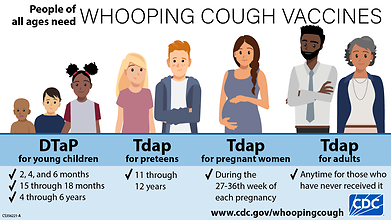
Whooping cough spreads through respiratory droplets and can affect people of any age. However, newborns and people who are not adequately vaccinated face a greater risk of severe illness.
Previous research has also found that unvaccinated children are more likely to develop severe illness or require hospitalization than vaccinated children.
Childhood Vaccination Rates Have Declined In The US
Read More: US Kindergarten Vaccination Rates Decline, Exemptions Rise as Measles Cases Hit 35-Year High
Despite the protection offered by vaccination, DTaP coverage among US kindergartners has declined in recent years.
CDC data show that coverage fell to 92% in the 2025–26 school year, down from 95.2% in 2017–18.
The findings underscore the importance of maintaining high childhood vaccination coverage to reduce pertussis infections and protect children against severe illness and death.
Identifying Whooping Cough Symptoms
Whooping cough often begins with cold-like symptoms, including a runny nose, sneezing, a mild cough, and sometimes a low-grade fever. After one to two weeks, coughing fits may become more severe and persistent.
The cough can be followed by a characteristic whooping sound as the person gasps for air. Vomiting after coughing fits can also occur. However, symptoms vary, particularly in infants, who may experience breathing difficulties without a typical cough.
Diagnosis may involve laboratory testing of a nasal or throat sample. Early recognition is especially important in infants because the infection can progress to serious complications.
HSV Kills 10-Day-Old Baby In UK: Mother Warns Of Little-Known Danger Of Cold Sores

Credit: iStock
Herpes simplex virus (HSV), which commonly causes cold sores, usually causes mild symptoms in adults but can be life-threatening in newborns, whose immune systems are still developing.
Meg Edmonds, from Staffordshire, UK, lost her 10-day-old daughter, Magnolia, to HSV in February.
“We didn't know a cold sore could kill a baby,” Meg told the BBC. She is now urging parents to learn about the risks cold sores pose to newborns.
The virus is suspected to have been passed on to Magnolia by her mother.
“The guilt is obviously unbearable; it's horrific, but I just try and remind myself that I didn't know and I did what I could have done with the knowledge that I did have,” Meg said.
Mother Did Not Know Cold Sores Could Endanger Newborns
Also read: Rare Pregnancy Infections Linked To 3-Fold Higher Autism Risk: What Is TORCH?
The 22-year-old said Magnolia was born “perfectly healthy” after what she described as a straightforward “water birth”.
Only later did Meg realise she had a sore on her lip around the time of the birth.
“Looking back at photos now, I can see that I had a lesion or sore on my lip whilst I was giving birth which I thought nothing of at the time,” she said.
Meg, who had never experienced a cold sore before, sought advice from health professionals but was reassured that the sore was nothing to worry about.
“They just thought that I might need to drink more or that it might just have been hormonal from giving birth only the day prior, so I thought nothing of it,” she said.
Magnolia's condition later deteriorated, and she died from HSV, according to the report.

Cold Sore Outbreak Brings Back Painful Memories
Meg said she had avoided visitors who were unwell, never kissed Magnolia and washed her hands frequently to protect her newborn from infections.
“I washed my hands constantly because I was worried in general about infections. But I never knew that if that passed to her it could kill her,” she said.
A subsequent cold sore outbreak brought back painful memories.
“I'm constantly reminded anyway that my daughter isn't here any more and why that is, but to actually have a physical reminder on my face is horrible,” she said.
How To Protect Newborns From HSV
Read More: Baby Not Sitting by 9 Months? Warning Signs Parents Should Know
According to the UK's National Health Service (NHS), newborns are particularly vulnerable to HSV, especially during the first six weeks of life. The infection can affect the eyes, mouth and skin or spread to other organs, potentially becoming life-threatening.
HSV can spread after birth through contact with a cold sore, including when someone with an active cold sore kisses a baby. It can also spread through herpes blisters on the breast during breastfeeding.
The NHS recommends these precautions to reduce the risk of infection:
- Wash hands: Wash hands thoroughly before handling a newborn.
- Avoid kissing: People with an active cold sore should not kiss a baby.
- Prevent direct contact: Keep cold sores and other herpes lesions away from the baby.
- Take care during breastfeeding: Do not breastfeed from a breast with herpes blisters until they have healed. Seek medical advice about feeding and expressed milk from the affected breast.
- Inform healthcare professionals: Pregnant women with a history of genital herpes or symptoms of a possible infection should inform their doctor or midwife.
Warning Signs Of Neonatal Herpes
Babies may not develop visible blisters, and neonatal herpes can progress rapidly. Seek urgent medical attention if a newborn has:
- Unusual irritability or difficulty settling.
- Poor feeding or feeds less than usual.
- A fever of 38°C or higher.
- A rash or sores on the skin, eyes or inside the mouth.
- Unusual lethargy, floppiness or difficulty waking.
- Breathing difficulties or seizures.
Flu & COVID-19 Linked To 90% Of Cases Of Rare, Life-Threatening Brain Disease In Children: Study
Credit: AI
Influenza and COVID-19 may trigger a rare but fatal brain condition in children, according to a new study published in Frontiers in Neurology.
Based on 138 reported cases of acute necrotizing encephalopathy (ANE), the research is built on 15 studies involving children under 18 diagnosed with ANE following respiratory viral infections.
ANE can cause rapid neurological deterioration, seizures and damage to deep structures of the brain, even in children who were previously healthy.
Influenza viruses accounted for 46% of the reported cases, while SARS-CoV-2, the COVID-19 virus, accounted for 42.3%. Together, they represented nearly 90% of the cases in the review.
The findings highlight the need to recognise neurological symptoms that develop after a child has a fever or respiratory infection.
However, ANE remains rare, and the study does not suggest that most children with flu or COVID-19 are at risk of developing the condition.
Flu And COVID-19 Accounted For Most Reported Cases
Influenza viruses were identified in 63 cases, while SARS-CoV-2 was identified in 58. Another 17 cases were linked to unspecified respiratory viral infections.
The findings suggest that influenza and COVID-19 are key reported triggers of ANE. However, the researchers cautioned that the studies were observations, and the findings cannot establish how often ANE develops among children infected with either virus.
Also read: Swimmer Archie Goodburn’s Plea Prompts UK Brain Cancer Research Review
What Is Acute Necrotizing Encephalopathy?
Acute necrotizing encephalopathy is a rare neurological disorder in which inflammation and tissue injury cause damage to the brain. It is mostly linked with a respiratory viral infection.
The condition is characterised by lesions in the thalami, two structures deep inside the brain that help process sensory information and regulate functions like alertness.
In some children, damage also affects the brainstem and other regions. Rather than the virus directly destroying brain tissue, an excessive inflammatory response may disrupt the blood-brain barrier, allowing inflammation to damage the brain.
Symptoms of Acute Necrotizing Encephalopathy
ANE usually starts with symptoms of the initial viral infection, like fever, cough, vomiting, and diarrhea, followed by rapid neurological decline, which may include:
- Seizures
- Confusion, drowsiness, and altered consciousness
- Coma lasting for weeks
- Problems with movement (ataxia)
- Abnormal muscle tone
One of the most concerning features of ANE is how quickly a child's condition can worsen after a febrile illness.
In the reviewed cases, fever was reported in 93.4% of children, altered consciousness in 94.9% and seizures in 68.6%. These figures describe children who had ANE, not all children with respiratory infections.
These symptoms require emergency medical assessment. Parents should not wait for a fever or other infection symptoms to resolve if a child develops seizures, confusion or reduced consciousness.
Mortality Rate Of ANE
Despite treatment, the outcomes reported in the study were serious. Of the 138 children included in the review, 54 died, giving a reported mortality proportion of 39.1%.
Survivors also experienced neurological complications, including problems affecting movement, cognition and development.
It is important to note that the study included published cases of a rare and severe disease, which may overrepresent children with particularly serious illness. It is not a population-wide estimate of the risk of death from ANE. Brain imaging like MRI can help doctors identify the characteristic lesions associated with the condition.
- Follow Us :


© $2026 Times Horizon Private Limited