
- Health Conditions A-Z
- Health & Wellness
- Nutrition
- Fitness
- Health News
- Ayurveda
- Videos
- Medicine A-Z
- Parenting
10 Surprising Facts That You Did Not Know Around Pregnancy
Credits: Canva
Pregnancy is a life-transforming journey and while there is so much changes that happens during this time, you cannot always be prepared for everything. Here are 10 surprising facts that you did not know were true during pregnancy.
The Nesting Instinct
If you have seen animals look for paper scraps, or take fur out of their own body or collect small twigs and stem to build a nest for their upcoming babies, even if the animals are domesticated, humans do the name. Humans do not take fur or hair out of their body, but we too experience a powerful urge to prepare our home for the baby. We clean it, decorate it and thanks to modern homes, we can now baby proof it do!
Mommy Brain
This happens in the first trimester, when tiredness, morning sickness and other symptoms can make the mother feel worn out and mentally fuzzy, often called the mommy brain. The National Institutes of Health also notes that cognitive function decline in the third trimester of pregnancy, leading to memory problems.
Mood Swings
Premenstrual syndrome (PMS) and pregnancy share several symptoms, such as breast swelling and tenderness, hormonal fluctuations, and mood swings. If you’ve experienced severe mood swings due to PMS, you may notice an intensification of these emotions during pregnancy. It's common to feel joyful one moment and tearful the next as your body adjusts to hormonal changes.
Breast Growth
An increase in breast size is one of the earliest signs of pregnancy apart from your missed period. It happens in the first trimester due to the higher levels of hormones like estrogen and progesterone. The growth continues throughout pregnancy.
Skin Changes
Have you heard about pregnancy glow? This happens because pregnancy women have an increased blood volume, this happens to provide extra blood flow to the uterus and other organs, especially the kidneys. This greater volume brings more blood to the vessels and increases oil gland secretion.
Hair and Nails
During pregnancy, many women notice changes in their hair texture and growth. Hormonal shifts can make hair grow faster and reduce hair loss. However, these changes are typically temporary, and many women experience some hair loss during the postpartum period or after they stop breastfeeding. In some cases, hair growth may also occur in unexpected areas like the face, belly, or around the nipples. Additionally, hair texture can shift, becoming drier or oilier, and some women even notice a change in hair color.
Nails can also undergo changes during pregnancy. Increased hormone levels may cause nails to grow faster and become stronger, but for some women, nails may become more brittle, splitting and breaking more easily. Like hair changes, these nail changes are usually temporary. If your nails are more prone to splitting or tearing, it’s helpful to keep them trimmed and avoid exposure to chemicals in nail polish and nail polish remover.
Your Feet Grow
If you have heard about it, then you already know that it is not just the clothes that do not fit you, it is your shoes too. Extra fluid in the pregnant body also leads to swollen feet. The joints also tend to be looser during pregnancy.
Joint Mobility
Your body also releases hormones like relaxin that prepares your body, especially the cervix for the birth. This loosens the ligament in your body, which may make you less stable .
Varicose veins, constipation, and hemorrhoids
Varicose veins, common in the legs and genital area during pregnancy, result from blood pooling in veins enlarged by pregnancy hormones. They often disappear after delivery. To prevent them, avoid prolonged sitting or standing, wear loose clothing and support hose, and elevate your feet when seated.
Hemorrhoids, which are varicose veins in the rectum, may develop due to increased blood volume and uterine pressure. They can cause pain, itching, bleeding, or stinging, especially during bowel movements. Constipation, caused by hormonal changes and uterine pressure on the large intestine, can worsen hemorrhoids by straining during bowel movements.
Prevent constipation and hemorrhoids by eating a fiber-rich diet, staying hydrated, and exercising regularly. If needed, consult your doctor about stool softeners, laxatives, or creams for relief.
Labor and what goes out of your body
When you are in labor, your amniotic sac, that has fluid that surrounds the baby, breaks or ruptures, which is what is also known as water breaking. For most women contractions start before their water breaks, if not, then the doctor may have to rupture the amniotic sac, in case the cervix is already dilated. Some women may feel the urge to pee, while for some it may feel a trickling their leg.
Galactagogues: Natural Ways To Support Breast Milk Production

Credit: iStock
Breast milk is the best source of nutrition for infants, providing essential nutrients and immune protection that support healthy growth and development. Breast milk ensures the required nutrition and immune protection for the child.
Certain maternal and birth-related factors, such as prolonged or complicated labour, caesarean delivery, postpartum complications, maternal illness, and delayed initiation of breastfeeding, may contribute to delayed onset of lactogenesis II (the onset of copious milk production).
Late onset of milk production may lead to the discontinuation of breastfeeding in the early stages and result in increased weight loss in the baby and the need for formula feeding.
Galactagogues, also called lactagogues, are substances that are believed to support milk production through various mechanisms. Some may influence hormones involved in lactation, including prolactin, although their exact mechanisms and effectiveness vary. They affect milk production in a physiological way. The most effective lactagogue is suckling. There are galactagogues, which increase milk production and can be taken through diet.
What Are Galactagogues
The word “galactagogue” is derived from the Greek words galacta, meaning milk, and agogos, meaning leading or promoting. They may be medicines or natural products such as food and herbs. Galactagogues work by influencing the hormones responsible for promoting milk production, which include prolactin (PRL).
Natural galactagogues have been used for a very long time to facilitate the production of breast milk. They are proven to be both safe and effective even though there is insufficient scientific evidence regarding their efficacy.
How Do Galactogogues works?
The exact mechanism of action of many natural galactagogues is not fully understood. Lactation is regulated by several factors and hormones. Prolactin plays an important role in milk synthesis, while oxytocin is responsible for the milk-ejection or let-down reflex. Some substances may influence hormonal pathways, including prolactin secretion; however, the mechanisms and clinical effectiveness of many herbal galactagogues remain uncertain.
Foods That Support Milk Production
Fenugreek Seeds
Fenugreek is one of the most commonly used herbal galactagogues. Some studies suggest that it may support milk production; however, evidence remains limited and inconsistent. It may also cause side effects such as gastrointestinal discomfort, diarrhoea, sweating, or a maple syrup-like odour of sweat and urine in some individuals.
Garlic
Garlic has been used as a natural lactation booster since ancient times. Garlic is one of the most effective functional foods that help enhance breast milk production. The aroma of garlic gets passed into breast milk and can help prolong the sucking time of babies and even affect their food choices later in life.
Fennel seeds
The consumption of fennel seeds works as a galactagogue by inducing the secretion of prolactin through the mechanism of a dopamine antagonist. These include anethole, a natural plant substance having estrogenic effects that assist in signaling the production of milk.
Barley
Barley contains beta-glucan, a type of soluble fibre. Some preliminary research suggests that beta-glucan may influence prolactin levels; however, more research is needed to determine whether barley consumption directly increases breast milk production. Barley contains gluten and should be avoided by individuals with coeliac disease or gluten-related disorders as advised by their healthcare professional.
Shatavari
It is rich in folic acid, vitamins A, C, and K, as well as phytoestrogens, which play a role in hormone regulation in relation to milk production, just like estrogen. Some of the factors regulating prolactin secretion are estrogens, which promote the growth of prolactin-secreting cells, enhance prolactin secretion, and reduce dopamine concentration. Tryptophan is another constituent that is known to be an essential amino acid that may increase prolactin secretion.
Drumstick leaves (Moringa)
Moringa (Moringa oleifera) leaves are traditionally used to support lactation and are also nutritionally rich. Some small studies suggest a possible benefit in supporting milk production, but further high-quality research is required to establish its effectiveness and optimal use.
Cumin seeds (Jeera)
Cumin seeds are commonly used as a culinary spice and have traditionally been included in postpartum diets. However, scientific evidence specifically supporting cumin as an effective galactagogue is currently limited. The plant has been found to contain estrogenic properties because of the increased development of mammary glands and hence milk production.
Ginger
Ginger is widely used as a culinary spice and has been traditionally included in postpartum diets. Limited research has explored its potential role in supporting lactation; however, there is currently insufficient evidence to confirm its effectiveness as a galactagogue.
Conclusion
Galactogogues have become a subject of increasing interest as an emerging field of study, as herbs and spices have been extensively used traditionally to increase milk production. While some plants have traditionally been used as galactogogues over many years, there is still little scientific information on their efficacy and safety, which varies depending on the specific herb.
Some research indicates possible effects, but additional high-quality research is required to prove their efficacy, safety, and mode of action. Therefore, galactagogues should be viewed as an auxiliary measure rather than a replacement for consistent and efficient breastfeeding and proper diet.
Childhood Allergies: Why Different Symptoms May Share A Common Cause
Credit: AI
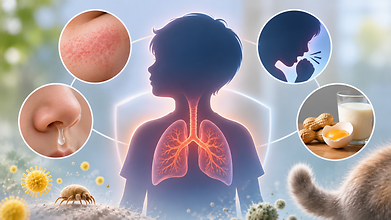
Childhood allergies rarely present as isolated issues. While one child may experience itchy skin and rashes, another may complain of a perennial runny nose and some wheeze a lot with infections, and yet others present with food-related symptoms. Although these are distinctly different manifestations, they could have a single root cause.
What Causes Allergies In Children?
Childhood allergies are basically an inappropriate immune response towards a substance that usually presents no harm, be it a food item or an allergen in the environment. However, it is not always easy to pick out what is causing the allergic response. The child's medical history as well as the nature and accompanying circumstances of the reaction, play a pertinent role in picking out what is precipitating the problem.
Two children may present with similar complaints but have different underlying allergic conditions. Understanding the pattern of the disease helps decide what investigations are needed and how best the condition can be managed.
Also read: In-Toeing In Children: When It Needs Assessment
How Allergies Can Affect Multiple Body Systems
Allergic diseases can affect multiple body systems. The most common are the skin, upper respiratory tract and the lower respiratory tract. Skin allergy manifests as atopic dermatitis or urticaria, upper respiratory tract can cause allergic rhinitis and conjunctivitis and lower respiratory tract can manifest as asthma.
There are also food allergies which could present with gastrointestinal symptoms or even more serious reactions. A child may also face multisystem involvement and this can sometimes be life-threatening like in a case of anaphylaxis.
Understanding The Role Of Type 2 Inflammation
Allergic disorders may present with multisystem involvement due to the fact that type 2 inflammation is a key driver in the pathology. Cytokines such as IL-31, IL-13 and IL-5 are integral to the formation of IgE antibodies and the activation of eosinophils. Genetic predisposition, skin barrier dysfunction, environmental exposure and the gut microbiota also contribute towards the development of allergies.
There is usually an evolution of allergic diseases as a child grows older. This is commonly referred to as the atopic march. It is common for a child to present with atopic dermatitis and then develop food allergies, allergic rhinitis or asthma later on in life. However, this is not always the case, and an allergic disorder cannot be extrapolated to the presence of any other based on this association alone.
Awareness to these associations can help parents and doctors to watch out for developing conditions and ensure early and appropriate intervention. For example, in a child presenting with persistent eczema, investigation for associated allergic disorders is vital if the history supports it. Early diagnosis and management can also help the parents identify red flags and seek help sooner.
How Are Childhood Allergies Diagnosed?
A thorough clinical history is an extremely valuable tool when it comes to diagnosing allergies. It is important for the doctor to know what the likely allergen was, how soon after exposure the symptoms cropped up, whether similar symptoms have occurred before, and what body systems are involved.
The timing of the reaction and whether it is a one-off or recurrent episode is important. A reaction occurring minutes after ingesting a certain food is very different from a food that causes symptoms after days of consumption.
Treatment And Management Of Allergies In Children
Skin prick tests and specific IgE blood tests are commonly used to screen for sensitisation to common allergens, but these are just pointers. A positive test does not necessarily signify a clinically relevant allergy. The symptoms and exposure history must always be taken into consideration.
Testing for specific IgE to a panel of foods without a clear indication is not only misleading but can also be harmful. Parents may unnecessarily eliminate food groups from the child's diet based on a positive test, thereby affecting nutrition. Similarly, total IgE levels are not helpful in diagnosing a specific allergy.
The treatment varies from managing acute symptoms (with antihistamines or steroids) to controlling chronic conditions (with regular inhaled steroids for asthma). Avoiding the allergen where possible, and treating flare-ups appropriately are the cornerstones of management. Immunotherapy with allergen extracts may be indicated in selected patients with respiratory allergies. Biologics may be considered in certain conditions under specialist supervision.
Why Childhood Allergies Need A Holistic Approach
Children at risk of anaphylaxis should have a personalised action plan and an epinephrine auto-injector available at all times.
Childhood allergies should not be managed in isolation. The focus should be on the child as a whole rather than a single presenting complaint. Awareness and management of any associated conditions can help prevent potentially serious complications.
By Dr Gargi Mathur, Senior Paediatrician, Shalby International Hospitals, Gurugram
In-Toeing In Children: When It Needs Assessment
Credit: AI
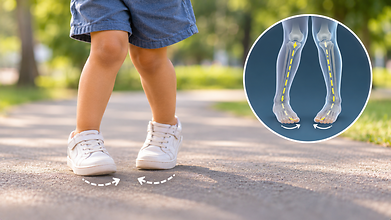
Parents may notice that a child’s feet point inward while walking or running. This is called in-toeing. It is common in young children and, in most cases, reflects normal development of the foot or leg bones. Many children improve naturally as they grow, without treatment.
However, it is not always helpful to dismiss a persistent or troublesome walking pattern as “just a growing phase.” The child’s age, the cause, whether the pattern is worsening, and its effect on movement all matter.
What can cause in-toeing?
In-toeing usually comes from one or more of three areas:
1)Foot: The front of the foot curves inward, a condition called metatarsus adductus. Flexible cases often improve naturally.
2)Shin: The shin bone turns inward, called internal tibial torsion. This is common in toddlers and usually improves with growth.
3)Thigh: The thigh bone turns inward, called femoral anteversion. It may become more noticeable when a child begins running or walking with the feet turned in.
The appearance of the feet alone does not always reveal the cause. A clinician can assess the child’s walking pattern and examine the hips, knees, shins and feet.
Also read: Hailey Bieber Opens Up About PMDD After Childbirth: What Is It And How Is It Different From PMS?
When should parents seek advice?
An occasional inward-pointing step, without pain or difficulty, usually needs observation rather than treatment. Arrange an assessment if the child:
- Trips or falls often, or has difficulty running, jumping or keeping up with peers.
- Avoids play or sports because of the way they walk.
- Has pain, swelling, a limp or difficulty bearing weight.
- Has a marked difference between the two legs.
- Develops a new or rapidly worsening walking pattern.
- Has a foot that is rigid or cannot be gently moved toward a straight position.
- Pain, limping, sudden onset, or marked asymmetry are reasons to look beyond a routine developmental variation.
What does assessment involve?
The clinician will ask when the in-toeing began, whether it is changing, and whether it affects daily activities. They will observe the child standing and walking, and assess foot flexibility, hip and leg rotation, balance and function.
X-rays are not routinely needed when the history and examination fit a typical developmental pattern. They may be considered if there is pain, trauma, unusual examination findings or concern for another condition.
Does every child need physiotherapy, special shoes or braces?
No. For typical, painless developmental in-toeing, reassurance and observation are usually appropriate. Special shoes, braces and orthotics do not correct the usual rotational causes. Physiotherapy may help when there is a separate issue—such as weakness, balance difficulty or impaired coordination—but it does not generally change the underlying bone rotation.
If in-toeing is severe, persistent and causing substantial functional difficulty, a paediatric orthopaedic specialist can advise whether further evaluation or treatment is appropriate. Surgery is rarely needed and is generally considered only for older children with severe deformity and significant functional problems.
A practical message for parents: Most children with in-toeing walk and play normally, and their alignment improves as they grow. The aim is not to make every child’s walking look identical; it is to ensure the child moves comfortably and safely. Seek an assessment for pain, limping, sudden change, pronounced asymmetry or meaningful difficulty with everyday activities.
- Follow Us :


© $2026 Times Horizon Private Limited