
- Health Conditions A-Z
- Health & Wellness
- Nutrition
- Fitness
- Health News
- Ayurveda
- Videos
- Medicine A-Z
- Parenting
Why Does High Blood Pressure Cause Nosebleeds?

Image Credit: Canva
It was a typical morning. My mother was getting ready; this was her usual routine: bustling around the house. When she suddenly stopped and shouted, blood was oozing from her nose. As kids, my siblings and I were terrified. We scrambled to help, but it wasn't until later that we learned the cause of that alarming moment: high blood pressure. That day was our first lesson in the silent yet powerful effects of hypertension. Nosebleeds, or epistaxis, are common, and nearly everyone experiences at least one in their lifetime.
While most are minor and often caused by dry air or irritation, some can signal underlying health concerns. One recurring question is whether high blood pressure causes nosebleeds or is merely coincidental.
Where Exactly Does a Nosebleed Occur?
The nose is covered by a rich plexus of small blood vessels, making it prone to bleeding. Most nosebleeds are anterior in origin, occurring at the front of the nose, and are relatively benign. They often occur because of irritants such as dry air, frequent nose-blowing, or trauma.
On the other hand, posterior nosebleeds are caused by a source that is located deeper within the nasal cavity. They are less common but more severe, as the blood tends to flow backward into the throat, making them more difficult to control. Common causes of posterior nosebleeds include trauma, medical conditions, or high blood pressure.
Connection Between Nosebleeds and High Blood Pressure
Hypertension is the condition whereby the pressure of blood against the arterial walls is consistently too high. Over time, this may damage the fine blood vessels in the nose, causing them to rupture more easily.
Significant studies have shown a strong relationship between hypertension and severe cases of nosebleeds necessitating urgent care. A certain study showed that patients diagnosed with high blood pressure had 2.7-fold increased chances of having nosebleeds that were not slight.
However, it should be noted that mild hypertension by itself does not cause nosebleeds. Nosebleeds are more likely to happen during a hypertensive crisis when the blood pressure suddenly rises to above 180/120. A hypertensive crisis can also have other symptoms such as a severe headache, shortness of breath, and anxiety. Therefore, it is considered a medical emergency.
Why Does Hypertension Increase the Risk?
Chronic hypertension makes the walls of blood vessels weaker and less elastic, which easily causes them to tear. In the nose, this is especially vulnerable because the blood vessels are close to the surface. Sudden surges in blood pressure, such as in a hypertensive crisis, can cause tears in these weakened vessels, resulting in nosebleeds.
While hypertension is a contributing cause, nosebleeds occur infrequently as the only manifestation of high blood pressure. This makes regular monitoring for blood pressure all the more crucial, as hypertension has the reputation of being the "silent killer" since people often do not present symptoms until the disease has run its course.
Other Causes of Nosebleeds
- Dry Air: Cold weather or house heating dries out membranes that line the nose, hence susceptible to cracking.
- Trauma: Blows in the nose, nose picking or excessive nose blowing can traumatize blood vessels.
- Intrinsic Disease: Liver disease and kidney disease and drug therapy that affect clotting such as blood thinners enhance the risk of nose bleeding.
- Foreign Bodies: Children especially tend to insert objects up their noses, which can be irritating and bleed.
- Allergies or Infections: Chronic nasal inflammation resulting from allergies or colds causes irritation to the nasal mucosa.
Managing Nosebleeds at Home
For most nosebleeds, you can manage them yourself at home:
1. Sit up and lean slightly forward to prevent swallowing blood.
2. Press your nostrils together for at least 10 minutes.
3. Use a cold compress on the bridge of your nose to constrict blood vessels.
4. If the bleeding continues, use a nasal decongestant spray.
Consult a doctor if the bleeding persists beyond 20 minutes, is heavy, or follows a head injury.
Preventing Nosebleeds
Preventive measures can decrease the incidence of nosebleeds:
- Use a humidifier to maintain moisture in the air.
- Apply saline sprays or gels to keep nasal passages hydrated.
- Avoid nasal trauma by being gentle when blowing your nose.
For patients with hypertension, managing blood pressure is the best way to minimize the risk of complications. A combination of lifestyle changes, such as maintaining a healthy diet, regular exercise, and prescribed medications, can help keep blood pressure in check.
When to Worry About Nosebleeds
Most nosebleeds are harmless, but they can sometimes be signs of an underlying health condition. In adults with high blood pressure, frequent or severe nosebleeds should never be ignored. A health provider should be consulted in order to rule out any serious conditions and ensure appropriate treatment.
Regular check-ups, a healthy lifestyle, and awareness about the relationship between nosebleeds and high blood pressure would go a long way to protect your health. Indeed, prevention is always better than cure.
Epistaxis and hypertension. Post Graduate Medical Journal. 1977
With Delhi AQI Nearing 400, Pollution & Flu Loom Ahead Of Diwali: What Happens When Both Hit Your Lungs?
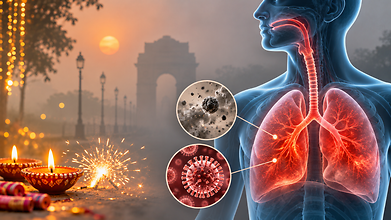
Credit: AI
Delhi's air quality remained in the Very Poor category on Thursday, with an AQI of 369 as pollution levels continued to rise across the Capital. With Diwali celebrations with firecracker fuel smoke to an already polluted city, concerns about respiratory health are mounting. The timing is alarming as it also coincides with the flu season, when respiratory infections are also circulating.
While air pollution and influenza both affect the respiratory system, it can put additional stress on the lungs. Pollutants can irritate the airways, trigger inflammation and weaken the lungs' natural defence mechanisms, while the influenza virus infects the respiratory tract.
Together, they can aggravate respiratory symptoms and make breathing more difficult, especially in people with pre-existing lung conditions.
According to Dr. Arup Halder, Consultant Pulmonologist at CK Birla Hospitals, CMRI Kolkata, prolonged exposure to air pollution can weaken the respiratory system's immunity.
“Exposure to air pollution, especially for long durations, can weaken the respiratory system's immunity. Fine particulates can become lodged in airways and damage the mechanisms the body has to protect itself. This makes respiratory infections much more likely, especially if viral in nature,” he told HealthandMe.
Dr. Suresh Sagadevan, Senior Interventional Pulmonologist at Gleneagles Hospital, Chennai, told HealthandMe that pollution can also interfere with the lungs' natural cleaning mechanisms.
He said that the respiratory tract contains tiny hair-like structures called cilia, which help remove dust and germs. Polluted air can affect their functioning, making it easier for respiratory viruses to infect the airways. However, pollution does not directly cause influenza nut it can compromise the respiratory system's ability to defend itself against such infections.
What Happens When Particulate Matter And Flu Affect The Lungs Together?
Particulate matter and influenza together can intensify inflammation in the respiratory system.
Fine particulate matter, like PM2.5, can penetrate deep into the lungs. It can cause inflammation and oxidative stress. At the same time, influenza viruses infect the cells lining the respiratory tract.
"When both exposures occur together, the existing inflammation can become more intense, potentially worsening coughing, breathing difficulty and airway irritation. In simple terms, the lungs are dealing with two different stresses at the same time," said Dr. Sagadevan.
Dr. Halder added that PM2.5 can also interfere with the body's ability to ward off irritants from the respiratory tract, while influenza can make breathing challenging.
Facing both together can be challenging for people whose respiratory or immune systems are already compromised.
Can Diwali Pollution Make Flu Symptoms Worse?
Also read: Air Pollution In Delhi: Experts Warn Of Red Eyes, Itching, Watering In Children
Firecracker smoke can aggravate an already infected and overwhelmed respiratory system. People with flu may experience excessive coughing, wheezing, chest tightness and breathlessness when they get exposed to high levels of pollution.
"Increased Diwali-related pollution will definitely worsen respiratory symptoms for individuals with the flu, especially during this period. The gases and particulate matter from firecracker smoke can lead to chest congestion and difficulty in breathing. In some cases, the pollution can worsen existing asthma and other lung-related conditions and trigger respiratory issues," said Dr. Halder.
Dr. Sagadevan said that people with asthma, chronic obstructive pulmonary disease (COPD) and other pre-existing respiratory conditions need to be particularly careful by limiting exposure.
Who Is Most Vulnerable When Flu Season Coincides With High Pollution?
Certain groups of people may face a greater risk when respiratory infections coincide with elevated pollution levels. These include:
- Children: Their lungs are still developing, making them more vulnerable to air pollution.
- Older adults: Age-related changes can reduce respiratory capacity and make it harder to cope with added stress on the lungs.
- Pregnant women: They need to take extra precautions against respiratory infections and environmental pollutants.
- People with asthma or COPD: Pollution can trigger flare-ups, worsen airway inflammation and aggravate breathing difficulties.
- Immunocompromised individuals: A weak immune system can make it harder to fight infections and increase the risk of severe illness.
Dr. Halder explains that older adults and people with weak immunity may be more susceptible to more serious flu symptoms. Meanwhile, those with existing lung conditions may experience worsening respiratory symptoms even with short periods of pollution exposure.
Pollution Effects Vs Flu: Symptoms
Pollution-related respiratory irritation and influenza can lead to similar symptoms, making it difficult to distinguish between the two. However, their onset and symptoms can differ.
Pollution-related irritation develops shortly after exposure to polluted air. Common symptoms include:
- Throat irritation or discomfort
- Burning or watering eyes
- Dry cough
- Sneezing
- Wheezing
- Chest discomfort
Flu, on the other hand, is a viral infection that mostly causes a sudden onset of symptoms, including:
- Fever
- Body aches and muscle pain
- Headache
- Fatigue
- Cough
- General weakness
"However, both can occur together, and symptoms may overlap. Persistent fever, worsening breathlessness or significant weakness should prompt medical evaluation," says Dr. Sagadevan.
Dr. Halder also recommends consulting a medical professional when symptoms make it difficult to determine whether the problem is pollution-related irritation or an infection.
How To Protect Your Lungs During Diwali And Flu Season
Reducing exposure to polluted air and taking precautions against respiratory infections can help protect lung health during the festive season.
Both doctors recommend the following measures:
1. Limit outdoor exposure: Avoid spending long periods outdoors, especially after firecracker bursting and during periods of heavy smoke.
2. Wear a well-fitting N95 mask: If you need to step outside when pollution levels are high, use a properly fitted N95 mask to reduce exposure to fine particulate matter.
3. Keep windows closed: Close doors and windows during periods of heavy smoke to limit the entry of outdoor pollutants. Ventilate indoor spaces when outdoor air quality improves.
4. Avoid outdoor exercise: Vigorous physical activity increases the amount of air you breathe in, increasing exposure. Avoid exercising outdoors when air quality is poor.
5. Avoid firecrackers and second-hand smoke: Staying away from firecracker smoke can reduce exposure to harmful pollutants.
6. Get vaccinated against influenza: Stay up to date with flu vaccinations to reduce the risk of influenza and its complications.
7. Maintain hand hygiene: Wash your hands regularly for infection prevention.
8. Seek medical attention: Do not ignore worsening fever, cough, wheezing or breathing difficulties, especially if you have an existing respiratory condition.
Dr. Sagadevan concludes, "Air pollution and influenza can independently affect respiratory health, but their coexistence can place additional stress on the lungs. During the festive season, protecting our lungs through pollution avoidance, vaccination and timely medical care should be a priority."
Common Diabetes Drug Metformin May Slash Long COVID Risk By More Than 50%

Credit: AI
Metformin is the first-line treatment for type 2 diabetes in adults and children aged 10 years and above. The drug has also found applications in managing Polyendocrine Metabolic Ovarian Syndrome (PMOS), formerly known as Polycystic Ovary Syndrome (PCOS). But a recent study says that it may have some potential use in a non-metabolic health condition: Long COVID.
Researchers found that people who were prescribed metformin shortly after testing positive for COVID-19 had a significantly lower risk of developing Long COVID than those prescribed other medications.
How Was The Study Conducted?
The study, titled Metformin at the Time of COVID-19 Infection and Risk of Long COVID: A Target Trial Emulation Study, was published in the Journal of Medical Virology recently.
Researchers have been exploring metformin's antiviral and anti-inflammatory effects, especially during the early stages of COVID-19 infection. They are specifically investigating if metformin could reduce the risk of Long COVID if taken soon after contracting the infection.
The researchers examined health records of more than 21 million people from the US National COVID Cohort Collaborative (N3C). They identified adults who had tested positive for COVID-19 between March 2020 and September 2023. They compared two groups:
Metformin group: People who received a new prescription for metformin within six days of their documented COVID-19 infection.
Comparison group: People who received prescriptions for other medications, including fluvoxamine, fluticasone, ivermectin or montelukast, during the same period.
The researchers excluded people who were already taking metformin or had conditions like diabetes, PCOS or gestational diabetes that could explain why they were prescribed the drug.
After statistical adjustments to make the groups more comparable, the researchers compared 248 people in each group. They then tracked the development of Long COVID or death over the following 180 days (six months).
Also read: Can Low-Dose Naltrexone Ease Long COVID Symptoms? New Study Examines The Evidence
Can Metformin Help Reduce The Risk Of Long COVID?
People who were prescribed metformin within six days of a COVID-19 infection had a 53% lower relative risk of Long COVID or death compared to those on other medications.
“Metformin prescription within the week following documented SARS-CoV-2 infection was associated with a 53% reduction in LC/D [long COVID or death] over 6 months in this primarily Omicron-infected sample,” wrote the authors, led by researchers from the University of Minnesota Medical School.
The study found that the risk of Long COVID or death within six months was 4.0% in the metformin group as 10 out of 248 people developed symptoms.
In the comparison group, the number was 8.5% as 21 out of 248 people presented symptoms of Long COVID. Overall, the weighted chance of Long COVID or death in patients on metformin or control treatment within six days of diagnosis was 6.3%. The absolute difference between the two groups was 4.5 percentage points.
“These results are also consistent with a recent sequential target trial analysis in the United Kingdom that assessed metformin started within 90 days of infection, HR [hazard ratio] 0.36,” the authors wrote. “The replication of results in clinical trials is important for informing treatment guidelines.”
More About Long COVID
Long COVID refers to symptoms that occur after a SARS-CoV-2 infection and cannot be explained by another diagnosis.
Symptoms may include brain fog, fatigue, cognitive difficulties, breathlessness, sleep disturbances and problems with everyday activities. These symptoms may last for months or even years.
Research has also suggested that brain inflammation may persist even after the virus is no longer detectable.
Some people improve over time, while others experience prolonged illness that affects their ability to lead routine lives.
She Takes Charge: Eminent Women Oncologists Chart What Breast Cancer Care Needs Beyond Treatment

When a woman is diagnosed with breast cancer, the conversation tends to centre on surgery, chemotherapy and targeted drugs. At She Takes Charge, a unique forum held in Delhi, eminent women oncologists turned to what comes with it: the fear, the diet confusion, the follow-ups, the return to work, and beyond just treating the cancer.
She Takes Charge brings leading women oncologists from across India onto one platform to improve breast cancer survivorship care. It extends the Take Charge campaign, launched by Novartis with Times Network in October 2025, which aims to help patients and their families advocate for themselves, hold informed discussions with their doctors and make the choices that are right for them. The campaign shifts the focus from survival alone to empowered living, with an emphasis on lowering the risk of recurrence while protecting quality of life. It reached around 90,000 people through its website last year.
The Delhi chapter, the first of the forum, was organised by Times Network and Novartis with the Hansa MedCell team, and was attended by oncologists in person and online. It is a pilot, meant to shape counselling toolkits for patients and paramedical staff around three themes: support, heal and empower.
In attendance were Dr Meenu Walia, Dr Pankaj Goyal, Dr Seema Singh, Dr Jyoti Wadhwa, Dr Priya Tiwari, Dr Saphalta Baghmar and Dr Kripa Bajaj. While, many joined virtually and included Dr Shalaka Joshi, Dr Shona Nag, Dr Jovita Martin and Dr Sailakshmi Dayana. Dr Priya Parmar, chief operating officer of the Indian Cancer Society in Delhi, who helped shape the Take Charge initiative, offered the patient perspective.

Information in her own language
“We need women to be armed with information,” Dr Parmar said, adding that it must come in a language the patient understands. She noted that a simple question such as “what should I eat” can hide something larger: a woman now living on dal, bhaat and aloo, and feeling guilty about what her illness has cost her family.
One size does not fit
Doctors suggested tailoring material by age, education and employment, and urged organisers to add economic status. Dr Dayana, a gynae-oncologist at Apollo Hyderabad, said women with a strong family history or a BRCA mutation need more intensive counselling, since they worry about what they may have passed on to their children. Others asked for separate content for women under 30, and for material that follows the treatment a patient is receiving.
Anticipate, then share the load
Moderating the support segment, Dr Walia said the aim is “treating the woman in totality.” She argued that side effects should be anticipated and managed early, with the whole treating team, including nurses and paramedical staff, ready to answer simple questions on food and nausea. One oncologist said the antiemetic section of the toolkit should reflect that a 2.5 mg dose of olanzapine, tested in a Tata Memorial randomised trial, had led to a change in NCCN guidelines.
Doctors also spoke of the burden on the treating oncologist. Patients in India often expect one doctor to explain the diagnosis, the treatment, the diet and the exercise, and some consultations run to an hour. Participants called for trained support staff and counsellors to share the work.
Video, volunteers and time alone
Doctors agreed that patients forget much of what they hear in the consulting room. Many now ask patients to record counselling sessions, and Dr Dayana said she wished for “a better and animated, a better edited video” to offer instead. Video was also seen as the way to reach women outside the metros, who may not see a specialist often. Dr Joshi described pre- and post-operative classes at her hospital, led by patient volunteers for almost a decade and now being converted into a QR code. Dr Baghmar urged oncologists to give each patient five to ten minutes alone, away from family members who often speak for her.
Myths on the plate
Diet drew the liveliest debate, with sugar, keto diets and boiled fruit coming up repeatedly. Dr Joshi’s advice was simple: “roti, sabzi, dal, rice is a kind of a square Indian meal that cannot go wrong.” Another oncologist said she sets no restrictions beyond avoiding food that is too spicy, too oily or cooked by someone whose hygiene is unknown. One doctor raised weight gain after treatment, noting that some patients on endocrine therapy ask about weight-loss injections. The advice was to check thyroid function and see an endocrinologist, not to give blanket advice.
On exercise, doctors favoured mild activity such as walking and yoga during treatment and strength work afterwards, always cleared by the treating oncologist. The group agreed to build evidence-based consensus documents on diet and sexual well-being.

Beyond the breast
Participants asked for content on contraception, pregnancy after treatment, genetic testing, screening for other cancers, breast prostheses, health insurance and caregivers, described by one doctor as a neglected pillar of cancer care. Doctors also flagged two issues that are often missed. Young women need counselling on preserving their eggs before chemotherapy, and some patients develop shoulder and spine problems after mastectomy that are mistaken for other pain. Follow-up testing was another gap: doctors said some clinicians still order routine chest X-rays, and the group wants a consensus on which scans are needed.
Novartis demonstrated two tools: an offline HTML tool for HR-positive, HER2-negative early breast cancer that walks patients through a treatment plan, and a patient microsite that adds follow-ups and medication reminders to a phone calendar. Feedback from She Takes Charge will feed into a white paper.
- Follow Us :


© $2026 Times Horizon Private Limited