
- Health Conditions A-Z
- Health & Wellness
- Nutrition
- Fitness
- Health News
- Ayurveda
- Videos
- Medicine A-Z
- Parenting
Who Can Donate Blood To Whom?
Credits: Canva
Do you know who can donate blood to you or who can you donate blood to? Blood donation may not be complex, but it does need to be compatible with yours and vice-versa. The blood types are determined by the presence or absence of certain antigens - substance that can trigger immune response if they are foreign to the body.
There are four major blood groups which are determined by the presence or absence of two antigens, A and B, on the surface of red blood cells. There is also a protein called the Rh factor, which can either be present (+) or absent (-), which creates A+, A-, B+, B-, O+. O-, AB+, AB- blood types.
Group A blood type has only A antigens on red blood cells and B antibody in the plasma. B has only B antigen on red cells and A antibody in the plasma. AB has both A and antigens on red cells, but neither A nor B antibody is present in the plasma. O has neither A nor B antigens on red cells, but both A and B antibody are present in the plasma.
Blood Type And Who Can You Donate To?
Your blood type determines who can you donate to. This is because there are very specific ways in which blood types must be matched for safe transfusion. The right blood transfusion could actually save you, while the wrong one could be lethal. Also, Rh-negative blood is given to Rh-negative patients and Rh-positive or Rh-negative blood can only be given to Rh-positive patients.
If you are O blood type, you can donate to O, A, B, and AB, if you are A blood type, you can donate to A and AB, if you are B blood type, you can donate to B and AB, however if you are AB, you can only donate to AB.
Who Can You Receive Blood From?
If you are O blood type, you can only receive from O. If you are A, you can receive from type A and O. If you are blood type B, you can receive from type B and O. If you are AB, you are lucky, you can receive blood from O, A, B, and AB.
There are more than 600 other known antigens, the presence or absence of which creates "rare blood types". Certain types are unique to specific ethnic or racial groups, this is why an African-American blood donation can be the best hope for the needs of patients with sickle cell disease, as per the Red Cross Organization.
Universal Blood Donor
Type O is one in high demand, as it can donate blood to anyone. O negative blood type is the universal blood type, which can donate to everyone, especially during the emergency transfusions and for immune deficient infants.
Who Have These Blood Types In US?
In the US, 37% Caucasian, 47% African-American, 39% Asians, and 53% Latino-American are O-positive. However, only 8% of Caucasian, 4% of African-American, 1% Asian, and 4% Latino=Americans are O-negative.
A+: 33% Caucasian, 34% African-American, 27% Asian, 29% Latino-American
A-: 7% Caucasian, 2% African-American, .5% Asian, 2% Latino-American
B+: 9% Caucasian, 18% African-American, 25% Asian, 9% Latino-American
B-: 2% Caucasian, 2% African-American, .4% Asian, 1% Latino-American
AB+:3% Caucasian, 4% African-American, 7% Asian, 2% Latino-American
AB-: 1% Caucasian, .3% African-American, .1% Asian, .2% Latino-American
Could GLP-1 Drugs Help Prevent Rupture Of Abdominal Aortic Aneurysm? Study Finds 46% Reduction In Risk
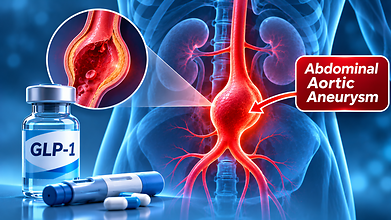
Credit: AI
The hype around GLP-1 weight loss drugs keeps growing due to numerous new benefits as well as side effects that are discovered every other day. A recent study found that the risk of aortic aneurysm rupture is significantly less among GLP-1 users. The study was published in the Journal of Vascular Surgery.
GLP-1 receptor agonists is a a class of medicines that is widely used to treat type 2 diabetes and obesity. Users have reported substantial weight loss results with the help of these medicines like Ozempic, Mounjaro, Zepbound and others.
Now, researchers have found that people with abdominal aortic aneurysms who used GLP-1 drugs had a 46% lower risk of rupture over five years compared with those who did not use these medicines. This means that GLP-1 drugs may also have cardiovascular benefit apart from diabetes and obesity.
The study analysed health records from 123 healthcare organisations in the US. It is based on more than 412,000 people diagnosed with abdominal aortic aneurysms who underwent imaging surveillance every six months.
After matching patients based on factors like age, sex, diabetes, high blood pressure, smoking, heart disease and kidney disease, the researchers compared 13,722 GLP-1 receptor agonist users with an equal number of non-users.
GLP-1 Drugs Linked To Fewer Aortic Aneurysm Ruptures
Also read: ‘Godzilla’ Drug Retatrutide Reverses Sleep Apnea In 1 In 4 Diabetes Patients
After five years, aortic aneurysm rupture was recorded in about 1.6% of people taking GLP-1 drugs, compared to 2.4% of those who were not taking them.
The researchers reported a hazard ratio of 0.538, indicating a 46.2% lower risk of rupture among GLP-1 drug users after adjustment.
The difference was also observed at the two-year mark, when rupture occurred in 1.1% of GLP-1 users compared to 1.8% of non-users.
People taking GLP-1 drugs also had fewer elective aneurysm repairs. At five years, 2.1% of users underwent elective repair compared to 3% of non-users.
The study further found lower rates of major cardiovascular events like heart attacks, strokes and heart failure, as well as lower all-cause mortality among GLP-1 users.
What Is An Abdominal Aortic Aneurysm?
An abdominal aortic aneurysm (AAA) occurs when a section of the aorta, the body's largest artery, becomes enlarged or bulges due to weakening of its wall. It develops in the part of the aorta that passes through the abdomen.
Many abdominal aortic aneurysms do not cause symptoms and are detected during tests. However, as the aneurysm enlarges, its risk of rupture increases.
A ruptured aneurysm is considered to be a medical emergency as it can cause severe internal bleeding. Symptoms may include sudden, severe abdominal or back pain, dizziness, fainting and a rapid heartbeat.
Smoking, older age, high blood pressure, atherosclerosis and a family history of aneurysms are among the risk factors.
GLP-1 Drugs & Lower Risk Of Aortic Aneurysm Rupture Risk
GLP-1 receptor agonists work by mimicking the naturally occurring GLP-1 hormone. They help regulate blood sugar by stimulating insulin release when glucose levels are high, slowing the emptying of stomach and reducing appetite.
Some of their effects may also impact blood vessel health. Abdominal aortic aneurysms develop through several processes, including inflammation, damage to vascular smooth muscle cells and changes in the proteins that maintain the artery wall.
GLP-1 drugs have shown anti-inflammatory and cardiovascular benefits in older research. The researchers suggest these effects may help explain the lower rates of aneurysm-related complications observed in the study.
The findings are promising but do not conclusively prove that GLP-1 medicines prevent aneurysm rupture. This was a retrospective observational study, meaning researchers examined existing health records rather than randomly assigning patients to receive the drugs.
One important limitation was that aneurysm size was not included among the matching variables. Since aneurysm size is a major determinant of rupture risk, differences between the groups could have impacted the findings.
When Missed Periods Are Not Just A Reproductive Issue: What Your Cycle May Be Saying About Your Bones
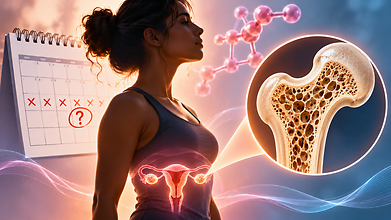
Credit: AI
When a woman misses her period, pregnancy is usually the first thing she thinks about. If that is ruled out, stress, weight changes or a hormonal imbalance may seem like the obvious explanations. But when periods become irregular or stop for several months, there may be more to the story.
In some women, these changes can also signal a risk to bone health. The menstrual cycle is controlled by a complex interaction between the brain and the ovaries. Oestrogen, one of the key hormones involved, is important not only for reproductive health but also for maintaining strong bones. It helps regulate the continuous process of bone breakdown and rebuilding.
When oestrogen levels remain low for a prolonged period, this balance can be disturbed, leading to a reduction in bone mineral density and, in some cases, an increased risk of fractures.
Menstrual health is not just about getting a period every month. It can offer important clues about what is happening elsewhere in the body.
Why Do Periods Sometimes Stop?
Also read: Why Do My Breasts Hurt Right Before My Period?
One possible cause is functional hypothalamic amenorrhoea, a condition in which the brain reduces the hormonal signals that stimulate the ovaries. It may occur when the body is under physical or emotional stress, particularly in the setting of inadequate food intake, rapid weight loss, excessive exercise or a combination of these factors.
In simple terms, the body may not be getting enough energy to support all its normal functions. Reproductive activity can slow down as a result. If this continues, the effects may extend beyond the menstrual cycle.
Low energy availability can affect hormones involved in bone formation and maintenance. Inadequate intake of protein, calcium and vitamin D may further compromise bone health.
The concern is particularly important in adolescents and young women, because these are the years when the body builds much of its peak bone mass. If this process is disrupted, they may not achieve their full bone-strength potential, which can have implications for bone health later in life. It can happen even when a woman is not underweight.
One common misconception is that only very thin women are at risk. In reality, a woman can have a seemingly healthy body weight and still not be eating enough to meet the demands of her daily activity.
A student under academic pressure may skip meals regularly. A working professional may combine long hours with restrictive eating, while a woman who exercises intensively may not increase her food intake to match her energy needs. In such situations, menstrual changes may be one of the first noticeable signs that something is wrong.
Persistent tiredness, declining exercise performance, poor recovery after workouts and recurrent bone or muscle injuries may provide additional clues.
These symptoms are easy to dismiss as the result of a busy lifestyle, but they deserve attention when they occur alongside irregular or absent periods.
Not Every Missed Period Has The Same Cause
Also read: Women With Endometriosis Are Earning Less, Reveals Study
Although inadequate energy intake and prolonged stress can affect menstruation, they are not the only explanations. Pregnancy must first be ruled out. Other possible causes include polycystic ovary syndrome (PCOS), thyroid disorders, raised prolactin levels, premature ovarian insufficiency, chronic illnesses and certain medications.
A woman should seek medical evaluation if her periods stop for three months without an explanation, if her cycles remain persistently irregular, or if menstrual changes are accompanied by significant weight loss, restrictive eating, excessive exercise, bone pain or a stress fracture.
The assessment usually begins with a detailed menstrual history and questions about diet, exercise, weight changes, stress and medication use. Depending on the findings, the doctor may recommend pregnancy testing, blood tests to assess thyroid function and reproductive hormones, prolactin levels and other investigations.
A bone mineral density scan may also be appropriate when periods have been absent for a prolonged period or when additional risk factors for bone loss are present.
Protecting Menstrual Health Also Means Protecting Bone Health
Treatment depends on the underlying cause. When inadequate energy availability is responsible, the priority is to restore a healthy balance between food intake, physical activity and recovery.
This may require nutritional guidance, changes to exercise routines and support for managing psychological stress. A gynaecologist may work with an endocrinologist, dietitian or mental-health professional, depending on the individual’s needs.
Adequate calcium, vitamin D and protein are important for bone health, but supplements alone cannot correct an ongoing energy deficit. Similarly, hormonal medication should not be prescribed simply to produce a period without first understanding why menstruation has stopped.
A menstrual cycle is more than a monthly reproductive event. Persistent changes can provide valuable clues about hormonal function, nutrition and overall health. Paying attention to these changes early can help identify underlying problems and, where necessary, protect bone health for the future.
Manosphere Is A Public Health Concern: Lancet Report Says Online Misogyny Harms Men's Mental Health

Credit: iStock
The manosphere is a network of male-centric online groups, forums and communities that focus on men’s issues, masculinity definition and the changing roles and treatment of men in today’s world. Oftentimes, the content produced in the manosphere leans heavily towards promoting misogyny online, distorting the definitions of feminism and masculinity.
A recent Lancet report highlights this issue, stating that these online communities that promote misogyny, male victimisation and hostility towards feminism are actually a growing public health problem. The report also suggests that this public health concern should be addressed in the same way as obesity or smoking.
The researchers say that the so-called manosphere not only normalises violence and misogyny towards women but also affects men’s mental health, fueling issues like social isolation and discouraging them from seeking help.
In the paper, titled Reframing the manosphere: a public health response to a commercial ecosystem, authors Sarah J Hawkes and Kent Buse describe the manosphere as a “diffuse commercial ecosystem and loose collection of online communities united by shared beliefs about masculinity, misogyny, and male victimisation”.
These communities often promote the idea that men are facing masculinity crisis and social isolation and that feminism has systematically disadvantaged and exploited them. The authors argue that these narratives can wrongfully make young men believe that their personal difficulties are due to women, which could direct their frustration towards the opposite gender.
The authors wrote, “Men’s problems are framed [in the manosphere] as the result of feminism rather than structural conditions, and masculine identity is commodified through products and paid content that normalise and reinforce health-harming and performance-oriented masculinities.”
Manosphere And Men's Mental Health
Also read: Gender-based Violence Surging Global Antimicrobial Resistance, Say Experts
The authors identify several conditions that can make boys and young men vulnerable to manosphere content, including loneliness, educational disengagement, social exclusion, financial insecurity and uncertainty about their future.
Prof Sarah Hawkes, the report’s other author, said, “The manosphere offers boys and young men belonging, identity and an explanation for why life feels hard."
She added, “Those needs are real. A response that only removes the manosphere, without offering something credible in its place, will fail. We need to offer boys something better, not just tell them what to avoid.”
The authors also say that they may also reinforce resentment towards women and promote toxic ideas about masculinity, gender, relationships and success. They also say that these communities can harm men's mental health, contribute to body image concerns and discourage them from seeking professional support.
The authors argue that this business model can exploit insecurity while presenting structural problems as individual failures or the result of feminism. Some influencers promote twisted ideas of masculinity and encourage followers to purchase supplements, hormones and financial products.
Prof Kent Buse, a co-author of the paper and co-founder of the social justice thinktank Global 50/50, explained, “This is a business model, not a fringe. Outrage and grievance are good for business, so the system rewards the most extreme content. Expect the playbook that served tobacco so well: blame the individual, and call regulation an attack on freedom. Public health has a tested toolkit for commercial harms and we should use it.”
Online Misogyny Contributes To Violence Against Women
Also read: 'Put Up with the Pain': UK Report Exposes Gaps in Women's Reproductive Healthcare
The report also examines the consequences of following manosphere for women and girls. The authors warn that the manosphere can normalise misogynistic outlooks, reinforce gender inequality and create an environment in which violence against women and girls is more readily accepted.
The concern is not limited to individual posts or influencers. The researchers describe a commercial network in which content creators can benefit from extreme expressions of gender and hostility.
They compare the strategies used by this online ecosystem with those of industries such as tobacco and ultra-processed food, arguing that both can shift responsibility towards individuals while resisting regulation.
“Outrage and grievance are good for business, so the system rewards the most extreme content,” said co-author Kent Buse.
He added, “Boys and men are not the problem. The problem is the conditions that leave them isolated and without a secure future, and the companies that profit from their anger and insecurity.”
Just Censoring Harmful Content May Not Be Enough
Also read: Amid Changing Health Laws In The US, Would Abortion Become Illegal?
The authors argue that simply removing misogynistic content or restricting access to certain communities will not address the reasons why young men are drawn to them.
Co-author Sarah Hawkes said, “The manosphere offers boys and young men belonging, identity and an explanation for why life feels hard. Those needs are real. A response that only removes the manosphere, without offering something credible in its place, will fail. We need to offer boys something better, not just tell them what to avoid.”
The report also calls for a coordinated response involving governments, schools, healthcare services and community organisations. This includes improving access to education, skills training and employment opportunities, addressing social isolation and ensuring that boys and young men can access mental health services.
Manosphere Is A Public Health Issue
The researchers identify six priorities for action: addressing the social and economic conditions that make young men vulnerable, improving collaboration between health and education services, developing effective communication strategies, regulating harmful platforms, investing in research and monitoring, and confronting the bigger misogyny and anti-gender equality attitudes that keeps these communities running.
They argue that regulation should focus on the commercial incentives that amplify harmful content, rather than placing the entire responsibility on individuals who consume it.
- Follow Us :


© $2026 Times Horizon Private Limited