
- Health Conditions A-Z
- Health & Wellness
- Nutrition
- Fitness
- Health News
- Ayurveda
- Videos
- Medicine A-Z
- Parenting
What Is Type 3 Diabetes? Insulin Resistance In The Brain That Could Trigger Alzheimer’s

What Is Type 3 Diabetes? Insulin Resistance In The Brain That Could Trigger Alzheimer’s
Most people are aware of type 1 and type 2 diabetes, but did you know there is a type 3 diabetes as well! It is a more obscure term. Although it is not an accepted medical diagnosis, type 3 diabetes has been discussed in the literature as a possible relationship between insulin resistance in the brain and Alzheimer's disease. This link has been described to help explain how metabolic disorders impact brain health, causing cognitive decline and dementia.
What is Type 3 Diabetes?
Type 3 diabetes is more of a misnomer because it should not be confused with type 3c diabetes, which relates to pancreatic dysfunction. The term "type 3 diabetes," on the other hand, has been loosely used by some scientists to analogously propose that Alzheimer's disease is strongly implicated with insulin resistance in the brain.
This concept was conceptualized by Dr. Suzanne de la Monte and Dr. Jack Wands of Brown University in the year 2008. This hypothesis postulated that Alzheimer's disease may be called type 3 diabetes for it bears many similarities with glucose metabolism disorder type 2 diabetes. Their concept arises from the basic principle that insulin is fundamental to blood sugar regulation, but it is also the case with the brain. When brain cells become insulin-resistant, they lose access to glucose, impairing their function.
Research published in the Journal of Diabetes Science and Technology supports this hypothesis by indicating that insulin resistance can be a significant contributor to the occurrence of dementia, also referred to as Alzheimer's. The symptoms of memory loss and diminished reasoning are associated with impaired glucose metabolism in the body, especially in the cerebral tissue.
Symptoms of Type 3 Diabetes
Although type 3 diabetes is not a "medical term," its symptoms correlate well with Alzheimer's diseases that are known to reduce the ability to think in an efficient manner and bring down brain health. These signs are:
- Loss of memory, especially short-term.
- Poor judgment and judgment ability
- Failure in recognizing people or places familiar once.
- Failure in the process of reading, writing or processing numbers
- Anxiety, agitation, or mood changes.
- Disorganized thoughts or confusion
- Lack of impulse control
As the disease advances, patients may be afflicted with severe complications including an inability to swallow or control their bodily functions. In the final stages, most patients die from fatal complications such as aspiration pneumonia.
Causes of Type 3 Diabetes
This may not be well understood with regards to type 3 diabetes, or the exact link between insulin resistance and Alzheimer's disease. Some identified contributing factors include the following:
1. Insulin Resistance
Insulin acts as an important regulatory mechanism of brain functions such as memory and cognition. The reduction in insulin signaling may impair metabolism of brain cells, thus bringing about neurodegeneration.
2. Type 2 Diabetes
These diseases show a strong relationship and those individuals diagnosed with type 2 diabetes have double chances of getting Alzheimer's. In the two, the main causes can be chronic inflammation, oxidative stress, and a defect in glucose metabolism.
3. Environmental and Lifestyle Factors
Insulin resistance associated with obesity, stress, and an unhealthy diet is considered a cause that may increase the chances of Alzheimer's disease.
Researches in Frontiers in Neuroscience and The Lancet Neurology have also highlighted that drugs used for antidiabetic medication may be crucial for the prevention or at least slowing down the course of Alzheimer's.
Treatments for Type 3 Diabetes
In 2022, in a study in Pharmaceuticals, researchers studied biomarker uptake in brain regions implicated in the faulty uptake and metabolism of blood sugar in Alzheimer’s patients.
Emerging Therapies
Research into such treatments as intranasal insulin has also been promising. Intranasal delivery of insulin directly to the brain has been reported to enhance glucose uptake by brain cells, improve memory, and boost cognitive performance. While such clinical trials have been shown to be successful, additional research is needed for safety and efficacy.
Medications
For patients being aggressive or agitated, antipsychotic drugs may be prescribed; however, therapies such as cognitive rehabilitation as well as cognitive stimulation therapy serve to preserve memory and executive function.
Lifestyle Interventions
Diet, exercise, and stress management are critical in preventing and managing insulin resistance. A review in the Journal of Alzheimer's Disease also highlighted the benefits of Kirtan Kriya meditation, which can regulate genes involved in insulin and glucose metabolism, improve sleep, and reduce inflammation.
Can Type 3 Diabetes Be Prevented?
Although type 3 diabetes is not officially recognized, its connection to Alzheimer’s disease underscores the importance of proactive measures for brain health. Some prevention strategies include:
1. Healthy Diet
Consuming a balanced diet rich in antioxidants, whole grains, and healthy fats may support brain health.
2. Regular Exercise
Physical activity improves insulin sensitivity, reduces inflammation, and enhances overall metabolic health.
3. Stress Reduction
Mindfulness practices, including meditation, have been shown to lower stress levels, which can reduce the risk of cognitive decline.
The term type 3 diabetes brings out the complex relationship between metabolic disorders and brain health. Even though it is not a recognized medical condition, the concept emphasizes the crucial role of insulin in brain function and its possible contribution to Alzheimer's disease. Continued research will hopefully provide hope for therapies such as intranasal insulin and lifestyle modifications.
The Black Death Bacterium Still Exists: From Medieval Europe To Modern-Day Outbreaks
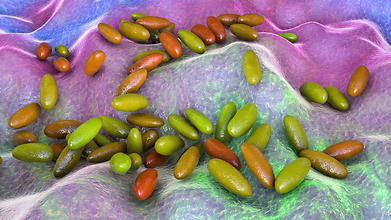
Credit: iStock
The Black Death swept across Eurasia and North Africa between 1346 and 1353, killing an estimated 30% to 60% of Europe's population.
Plague continued to recur in Europe over subsequent centuries, causing millions of deaths. Caused by Yersinia pestis, the same bacterium responsible for plague today, the Black Death was primarily associated with bubonic plague, although pneumonic plague also occurred.
Bubonic plague typically spreads through infected flea bites, while pneumonic plague affects the lungs and can spread between people through infectious respiratory particles during close contact. All forms can be fatal without prompt treatment, but antibiotics are effective when administered early.
India's 1994 Plague Outbreak
Although often associated with medieval history, plague continues to occur in parts of the world.
In 1994, India experienced an outbreak involving both bubonic and pneumonic plague, following heavy flooding and reports of exposure to dead rats.
“When the plague outbreak happened in India, I was one of the people who investigated it. The outbreak involved bubonic plague, which can be treated with antibiotics, and Surat also saw 64 to 68 cases of pneumonic plague. We identified the plague bacillus and traced its cycle in the surrounding wildlife. Plague surveillance in rats and other animals is essential to detect outbreaks early and take preventive measures,” Dr. N.K. Ganguly, former Director General of the Indian Council of Medical Research (ICMR), told HealthandMe.
There were 693 suspected cases that tested positive for Yersinia pestis antibodies and 56 deaths nationwide.
Surveillance, hygiene and timely treatment were essential to controlling the disease, said Dr. Amitabh Banerjee, an epidemiologist and former member of the Indian Armed Forces’ mobile epidemic investigation team. He investigated the 2002 pneumonic plague outbreak in Himachal Pradesh, which caused 16 cases and four deaths.
Plague Still Exists In Africa And The US
In the US, an average of about seven human plague cases are reported annually, mostly in rural areas of the American West, according to the Centers for Disease Control and Prevention (CDC).
The continued presence of Yersinia pestis in animal populations means the disease has not been eradicated.
“People think the plague is gone, it was something that occurred 500 years ago. It's not. It's here amongst us,” Simon Clarke of the University of Reading in the UK told the Associated Press. “Unless you get rid of those wild animals, which of course is not possible, then you're not going to get rid of the bacteria.”
Russia's Plague Scare: What We Know
Russia has completed checks following the October 2 death of 28-year-old laboratory worker Darya Shipilova in Siberia. Authorities have not confirmed plague as the cause, describing her illness as pneumonia of unknown origin. Nearly 5,000 samples reportedly showed no dangerous pathogens.
Reports of a second death linked to the plague was called "fake news" by Russia, and no plague outbreak has been confirmed in Russia. The WHO and US have requested Russia for more transparency regarding the cases.
Can Plague Be Eradicated?
Plague persists because Yersinia pestis circulates naturally among wild and domestic animals, including rodents, and their fleas. Eliminating human cases in one location does not remove the bacterium from these animal reservoirs.
Dr. Banerjee said plague can be deadly, particularly when it affects the lungs, but modern antibiotics are highly effective when treatment begins early.
“Plague cannot be eradicated because it is in wildlife, it is in rodents and all. So the only thing is hygiene and, with modern antibiotics, there should not be any panic,” he told HealthandMe.
Bubonic plague does not typically spread directly between people, while pneumonic plague can spread through infectious respiratory particles during close contact. Pneumonic plague can progress rapidly and requires urgent treatment.
Dr. Banerjee cautioned against assuming that a suspected case automatically signals a wider outbreak, noting that early diagnosis and appropriate antibiotic treatment are crucial.
Saba Ali Khan Opens Up About Brain Tumour: Can It Go Unnoticed If You Walk, Talk And Work Normally?

Credit: YouTube/@SohaAliKhanP
Indian jewelery designer Saba Ali Khan, daughter of veteran actress Sharmila Tagore and cricketer Mansoor Ali Khan Pataudi, has opened up about her brain tumor diagnosis at the age of 27.
Speaking on her sister, actress Soha Ali Khan’s podcast, Saba recalled that her diagnosis came as a surprise, without common warning signs such as headaches or vision loss.
Dr. Mazda K. Turel, the neurosurgeon who treated her at Wockhardt Hospitals, Mumbai, told HealthandMe that people with brain tumors can be “walking, talking and functioning normally” despite having a potentially serious tumor. He explained why tumors can go unnoticed and which symptoms warrant medical attention.
How Saba Ali Khan Discovered Her Brain Tumor
Saba recalled fainting while out with a friend. After losing consciousness a second time, she took around 20–25 minutes to regain consciousness.
An MRI revealed a shadow in the third ventricle of her brain. Doctors initially diagnosed a colloid cyst, a rare, non-cancerous growth.
Six months later, she underwent surgery and was diagnosed with pilocytic astrocytoma, a slow-growing, generally low-grade tumor of the brain or spinal cord.
Also read: Survival In Aggressive Brain Tumors Improves By Up To 50% in India, Say Doctors
Why Brain Tumours Go Undetected In Young Adults
“Brain tumors don’t check your age before making an appearance,” Dr. Turel said. “In young adults, symptoms are often dismissed as stress, migraines, fatigue or lack of sleep. Some tumors grow slowly, allowing the brain to adapt remarkably well.”
“The brain has an extraordinary ability to compensate, especially when a tumor grows slowly or develops in a relatively silent area,” he explained.
Early signs may include persistent headaches, subtle personality changes, difficulty concentrating, blurred vision and unexplained seizures. Other clues include forgetting familiar words, unexplained irritability, occasional imbalance and brief episodes of staring or losing awareness.
Sometimes, family members notice changes before the patient does. Dr. Turel illustrated the difference between ordinary forgetfulness and a potentially concerning change: “If you forget keys, that is OK, but if you forget what the keys are for,” it is a sign to get checked.
“The problem is that these symptoms are common, but their persistence or progression is what deserves attention,” he told HealthandMe.
How Tumor Location Affects Symptoms
Read More: Can 'Eye Strain' Lead To Brain Cancer? Experts Explain
Symptoms often depend more on where a tumor is located than on its size, Dr. Turel explained.
- Frontal lobe: Changes in personality or judgement.
- Temporal lobe: Memory problems or unusual seizures.
- Visual pathways: Blurred or double vision.
- Cerebellum: Problems with balance and coordination.
“New speech difficulties, weakness, unexplained seizures or progressive cognitive changes should never be casually dismissed,” he warned.
Brain Tumor Or Migraine: When Should A Headache Worry You?
Migraines usually follow a recognizable pattern and may involve nausea or sensitivity to light and sound, Dr. Turel said.
Tumor-related headaches are more concerning when they are new, progressively worsening, different from previous headaches or accompanied by neurological changes. They may be worse in the morning or with coughing and straining, although this is not always the case.
A persistent headache that progressively worsens, wakes someone from sleep or occurs with vomiting, visual changes or neurological symptoms warrants medical evaluation.
"A sudden, explosive headache that reaches maximum intensity within seconds—a thunderclap headache—is a medical emergency," the neurosurgeon said, noting that it can occur while "walking, talking and functioning normally"
It may indicate bleeding around the brain from a ruptured aneurysm rather than a tumor. Sudden weakness, confusion, loss of consciousness or a first seizure also require emergency assessment.
“Most headaches are not caused by brain tumors, and a headache alone rarely indicates one. The key is not to panic about every headache, but to recognize when an old familiar headache begins behaving like a stranger,” Dr. Turel said.
The 10-Minute Silence Test: What Your Brain Reveals When You Stop Filling Every Quiet Moment With Your Phone

Credit: iStock
When was the last time you stood in a queue without looking at your phone? Or had a cup of tea without scrolling through messages? Or sat in a car, waiting for someone, without opening Instagram simply because there was nothing else to do?
Try it today. Put your phone away for 10 minutes and do absolutely nothing with it. It sounds easy. For many of us, it isn't. The first thing you may notice is not peace, but restlessness. You may wonder if someone has messaged you. You may feel like checking the news, looking at the time or opening an app without even knowing why.
As a neurologist, I find this interesting because it tells us something about how we have trained our attention. Our phones have become so closely woven into everyday life that we often reach for them before we even realize we are bored.
The problem isn't the phone. It's the constant need for stimulation. There is nothing inherently wrong with using a smartphone. We use it to work, communicate, navigate, learn and stay connected.
The problem begins when every small gap in our day has to be filled.
Waiting for the lift? Check the phone.
Waiting for your coffee? Scroll.
Watching television? Check messages.
Feeling slightly bored? Open an app.
Our brains are naturally drawn towards novelty. A notification, a new message or a fresh video gives our attention something new to respond to. When this happens repeatedly, checking the phone can become almost automatic.
That is why I sometimes ask patients not only how much time they spend on their phones, but how often they feel the need to check them. Those are two very different questions.
What Happens When The Screen Goes Away?
The first few minutes may feel surprisingly busy inside your head. An unfinished conversation may come to mind. So might tomorrow's meeting, a pending task or something that has been worrying you. You may also find yourself simply daydreaming.
We often assume that a quiet mind should mean an empty mind. It doesn't. When there is no constant stream of information coming from outside, the mind naturally moves towards memories, plans, emotions and thoughts that have been sitting in the background.
That isn't necessarily overthinking. It is part of normal mental activity. Sometimes we are so quick to distract ourselves that we don't give ourselves the opportunity to notice what we are actually thinking or feeling.
What Should Concern Us Is Fragmented Attention
There is another part of this conversation that gets overlooked. We often talk about screen time, but the way we use our screens matters too. Imagine someone working on an important task but checking WhatsApp every few minutes, responding to an email, looking at a notification and then returning to the original task. Even if the total phone usage doesn't look alarming, their attention has been repeatedly pulled away.
Over time, this can make uninterrupted concentration feel uncomfortable.
So instead of asking only, “How many hours am I on my phone?”, perhaps we should occasionally ask, “How often am I allowing my attention to be interrupted?”
Try The 10-minute Test
You don't need to give up your phone or spend an hour meditating. Start small.
Have your morning tea without a screen. Sit on the balcony. Take a short walk without headphones. Wait for five or 10 minutes without automatically reaching into your pocket.
Don't try to stop your thoughts. Just notice them. You may discover that you are more restless than you expected. Or perhaps you will find that your mind settles after a few minutes.
Either way, that is useful information. Mental wellbeing isn't only about learning how to manage stress when it becomes overwhelming. It is also about creating small pockets of time in which the brain isn't constantly being asked to consume, respond and move on.
In a world that has made every spare minute scrollable, being comfortable with a little silence may be a surprisingly valuable habit for the brain.
(Dr Neha Pandita, Senior Consultant Neurologist and Unit Head, Clinical Lead - Parkinson's disease & Movement Disorders, Fortis Hospital, Noida)
- Follow Us :


© $2026 Times Horizon Private Limited