
- Health Conditions A-Z
- Health & Wellness
- Nutrition
- Fitness
- Health News
- Ayurveda
- Videos
- Medicine A-Z
- Parenting
What Is Diabetes Insipidus, The Condition That Cannot Hold Fluid In Your Body?

Diabetes (Credit: Canva)
Diabetes insipidus (DI) is a rare medical condition that disrupts the body's ability to regulate water, resulting in excessive thirst and an unusually high volume of urine. This condition affects the kidneys' ability to concentrate urine and causes individuals to produce between 3 and 20 quarts of dilute, colourless urine daily, compared to an average of 1 to 2 quarts. It is pertinent to note that DI is not related to diabetes mellitus, which disrupts the body's insulin production.
Types Of Diabetes Insipidus
Central Diabetes InsipidusThis condition results from damage to the hypothalamus or pituitary gland, which impairs the production or release of vasopressin, a hormone responsible for water retention. When vasopressin levels are inadequate, the kidneys fail to conserve water, leading to excessive urination. It can result from Brain injuries or surgeries, tumours, infections or inflammation and aneurysms.
Nephrogenic Diabetes Insipidus
This type occurs when the kidneys fail to respond to vasopressin, causing excessive fluid loss. Common triggers include chronic kidney disease, and electrolyte imbalances, such as high calcium or low potassium levels. Additionally, medications like lithium
and urinary tract blockages can also cause Nephrogenic DI.
Gestational Diabetes Insipidus
A rare condition seen only during pregnancy, this occurs when the placenta produces an enzyme that breaks down vasopressin or increases prostaglandin levels, reducing kidney sensitivity to the hormone. Symptoms of this are usually mild and often resolve postpartum but can recur in future pregnancies.
Symptoms And Warning Signs
- Severe thirst, often leading to the consumption of over a gallon of water daily
- Frequent urination (polyuria), sometimes exceeding 20 quarts per day
- Nighttime urination and bed-wetting
- Weakness, muscle pain, and preference for cold drinks
In severe cases, dehydration may develop, manifesting as fatigue, dizziness, dry mouth, confusion, nausea, or fainting. Infants and children with DI may exhibit crankiness, poor feeding, slow growth, fever, or vomiting.
Causes And Risk Factors
DI stems from issues with vasopressin production or response. Central DI arises from damage to brain structures, while nephrogenic DI relates to kidney dysfunction. Risk factors include:
- Genetic mutations affecting water regulation
- Certain medications like diuretics or lithium
- Metabolic disorders that alter calcium or potassium levels
- Brain injuries or surgeries
Diagnosis And Testing
Diagnosing DI involves a combination of medical history, physical exams, and specialized tests:
- Urinalysis: Evaluates urine concentration and glucose levels to distinguish DI from diabetes mellitus.
- Blood tests: Check electrolyte, glucose, and vasopressin levels.
- Water deprivation test: Measures changes in weight, blood sodium, and urine concentration during fluid restriction.
- MRI: Detects abnormalities in the hypothalamus or pituitary gland.
- Genetic screening: Identifies inherited risk factors.
Although DI is rare, affecting about 1 in 25,000 people, early diagnosis and targeted treatment can significantly improve quality of life. Researchers continue to explore its causes and treatments to better support those living with this challenging condition.
Perimenopause Is Not Just About Periods: The Metabolic Changes Women Should Know About
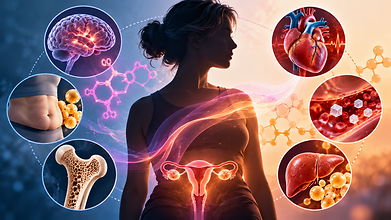
Credit: AI
When we think of perimenopause, irregular periods, hot flashes and mood changes usually come to mind. But the transition to menopause is not limited to the menstrual cycle. Behind the scenes, changing ovarian hormones—particularly fluctuating and eventually declining estrogen—can influence body composition, insulin sensitivity, cholesterol levels, bone health and cardiovascular risk.
For many women, these metabolic changes begin years before their final menstrual period.
Why does weight suddenly behave differently?
A common concern during perimenopause is: “I haven’t changed my diet, so why am I gaining weight around my abdomen?”
Ageing itself contributes to gradual loss of muscle mass and changes in energy expenditure. At the same time, the menopausal transition is associated with a shift in fat distribution, with a greater tendency to accumulate visceral or abdominal fat.
This matters because visceral fat is metabolically active. An increase in abdominal fat can be associated with insulin resistance, abnormal cholesterol levels and a higher risk of metabolic disease. So, the change in waist circumference may sometimes tell us more about metabolic health than the number on the weighing scale alone.
Also read: After Menopause, These Breast Changes Shouldn’t Be Ignored
Blood sugars may raise up too
Estrogen interacts with several pathways involved in glucose and fat metabolism. During midlife, changes in body composition, reduced physical activity, sleep disturbance and hormonal changes can collectively make insulin sensitivity less favourable.
This does not mean every woman going through perimenopause will develop diabetes. However, women who already have risk factors—such as overweight or obesity, prediabetes, a history of gestational diabetes or a strong family history of type 2 diabetes—should be particularly mindful.
Cholesterol and heart health deserve attention
The menopausal transition can also be accompanied by unfavourable changes in the lipid profile, including changes in LDL cholesterol. Cardiovascular risk increases with age, and menopause is an important time to reassess risk factors such as blood pressure, glucose, cholesterol, smoking, physical activity and body composition.
Women often spend years focusing on reproductive health while overlooking these equally important metabolic markers.
Also read: World Menopause Day: Is It Empty Nest Syndrome Or Menopause Symptoms? Expert Explains
Muscles and bones need attention as well
Midlife is also an important period for protecting muscle and bone. Declining estrogen after menopause accelerates bone loss, while ageing contributes to loss of muscle mass.
Resistance training therefore becomes especially valuable. Adequate protein intake, regular weight-bearing exercise, sufficient calcium and vitamin D, good sleep and avoiding smoking can support healthier ageing.
What should women do?
Perimenopause should not be viewed as a disease, nor should every symptom or kilogram gained in midlife automatically be blamed on hormones. Instead, it is an opportunity for a metabolic health check.
Women should discuss appropriate screening for blood pressure, blood glucose or HbA1c, lipid profile, weight and waist circumference monitoring , DEXA scan for bone health, depending on their individual risk factors.
Most importantly, don’t wait for menopause to start thinking about metabolic health. The perimenopausal years can be an important window to build muscle, improve fitness, optimise nutrition and identify metabolic risk early.
Perimenopause is more than a change in periods—it is a transition in whole-body health. Understanding these changes early can help women enter the next phase of life stronger, healthier and better prepared.
(By Dr. Seema Daksh, MBBS, MD (Internal Medicine), DM (Endocrinology), Consultant Endocrinologist,Kailash Hospital, Greater Noida)
Loud Snoring Is Not Always Harmless: Sleep Apnoea can Become a Stroke-Risk Concern

Credit: iStock
Loud habitual snoring is often dismissed as a nuisance or simply a part of sleeping. For some people, it may be an early warning sign of obstructive sleep apnoea, a condition in which breathing repeatedly slows or stops during sleep. When left unaddressed, sleep apnoea can quietly strain the heart and blood vessels, increasing the risk of blood pressure, irregular heart rhythms, heart attack and stroke.
Snoring happens when relaxed tissues in the throat vibrate as air moves through a narrowed airway. Not everyone who snores has a problem and occasional snoring is common. However loud and regular snoring, especially when a bed partner notices pauses in breathing, choking or gasping should not be ignored. It may indicate sleep apnoea, where the airway collapses repeatedly during sleep.
Each time breathing stops, oxygen levels drop. The brain briefly wakes the body up to restart breathing. Most people do not remember these interruptions but their body feels the effects. Over time, this cycle can disturb sleep, raise blood pressure, increase inflammation and put pressure on the cardiovascular system.
Also read: ‘Godzilla’ Drug Retatrutide Reverses Sleep Apnea In 1 In 4 Diabetes Patients
Risk factor & symptoms
Sleep apnoea is increasingly recognised as a risk factor for stroke. It can worsen hypertension. Contribute to atrial fibrillation, an irregular heartbeat that raises the likelihood of a stroke. The concern becomes greater in people who already have conditions such as diabetes, obesity, high cholesterol or a family history of heart disease.
For them, untreated sleep apnoea may add to the strain on the heart and blood vessels. A landmark study by the All India Institute of Medical Sciences (AIIMS) New Delhi estimates that roughly 104 million Indians suffer from Obstructive Sleep Apnea (OSA), with about 47 million cases classified as moderate to severe.
There are also signs that should prompt a conversation with a doctor. Waking up unrefreshed despite spending hours in bed, feeling excessively sleepy during the day, experiencing morning headaches, and struggling to concentrate or becoming unusually irritable can all be linked to poor-quality sleep caused by sleep apnoea. If snoring is accompanied by any of these symptoms a sleep study may be recommended to confirm whether it is snoring or a more serious breathing disorder.
Remedies
The reassuring part is that sleep apnoea is treatable. Depending on its cause and severity, doctors may suggest weight management where relevant, avoiding alcohol and sedatives close to bedtime, treating congestion, changing sleep position, using an oral appliance or undergoing CPAP therapy, which keeps the airway open during sleep.
The message is not to worry about every snore but to take loud snoring seriously particularly when it comes with breathing pauses or daytime tiredness. Early diagnosis can improve sleep, energy and overall quality of life while helping reduce long-term risks to the heart and the brain.
Perimenopause & Cardiovascular Health: Why Neglecting Heart Warning Signs During Perimenopause Can Lead to Heart Issues

Credit: iStock
Perimenopause is often described as a transition marked by hot flashes, mood swings and irregular periods. Because these changes are common, many women simply accept them as an inevitable part of ageing. But the years around menopause are also an important turning point for cardiovascular health.
The connection is partly hormonal. As ovarian function changes, oestrogen levels fluctuate and eventually decline. Oestrogen has several favourable effects on the cardiovascular system, including effects on blood vessels, cholesterol metabolism and vascular function. Its decline does not suddenly “cause” heart disease, but it can coincide with changes in blood pressure, cholesterol, body fat, glucose metabolism and vascular health that collectively increase cardiovascular risk.
When Menopause Symptoms Could Signal A Heart Problem
Not every symptom during perimenopause is cardiac. Hot flashes, night sweats, sleep disturbance, anxiety and palpitations are common. However, new, severe or unusual symptoms deserve attention—particularly in women who have cardiovascular risk factors.
Chest discomfort is one symptom that should never automatically be attributed to menopause. Women may experience coronary disease differently from the classic crushing chest pain often described in men. Pressure, tightness, burning or discomfort in the chest, upper abdomen, back, jaw or arms may occur. Breathlessness, unusual fatigue, nausea, sweating or light-headedness can also accompany cardiac problems.
Palpitations And Irregular Heartbeats: When To Seek Help
Similarly, repetitive palpitations should not simply be labelled as hormonal. Perimenopausal fluctuations, stress, poor sleep and hot flashes can increase awareness of the heartbeat, but persistent rapid or irregular heartbeats, particularly when associated with dizziness, fainting, chest discomfort or breathlessness, warrant evaluation.
Increase in Blood pressure is another important warning sign. Hypertension is often silent, and women may discover it incidentally during this period. Repeated elevated readings should be assessed rather than attributed to stress.
Oestrogen influences the endothelium—the inner lining of blood vessels—and contributes to healthy vascular function. During the menopausal transition, hormonal fluctuations and eventual oestrogen decline occur alongside changes in lipid metabolism and body composition.
LDL cholesterol may rise, while HDL and triglyceride patterns can also change. Fat distribution often shifts towards the abdomen, even without a dramatic change in overall body weight. Muscle mass may decline and insulin resistance can increase.
Blood pressure may also rise with age. Sleep disruption, reduced physical activity, stress and changes in diet can further compound these effects.
It is important, however, not to think of menopause as a single switch that suddenly transforms a woman from low-risk to high-risk. Traditional risk factors like obesity, diabetes, smoking etc can increase the risk profile. Menopause is better understood as a period when existing risk factors may become more apparent or begin to accelerate.
Also read: Times Network India Health Summit 2026 Key Takeaways: AI, Fertility, AYUSH, Cancer Care And More
Prevention should begin before menopause
The menopausal transition provides an excellent opportunity for a cardiovascular “health audit.”
Know your numbers. Blood pressure, fasting glucose or HbA1c, lipid profile and weight/waist circumference should be assessed according to individual risk. A woman with diabetes, hypertension, kidney disease, premature menopause or a strong family history of premature coronary disease may require more intensive assessment.
Keep moving. Regular aerobic activity combined with resistance training is particularly valuable. Brisk walking, cycling, swimming or similar activities can be complemented by strength training two or more times a week. Physical activity helps control blood pressure, glucose, weight and cholesterol while preserving muscle mass.
Pay attention to diet. A heart-healthy dietary pattern should emphasise vegetables, fruits, legumes, whole grains, nuts, seeds and appropriate sources of protein, while limiting highly processed foods, excess sugar, refined carbohydrates, trans fats and excessive salt. Alcohol should be limited.
Do not smoke. Smoking substantially increases cardiovascular risk, and stopping at any age provides meaningful benefit.
Protect sleep and manage stress. Insomnia and night sweats are common during perimenopause, but persistent sleep deprivation can adversely affect blood pressure, glucose regulation, appetite and overall cardiovascular health. Treating significant sleep problems is therefore part of cardiovascular prevention—not simply improving.
Menopausal hormone therapy (MHT) should not be viewed as a treatment for preventing heart attacks. Its cardiovascular effects depend on factors such as age, timing relative to menopause, the formulation used, route of administration and a woman’s underlying cardiovascular and thrombotic risk.
For women with troublesome menopausal symptoms, the decision about MHT should therefore be individualised after discussing benefits, risks and alternatives with an appropriately qualified clinician. Hormone therapy should not be started solely for cardiovascular protection.
A new perspective on menopause
Perhaps the most important message is that perimenopause should not be regarded simply as a collection of symptoms to be endured. It is also an opportunity to identify cardiovascular risk.
The hormonal transition is natural. Cardiovascular disease is not inevitable. Recognising this window as an opportunity for prevention can help women enter the postmenopausal years with a healthier heart—and with a clearer understanding that caring for cardiovascular health is an essential part of healthy ageing.
- Follow Us :


© $2026 Times Horizon Private Limited