
- Health Conditions A-Z
- Health & Wellness
- Nutrition
- Fitness
- Health News
- Ayurveda
- Videos
- Medicine A-Z
- Parenting
What Is Chikungunya And How Can It Be Prevented?

Chikungunya Disease and Prevention (Credits-Freepik)
Overview
This is a disease that is transmitted from mosquitoes to humans and affects many people in the world. Found in densely populated countries and continents, like Africa, Asia and the tropics of the Americas, this has severe symptoms. This viral disease is caused by the Chikungunya virus of the Togaviridae. First identified in the United Republic of Tanzania in 1952 and subsequently in other countries like Africa and Asia. Since 2004 the outbreak of CHIKV virus has become more widespread and caused partly due to the viral adaptations allowing the virus to be spread more easily by Aedes albopictus mosquitoes. The transmission has been noted to persist in countries where there is a large population, but interestingly, the transmission has been interrupted on islands where a high proportion of the population is infected and then immune.
Symptoms
The onset of the disease is usually in 4-8 days and after a bite of an infected mosquitoes, it is characterized by an abrupt onset of fever and then joint pain. This joint pain is severed and lasts for a few days but may prolong for months maybe even years. Other signs are joint swelling, muscle pains, headache, nausea, fatigue and rash. These symptoms also overlap with those of dengue and Zika virus and can be misdiagnosed. Most people fully recover from the infection and experience only mild and sometimes the infection even goes unrecognized. However, there have been cases of eye, heart, and neurological complications. The elderly and newborns are more susceptible to the infection and if they have any underlying conditions then they are likely to become severely ill increasing the risk of death.
Diagnosis and treatment
The diagnosis and treatment of the virus may be done by blood sampling and other tests like reverse transcriptase–polymerase chain reaction (RT–PCR). Other tests detect the activity of the antibodies. These can be detected in the first week after illness onset and can be detected for about 2 months. Many clinical measures can be taken to address fever and joint pain. But there is no specific anti-viral drug treatment for the virus.
Preventing Chikungunya
As this disease is caused by the bite of a mosquito, you must reduce the opportunities to let the mosquito breed. Mosquitoes bite during the day and night, and for people who live in risk areas like southeast Asia, Africa and tropical regions of America, many outbreaks happen each year. The best way to prevent it is to protect yourself from the mosquito's bite. You also must get vaccinated before travelling to any of these regions. Use insect repellent, and wear long-sleeved shirts and pants. You can also treat your clothes and gear with permethrin. As we all know, they tend to breed in humid places and places where they have access to water, so try to close the rooms that are air-conditioned with screens and windows. Use nets and mosquito repellents if you are sleeping outside. There are many different types of mosquito repellents like paper, liquid etc, and they are quite effective. If your job needs, you to be stationary for long hours or frequently go outside you must take the necessary precautions.
Radiotherapy Cuts Risk Of Atypical Meningioma Recurrence By Nearly Half: Lancet Study
Credit: AI
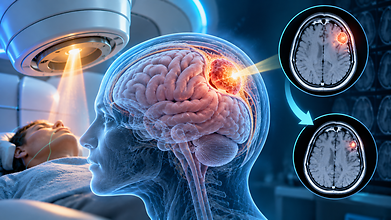
After surgery, radiotherapy could significantly decrease the chances of an atypical meningioma returning, according to a new international phase 3 trial published in The Lancet.
The findings come from the ROAM/EORTC-1308 trial, the first randomised controlled trial to directly test whether patients with a completely removed atypical meningioma benefit from receiving radiotherapy or whether regular scans and observation are enough.
The results could help settle a treatment question that has remained uncertain for years.
What Is An Atypical Meningioma?
Meningiomas are the most common brain tumours in adults. They develop from the meninges, the protective membranes surrounding the brain, and spinal cord.
An atypical meningioma is classified as a WHO grade 2 tumour. Unlike grade 1 meningiomas, that generally grow slowly, grade 2 tumours are more likely to grow again after surgery.
Even when surgeons manage to remove the entire visible tumour, microscopic tumour cells may remain, sparking a risk of recurrence.
Also read: The Gynecological Cancer Symptoms Women Often Mistake for “Normal” Ageing Like
What Did The Lancet Study Find?
The ROAM/EORTC-1308 trial enrolled 157 patients whose atypical meningiomas had been completely removed surgically. They were randomly assigned to either:
- Radiotherapy: 78 patients received 30 sessions of radiotherapy
- Observation: 79 patients underwent regular imaging surveillance
After a median follow-up of about five years, the difference in recurrence was significant. 14% of patients in the radiotherapy group experienced a recurrence, compared to 30% in the observation group. In other words, the risk of recurrence was reduced by nearly half with postoperative radiotherapy.
Additionally, at five years, about 80% of patients receiving radiotherapy remained free of recurrence, compared to about 64% of those who were monitored without immediate radiotherapy.
Also read: After 70% of His Tongue Was Removed For Cancer, Lawyer Regains Speech & Returns To Court
The Trial Cements Necessary Evidence
Until now, doctors have had to weigh two approaches after complete surgical removal of an atypical meningioma.
One option is to give radiotherapy immediately, hoping to destroy microscopic tumour cells that surgery may have missed. The other is to monitor the patient with regular brain scans and use radiotherapy if the tumour returns.
The uncertainty existed as strong randomised evidence showing whether immediate radiotherapy actually reduced recurrence had been lacking. The trial helps cement that evidence.
Who Needs Radiotherapy After Surgery?
The researchers say that treatment decisions still need to be made jointly by doctors and patients, taking into account possible side effects and the long-term consequences of radiation treatment. Serious radiation-related complications were uncommon in the trial.
The study also did not establish whether the recurrence benefit extends beyond five years. This means that longer follow-up will be needed to gather more evidence. According to the researchers, the findings are expected to shape national and international treatment guidelines.
The options may extend for patients who have undergone complete removal of a WHO grade 2 atypical meningioma. Rather than contemplating “Should we simply watch and wait?”, they can consider moving to a more evidence-based discussion about whether postoperative radiotherapy should be offered upfront.
How Technology & Newer Cardiac Procedures Are Transforming Heart Care

Credit: iStock
Heart care has been revolutionized in recent decades. New imaging tools, less invasive procedures, implantable devices and digital instruments are allowing doctors to find problems earlier and with more detail. This means that treatment options tend to be more personalized and recovery time can be shortened.
A big part of this shift comes from new tech in heart testing. Doctors can see how big the heart is, what shape it is and how it moves using cardiac CT, MRI and echo. These tests can give specific information on the functioning of the heart. AI is also being looked at for tasks like reading ECG results, analysing heart scans, and tracking patients over time. The American Heart Association says AI may have uses across heart care. At the same time, many tools still need more proof in real clinical settings before they are widely used.
From Open Surgery To Less Invasive Heart Procedures
Also read: Don’t Miss a Beat: Why Every Newborn Deserves a Heart Check
Tech is also changing how some heart issues are handled. In the past, some cases needed full open surgery. Now, for certain patients, doctors may use catheter-based or minimally invasive methods instead. Take TAVR as an example. In that approach, a new aortic valve is placed using a catheter. It is positioned inside the older, damaged valve. For the right group of patients, this can avoid open surgery.
Device design is moving forward too. Newer cardiac devices are adding options for people with rhythm problems and other heart conditions. Leadless pacemakers are one example. These devices are meant to support heart rhythm in an effective way while reducing some drawbacks seen with older device types.
Wearables And Remote Monitoring: The Next Step In Heart Care
Remote monitoring and wearable tools are growing fast. Some devices can track things like heart rate all day. That can reveal issues that someone might not notice on their own. Still, these tools should sit alongside routine checkups. They should not be used to diagnose yourself.
At the end of the day, the goal is not to swap out a cardiologist for a machine. Tech should help doctors gather clearer data. It can also support more accurate procedures. It may even spot disease earlier than before. What treatment makes sense varies from person to person. Doctors weigh age, past health, how bad the condition is, the test results, and the overall level of risk. As new heart devices keep coming, doctors will need solid proof and good judgment about who should use them. That is how new ideas lead to real gains in heart care.
That Small Shadow On The Lung: Why Finding Out Matters
Credit: iStock
She came to the hospital because of a cough that would not go away. The cough was eventually found to be nothing serious. But her CT scan revealed something unexpected — a 12 mm nodule in the outer part of her right lung.
She had never smoked. She felt completely well.
Yet that tiny shadow raised a big question: was it an old tuberculosis scar, a harmless growth, or an early lung cancer?
A CT scan can show us that a nodule is there. It cannot always tell us what it is.
This is an increasingly familiar situation. As CT scans have become more widely used, particularly after the COVID-19 pandemic, doctors are finding small lung nodules in people being scanned for entirely different reasons. Most turn out to be benign. Some, however, need closer assessment.
India has another challenge. Tuberculosis and its scars are common, and a lung shadow can sometimes be attributed to TB without tissue confirmation. While treating tuberculosis promptly is important, assuming that every suspicious nodule is TB can occasionally delay the diagnosis of something else, including cancer.
The answer, when appropriate, is to obtain a tissue sample.
Traditionally, a small nodule deep in the lung could be difficult to reach. A needle biopsy through the chest can be effective but carries a risk of a collapsed lung. Conventional bronchoscopy is excellent for the larger airways but becomes more challenging as the target gets smaller and farther towards the edge of the lung. Surgery may sometimes be necessary.
Newer techniques are changing the picture.
Navigation bronchoscopy uses the patient's CT scan to create a three-dimensional map of the airways and guide a thin catheter towards the nodule. Cone Beam CT adds real-time three-dimensional imaging during the procedure, allowing the doctor to check where the instruments are in relation to the lesion before taking the biopsy.
In simple terms, navigation helps us find the way; Cone Beam CT helps us confirm we are there.
The tissue can then be examined immediately where appropriate, helping determine whether the sample is adequate and whether additional material is needed for advanced testing.
Importantly, not every nodule needs a biopsy. Many are best managed through carefully planned follow-up scans. The decision depends on the nodule's size and appearance, previous scans, and the patient's overall risk.
For patients, the message is reassuring: a lung nodule does not mean cancer. But it should not be ignored either.
Keep previous scans. Ask what the likely possibilities are. Understand why your doctor recommends surveillance or biopsy — and make sure the follow-up happens.
Today, advanced bronchoscopy is helping doctors turn a worrying shadow into something much more useful: an answer.
(By Dr Shyam Krishnan, Intervention Pulmonologist, CMRI)
- Follow Us :


© $2026 Times Horizon Private Limited