
- Health Conditions A-Z
- Health & Wellness
- Nutrition
- Fitness
- Health News
- Ayurveda
- Videos
- Medicine A-Z
- Parenting
What Is Blue Light? How Does It Impact Sleep?

Blue Light (Credit: Canva)
Blue light emitted by devices like smartphones, computers, and televisions is becoming a major factor disrupting our sleep cycles. Research reveals that a significant number of Americans use electronic devices close to bedtime, contributing to poor sleep quality. Reducing exposure to blue light, particularly in the evening, is a simple yet effective way to help your body prepare for restful sleep.
What Is Blue Light?
Blue light is part of the visible light spectrum and is emitted by natural and artificial sources like the sun, fluorescent lights, LED lights, and digital screens. This wavelength is known for influencing our alertness, mood, and sleep patterns. During the day, blue light plays a role in regulating circadian rhythms, helping us stay alert and focused. However, exposure to it in the evening can have a detrimental effect on sleep quality.How Does Blue Light Impact Circadian Rhythms?
Circadian rhythms are 24-hour cycles that control essential bodily functions, including sleep. Light is the primary factor that aligns these rhythms with day and night. Historically, exposure to sunlight during the day helped set our body clocks, signaling when to be awake and when to sleep. However, the widespread use of artificial lighting and electronic devices has introduced more light exposure after dark, disrupting these natural cycles.
Blue light, in particular, has the strongest impact on circadian rhythms. During daylight hours, blue light helps us feel alert by stimulating the brain, raising body temperature, and increasing heart rate. But in the evening, exposure to blue light can confuse the body’s internal clock, suppressing melatonin—the hormone responsible for making us feel sleepy. As a result, our brains may remain in “daytime mode,” preventing us from winding down for the night.
Health Consequences Of Disrupted Sleep
Persistent disruption of circadian rhythms can lead to a range of health issues, including metabolic disorders, poor mental health, and increased risk for conditions like depression and anxiety. Furthermore, the inability to sleep well at night affects cognitive performance, mood, and overall well-being. Chronic exposure to blue light in the evening may significantly contribute to these negative health outcomes.
Devices That Emit Blue Light
Many common devices in our daily lives emit blue light, including:
- Smartphones and tablets
- Computer monitors and laptops
- Televisions and e-readers
- LED and fluorescent lighting
- Video game consoles
How To Minimize Blue Light Exposure
To reduce the effects of blue light on your sleep, here are some practical strategies:
1. Turn off screens before bed: Try to avoid using electronic devices at least two to three hours before bedtime. Reducing screen time helps prevent blue light from interfering with melatonin production.
2. Adjust your lighting: Dim your home’s lights or switch to warmer-toned lighting in the evening. You can also use lamps with red or orange light, which are less likely to impact your circadian rhythms.
3. Night mode settings: Many smartphones and computers have a "night mode" feature that reduces blue light emission. Make use of these features to limit exposure in the hours leading up to bedtime.
4. Blue light-blocking glasses: Special glasses designed to filter out blue light may be helpful for some individuals. These glasses can block or reduce the melatonin-suppressing effects of blue light.
5. Apps for blue light reduction: There are several smartphone and computer apps available that reduce blue light emission, allowing you to use your devices before bed without disturbing your sleep.
6. Create a sleep-friendly environment: If you can’t control light sources in your bedroom, consider using an eye mask to block out ambient light and promote better sleep.
US Woman’s Pancreatic Cancer Spotted On Routine Heart Scan: How It Saved Her Life
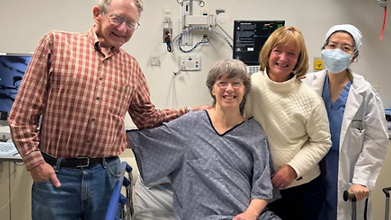
Credit: Vicky Titcomb
A routine heart scan helped doctors detect pancreatic cancer in a 72-year-old US woman before it was too late. Vicky Titcomb, a Cape Cod bookstore owner and great-grandmother, underwent the scan at Mass General Brigham in March 2025, before traveling to New York City to visit her son.
Although she felt healthy, the scan revealed an abnormality on her pancreas. Further testing confirmed pancreatic cancer, one of the deadliest forms of cancer, CBS News reported.
“I felt like my life just switched in that moment,” Titcomb said. “It was a very weird feeling.”
Titcomb had undergone treatment for breast cancer in 2012.
In 2025, she was diagnosed with stage 1 breast cancer as well as pancreatic cancer. Doctors also found a mass on her ovary, which proved benign after the ovary was removed.
Why Early Detection Matters In Pancreatic Cancer
Pancreatic cancer is often diagnosed after it has spread to other organs. Its five-year overall survival rate is 13%.
The American Association for Cancer Research noted in its 2026 Cancer Progress Report that pancreatic cancer survival rates have shown little improvement despite advances in cancer care.
Doctors at Mass General Brigham planned chemotherapy and radiation to shrink Titcomb’s pancreatic tumor before surgery.
“I was told the size of the (pancreatic) cancer was about the size of a grape. The goal, to me, was trying to make this cancer a raisin,” she said. “That's the way I visualized it.”
The plan was to perform a Whipple procedure, a complex operation that removes the head of the pancreas, part of the small intestine, the gallbladder and the bile duct. Only about one in five pancreatic cancer patients is eligible for this surgery.
Titcomb’s early diagnosis made the operation possible.
“If I had not had that scan when I did, the outcome would have been bad,” she said.
Chemotherapy, Radiation And Surgery
Titcomb began chemotherapy in June 2025, receiving eight doses over four months. She then underwent three weeks of radiation and additional chemotherapy.
Surgical oncologist Dr. Thomas Clancy said she tolerated the treatment “very well.” The therapy shrank the pancreatic tumor enough for surgery.
On November 4, Titcomb underwent surgery to treat her breast cancer. Just over two weeks later, Clancy performed a robotic Whipple procedure to remove the affected part of her pancreas and other structures.
The operation was successful, and Titcomb said she was walking that night. She returned home after several days in the hospital.
Although she was recovering well, Clancy recommended two more months of chemotherapy because pancreatic cancer can be aggressive.
“There was a lot going on,” Titcomb said. “I just tried to cope with the day-to-day.”
No Evidence Of Cancer After Treatment
In March 2026, after further treatment, Clancy told Titcomb she had no evidence of cancer. She will continue to undergo scans every three months.
“She’s living her life. I generally tell patients at this point, ‘You’re done with therapy ... you go about your days,’” Clancy said. “The goal is to not be thinking about it all the time.”
Titcomb is returning to running her bookstore, which family members helped manage during her treatment. She is also spending time with her children, grandchildren and great-grandchildren, keeping in touch with those who live far away through photos, videos and phone calls.
World Arthritis Day - Arthritis At 42, 62 & Even 15: How Treatment & Rehabilitation Help Patients Regain Mobility

Credit: AI
Arthritis can affect people at different stages of life, limiting their ability to walk, climb stairs or carry out everyday activities with ease. While treatment largely depends on the extent of joint damage and the patient's condition, treatment approaches ranging from joint-preserving surgery to knee and hip replacement can help restore mobility. Rehabilitation still remains an essential part of recovery.
On World Arthritis Day, doctors explain how arthritis is treated and managed at different ages using real-life cases and highlighting how they assess joint damage, choose strategies and use physiotherapy to help patients return to their routines.
Knee Preservation Before Replacement
A 42-year-old man with grade 3 osteoarthritis in his right knee had been experiencing pain and locking. His symptoms began after a knee injury six years earlier and worsened with time. X-rays revealed marked varus alignment, cartilage and meniscus damage. Earlier consultations had suggested knee replacement, but given his age, doctors opted for knee preservation surgery.
Dr. Tapish Ravindra Shukla, Consultant Orthopaedics and Sports Medicine, Fortis Escorts Hospital, Amritsar, told HealthandMe that he performed three procedures in a single sitting: high tibial osteotomy to correct alignment and shift weight away from the damaged inner compartment, bone marrow aspirate concentrate (BMAC) to treat the cartilage defect, and meniscus repair.
The patient walked with a walker for approximately three weeks, began jogging at six weeks and was running by three months.
The case brings us to an important point, i.e., assessing whether a damaged joint can be preserved, especially in younger patients who may otherwise face joint replacement early in life.
When Hip Replacement Becomes Necessary?
In another case, a patient developed pain in both hips after recovering from a major head injury. During prolonged rehabilitation, he had received steroids and anti-epileptic medication for an extended period. He was subsequently diagnosed with bilateral avascular necrosis, a condition in which compromised blood supply damages bone and can lead to joint destruction.
Initially, doctors performed core decompression to relieve pressure within the affected bone and attempt to preserve the joints. The patient experienced relief and continued his routine activities for nearly two years.
However, following a minor slip and fall, the pain returned. Further evaluation and X-rays showed significant progression of arthritis, prompting a recommendation for total hip replacement.
Dr. P Keerthivasan, Senior Consultant and Spine Surgeon, Kauvery Hospital, Alwarpet, Chennai, explained to us the importance of understanding the condition, accepting when treatment needs to change and planning for recovery. Following hip replacement, the patient began mobilising the next day and progressed well during the immediate recovery period.
The case illustrates that joint-preserving procedures may provide relief in selected patients, but progressive joint damage can make replacement necessary.
Also read: Joint Pain In Your 30s And 40s: When Should You Worry?
Knee Replacement To Improve Quality Of Life
A 65-year-old woman with osteoarthritis in both knees had severe pain and difficulty walking, climbing stairs and performing daily activities. She had become dependent on painkillers, raising concerns about potential kidney damage with prolonged use. Doctors recommended total knee replacement.
Dr. Rishabh Tiwari, Consultant (JR), Orthopaedics, and Dr. Vivek Allahbadia, Consultant, Orthopaedic Surgery, P.D. Hinduja Hospital & Medical Research Centre, Khar, treated the patient using a minimally invasive technique in which the tendon was lifted rather than cut. The posterior cruciate ligament (PCL) was also preserved.
According to the doctors, these approaches can help reduce postoperative pain, limit bone loss and provide a more natural feel to the replaced knee.
The patient could lift her leg on the night of surgery. The following day, she was walking with full weight-bearing, bending and straightening her knee, and using the washroom independently. Training to climb stairs began on the second day, and she was discharged that day.
At one-and-a-half months, she could perform daily activities without pain and travel independently to nearby friends and relatives. The case stresses upon how surgical technique and early mobilisation can contribute to a patient's return to everyday activities.
In another case of knee replacement, a 62-year-old woman with severe osteoarthritis in both knees had spent nearly four years avoiding stairs, temples and long walks with her grandchildren. Pain, stiffness and fear of falling had increasingly restricted her activities. “She stopped joining family outings because I couldn’t keep up,” she told her doctor.
Dr. Bhushan Shitole, Consultant Orthopaedic Surgeon and Director at Vencer Hospital, told us that he recommended robotic-assisted total knee replacement using an imageless robotic system. The technology creates a three-dimensional plan of the joint before surgery and helps the surgeon plan implant positioning according to the patient's anatomy.
“Robotic planning lets us match the implant to the patient’s unique anatomy so the first steps after surgery are already better aligned,” Dr. Shitole said. “That first confident walk is often the real turning point.”
Following surgery, the patient began walking with minimal support within days. Structured physiotherapy focused on strength, balance and gait training. By the end of the first month, she was moving independently at home. Three months later, she boarded a cruise she had postponed.
“The robot didn’t just replace my knee. It gave her back the confidence to live the life she wanted,” Dr. Shitole said.
The case highlights that recovery involves more than replacing the damaged joint. Regaining balance, strength and confidence is also central to returning to normal activities.
Severe Arthritis In Children
Arthritis and joint destruction are not restricted to older adults. A 15-year-old boy with Morquio syndrome, a rare genetic disorder affecting skeletal development, developed severe arthritis in both hips. Pain and complex hip deformities made walking and everyday activities difficult.
Because of his small skeletal anatomy and the complexity of the deformities, doctors opted for staged bilateral hip replacements. The surgical team used CT scans to create a three-dimensional printed model of the pelvis and specialised R.I Hip software to simulate the procedures virtually. This helped them select correct sized implants, plan positioning and anticipate physiological challenges.
The two hip replacements were performed three days apart. The boy was able to stand and walk with support the day after each procedure.
The treating doctor, Dr. Vaibhav Bagaria, Director, Orthopaedics- Sir HN Reliance Foundation Hospital, Mumbai, told us that rehabilitation played a huge role.
“A successful joint replacement restores the mechanics of movement, but rehabilitation helps restore the confidence to move. Both are equally important for meaningful recovery, ” he said.
Physiotherapy focused on progressive walking, muscle strengthening, balance and functional independence, with the programme tailored to the boy's underlying skeletal condition.
The case also highlights the additional considerations involved in treating young patients, including implant longevity and the possibility of revision surgery in the future.
Across these cases, treatment ranged from procedures intended to preserve a joint to partial or total replacement of severely damaged joints. The choice depended on the patient's age, the extent of joint destruction, associated conditions and the likelihood of preserving function.
Rehabilitation was central to each case. Early mobilisation helped patients use their joints after surgery, while physiotherapy helped with strength, balance, walking and daily independence.
Flu Vaccine: Why October Is A Good Time To Get Your Family Vaccinated

Credit: iStock
With flu season setting in across countries, including the US and the UK, doctors are urging people to get their annual flu shots. October offers an opportunity to build protection before winter flu activity increases.
The UK Health Security Agency (UKHSA) reported above-average flu activity and urged at-risk groups to get vaccinated. England's flu vaccination program last winter is estimated to have prevented about 100,000 hospital admissions and 7,000 deaths.
The US Centers for Disease Control and Prevention (CDC) recommends annual flu vaccination for everyone aged six months and older. The seasonal vaccine targets influenza A(H1N1), A(H3N2) and B/Victoria viruses.
In September, the Indian Medical Association (IMA) also highlighted annual influenza vaccination and gaps in adult immunization.
Why Is October A Good Time To Get Vaccinated?
Also read: Flu Activity Rises Early In US, UK And Japan: Why Experts Urge Vaccination Before Winter
The flu vaccine takes about two weeks to build protection, making October a good time to get vaccinated before winter, Dr. Bhawna Malik, Senior Consultant-Neonatologist and Pediatric Intensivist at Motherhood Hospitals, Greater Noida, told HealthandMe.
In India, flu activity can increase between January and March. Vaccination in October allows time for immunity to develop before this period.
However, October is not the only option. Dr. Vikas Maurya, Senior Director and HOD, Pulmonology, Fortis Hospital, Shalimar Bagh, told HealthandMe that vaccination can also be taken between April and mid-June, ahead of another period of flu activity from July to September.
He said one dose annually is generally sufficient, with timing depending on local flu patterns and the vaccine used.
Who Should Get The Flu Vaccine?
Healthy adults and children, as well as people with underlying conditions, can benefit from flu vaccination. Influenza can cause pneumonia, hospitalization and other severe complications.
Older adults, particularly those aged 65 and above, and people with diabetes, heart disease, kidney or liver disease, asthma or chronic obstructive pulmonary disease (COPD) face a higher risk of complications.
“Flu vaccination doesn't protect just yourself against the risk of having influenza but it also prevents transmission of infection to other vulnerable people around ourselves like little ones, elderly family members and people with medical conditions,” Dr. Malik said.
Dr. Mohit Bhardhwaj, Consultant, Pulmonology, PB Health, Gurugram, told HealthandMe that annual vaccination helps protect individuals and reduce transmission, as flu viruses change and vaccine protection can decrease over time.
Flu Vaccine Schedule For Children And Adults
Read More: Flu 2026: Symptoms To Watch For As New Season Begins
The vaccine can be administered from six months of age. The schedule depends on age and previous vaccination history.
- Children aged six months to eight years: Some children receiving the vaccine for the first time need two doses at least four weeks apart.
- Children aged nine and above: Annual vaccination is generally recommended.
- Adults: One dose each flu season is generally recommended.
- Infants younger than six months: Cannot be vaccinated directly.
Dr. Malik recommends vaccination for parents, siblings and caregivers to help reduce the risk of transmitting influenza to infants who are too young to receive the vaccine.
Are There Any Side Effects?
Most flu vaccine side effects are mild and may include injection-site pain, redness or swelling, fever, headache, body aches and tiredness. These generally settle within a few days, Dr. Bhardhwaj said.
A cooling pack or an ice pack wrapped in cloth may help relieve injection-site discomfort. Nasal vaccines may cause a stuffy nose, cough or headache, Dr. Maurya noted.
The injected flu vaccine cannot cause influenza. Anyone experiencing persistent fever, breathing difficulty or unusual symptoms should seek medical advice. Those with a history of serious allergic reactions to a previous flu vaccine should consult their doctor before vaccination.
- Follow Us :


© $2026 Times Horizon Private Limited