
- Health Conditions A-Z
- Health & Wellness
- Nutrition
- Fitness
- Health News
- Ayurveda
- Videos
- Medicine A-Z
- Parenting
What Happens To Your Body When You Hold Your Pee For Too Long?

Have you ever been in a situation where you felt like you needed to pee but could not use a restroom? A lot of times, especially in public, during an office meeting or an interview, we come across such circumstances, while sometimes we hold pee to not embarrass ourselves socially, or just because of the lack of facilities. Doing that often may not be good for our health.
How much pee can a person hold?
The urinary bladder is a hollow, pear-shaped organ that forms part of the urinary system. The bladder's role while is to store urine, it also releases once the limit is crossed, which is around one pint or two cups of liquid. However, under certain circumstances, it can stretch to hold more than this.
We start to fee the urge to urinate when it is filled halfway.
What can happen if you hold your pee long too often?
When you hold your pee too often, your bladder stretches and the muscle weakens. As time pass by, it can become difficult for your bladder to empty it completely. This can lead to urinary retention, and being unable to fully emptying your bladder.
Discomfort Due To Holding Pee
Pain
Ignoring the urge to pee regularly can lead to pain or discomfort in the bladder or kidneys. When you eventually make it to the bathroom, urinating might feel painful.
Additionally, the muscles involved in holding urine may remain partially tense even after you’ve emptied your bladder, potentially causing pelvic cramps.
Urinary Tract Infection
One of the most common discomforts caused by holding in pee for too long is Urinary tract infection. It can cause bacteria to multiply.
As per the Urology Care Foundation, people should avoid holding in pee for extended periods, as it increases the risk of UTIs. Dehydration, poor personal hygiene, and certain medications can also increase the risk of developing a UTI.
Common symptoms of a UTI include:
- A burning or stinging sensation during urination
- Pain in the pelvis or lower abdomen
- A persistent urge to urinate
- Strong or foul-smelling urine
- Cloudy or discolored urine
- Consistently dark urine
- Blood in the urine
Bladder Stretching
As mentioned before, in long run, regularly holding in pee could cause the bladder to stretch and make it difficult or sometimes, impossible for the bladder to contract and release pee.
If someone has a stretched bladder, sometimes, extra measures like a catheter could also be necessary.
Damage to Pelvic Floor Muscles
Regularly holding in urine can strain and potentially damage the pelvic floor muscles.
One key muscle, the urethral sphincter, helps keep the urethra closed to prevent leaks. Damage to this muscle may lead to urinary incontinence. Performing pelvic floor exercises, like Kegels, can help strengthen these muscles, repair damage, and reduce the risk of leakage.
Kidney Stones
For individuals prone to kidney stones or those with high mineral levels in their urine, holding in pee may contribute to stone formation. Urine naturally contains minerals like uric acid and calcium oxalate, which can crystallize and form stones over time.
Adenomyosis: When The Uterine Lining Grows Into The Muscle
Credit: iStock
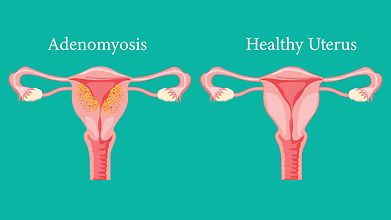
Adenomyosis is a condition that can affect younger women too. It is not limited to women in their 30s or 40s, although it becomes more common with age. Pooja, a 39-year-old pilot, noticed her periods becoming heavier and more painful. Increasing bleeding left her exhausted, while pelvic pain began interfering with daily life. Further evaluation and imaging revealed adenomyosis. Treatment helped bring her bleeding and pain under better control.
Symptoms such as heavy periods, painful cramps and pelvic discomfort may be caused by adenomyosis, a benign condition in which tissue similar to the uterine lining grows into the muscular wall of the uterus. It is sometimes mistaken for endometriosis because the symptoms can be similar. However, the two conditions are different, although they can occur together.
Adenomyosis can occur across different age groups. Nearly 1 in 10 women with subfertility may have isolated adenomyosis, while pooled studies suggest it may be found in almost 1 in 2 women presenting with pelvic pain.
It can also affect women who are not planning pregnancy. A woman in her 40s or 50s may notice increasingly heavy periods, severe cramps or pelvic pressure that begins interfering with work and daily life. Even after years of having periods without major problems, a sudden change in bleeding or pain should not simply be dismissed as ageing.
What Exactly Is Adenomyosis?
The uterus has an inner lining called the endometrium and a muscular layer called the myometrium. Normally, these layers remain separate. In adenomyosis, tissue similar to the endometrium is found within the muscular wall.
This tissue responds to hormonal changes during the menstrual cycle, contributing to inflammation and thickening of the uterine muscle. The uterus may become enlarged and tender, and periods may become heavier or more painful.
Adenomyosis vs Endometriosis: What’s the Difference?
The main difference between the two conditions is where the tissue grows. In adenomyosis, tissue similar to the uterine lining grows into the muscle wall of the uterus. In endometriosis, similar tissue grows outside the uterus, commonly around the ovaries, pelvic lining and other pelvic organs.
Adenomyosis is more commonly associated with heavy or prolonged menstrual bleeding, severe cramps and pelvic pressure. Endometriosis may more commonly cause pelvic pain, painful periods, pain during sex, or pain during bowel movements or urination, particularly around periods.
However, symptoms can overlap, and both conditions can affect fertility. Therefore, symptoms alone cannot reliably distinguish between them.
What Are the Symptoms?
Some women with adenomyosis have no symptoms, while others experience problems that affect their work and daily activities.
Common symptoms include:
- Heavy or prolonged menstrual bleeding
- Severe period cramps
- Pelvic pain or pressure
- Pelvic tenderness
- Pain during intercourse
- Fatigue associated with heavy bleeding
Heavy bleeding can eventually cause iron-deficiency anaemia, resulting in tiredness, weakness and reduced energy. Adenomyosis may also be identified during an evaluation for difficulty conceiving.
Who May Be At Risk?
Adenomyosis is more commonly diagnosed in women in their 30s and 40s. Previous childbirth, caesarean section and certain uterine surgeries or procedures may be associated with a higher likelihood.
However, these are not requirements, and adenomyosis can occur without them. Age or medical history alone should not be used to rule it out.
Preety, a 32-year-old housewife, was being evaluated for difficulty conceiving. During her fertility assessment, imaging suggested adenomyosis. Her doctors considered her symptoms and reproductive goals while planning treatment.
Her case highlights an important point: adenomyosis does not look the same in every woman, and treatment cannot follow a one-size-fits-all approach.
How Is Adenomyosis Diagnosed and Treated?
Diagnosis usually begins with a detailed discussion about symptoms and medical history, followed by a gynaecological examination where appropriate.
Ultrasound is commonly used as the first imaging investigation, while MRI may be recommended for a more detailed assessment.
Treatment depends on individual needs. There is no single treatment suitable for every woman with adenomyosis. Doctors consider symptom severity, age, overall health, response to previous treatments and, importantly, whether she wants to become pregnant now or in the future.
Management may include medicines to control pain or bleeding, hormonal treatments and, in selected cases, procedures or surgery. Hormonal IUDs may also be considered for women who are not currently planning pregnancy. In severe cases, hysterectomy may be considered when future pregnancy is not desired.
Women planning pregnancy may require a different approach from those who have completed their family.
The goal is to control symptoms, protect quality of life and address reproductive goals.
Don’t Normalise Debilitating Periods
A major challenge with adenomyosis is that its symptoms can be normalised. A woman may spend years believing that extremely heavy bleeding or debilitating cramps are simply part of having periods. They should not automatically be ignored.
If periods become significantly heavier, pain worsens, bleeding causes fatigue or anaemia, or pelvic pain interferes with daily life or fertility plans, a consultation with a gynaecologist can help identify the underlying cause.
Adenomyosis is benign, but living with its symptoms does not have to be accepted as normal. Recognising the signs, getting evaluated and choosing treatment based on individual needs can help women regain control of their reproductive health and quality of life.
(By Dr Kanchi Khurana, Associate Director – Department of Fertility at Cloudnine Group of Hospitals, Chandigarh)
Breast Cancer Awareness Day: Experts Explain Most Overlooked Breast Changes That Can Delay Diagnosis In Men
Credit: AI
Breast cancer in men is far less common than in women. So there are a lot of factors that drive delay in breast cancer diagnosis in men. A breast lump in a man is dismissed as a fatty deposit, a hormonal change or something that happens only to women. However, men have breast tissue too, so overlooking warning signs can delay diagnosis.
On Breast Cancer Awareness Day, four experts spoke to HealthandMe about the breast changes men should watch for, why the disease is detected late, how to identify suspicious lumps from benign breast enlargement, and which men face a higher risk.
Besides misinformation and misconception, Dr Deepak Jha, Chief, Surgical Oncology and Breast Surgery, Artemis Hospital, Gurugram, pointed towards an important societal factor that can delay breast cancer diagnosis in men.
Dr. Jha said, “Embarrassment and fear of judgment can also put men off seeking medical advice.”
Breast Cancer Awareness Day: Breast Changes Should Men Never Ignore
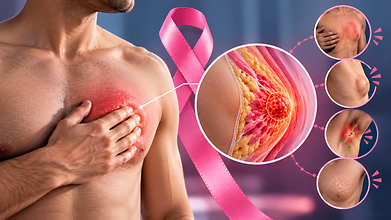
A lump is not the only warning sign of breast cancer in men. Changes in the nipple, surrounding skin and underarm area may also warrant medical evaluation.
Dr Ankur Bahl, Principal Director, Medical Oncology, Fortis Cancer Institute, Defence Colony, explains that breast cancer can sometimes present with changes in the nipple or surrounding skin without an obvious lump.
“Men should watch for changes such as nipple inversion, unusual discharge, particularly blood-stained discharge, persistent redness, skin dimpling, ulceration or changes in the shape of the breast. Swelling in the underarm area may also warrant evaluation,” he told us.
Dr Jha, highlights thickening in the breast, even when there is no distinct lump, which is an overlooked sign of breast cancer.
“Cancer can sometimes start with subtle signs that are often disregarded. Even though pain is not a typical early sign of breast cancer, persistent pain should not be ignored,” he said.
Dr Kanav Kumar, Consultant Surgical Oncology, Head and Neck Cancer Institute of India, also urges men to pay attention to changes around the nipple and breast skin.
“Men should look out for changes in the nipple or the skin around the breast, even if they cannot feel a lump. Warning signs include the nipple turning inward, unusual or blood-stained nipple discharge, redness, scaling, skin dimpling or sores that do not heal. Swelling in the armpit or near the collarbone should also be checked,” he said.
Dr Ritu Dave, Medical Oncologist and Hemato-Oncologist, M|O|C Cancer Care, Pune, too, identifies nipple inversion, bloody discharge, redness or scaling, skin dimpling, thickening, ulceration and changes in breast shape as signs requiring medical evaluation.
She said that these changes do not necessarily indicate cancer, but persistent or unexplained symptoms should not be ignored. Men should seek medical advice rather than wait for a lump to appear or for existing symptoms to worsen.
Why Is Breast Cancer Diagnosed Late In Men?
Low awareness and embarrassment contribute to delays in diagnosing male breast cancer. Many men do not consider the disease a possibility and may dismiss early symptoms as harmless.
Dr Bahl explains that men may delay seeking medical advice because of the assumption that breast cancer affects only women. He adds that symptoms may be neglected until a lump enlarges. Dr Jha points to a similar problem, stating that men may mistake a breast lump for a fat deposit, a hormonal change or a benign swelling.
Dr Kumar explains how these misconceptions can affect early detection. “Breast cancer is often seen as a woman's disease, so men may not recognise its symptoms or consider it a possibility. Some may dismiss a lump as harmless or delay seeing a doctor because of embarrassment or a lack of awareness,” he said.
Another important factor is the absence of routine screening for the general male population. As Dr Dave explains, “There is also no routine mammography screening for the general male population.”
This means that male breast cancer is often investigated only after symptoms become noticeable. Dr Dave also highlights an anatomical consideration: “Because men have less breast tissue, a tumour can reach the skin or nipple relatively early.”
Breast Cancer Or Gynecomastia?
Not every breast lump in a man is cancerous. Gynecomastia, a non-cancerous enlargement of male breast gland tissue, is a common alternative explanation. It may be caused due to hormonal changes or certain medications.However, men should not rely on how a lump feels to determine whether it is harmless.
Dr Bahl explains the typical differences between the two conditions. “Gynecomastia, or enlargement of breast tissue in men, commonly causes a rubbery or firm, often disc-shaped area directly beneath the nipple. It may affect one or both breasts and can be tender. A suspicious lump may feel hard.” he said.
Dr Jha also said that a cancerous lump is more likely to be hard, painless, irregular and present on one side, sometimes away from the nipple. Nipple inversion, bloody discharge, skin dimpling and underarm swelling are additional warning signs he flagged.
Which Men Are At Higher Risk Of Breast Cancer?
Although male breast cancer is uncommon, certain genetic and lifestyle factors can increase the risk. Dr Bahl said increasing age, strong family history of breast or ovarian cancer, inherited BRCA1 or BRCA2 gene mutations, Klinefelter syndrome, previous chest radiation, liver disease, obesity and conditions associated with prolonged oestrogen exposure as relevant risk factors.
Dr. Kumar said, “The risk increases with age, particularly after 50.”
Other factors include previous radiation treatment to the chest and certain liver or testicular conditions. Dr Jha also identifies obesity and certain testicular disorders among the factors that require attention.
Dr Dave highlights the importance of identifying men with inherited mutations or a family history, who may need more monitoring.
She said, “Men with significant family history or inherited mutations should discuss genetic counselling and an individualised monitoring plan with their doctor. Routine mammography is not recommended for all men.”
Men with these risk factors should discuss these factors with their specialists. Depending on their medical and family history, genetic counselling, testing or personalised testing may be suitable.
Also read: US Woman’s Pancreatic Cancer Spotted On Routine Heart Scan: How It Saved Her Life
Tests Needed To Rule Out Breast Cancer In Men
When a man presents with specific breast changes, doctors begin with a clinical examination and an assessment of his medical and family history.
Dr Bahl explains that the initial evaluation includes examining the breasts and lymph nodes, followed by diagnostic imaging and a biopsy.
He said, “Depending on the findings and the patient's age, diagnostic imaging may include mammography and targeted ultrasound. If the examination or imaging raises suspicion, a core needle biopsy is generally performed to obtain tissue for pathological confirmation.”
Dr Jha explains why imaging alone may not be sufficient. “Imaging can show that a change is suspicious, but it cannot always prove cancer. Doctors usually diagnose it with a core needle biopsy, which removes a small piece of tissue,” he said.
The biopsy sample is examined to establish whether cancer is present. If the diagnosis is confirmed, further testing helps determine the type of cancer and treatment.
Dr Dave explains the role of additional tumour testing. “In case when cancer is diagnosed, further analysis of hormonal receptors and HER2 will be necessary,” she said.
Hormone receptor and HER2 results help doctors understand the tumour's features and design treatment. Depending on the clinical stage and findings, further investigations may be needed.
Dr Kumar stresses the importance of timely assessment, saying that the first step is a clinical examination, followed by mammography or ultrasound where indicated and a biopsy if the findings are suspicious.
Flu, COVID, RSV, Shingles Vaccines: Studies Link All 4 To Better Heart Health
Credit: AI
Vaccines against influenza, COVID-19, respiratory syncytial virus (RSV) and shingles are given to prevent infections. But new research suggests they may also help protect the heart, especially in older adults and people who already have cardiovascular disease.
A recent report published by The Washington Post speaks about the evidence of these four vaccines to lower rates of cardiovascular problems.
The evidence varies across vaccines, and not all studies establish that vaccination directly prevents heart disease. However, experts say preventing severe infections may help reduce the strain viruses place on the cardiovascular system.
“We’re beginning to understand the large number of problems these viruses can cause beyond, say, a cough and fever,” said Paul Heidenreich, a professor of cardiovascular medicine at Stanford Medicine, in the report.
Shingles Vaccine Linked To Lower Heart Disease
Shingles occurs when the varicella-zoster virus, which causes chickenpox, reactivates in the body. It can cause a painful rash and nerve pain. Research has also linked shingles to cardiovascular complications, including heart attacks and strokes.
A study published in Nature Medicine in August 2026 compared adults aged 60 and older who received the newer shingles vaccine, Shingrix, with those who received the older vaccine, Zostavax.
Over seven years of follow-up, people who received Shingrix had lower rates of ischaemic heart disease and heart failure than those who received Zostavax. The study did not prove that the vaccine caused the difference, but it added to earlier research on shingles vaccination and cardiovascular health.
A separate 2025 study of adults aged 50 and older also found an association between receiving two doses of Shingrix and a lower risk of stroke and heart attack.
Noreen Nazir, a cardiologist and co-author of recent American College of Cardiology guidance, described the new findings as “a really great addition to the literature”.
Flu Vaccine May Reduce Heart Attack Risk
Annual influenza vaccination is recommended for nearly everyone aged six months and older in the United States. Influenza can cause more than fever, cough and body aches. The infection can trigger inflammation, increase the strain on the heart and worsen cardiovascular disease.
According to The Washington Post, influenza infection was linked with a sixfold increase in hospitalisations for heart attacks during the week after a positive flu test.
The risk is concerning for people with existing heart disease. Severe influenza can worsen underlying conditions and increase the likelihood of cardiovascular complications.
William Schaffner, a professor of infectious diseases at Vanderbilt University Medical Center and a co-author of the American College of Cardiology paper, said people hospitalised with an underlying high-risk condition like heart disease are “much more likely to have a cardiovascular event”.
Also read: Washington Reports Human Bird Flu Case After Dairy Cattle Exposure: Should You Be Worried?
COVID-19 Vaccines May Help Prevent Heart Complications
COVID-19 can affect the cardiovascular system during and after infection. Complications include heart attacks, strokes, abnormal heart rhythms and pericarditis, which is inflammation of the sac surrounding the heart.
People with pre-existing heart conditions are also at greater risk of severe COVID-19. During the pandemic, people with heart disease were three times as likely to develop severe infection, according to the report.
Research has also linked COVID-19 infection to longer-term vascular changes. A 2025 study published in the European Heart Journal found an association between COVID-19 and early vascular ageing, a process in which arteries become stiffer and less elastic.
The report notes that updated COVID-19 vaccines have been approved in the United States for adults aged 65 and older and younger people with at least one underlying health condition that increases their risk of complications.
RSV Vaccine May Help Protect Older Adults With Heart Disease
Respiratory syncytial virus causes a respiratory illness in infants and young children, but it can also cause severe disease in older adults. RSV can also worsen existing cardiovascular conditions, including heart failure.
A study spanning five RSV seasons found that nearly one-quarter of adults aged 50 and older who were hospitalised with RSV experienced an acute cardiac event, often involving heart failure. Those who had a cardiac emergency had nearly twice the risk of severe outcomes compared to those who did not.
Schaffner said, “There continues to be a high risk of cardiovascular events even after you recover from these viral infections,” he said.
The US Centers for Disease Control and Prevention recommends a single dose of RSV vaccine for adults aged 75 and older and adults aged 50 to 74 who are at increased risk of severe RSV illness.
- Follow Us :


© $2026 Times Horizon Private Limited