
- Health Conditions A-Z
- Health & Wellness
- Nutrition
- Fitness
- Health News
- Ayurveda
- Videos
- Medicine A-Z
- Parenting
Using BMI To Classify People As Obese Is Flawed Say Experts

A new report published in The Lancet Diabetes & Endocrinology challenges the conventional definition of obesity, and urges a shift from the reliance on Body Mass Index (BMI) to a more nuanced approach. This is supported by over 50 global medical experts. The report also recommends splitting the term "obesity" into two categories: "Clinical obesity" and "Pre-clinical obesity". This aims to improve diagnosis and treatment for over a billion people worldwide living with obesity.
Clinically Obese
This applies to individuals whose obesity has progressed to a disease state, manifesting in organ damage, heart disease, type 2 diabetes, or other health complications. These individuals could also experience symptoms like breathlessness, joint pain, or impaired daily functioning. Treatment also involves medical interventions, including weight-loss medications or surgery.
Pre-Clinic Obese
Whereas the term "pre-clinic obese" refers to those who are overweight but not yet exhibiting health issues. While they may be at risk of developing obesity-related conditions, their organ function and overall health remain intact. What they need is preventive care, which includes dietary guidance, counselling, and regular monitoring to avoid and reduce future health risks.
What does the study say?
The study, led by Professor Francesco Rubino from King's College London emphasizes that obesity is not one-size-fits-all condition. This means it should rather be treated as a spectrum as some individuals maintain normal organ function despite being classified as obese. There are others who may face severe health complications too. However, the current method of calculating obesity based on BMI often leads to misdiagnosis or inadequate care.
The report also states that BMI, while is useful for analyzing population trends, is a flawed unit of measuring individual health. Therefore, there is a need to redefine obesity, and healthcare professionals can provide more precise care by distinguishing those who need immediate medical intervention and those who require preventive strategies.
Limitations of BMI, Why It Falls Short?
BMI is used to classify individuals as underweight, healthy weight, overweight, or obese based on their height and weight. It is calculated by dividing weight in kilograms by health in meters squared. However, there are reasons while it falls short.
•Muscle vs Fat: Athletes or muscular individuals often have high BMIs despite the low body fat
•Fat Distribution: BMI does not measure fat around the waist or organs, which could be more dangerous to one's health.
•Individual Health Variation: It also overlooks the specific health conditions such as heart diseases or diabetes, or any other, while evaluating a person's category in terms of weight.
ALSO READ: Is It Time To Say Goodbye To BMI?
Scope Of Study
By redefining obesity, the study could transform the approach to diagnosis and treatment. It can focus on individual health risks rather than BMI alone. Healthcare providers can also offer tailored care. This also will ensure hat weight-loss medications like Wegovy or Mounjaro are prescribed only to those who genuinely require it.
As per Professor Louise Baur from the University of Sydney, a Children's obesity expert said that this redefinition allows both adults and children to receive more appropriate care while reducing over-diagnosis and unnecessary treatments.
Patients Treated By Female Doctors Have Lower Risk Of Death, Study Finds

Credit: iStock
Does a patient’s chances of serious outcomes differ if they are treated by a female doctor? A recent study looks into this hypothesis to ascertain the difference between chances of a patient dying under a male and a female doctor.
According to the study, hospitalised patients treated by female doctors have a lower risk of dying within 30 days. They are also less likely to be re-hospitalised than those treated by male doctors. The study is published in JAMA Network Open.
"Past research has largely focused on surgical patients and the admitting physician only. Our findings add to the growing body of research examining the relationship between physician sex and patient outcomes, broadening the evidence beyond surgical care to a wider range of medical conditions and other physicians," says Dr. Angela Jerath, an ICES scientist, and Associate Professor, Department of Anesthesiology & Pain Medicine at the University of Toronto's Temerty Faculty of Medicine.
After analysing the health records of 958,150 adults admitted to hospitals in Ontario, Canada, between 2008 and 2022, researchers found that the 30-day mortality rate was 12.3% among patients treated by female physicians, compared to 13.7% among those treated by male physicians.
The findings also show a small difference in hospital readmissions. The 30-day readmission rate was 18.6% for patients treated by female doctors and 18.9% for those treated by male doctors.
The researchers examined outcomes across seven common medical conditions, including heart attacks, pneumonia and other acute illnesses.
They also considered the number of hospital days during which patients received care from female doctors, recognising that several doctors may be involved in a patient's treatment during an admission.
Patients Treated By Female Doctors Are Less Likely To Die In A 30-Day Period
Also read: Manosphere Is A Public Health Concern: Lancet Report Says Online Misogyny Harms Men's Mental Health
After accounting for patient, physician and hospital characteristics, treatment by a female physician was linked with 12% lower adjusted odds of death within 30 days compared to treatment by a male physician.
The researchers also found that for every 10% increase in the proportion of hospital days managed by female physicians, the adjusted odds of 30-day mortality decreased by 7%. This was observed for most medical conditions that were studied. Atrial fibrillation was the only exception.
The difference in mortality was also seen at longer follow-up periods. Patients treated by female physicians had lower mortality at 90 days and one year.
The findings were observed among both male and female patients. Female patients treated by female physicians had the lowest adjusted 30-day mortality rate in the analysis.
Why Patients May Have Better Outcomes With Female Doctors?
The study did not establish why patients treated by female physicians experienced better outcomes. However, the researchers discussed possible differences in clinical practice and communication.
Female physicians may be more likely to engage in patient-focused communication, spend more time with patients, follow clinical guidelines and involve colleagues in decision-making.
These practices could influence how symptoms are studied, treatment decisions are made and coordinated during hospitalisation.
"The goal is not to favour one group of physicians over another but to identify practices and behaviours that may help improve care across the health system," says Jerath.
"An important strength of this study is that, unlike surgical care, patients admitted to hospital for medical conditions are generally assigned physicians based on rotating schedules rather than patient or referring physician preferences, helping to minimize referral bias."
Retatrutide Vs Ozempic: Eli Lilly’s Experimental Drug Delivers More Than Double The Weight Loss
Credit: AI
Eli Lilly's experimental weight-loss drug retatrutide, being referred to as ‘Godzilla’, continues to outperform its rivals like Ozempic.
According to a recent head-to-head Phase 3 clinical trial involving adults with type 2 diabetes, it delivered more than twice the average weight loss achieved with Ozempic.
Ozempic Vs Retatrutide
Participants who took the highest dose of retatrutide lost an average of 20.9% of their body weight over 80 weeks, compared to 9.4% among those receiving Ozempic's highest approved dose for type 2 diabetes.
The trial, called TRANSCEND-T2D-2, involved more than 1,000 adults with type 2 diabetes. It compared once-weekly injections of retatrutide at doses of 9 mg and 12 mg with semaglutide, the active ingredient in Ozempic, at 2 mg.
At the end of 80 weeks, participants taking retatrutide 9 mg lost an average of 44.3 pounds (20.1 kg), while those receiving the 12 mg dose lost 47.4 pounds (21.5 kg). The Ozempic group lost an average of 20.9 pounds (9.5 kg).
The findings mark the first Phase 3 head-to-head comparison of retatrutide with another medicine in this class.
Also read: ‘Godzilla’ Drug Retatrutide Reverses Sleep Apnea In 1 In 4 Diabetes Patients
Retatrutide Also Improved Blood Sugar
The trial found that retatrutide also resulted in produced greater reductions in HbA1c, a measure of average blood glucose over approximately three months.
At 80 weeks, participants taking either dose of retatrutide recorded an average HbA1c reduction of 2.2%, compared to 1.8 % among those receiving Ozempic.
The experimental drug also resulted in greater improvements in cardiovascular risk factors like non-HDL cholesterol, triglycerides and systolic blood pressure.
Side Effects Of Retatrutide
The most commonly reported side effects of retatrutide were gastrointestinal symptoms like diarrhoea, nausea, constipation, vomiting and indigestion.
Diarrhoea was reported in 28.3% of participants receiving the 9 mg dose and 32.7% receiving 12 mg, compared to 26.4% in the Ozempic group. Nausea occurred in 21.2%, 23.8% and 21.3% of participants, respectively.
Researchers also reported a higher incidence of dysesthesia, an abnormal sensation that can include tingling, burning or skin sensitivity, among participants taking retatrutide.
Treatment discontinuation because of side effects occurred in 4.8% of the 9 mg group and 7.9% of the 12 mg group, compared to 2.7% of the Ozempic group.
More About Retatrutide
Retatrutide is a once-weekly injectable drug that targets three hormone receptors involved in regulating appetite, blood sugar and metabolism. They are GLP-1, GIP and glucagon.
GLP-1 helps regulate appetite and blood sugar while slowing the process of stomach emptying. GIP also plays a role in glucose regulation and insulin release. Glucagon is involved in controlling blood glucose and energy metabolism.
Ozempic, manufactured by Novo Nordisk, acts on the GLP-1 receptor. Eli Lilly's Mounjaro and Zepbound, which contain tirzepatide, target both GLP-1 and GIP receptors.
Retatrutide remains an investigational drug and has not been approved by the US Food and Drug Administration (FDA) or other regulatory authorities.
Eli Lilly plans to submit the drug for FDA approval in early 2027. The company said detailed results from the trial would be presented at a future medical meeting and published in a peer-reviewed journal.
Could GLP-1 Drugs Help Prevent Rupture Of Abdominal Aortic Aneurysm? Study Finds 46% Reduction In Risk
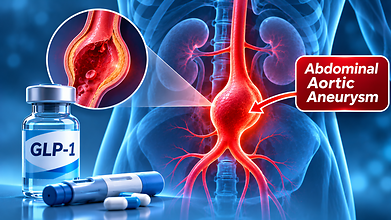
Credit: AI
The hype around GLP-1 weight loss drugs keeps growing due to numerous new benefits as well as side effects that are discovered every other day. A recent study found that the risk of aortic aneurysm rupture is significantly less among GLP-1 users. The study was published in the Journal of Vascular Surgery.
GLP-1 receptor agonists is a a class of medicines that is widely used to treat type 2 diabetes and obesity. Users have reported substantial weight loss results with the help of these medicines like Ozempic, Mounjaro, Zepbound and others.
Now, researchers have found that people with abdominal aortic aneurysms who used GLP-1 drugs had a 46% lower risk of rupture over five years compared with those who did not use these medicines. This means that GLP-1 drugs may also have cardiovascular benefit apart from diabetes and obesity.
The study analysed health records from 123 healthcare organisations in the US. It is based on more than 412,000 people diagnosed with abdominal aortic aneurysms who underwent imaging surveillance every six months.
After matching patients based on factors like age, sex, diabetes, high blood pressure, smoking, heart disease and kidney disease, the researchers compared 13,722 GLP-1 receptor agonist users with an equal number of non-users.
GLP-1 Drugs Linked To Fewer Aortic Aneurysm Ruptures
Also read: ‘Godzilla’ Drug Retatrutide Reverses Sleep Apnea In 1 In 4 Diabetes Patients
After five years, aortic aneurysm rupture was recorded in about 1.6% of people taking GLP-1 drugs, compared to 2.4% of those who were not taking them.
The researchers reported a hazard ratio of 0.538, indicating a 46.2% lower risk of rupture among GLP-1 drug users after adjustment.
The difference was also observed at the two-year mark, when rupture occurred in 1.1% of GLP-1 users compared to 1.8% of non-users.
People taking GLP-1 drugs also had fewer elective aneurysm repairs. At five years, 2.1% of users underwent elective repair compared to 3% of non-users.
The study further found lower rates of major cardiovascular events like heart attacks, strokes and heart failure, as well as lower all-cause mortality among GLP-1 users.
What Is An Abdominal Aortic Aneurysm?
An abdominal aortic aneurysm (AAA) occurs when a section of the aorta, the body's largest artery, becomes enlarged or bulges due to weakening of its wall. It develops in the part of the aorta that passes through the abdomen.
Many abdominal aortic aneurysms do not cause symptoms and are detected during tests. However, as the aneurysm enlarges, its risk of rupture increases.
A ruptured aneurysm is considered to be a medical emergency as it can cause severe internal bleeding. Symptoms may include sudden, severe abdominal or back pain, dizziness, fainting and a rapid heartbeat.
Smoking, older age, high blood pressure, atherosclerosis and a family history of aneurysms are among the risk factors.
GLP-1 Drugs & Lower Risk Of Aortic Aneurysm Rupture Risk
GLP-1 receptor agonists work by mimicking the naturally occurring GLP-1 hormone. They help regulate blood sugar by stimulating insulin release when glucose levels are high, slowing the emptying of stomach and reducing appetite.
Some of their effects may also impact blood vessel health. Abdominal aortic aneurysms develop through several processes, including inflammation, damage to vascular smooth muscle cells and changes in the proteins that maintain the artery wall.
GLP-1 drugs have shown anti-inflammatory and cardiovascular benefits in older research. The researchers suggest these effects may help explain the lower rates of aneurysm-related complications observed in the study.
The findings are promising but do not conclusively prove that GLP-1 medicines prevent aneurysm rupture. This was a retrospective observational study, meaning researchers examined existing health records rather than randomly assigning patients to receive the drugs.
One important limitation was that aneurysm size was not included among the matching variables. Since aneurysm size is a major determinant of rupture risk, differences between the groups could have impacted the findings.
- Follow Us :


© $2026 Times Horizon Private Limited