
- Health Conditions A-Z
- Health & Wellness
- Nutrition
- Fitness
- Health News
- Ayurveda
- Videos
- Medicine A-Z
- Parenting
The Parasitic Twin: Can You Be Born With A Human Attached To You?
Credits: Canva
Imagine this. A young teenager, 17, years old, who is fully developed. Now imagine this, the same teenager has a fully developed extra set of limbs and a pelvis. That extra set of pair is attached with chest artery. But, how can this happen?
While it is extremely rare, and has a chance of less than one case occurring per 100,000 births. Such things do happen. This is called parasitic twin.
What Is A Parasitic Twin?
It is an extremely rare type of cojoined twin where a baby is born with an underdeveloped twin attached to its body. This condition is also known as vestigial twins. The condition is very closely related to conjoined twins, where babies are connected at birth and share organs. However, the main difference is that in conjoined twins, there are two developed babies, whereas in parasitic twins, only one is fully developed, other one is underdeveloped and non functional.
In such a case, the twin who is developed is medically known as the autositic or the dominant twin. The dominant twin is healthy in most aspect but may have extra tissue, organs, or limbs from the parasitic twin.
The parasitic twin may be attached with the dominant twin through several places. The common joints are at the head, torso, chest, pelvis, buttocks, or back. In these cases, the parasitic twin is not alive and they die either in the womb or during the childbirth.
Doctors Remove Parasitic Twin
Now, let's go back to the case we referred to, where a young teenager had an extra pair of limbs attached to chest. The teenager who has not been named is from Uttar Pradesh's Unnao neighbourhood, and was treated in AIIMS, Delhi. The team of doctors successfully removed the extra set of limbs from his body.
Dr Asuri Krishna, who led the team of specialist who surgically removed the extra limbs told the BBC that only 40 to 50 cases of parasitic twins have been documented in world medical literature, and in those cases, the surgery had been attempted on children. The doctor said that without much medical literature to guide them, the team of doctors depended on "intuition, skill and knowledge".
The doctor shared that the child had two fully formed legs, buttocks and external genitalia, which weighed around 15kg "protruding from his abdomen".
How Was The Surgery Performed?
The doctor shared that first they identified how interconnected the parasitic and host twins were. The doctors took scans and found that parasitic twin was attached to the teen's breastbone. The blood was being supplied from a vessel in his chest. However, "there wasn't much connection with other main organs like the liver or kidneys," said Dr Krishna. The team also found a large cyst in the teen's abdomen.
Then the surgery was performed in two stages. In the first stage, the parasitic twin was removed. Then the cystic mass was extracted from the surrounded area. The entire surgery was completed in two and a half hours and the team of doctors included radiologists, anaesthetists, and plastic surgeons.
The biggest challenge was when the teen's blood pressure dropped as 30 to 40% of his blood flowed to the parasitic twin, however, the doctors were prepared for it and they stabilized him.
Perimenopause Is Not Just About Periods: The Metabolic Changes Women Should Know About
Credit: AI
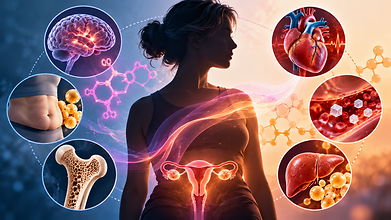
When we think of perimenopause, irregular periods, hot flashes and mood changes usually come to mind. But the transition to menopause is not limited to the menstrual cycle. Behind the scenes, changing ovarian hormones—particularly fluctuating and eventually declining estrogen—can influence body composition, insulin sensitivity, cholesterol levels, bone health and cardiovascular risk.
For many women, these metabolic changes begin years before their final menstrual period.
Why does weight suddenly behave differently?
A common concern during perimenopause is: “I haven’t changed my diet, so why am I gaining weight around my abdomen?”
Ageing itself contributes to gradual loss of muscle mass and changes in energy expenditure. At the same time, the menopausal transition is associated with a shift in fat distribution, with a greater tendency to accumulate visceral or abdominal fat.
This matters because visceral fat is metabolically active. An increase in abdominal fat can be associated with insulin resistance, abnormal cholesterol levels and a higher risk of metabolic disease. So, the change in waist circumference may sometimes tell us more about metabolic health than the number on the weighing scale alone.
Also read: After Menopause, These Breast Changes Shouldn’t Be Ignored
Blood sugars may raise up too
Estrogen interacts with several pathways involved in glucose and fat metabolism. During midlife, changes in body composition, reduced physical activity, sleep disturbance and hormonal changes can collectively make insulin sensitivity less favourable.
This does not mean every woman going through perimenopause will develop diabetes. However, women who already have risk factors—such as overweight or obesity, prediabetes, a history of gestational diabetes or a strong family history of type 2 diabetes—should be particularly mindful.
Cholesterol and heart health deserve attention
The menopausal transition can also be accompanied by unfavourable changes in the lipid profile, including changes in LDL cholesterol. Cardiovascular risk increases with age, and menopause is an important time to reassess risk factors such as blood pressure, glucose, cholesterol, smoking, physical activity and body composition.
Women often spend years focusing on reproductive health while overlooking these equally important metabolic markers.
Also read: World Menopause Day: Is It Empty Nest Syndrome Or Menopause Symptoms? Expert Explains
Muscles and bones need attention as well
Midlife is also an important period for protecting muscle and bone. Declining estrogen after menopause accelerates bone loss, while ageing contributes to loss of muscle mass.
Resistance training therefore becomes especially valuable. Adequate protein intake, regular weight-bearing exercise, sufficient calcium and vitamin D, good sleep and avoiding smoking can support healthier ageing.
What should women do?
Perimenopause should not be viewed as a disease, nor should every symptom or kilogram gained in midlife automatically be blamed on hormones. Instead, it is an opportunity for a metabolic health check.
Women should discuss appropriate screening for blood pressure, blood glucose or HbA1c, lipid profile, weight and waist circumference monitoring , DEXA scan for bone health, depending on their individual risk factors.
Most importantly, don’t wait for menopause to start thinking about metabolic health. The perimenopausal years can be an important window to build muscle, improve fitness, optimise nutrition and identify metabolic risk early.
Perimenopause is more than a change in periods—it is a transition in whole-body health. Understanding these changes early can help women enter the next phase of life stronger, healthier and better prepared.
(By Dr. Seema Daksh, MBBS, MD (Internal Medicine), DM (Endocrinology), Consultant Endocrinologist,Kailash Hospital, Greater Noida)
Perimenopause & Cardiovascular Health: Why Neglecting Heart Warning Signs During Perimenopause Can Lead to Heart Issues

Credit: iStock
Perimenopause is often described as a transition marked by hot flashes, mood swings and irregular periods. Because these changes are common, many women simply accept them as an inevitable part of ageing. But the years around menopause are also an important turning point for cardiovascular health.
The connection is partly hormonal. As ovarian function changes, oestrogen levels fluctuate and eventually decline. Oestrogen has several favourable effects on the cardiovascular system, including effects on blood vessels, cholesterol metabolism and vascular function. Its decline does not suddenly “cause” heart disease, but it can coincide with changes in blood pressure, cholesterol, body fat, glucose metabolism and vascular health that collectively increase cardiovascular risk.
When Menopause Symptoms Could Signal A Heart Problem
Not every symptom during perimenopause is cardiac. Hot flashes, night sweats, sleep disturbance, anxiety and palpitations are common. However, new, severe or unusual symptoms deserve attention—particularly in women who have cardiovascular risk factors.
Chest discomfort is one symptom that should never automatically be attributed to menopause. Women may experience coronary disease differently from the classic crushing chest pain often described in men. Pressure, tightness, burning or discomfort in the chest, upper abdomen, back, jaw or arms may occur. Breathlessness, unusual fatigue, nausea, sweating or light-headedness can also accompany cardiac problems.
Palpitations And Irregular Heartbeats: When To Seek Help
Similarly, repetitive palpitations should not simply be labelled as hormonal. Perimenopausal fluctuations, stress, poor sleep and hot flashes can increase awareness of the heartbeat, but persistent rapid or irregular heartbeats, particularly when associated with dizziness, fainting, chest discomfort or breathlessness, warrant evaluation.
Increase in Blood pressure is another important warning sign. Hypertension is often silent, and women may discover it incidentally during this period. Repeated elevated readings should be assessed rather than attributed to stress.
Oestrogen influences the endothelium—the inner lining of blood vessels—and contributes to healthy vascular function. During the menopausal transition, hormonal fluctuations and eventual oestrogen decline occur alongside changes in lipid metabolism and body composition.
LDL cholesterol may rise, while HDL and triglyceride patterns can also change. Fat distribution often shifts towards the abdomen, even without a dramatic change in overall body weight. Muscle mass may decline and insulin resistance can increase.
Blood pressure may also rise with age. Sleep disruption, reduced physical activity, stress and changes in diet can further compound these effects.
It is important, however, not to think of menopause as a single switch that suddenly transforms a woman from low-risk to high-risk. Traditional risk factors like obesity, diabetes, smoking etc can increase the risk profile. Menopause is better understood as a period when existing risk factors may become more apparent or begin to accelerate.
Also read: Times Network India Health Summit 2026 Key Takeaways: AI, Fertility, AYUSH, Cancer Care And More
Prevention should begin before menopause
The menopausal transition provides an excellent opportunity for a cardiovascular “health audit.”
Know your numbers. Blood pressure, fasting glucose or HbA1c, lipid profile and weight/waist circumference should be assessed according to individual risk. A woman with diabetes, hypertension, kidney disease, premature menopause or a strong family history of premature coronary disease may require more intensive assessment.
Keep moving. Regular aerobic activity combined with resistance training is particularly valuable. Brisk walking, cycling, swimming or similar activities can be complemented by strength training two or more times a week. Physical activity helps control blood pressure, glucose, weight and cholesterol while preserving muscle mass.
Pay attention to diet. A heart-healthy dietary pattern should emphasise vegetables, fruits, legumes, whole grains, nuts, seeds and appropriate sources of protein, while limiting highly processed foods, excess sugar, refined carbohydrates, trans fats and excessive salt. Alcohol should be limited.
Do not smoke. Smoking substantially increases cardiovascular risk, and stopping at any age provides meaningful benefit.
Protect sleep and manage stress. Insomnia and night sweats are common during perimenopause, but persistent sleep deprivation can adversely affect blood pressure, glucose regulation, appetite and overall cardiovascular health. Treating significant sleep problems is therefore part of cardiovascular prevention—not simply improving.
Menopausal hormone therapy (MHT) should not be viewed as a treatment for preventing heart attacks. Its cardiovascular effects depend on factors such as age, timing relative to menopause, the formulation used, route of administration and a woman’s underlying cardiovascular and thrombotic risk.
For women with troublesome menopausal symptoms, the decision about MHT should therefore be individualised after discussing benefits, risks and alternatives with an appropriately qualified clinician. Hormone therapy should not be started solely for cardiovascular protection.
A new perspective on menopause
Perhaps the most important message is that perimenopause should not be regarded simply as a collection of symptoms to be endured. It is also an opportunity to identify cardiovascular risk.
The hormonal transition is natural. Cardiovascular disease is not inevitable. Recognising this window as an opportunity for prevention can help women enter the postmenopausal years with a healthier heart—and with a clearer understanding that caring for cardiovascular health is an essential part of healthy ageing.
Why Halloween Can Be Scary for Your Heart and Lungs: Other Health Hazards to Watch

Credit: AI image
From haunted houses and sudden scares to sweet treats and costumes, Halloween fun can come with hidden health risks, particularly for people with existing heart and lung conditions.
Experts explain how sudden fright, excessive sugar and common activities on Halloween, observed on October 31, can affect heart and lung health.
How Sudden Scares Can Affect Your Heart
A sudden scare activates the body's sympathetic nervous system, raising heart rate and blood pressure while constricting blood vessels.
This response is usually harmless in healthy people, but may pose risks for those with arrhythmias, coronary artery disease or a history of stents or heart surgery.
A racing heartbeat should settle after the scare. Persistent palpitations, dizziness, shortness of breath, chest pain or tightness, nausea, sweating or fainting warrant medical attention, says Dr Mohamed Gabr, cardiologist and electrophysiologist at Baylor College of Medicine.
In addition, excessive consumption of sugar candies during Halloween can contribute to obesity, diabetes, high blood pressure and unhealthy cholesterol levels. Cholesterol and plaque buildup in the coronary arteries can begin at a young age.
Also read: You Feel Healthy. But Plaque May Already Be Building In Your Arteries In Your 20s
Halloween Activities That Can Trigger Asthma
Halloween activities can expose people with asthma to several triggers. Ragweed pollen, mould on damp fallen leaves and cold, dry air can worsen symptoms during autumn, according to the American Lung Association.
Fog machines and dry ice effects in haunted houses can release water droplets and chemicals, including glycol-based solvents, that may irritate airways. Glitter machines, bonfire smoke, dust from stored costumes and decorations, and strong fragrances can also trigger symptoms.
Dr Rubabin Tooba, a pulmonologist with Northwestern Medicine, says these exposures may cause coughing, wheezing, breathlessness and chest tightness, particularly in people with asthma, severe allergies or COPD. Tight-fitting masks can also make breathing difficult.
Fear, excitement and laughter may trigger asthma symptoms in some people. Trick-or-treating can bring additional exposure to pet dander, scented candles, cigarette smoke and fireplace fumes.
Pumpkin Carving And Halloween Injuries
Read More: Why Are Asthma Cases Rising Among Young Kids? Early Symptoms Parents Must Not Ignore
The US Consumer Product Safety Commission (CPSC) estimates that an annual average of 3,200 Halloween-related injuries were treated in US emergency departments over a recent three-year period.
Pumpkin carving accounted for 55% of these injuries, while 25% were related to falls while putting up decorations, tripping on costumes or walking while trick-or-treating. The remaining 20% involved lacerations, ingestions, allergic reactions and other costume- or decoration-related injuries.
Children younger than 18 years accounted for 46% of injuries, with approximately 10% occurring in children aged 6 years or younger.
The Plastic Hand Trauma Unit at Royal Devon and Exeter Hospital has also treated patients with deep cuts, severed tendons and nerve damage from pumpkin carving, BBC reported.
How Can You Stay Safe This Halloween
- Protect your heart: Be mindful of sudden scares if you have an existing heart condition. Seek medical attention for persistent palpitations, chest pain, breathlessness or fainting.
- Moderate candy: Limit sugary treats and consider fruit alternatives.
- Avoid asthma triggers: Ask about fog effects at haunted attractions and leave if you experience breathing discomfort.
- Check costumes and decorations: Clean stored items before use and discard anything with mould or a musty smell. Choose breathable, open-face masks.
- Use makeup carefully: Choose fragrance-free or hypoallergenic products and apply them in well-ventilated spaces.
- Carry asthma medication: Keep your prescribed quick-relief inhaler and spacer handy. Watch for coughing, wheezing or chest tightness, and take breaks when needed.
- Reduce infection risks: Practise good hand hygiene, stay home when sick and keep vaccinations up to date.
- Carve pumpkins safely: Avoid kitchen knives. Use pumpkin-carving kits with serrated tools and make small, controlled cuts.
- Follow Us :


© $2026 Times Horizon Private Limited