
- Health Conditions A-Z
- Health & Wellness
- Nutrition
- Fitness
- Health News
- Ayurveda
- Videos
- Medicine A-Z
- Parenting
Regular Blood Donation May Influence Cancer Risk
Credits: Canva
A recent study suggests that people who donate blood regularly may have genetic changes in their blood that could in fact reduce the risk of developing cancer. It is conducted by the researchers at the Francis Crick Institute, and the study has now provided new insights into how and why blood cancers develop. The study is published in the journal Blood and was conducted by the scientists from Heidelberg and the German Red Cross blood donation center. There is yet a need for further research to confirm these findings.
What Did The Study Find?
The researchers examined the blood of two groups of healthy male donors in their 60s:
- One group had donated blood three times a year for 40 years.
- The other group had donated only about five times in total.
The goal was to analyze genetic mutations in their blood and assess whether frequent donation had any impact on their genetic makeup.
How Can Blood Donation Affect Stem Cells?
As and when people age, their blood and other cells naturally develop mutations and some of them can also increase the risk of cancer. When anyone donates blood, his or her body compensates by producing new blood cells, which can influence the genetic diversity of stem cells in the bone marrow. The study also found that both groups had a similar number of mutations. For instance the frequent donors had 217 mutations, while the irregular donors had 212 mutations.
However, the nature of these mutations differed. In the frequent donors, 50% of the mutations were of a type not associated with a high risk of blood cancers, compared to only 30% in the irregular donors.
Further laboratory analysis showed that these specific mutations behaved differently from those linked to leukemia, a type of blood cancer. When human blood stem cells with these mutations were injected into mice, they were found to be highly effective at producing red blood cells, which is considered a positive outcome.
Dr. Hector Huerga Encabo, one of the study authors, emphasized that these mutations do not indicate an increased risk of leukemia. The findings suggest that regular blood donation may influence how stem cells evolve, but whether this translates into a lower cancer risk remains uncertain.
Read More: Who Can Donate Blood To Whom?
Limitations
One notable disadvantage is the "healthy-donor effect"—because blood donors are often healthier than the general population, their lower cancer risk could be unrelated to blood donation.
Dominique Bonnet, senior researcher and head of a stem-cell laboratory at the Francis Crick Institute, stressed the need for larger studies with female volunteers to confirm the findings.
Despite ongoing research into potential health benefits for donors, the primary goal of blood donation remains saving lives. NHS Blood and Transplant emphasized that while the study is interesting, further research is required to draw firm conclusions. The organization also noted that blood supplies are currently critically low and encouraged eligible individuals to donate.
Also Read: How Long After a Tattoo or Piercing Can I Donate Blood?
1 In 5 US Lung Cancer Patients Never Smoked: Report Highlights Hidden Risk Factors
Credit: AI
One of the most common contributing factors in lung cancer is smoking but a recent report suggests an alarming pattern in which cases among non-smokers are on the rise.
Pope Leo XIV was recently diagnosed with lung adenocarcinoma, a type of aggressive cancer that develops in the cells lining the lungs. He had no history of smoking. The 71-year-old pontiff underwent surgery to have part of his right lung lobe removed. According to reports, he is out of the hospital and recovering well.
Another case is of Stanford physician Bryant Lin whose stubborn cough led him to seek medical attention. After six weeks, he underwent an X-ray. The diagnosis stated that he had stage 4 lung cancer. Lin was less than a month away from turning 50, and he had never smoked a cigarette in his entire life.
“Definitely a shock,” Lin recalled according to The Washington Post. By the time doctors identified the cancer in spring 2024, it had spread to his liver, bones and brain.
According to the US Centers for Disease Control and Prevention (CDC), around 10% to 20% of lung cancers in the United States are reported in people who have never smoked or have smoked fewer than 100 cigarettes in their lifetime. That amounts to an estimated 20,000 to 40,000 cases annually.
For these patients, their no-smoking history can delay diagnosis and treatment. Hence, researchers are now looking into how environmental exposures, genetic causes and the biology of tumours may contribute to lung cancer in non-smokers.
Lung Cancer In People Who Have Never Smoked
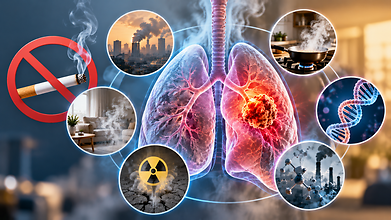
Smoking remains the leading risk factor for lung cancer. But other reasons like exposure to radon, secondhand smoke, air pollution and asbestos can also increase risk. Family history plays a role, especially when a first-degree relative has cancer before age 50.
Researchers are also examining genetic differences that may help explain why some people develop lung cancer despite never smoking.
A study published in September identified a rare genetic mutation concentrated in the southeastern United States that was associated with a 60-fold higher risk of lung cancer among never-smokers. The finding focuses on a possible role for inherited susceptibility, but it does not explain most cases in this group.
Lung cancer also has a different demographic profile among people who have never smoked. Women who have never smoked are more than twice as likely as their male counterparts to develop lung cancer, according to research cited by The Washington Post.
“Two-thirds of nonsmoking-related lung cancer happens in women, so there’s certainly an association with female sex,” said Jaclyn LoPiccolo, a medical oncologist at Dana-Farber Cancer Institute who co-authored the mutation study.
She added, “Nonsmoking-related lung cancer is also more common in people of East Asian descent, but whether that’s a genetic or environmental association, we don’t yet know.”
These Cancers Are Often Diagnosed Late
People who have never smoked may not recognise a persistent cough or other respiratory symptoms as signs of lung cancer. Doctors may initially consider more common explanations if the patient has no smoking history.
Never-smokers are often diagnosed late at more advanced stages of the disease because their doctors initially consider lung cancer to be less likely.
Haiying Cheng, a medical oncologist at Montefiore Einstein Medical Center in New York, said the stigma surrounding the disease can compound the problem. “A cancer diagnosis should never become a judgment about a patient,” Cheng said.
She added that clinicians need to consider assumptions beyond smoking when it comes to lung cancer and focus on the patient’s risk profile and tumour biology.
Lin is receiving antibody therapy targeting a cancer-driving mutation. He had a positive response to treatment.
“The treatment has done wonders for me,” he said. “When I was a medical student or resident, I would have never thought a Stage 4 lung cancer patient could be very productive and have a high quality of life almost two-and-a-half years after diagnosis.”
In the United States, the US Preventive Services Task Force recommends annual low-dose CT screening for adults aged 50 to 80 who have a smoking history. People who have never smoked are not included in these recommendations.
As researchers dig deeper into lung cancer chances in non-smokers, there is growing interest in different screening recommendations. Taiwan, for example, has a national early-detection programme offering low-dose CT scans to non-smokers with a family history of lung cancer.
Lin has urged his own sons to consider screening at a younger age. “I’ve got two sons, and I told them, ‘When you hit 45 or even 40, think about getting screened,’” he said.
Can Holding Your Urine During Long Office Hours or Traffic Jams Affect Urinary Health?
Credit: iStock
Holding urine occasionally, such as during a long meeting or traffic jam, is generally not harmful for most healthy adults. However, repeatedly delaying urination for extended periods may affect urinary health, particularly in people who are prone to urinary tract infections (UTIs) or have existing bladder problems.
What Happens When You Hold Urine for Too Long?
When urine remains in the bladder for too long, it can become uncomfortable and may contribute to bladder overdistension. In some individuals, particularly those with underlying urinary retention or bladder dysfunction, regularly postponing urination may worsen existing problems.
While holding urine does not directly cause a UTI in every case, incomplete bladder emptying can increase the risk of infection.
Also read: Are People With CKD At Higher Risk Of Dementia And Cognitive Problems?
Why You Should Not Reduce Water Intake to Avoid Bathroom Break
People who work long hours or commute frequently should try to respond to the urge to urinate rather than routinely suppressing it.
Maintaining adequate hydration is equally important, as deliberately drinking less water to avoid bathroom breaks can lead to concentrated urine and may increase the risk of certain urinary problems like concentrated urine leading to crystallization and stone formation.
When Should You Seek Medical Advice?
If you experience persistent urgency, burning during urination, lower abdominal discomfort, difficulty passing urine or blood in the urine, seek medical advice. Developing regular bathroom habits and ensuring convenient access to washrooms can help support long-term urinary health.
It is also important to recognise when urinary symptoms may indicate a more serious problem. Inability to pass urine despite a strong urge, particularly when accompanied by severe lower abdominal pain or swelling, requires urgent medical attention.
Fever, chills or pain in the back or side alongside urinary symptoms may indicate a kidney infection and should be assessed promptly. Avoid assuming that such symptoms are simply the result of holding urine for too long.
By Dr. Vikram Kalra, Principal Director - Nephrology and Kidney Transplant, Aakash Healthcare Multi Speciality Hospital, Dwarka
After Menopause, These Breast Changes Shouldn’t Be Ignored
Credit: AI
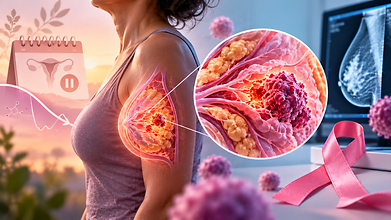
Menopause brings several changes to a woman’s body, and the breasts are no exception. As levels of oestrogen and other hormones decline, the glandular tissue in the breasts gradually decreases and is replaced by fatty tissue. This can change how the breasts look and feel.
For many women, breasts may become softer, less firm or change slightly in size and shape after menopause. Loss of skin elasticity with age can also contribute to changes in breast shape.
These changes can be a normal part of aging. But not every breast change after menopause should be attributed to hormones.
What breast changes can happen after menopause?
The hormonal changes associated with menopause can alter the composition of breast tissue. Some women may notice that their breasts feel softer or less dense than they did before menopause. Changes in skin elasticity can also lead to sagging or a gradual change in breast shape.
These changes, by themselves, are generally not a cause for alarm.
The concern arises when a new, unusual or persistent change appears, particularly if it is different from what a woman has experienced before.
Which breast changes should not be ignored?
After menopause, women should speak to a doctor if they notice:
- A new change in the size or shape of one breast
- A new lump or area of thickening in the breast
- Persistent swelling in the breast
- Dimpling, puckering or thickening of the breast skin
- A newly inverted or retracted nipple
- Unusual nipple discharge, particularly if it contains blood
- A change in the appearance of the nipple or areola
- A new lump or swelling in the armpit or near the collarbone
These signs do not necessarily mean that cancer is present. Several benign breast conditions can cause similar changes. However, they should not be self-diagnosed or automatically dismissed as a consequence of menopause.
What about breast pain?
Breast pain is commonly caused by benign conditions and, before menopause, may also be associated with hormonal fluctuations. After menopause, persistent or unexplained breast pain should nevertheless be discussed with a doctor, particularly if it occurs alongside another breast change.
It is also important to remember that the absence of pain does not rule out breast cancer. Many breast cancers do not cause pain, and some may not produce a lump that can be felt.
This is one reason women should not wait for pain or a clearly palpable lump before seeking medical advice when they notice something unusual.
Is breast cancer screening necessary after menopause?
Screening remains an important part of breast health after menopause, but the appropriate approach depends on factors such as age, family history, personal medical history and individual risk.
Women should discuss screening with their healthcare provider and follow recommendations appropriate to their age and risk profile. Every woman should also learn how to perform a self-breast examination and become familiar with the normal look and feel of her breasts. Regular self-examination can help women notice new or unusual changes early and seek medical advice promptly.
Self-breast examination should complement, rather than replace, recommended screening and clinical evaluation. If a woman notices a new lump, skin change, nipple change or any other unusual finding, she should consult a doctor even if her routine screening is due later.
Those with a strong family history of breast or ovarian cancer, or a known genetic predisposition to breast cancer, may require a different or more intensive screening strategy.
Importantly, screening is intended for women who do not have symptoms. If a woman notices a new breast change, she should not simply wait for her next routine screening appointment; she should discuss the change with a doctor.
Also read: Breast Cancer: Are Women in India Being Diagnosed Too Late?
Don't blame every change on menopause
Menopause is a natural stage of life, but it should not become an explanation for every new symptom.
Most breast changes are not cancerous. However, the only way to determine the cause of a persistent or suspicious change is through appropriate medical evaluation.
Women should become familiar with how their breasts normally look and feel and pay attention to changes that are new or unusual for them.
Breast health does not become less important after menopause. In fact, continuing to pay attention to changes, practising regular self-breast examination and staying up to date with appropriate screening can help detect problems early.
The message is not to fear every change, but to avoid ignoring one simply because menopause has begun. When something feels or looks different, getting it checked is always better than assuming it is “just menopause.”
By Dr. Tapti Sen, Sr. Consultant ,Breast Surgery, RG Stone Urology & Laparoscopy Hospital, Kolkata
- Follow Us :


© $2026 Times Horizon Private Limited