
- Health Conditions A-Z
- Health & Wellness
- Nutrition
- Fitness
- Health News
- Ayurveda
- Videos
- Medicine A-Z
- Parenting
Men Have Bigger Kidneys But Does That Mean Women Pee More?
Credit: Canva
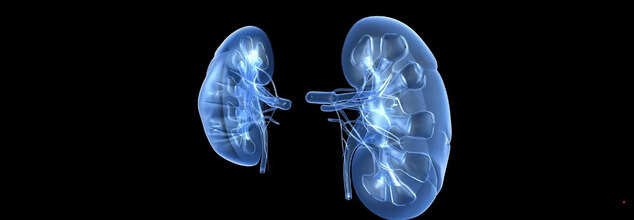
We’ve all heard the joke at some point — women take longer in the bathroom because they “pee more.” But is there any truth behind this bathroom stereotype? As it turns out, science is more complex than that, and the answer lies deep within the structure of our kidneys.
Biologically speaking, men generally have larger kidneys than women. But does that mean they produce more urine? Not necessarily.
A recent review of autopsy data has revealed some interesting findings. While men do tend to have physically larger kidneys, researchers aren’t entirely sure if this difference holds up once body size — such as height, weight, or body surface area (BSA) — is taken into account. In other words, just because a man has a bigger kidney doesn’t automatically mean it's more efficient or produces more urine.
Size Doesn’t Always Equal Output
Kidneys are vital organs responsible for filtering waste from the blood and maintaining fluid balance. Each kidney contains roughly a million nephrons — tiny filtering units that help produce urine. The number of nephrons is believed to be associated with kidney size. So, in theory, larger kidneys might have more nephrons and a higher filtering capacity.However, here's where it gets interesting: When kidney size is adjusted relative to body size, men may not actually have significantly larger kidneys than women. And in clinical settings, women often show better kidney health outcomes over time. Studies suggest that women are less likely to develop or progress to chronic kidney disease (CKD), even though they may report more frequent urination.
So Why Do Women Feel the Urge More Often?
The frequency of urination is influenced by several factors beyond kidney size — including bladder size, hormone levels, fluid intake, and even societal behavior. On average, women have slightly smaller bladders than men, which means they may feel the need to urinate more often, especially when consuming the same amount of fluids.Hormonal fluctuations during menstruation, pregnancy, or menopause also play a significant role in urinary patterns. Estrogen, for instance, affects the urinary tract and can make women more sensitive to the urge to go.
What It All Means
So, do women pee more than men? It depends. While they may urinate more frequently due to bladder size and hormonal factors, this doesn’t necessarily mean they produce more urine overall. The larger kidneys in men may be more efficient, but that doesn’t equate to more trips to the restroom.Ultimately, urination is a deeply personal — and variable — experience. If you find yourself making more frequent bathroom visits than usual, regardless of gender, it might be worth discussing with a healthcare provider.
Because when it comes to your health, every drop matters.
Perimenopause Is Not Just About Periods: The Metabolic Changes Women Should Know About
Credit: AI
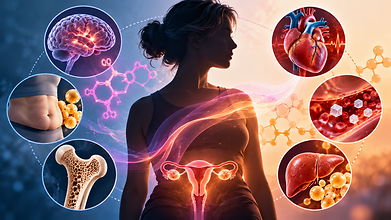
When we think of perimenopause, irregular periods, hot flashes and mood changes usually come to mind. But the transition to menopause is not limited to the menstrual cycle. Behind the scenes, changing ovarian hormones—particularly fluctuating and eventually declining estrogen—can influence body composition, insulin sensitivity, cholesterol levels, bone health and cardiovascular risk.
For many women, these metabolic changes begin years before their final menstrual period.
Why does weight suddenly behave differently?
A common concern during perimenopause is: “I haven’t changed my diet, so why am I gaining weight around my abdomen?”
Ageing itself contributes to gradual loss of muscle mass and changes in energy expenditure. At the same time, the menopausal transition is associated with a shift in fat distribution, with a greater tendency to accumulate visceral or abdominal fat.
This matters because visceral fat is metabolically active. An increase in abdominal fat can be associated with insulin resistance, abnormal cholesterol levels and a higher risk of metabolic disease. So, the change in waist circumference may sometimes tell us more about metabolic health than the number on the weighing scale alone.
Also read: After Menopause, These Breast Changes Shouldn’t Be Ignored
Blood sugars may raise up too
Estrogen interacts with several pathways involved in glucose and fat metabolism. During midlife, changes in body composition, reduced physical activity, sleep disturbance and hormonal changes can collectively make insulin sensitivity less favourable.
This does not mean every woman going through perimenopause will develop diabetes. However, women who already have risk factors—such as overweight or obesity, prediabetes, a history of gestational diabetes or a strong family history of type 2 diabetes—should be particularly mindful.
Cholesterol and heart health deserve attention
The menopausal transition can also be accompanied by unfavourable changes in the lipid profile, including changes in LDL cholesterol. Cardiovascular risk increases with age, and menopause is an important time to reassess risk factors such as blood pressure, glucose, cholesterol, smoking, physical activity and body composition.
Women often spend years focusing on reproductive health while overlooking these equally important metabolic markers.
Also read: World Menopause Day: Is It Empty Nest Syndrome Or Menopause Symptoms? Expert Explains
Muscles and bones need attention as well
Midlife is also an important period for protecting muscle and bone. Declining estrogen after menopause accelerates bone loss, while ageing contributes to loss of muscle mass.
Resistance training therefore becomes especially valuable. Adequate protein intake, regular weight-bearing exercise, sufficient calcium and vitamin D, good sleep and avoiding smoking can support healthier ageing.
What should women do?
Perimenopause should not be viewed as a disease, nor should every symptom or kilogram gained in midlife automatically be blamed on hormones. Instead, it is an opportunity for a metabolic health check.
Women should discuss appropriate screening for blood pressure, blood glucose or HbA1c, lipid profile, weight and waist circumference monitoring , DEXA scan for bone health, depending on their individual risk factors.
Most importantly, don’t wait for menopause to start thinking about metabolic health. The perimenopausal years can be an important window to build muscle, improve fitness, optimise nutrition and identify metabolic risk early.
Perimenopause is more than a change in periods—it is a transition in whole-body health. Understanding these changes early can help women enter the next phase of life stronger, healthier and better prepared.
Why Halloween Can Be Scary for Your Heart and Lungs: Other Health Hazards to Watch

Credit: AI image
From haunted houses and sudden scares to sweet treats and costumes, Halloween fun can come with hidden health risks, particularly for people with existing heart and lung conditions.
Experts explain how sudden fright, excessive sugar and common activities on Halloween, observed on October 31, can affect heart and lung health.
How Sudden Scares Can Affect Your Heart
A sudden scare activates the body's sympathetic nervous system, raising heart rate and blood pressure while constricting blood vessels.
This response is usually harmless in healthy people, but may pose risks for those with arrhythmias, coronary artery disease or a history of stents or heart surgery.
A racing heartbeat should settle after the scare. Persistent palpitations, dizziness, shortness of breath, chest pain or tightness, nausea, sweating or fainting warrant medical attention, says Dr Mohamed Gabr, cardiologist and electrophysiologist at Baylor College of Medicine.
In addition, excessive consumption of sugar candies during Halloween can contribute to obesity, diabetes, high blood pressure and unhealthy cholesterol levels. Cholesterol and plaque buildup in the coronary arteries can begin at a young age.
Also read: You Feel Healthy. But Plaque May Already Be Building In Your Arteries In Your 20s
Halloween Activities That Can Trigger Asthma
Halloween activities can expose people with asthma to several triggers. Ragweed pollen, mould on damp fallen leaves and cold, dry air can worsen symptoms during autumn, according to the American Lung Association.
Fog machines and dry ice effects in haunted houses can release water droplets and chemicals, including glycol-based solvents, that may irritate airways. Glitter machines, bonfire smoke, dust from stored costumes and decorations, and strong fragrances can also trigger symptoms.
Dr Rubabin Tooba, a pulmonologist with Northwestern Medicine, says these exposures may cause coughing, wheezing, breathlessness and chest tightness, particularly in people with asthma, severe allergies or COPD. Tight-fitting masks can also make breathing difficult.
Fear, excitement and laughter may trigger asthma symptoms in some people. Trick-or-treating can bring additional exposure to pet dander, scented candles, cigarette smoke and fireplace fumes.
Pumpkin Carving And Halloween Injuries
Read More: Why Are Asthma Cases Rising Among Young Kids? Early Symptoms Parents Must Not Ignore
The US Consumer Product Safety Commission (CPSC) estimates that an annual average of 3,200 Halloween-related injuries were treated in US emergency departments over a recent three-year period.
Pumpkin carving accounted for 55% of these injuries, while 25% were related to falls while putting up decorations, tripping on costumes or walking while trick-or-treating. The remaining 20% involved lacerations, ingestions, allergic reactions and other costume- or decoration-related injuries.
Children younger than 18 years accounted for 46% of injuries, with approximately 10% occurring in children aged 6 years or younger.
The Plastic Hand Trauma Unit at Royal Devon and Exeter Hospital has also treated patients with deep cuts, severed tendons and nerve damage from pumpkin carving, BBC reported.
How Can You Stay Safe This Halloween
- Protect your heart: Be mindful of sudden scares if you have an existing heart condition. Seek medical attention for persistent palpitations, chest pain, breathlessness or fainting.
- Moderate candy: Limit sugary treats and consider fruit alternatives.
- Avoid asthma triggers: Ask about fog effects at haunted attractions and leave if you experience breathing discomfort.
- Check costumes and decorations: Clean stored items before use and discard anything with mould or a musty smell. Choose breathable, open-face masks.
- Use makeup carefully: Choose fragrance-free or hypoallergenic products and apply them in well-ventilated spaces.
- Carry asthma medication: Keep your prescribed quick-relief inhaler and spacer handy. Watch for coughing, wheezing or chest tightness, and take breaks when needed.
- Reduce infection risks: Practise good hand hygiene, stay home when sick and keep vaccinations up to date.
- Carve pumpkins safely: Avoid kitchen knives. Use pumpkin-carving kits with serrated tools and make small, controlled cuts.
How Much Does an Underactive Thyroid Really Matter in Fertility?
Credit: iStock
When a couple has difficulty conceiving, thyroid checks are among the first things doctors do. Yet, it is an important fact that one often forgets - overt hypothyroidism or mild/subclinical hypothyroidism are actually very different things.
Having a thyroid that is not active enough means the body is not producing enough thyroid hormones. These hormones regulate metabolism and at the same time can greatly affect the functioning of the reproductive system like the occurrence and regularity of the menstrual cycle, ovulation and the hormonal environment that is necessary for pregnancy. Still, new findings suggest that we should not always take the blame for infertility just because the TSH level is borderline or abnormal.
When hypothyroidism genuinely affects fertility
Undiagnosed, overt hypothyroidism has the potential to disrupt reproduction in many ways. Lower levels of thyroid hormones may alter the balance in hypothalamic-pituitary-ovarian axis, which would affect ovulation and menstruation. In severe cases of hypothyroidism, higher prolactin levels could be observed, disrupting endocrine signaling.
According to new 2026 American Thyroid Association guidelines, overt hypothyroidism is considered to be a known risk factor for infertility and recurrent miscarriages. Specifically, according to the guideline, menstrual problems have been seen in 23% of women with untreated overt hypothyroidism, and about 2–3% of all cases of anovulation are due to hypothyroidism.
It is important to note that women with known hypothyroidism, who received appropriate treatment with levothyroxine and were in a euthyroid state, had the same chances for fertility as women without thyroid disorder.
Thus, the message here is not that women with hypothyroidism are unable to conceive. It is that thyroid dysfunction should not go untreated during planning of pregnancy.
Also read: World Iodine Deficiency Day: Significance And Importance
But what about a mildly raised TSH?
This is where the science becomes considerably more interesting.
Subclinical hypothyroidism generally means that TSH is elevated while free T4 remains within the normal range. It is increasingly detected during fertility investigations, partly because women are being tested more frequently.
But does every mildly elevated TSH require treatment?
A 2025 review article published in Current Opinion in Obstetrics & Gynecology concluded there isn't enough reliable evidence at this time to consider subclinical hypothyroidism as a contributor to infertility. It was also found that the use of levothyroxine was not consistently tied to improved pregnancy or live-birth outcomes in women suffering from subclinical hypothyroidism. The authors advocated for screening and treatment practices that are selective rather than universal.
This new recommendation represents a clear departure from the previous approach that was often overly aggressive in treating women with marginal thyroid test results.
The same findings were reported in a randomized trial-based 2024 systematic review and meta-analysis, which was published in a leading international medical journal by the world's largest academic medical publisher. The analysis showed that preconception levothyroxine administration had no statistically significant effect on live birth rates or pregnancy or miscarriage rates in subclinical hypothyroid women. Still, it should be mentioned that the scientists have recognized this issue and they have pointed out that for women with a TSH level above 4 mIU/L, the evidence is even more uncertain and that better trials are needed.
Also read: World Menopause Day: Is It Empty Nest Syndrome Or Menopause Symptoms? Expert Explains
New 2026 IVF data add another layer
A quite relevant study published in Human Reproduction in July of the same year examined 412 women who were subclinically hypothyroid and had frozen embryo transfers. In this group, 198 got levothyroxine whereas the other 214 were untreated. The live-birth rates were 43.9% for levothyroxine users against 39.3% in the untreated group. Even though the numbers were better for the treated group, the difference was not statistically significant.
It is also remarkable that apart from the levothyroxine group, they got other embryological results as well, including more fertilised oocytes, Day-3 embryos, good-quality Day-3 embryos and blastocysts. Yet it didn't lead to statistical significance of the live births. It's a typical point in fertility medicine that even if lab or embryological indicators are enhanced, it doesn't necessarily mean having more children.
In addition, the study carried out in 2026 on women undergoing the procedure of assisted reproduction, who left untreated, revealed that women with untreated TSH between around 3.6 and 6 mIU/L retrieved fewer oocytes. Yet, the live-birth rates after accounting for other factors turned out to be no significant difference at all (1,2).
In fact, there was quite a relevant study carried out recently on the effect of levothyroxine on the frozen embryo transfer (FET) outcomes in cases of subclinical hypothyroidism. It was conducted in Human Reproduction in July 2026. The participants of the study were 412 hypothyroid women who were undergoing FET (frozen embryo transfer).
Does thyroid disease affect egg quality?
Some evidence is emerging from here, but it should not yet be presented as an undisputed scientific fact.
On a big research scale with 2,867 women who were in the first IVF treatment cycle, it turned out that women who had subclinical or even overt hypothyroidism had their ovarian function decline much more than normal women, which was assessed through AMH and antral follicle count independent of thyroid autoimmunity. Though being an observational study, it just indicates the presence of a connection but not that hypothyroidism is causing the ovarian reserve to diminish.
The reason for drawing up such a clear line between them is that fertility depends on age, female factors like ovarian reserve, endometriosis PCOS, tubal factors, male factors like sperm quality, metabolic health and many other variables. Thyroid function is just one aspect out of a large puzzle not the complete picture
What about Hashimoto's and thyroid antibodies?
Thyroid autoimmunity is another contributing factor. There are cases where some females have thyroid antibodies, specifically thyroid peroxidase antibodies, even when the thyroid hormones of the individual are within normal range.
There is an inconclusive body of evidence associating the existence of thyroid antibodies with difficulty conceiving. In a review conducted in 2025, there was no substantial evidence that would support routine screening for every infertile female. The more recent 2026 ATA guidelines highlight the importance of taking into consideration the individual needs of the patient.
So, should every woman trying to conceive have a thyroid test?
Not necessarily in exactly the same way.
A thyroid assessment is particularly important for women with a previous thyroid disorder, symptoms suggestive of hypothyroidism, irregular menstrual cycles, infertility, recurrent pregnancy loss, autoimmune disease or a family history of thyroid disease.
Recent Indian health coverage has also highlighted the importance of checking thyroid function during preconception care. A January 2026 Hindustan Times report noted the association between thyroid dysfunction and menstrual irregularities, infertility and recurrent miscarriage, while recommending greater awareness around testing during preconception and early pregnancy.
The bottom line
Thyroid gland is the most misused organ when it comes to health, Mainly when it comes to treatment.
When a woman suffers from uncorrected overt hypothyroidism, this can clearly interfere with fertilization by causing ovulation and monthly cycle irregularities and affecting fertility generally, which needs to be corrected before pregnancy whenever it is feasible. Generally, fertility results are encouraging after thyroid hormone levels are kept within the normal range.
In case of very mild to subclinical hypothyroidism In particular when the TSH is only a little bit above the normal levels and free T4 remains stable, the situation is far from a textbook case and it is rather a grey zone. However, new research conducted in 2025 and 2026 increasingly supports the idea of going beyond a one-size-fits-all prescription of levothyroxine to women with borderline TSH.
The only reasonable course of action for a woman who wants to conceive is as simple as: assess thyroid function clinically only when it is necessary (i.e., when there are clinical signs/symptoms of thyorid imbalance/ disease). Determine if the imbalance is one of those that are clinically overt (like signs and symptoms of overt hypothyroidism, elevated TSH, etc.) or clinically subclinical, then consider the TSH level, symptoms, thyroid antibodies, reproductive history, etc., and refer the treatment to an endocrinologist or fertility specialist to decide.
The goal is not to chase an arbitrary “perfect” TSH number. The goal is to identify genuine thyroid disease, treat it appropriately and avoid allowing either an untreated disorder or unnecessary treatment to become another source of anxiety during an already stressful fertility journey.
- Follow Us :


© $2026 Times Horizon Private Limited