
- Health Conditions A-Z
- Health & Wellness
- Nutrition
- Fitness
- Health News
- Ayurveda
- Videos
- Medicine A-Z
- Parenting
Is Your Sore Throat Viral, Bacterial Or Allergic? Find Out Here
Image Credit: Canva
One of the commonest causes of illness, a sore throat often clears up on its own, but knowing what's causing it is important to treat it properly. Viral, bacterial, or caused by allergic elements - these kinds of sore throats have different characteristics that need different responses.
Sore throats have several origins, including infection and environmental factors. Some common causes include:
Viral infections: Viruses cause 90% of sore throat cases. Sore throats may result due to flu or common cold as well as those from chickenpox and measles that can all cause irritation.
Bacterial Infections: Streptococcus bacteria, the most common cause of strep throat, is the most common bacterial source. Strep throat is contagious and can lead to complications if untreated.
Allergies: Pollen, pet dander, and mold can trigger throat irritation, often accompanied by postnasal drip, sneezing, and watery eyes.
Environmental Factors: Dry air, pollution, and smoke can dry out or irritate the throat, creating a scratchy sensation.
Other Causes: GERD, vocal strain, even tumors may be responsible for chronic sore throats.
How to Distinguish Between Viral, Bacterial, and Allergic Sore Throats
Determining your cause of sore throat requires analysis of symptoms that accompany it, how long the sore throat lasts, and how bad the sore throat is.
Viral Sore Throats
The viruses that cause a sore throat are usually similar to a cold in their symptoms and tend to be milder than bacterial infections.
Symptoms of Viral Sore Throat
- Red, swollen throat without white patches
- Persistent cough
- Runny nose and nasal congestion
- Fever, usually mild
Duration: Viral infections last for 7–10 days without antibiotics.
Treatment: Home remedies, such as warm fluids, saltwater gargling, and over-the-counter pain relievers can help alleviate it.
Also Read: Flu Season Grips 40 States In US, CDC Reports Alarming Numbers
Bacterial Sore Throats
Bacterial sore throats, mainly strep throat, are more severe and require prompt medical attention to prevent complications.
Symptoms of Bacterial Sore Throat
- Red and swollen tonsils with white patches or streaks of pus
- High fever
- Absence of a cough
- Nausea, vomiting, or stomach pain (especially in children)
- Small red spots on the roof of the mouth
Diagnosis: Rapid strep tests or throat cultures confirm the presence of bacteria.
Treatment: Antibiotics are necessary to eliminate the infection. Without treatment, complications like rheumatic fever or abscesses can develop.
Sore Throats Caused by Allergies
Throat irritation is caused by postnasal drip. Allergies create a buildup and drip of mucus down the back of the throat.
Allergic Sore Throat Symptoms
- Irritation of the throat and ears
- Runny eyes, sneezing, and nasal congestion
- These symptoms are usually relieved by antihistamines or removal from the source of the allergen
Duration: Allergic sore throats are sustained for as long as the allergens are exposed.
When to Seek Medical Care?
A sore throat should be taken to a doctor if:
- The condition lasts more than a week.
- There is shortness of breath or swallowing becomes painful.
- Swelling is too pronounced or the pain in the throat is extreme.
- High fever, rash, or joint pain occur along with the sore throat.
- A child shows signs of dehydration or refuses fluids due to throat pain.
Early diagnosis can prevent complications and speed recovery.
Effective Treatment for Sore Throats
Home Remedies for Viral and Allergy-Related Sore Throats
Viral infections and allergies often respond well to non-invasive treatments:
- Drink warm teas, broths, or water to soothe the throat.
- Gargling with warm, salty water can reduce inflammation.
- These help soothe an irritated throat and can alleviate coughing.
Let your body rest sufficiently. Humidifying dry air will help keep the throat moist, especially when winter is on its way.
Why Not All Sore Throats Require Antibiotics?
Bacterial infections require antibiotics such as penicillin or amoxicillin. Finish the treatment completely to avoid reoccurrence or resistance.
How to Keep Sore Throats at Bay When Winter Is Near
Prevention is better than cure, and simple lifestyle changes can reduce your risk:
- Wash your hands frequently to avoid infections.
- Avoid close contact with sick individuals.
- Use air purifiers to minimize exposure to irritants.
- Stay hydrated and maintain a balanced diet to boost immunity.
Understanding the cause of your sore throat—whether viral, bacterial, or allergic—is key to effective treatment and recovery. While many sore throats resolve on their own, seeking timely medical advice for persistent or severe symptoms can prevent complications. Prioritize self-care, and don’t hesitate to consult a doctor when needed. Remember, your throat’s health is a vital part of your overall well-being.
That Small Shadow On The Lung: Why Finding Out Matters
Credit: iStock
She came to the hospital because of a cough that would not go away. The cough was eventually found to be nothing serious. But her CT scan revealed something unexpected — a 12 mm nodule in the outer part of her right lung.
She had never smoked. She felt completely well.
Yet that tiny shadow raised a big question: was it an old tuberculosis scar, a harmless growth, or an early lung cancer?
A CT scan can show us that a nodule is there. It cannot always tell us what it is.
This is an increasingly familiar situation. As CT scans have become more widely used, particularly after the COVID-19 pandemic, doctors are finding small lung nodules in people being scanned for entirely different reasons. Most turn out to be benign. Some, however, need closer assessment.
India has another challenge. Tuberculosis and its scars are common, and a lung shadow can sometimes be attributed to TB without tissue confirmation. While treating tuberculosis promptly is important, assuming that every suspicious nodule is TB can occasionally delay the diagnosis of something else, including cancer.
The answer, when appropriate, is to obtain a tissue sample.
Traditionally, a small nodule deep in the lung could be difficult to reach. A needle biopsy through the chest can be effective but carries a risk of a collapsed lung. Conventional bronchoscopy is excellent for the larger airways but becomes more challenging as the target gets smaller and farther towards the edge of the lung. Surgery may sometimes be necessary.
Newer techniques are changing the picture.
Navigation bronchoscopy uses the patient's CT scan to create a three-dimensional map of the airways and guide a thin catheter towards the nodule. Cone Beam CT adds real-time three-dimensional imaging during the procedure, allowing the doctor to check where the instruments are in relation to the lesion before taking the biopsy.
In simple terms, navigation helps us find the way; Cone Beam CT helps us confirm we are there.
The tissue can then be examined immediately where appropriate, helping determine whether the sample is adequate and whether additional material is needed for advanced testing.
Importantly, not every nodule needs a biopsy. Many are best managed through carefully planned follow-up scans. The decision depends on the nodule's size and appearance, previous scans, and the patient's overall risk.
For patients, the message is reassuring: a lung nodule does not mean cancer. But it should not be ignored either.
Keep previous scans. Ask what the likely possibilities are. Understand why your doctor recommends surveillance or biopsy — and make sure the follow-up happens.
Today, advanced bronchoscopy is helping doctors turn a worrying shadow into something much more useful: an answer.
(By Dr Shyam Krishnan, Intervention Pulmonologist, CMRI)
World Lung Day: Dry Cough, Breathlessness May Not Always Be Asthma — Could It Be ILD?
Credit: Guy's and St. Thomas Specialist Care
Dry cough and breathing difficulty aren’t always caused by asthma, COPD, or infections. They can also be signs of interstitial lung disease (ILD), a group of lung conditions that can cause inflammation and scarring and, in some cases, progressive loss of lung function.
ILD can go unnoticed in its early stages because its symptoms are often mistaken for more common respiratory conditions. By the time a patient undergoes a CT scan and reaches an ILD clinic, significant lung scarring may have already developed — and some of that damage may be irreversible.
Millions May Be Living With ILD Worldwide
A Global Burden of Disease Study 2023 analysis, published in December 2025, estimated that 4.58 million people were living with ILD and pulmonary sarcoidosis worldwide in 2023, with 112,650 deaths attributed to the conditions that year.
“The true global burden of ILD is higher than currently reported, particularly in underserved populations and low- and middle-income countries,” Prof. Marlies Wijsenbeek-Lourens, Pulmonologist and Head of the Center for Interstitial Lung Diseases and Sarcoidosis at Erasmus University Medical Center, Netherlands, told HealthandMe.
The global expert said most available epidemiological data come from Europe, North America, Japan, South Korea and Australia, where access to specialist care, multidisciplinary diagnosis and high-resolution CT imaging is generally more available.
“As a result, large parts of Africa, South America, South and Southeast Asia remain underrepresented in current estimates. In these regions, more limited access to diagnostic facilities, fewer ILD specialists and under-recognition of disease undoubtedly result in substantial underdiagnosis.”
Even in high-income countries, she added, some patients with ILD likely remain undiagnosed because symptoms such as breathlessness and cough are often attributed to more common conditions.
What Is Interstitial Lung Disease?
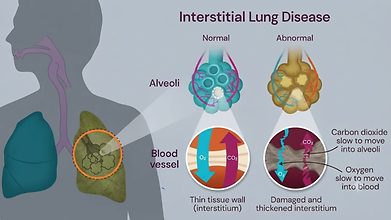
ILD is not a single disease but a group of more than 200 lung conditions. The disease affects the interstitium, the tissue surrounding and supporting the lungs’ air sacs, or alveoli. In ILD, this tissue can become inflamed and/or scarred.
As scarring progresses, the lungs can become stiffer, making it harder for them to expand and reducing the efficiency of oxygen transfer. As the disease progresses, the lung shrinks, making it difficult for the patient to breathe.
According to Prof. Marlies, there is a rise in ILD diagnoses due to several factors, such as:
- Better awareness
- More HRCT scans
- Better diagnosis
- Ageing populations
- Autoimmune disease
- Environmental and occupational exposure.
When Should Doctors Suspect ILD?
Some forms of ILD can be treated more effectively when identified early, before permanent lung damage occurs.
“Unfortunately, many patients still reach an ILD specialist late. Breathlessness and cough may initially be treated as asthma, infection or sometimes even tuberculosis. By the time a CT scan is done and the patient reaches an ILD clinic, significant scarring may already have developed,” Dr Asmita Mehta, Professor and Head, Department of Respiratory Medicine at Amrita Institute of Medical Sciences, Kochi, told HealthandMe.
“A dry cough and gradually progressive breathlessness lasting for more than three months, particularly breathlessness while walking or climbing stairs, should raise suspicion of ILD rather than simply being attributed to asthma, infection or ageing,” she added.
Read More: US Cancer Death Rates Fall For Men, Women: Lung Cancer Progress Drives Decline
Doctors should think of ILD especially when these symptoms do not improve with usual treatment, when fine crackling sounds are heard in the lungs, or when oxygen levels fall during walking.
It is also important to ask about joint pain, skin changes, dry eyes or mouth, and exposure to birds, mould, biomass smoke or occupational dust. Sometimes the clue to ILD is outside the lungs, the expert said.
ILD And COVID-19
Pre-existing ILD was associated with worse outcomes during COVID-19. Now, six years later, some patients who had severe COVID-19 also continue to show persistent lung abnormalities.
“The reassuring part is that not every abnormal CT after COVID means progressive lung fibrosis. In many patients, the lung changes gradually improve or remain stable. Some patients who had very severe COVID, prolonged ICU admission, or required ventilation may be left with persistent scarring and may need longer follow-up,” Dr Asmita said.
What Does ILD Look Like In India?
Common ILD diagnoses seen in India include connective tissue disease-associated ILD (CTD-ILD), hypersensitivity pneumonitis (HP), idiopathic pulmonary fibrosis (IPF), sarcoidosis and idiopathic nonspecific interstitial pneumonia (NSIP).
Dr Asmita said that, apart from idiopathic pulmonary fibrosis, ILD related to autoimmune diseases and environmental exposures is also commonly seen in India. These exposures can include birds, mould, biomass smoke and certain occupations.
Epidemiological reviews estimate the overall prevalence of ILD in India to range between 49.0 and 98.1 per 100,000 people, with an annual crude incidence rate of 10.1 to 20.2 per 100,000 population.
India is also building a larger national evidence base through the ICMR-led Indian Network of Pulmonary Fibrosis (INPF) registry.
Biggest Challenges For ILD Patients In India
- Delayed diagnosis: Symptoms can be mistaken for asthma, infections, or tuberculosis.
- Limited specialist access: ILD specialists and advanced diagnostic facilities are concentrated in larger centres.
- High treatment costs: Medicines, investigations, oxygen, and pulmonary rehabilitation can be expensive.
- Limited transplant access: Lung transplantation remains available only to a limited number of eligible patients.
- Low awareness: Many patients and families are unfamiliar with ILD and its long-term nature.
“We therefore need not only earlier diagnosis, but better awareness, affordable treatment, wider access to ILD specialists and stronger advanced-care and transplant programs,” Dr Asmita said.
Loss Of Y Chromosome In Men May Signal Higher Cancer Risk

Credit: iStock
Humans and most mammals have two sex chromosomes, X and Y. Females typically have two X chromosomes (XX), while males typically have one X and one Y chromosome (XY). As men age, many of their cells gradually lose the Y chromosome, due to a common genetic change.
Research has shown that cancer incidence and mortality rate are more among men than women. A new study may offer clues as to why.
Researchers from the University of Arizona found that loss of the Y chromosome in men’s tissues could create conditions that allow cancer to develop.
The research, published in JCI Insights, found that Y chromosome loss creates a pre-neoplastic field effect — a hidden zone of genetic vulnerability in normal-appearing tissue that may provide fertile ground for cancer development.
What Did The Study Find?
Also read: US Cancer Death Rates Fall For Men, Women: Lung Cancer Progress Drives Decline
Previous studies have linked loss of the Y chromosome in blood cells to an increased risk of disease. The new study systematically profiled Y chromosome loss across normal, precancerous and cancerous tissues from 11 major human organs.
“We were able to show that the loss of the Y chromosome is found in normal-appearing tissues adjacent to a tumor,” said physician-scientist Dr. Dan Theodorescu of the University of Arizona Cancer Center.
“That finding is what makes this discovery so exciting. It suggests we may be looking at one of the earliest signposts of cancer forming.”
The team analyzed 1,000 tissue samples from 405 men, using an automated fluorescent imaging system to examine more than 4.3 million individual cell nuclei and measure the ratio of Y to X chromosomes.
In one part of the study, researchers created detailed maps of bladder tissue removed during cancer surgery.
The maps showed that Y chromosome loss increased as tissue progressed from normal tissue to early abnormal cells and then to cancer.
Y chromosome loss in normal-appearing tissue was highest in samples from colon, rectal, esophageal, pancreatic and lung cancers.
“We are now thinking of this as a gradient, similar to a hillside that slowly gets steeper,” Theodorescu said. “The closer the tissue is to a cancer, the more Y chromosome loss we see. That gradient could one day help doctors suspect trouble in biopsies that miss a smaller cancer.”
How Y Chromosome Loss May Affect Cancer
Read More: UK NHS Trust To Review 4,500 More Breast Cancer Cases After 20 Unnecessary Mastectomies
Theodorescu’s previous research examined how loss of the Y chromosome in cancer cells can help them evade the immune system. This may help explain why Y chromosome loss has been associated with higher mortality from certain carcinomas.
What Does The Y Chromosome Do?
The Y chromosome spans more than 59 million DNA base pairs and accounts for almost 2% of the DNA in human cells. It contains roughly 70 to 200 genes involved in protein production.
The chromosome contains genes that play important roles in male sex development and fertility, including sperm production.
Beyond reproduction, research suggests that the Y chromosome can influence immune and inflammatory responses in men, potentially affecting susceptibility to certain diseases.
Cancer Risk In Men
Globally, cancer is diagnosed more often in men than in women, with men having roughly a 25% higher incidence rate. Men also account for a greater share of cancer deaths worldwide.
Some of the most common cancers affecting men include prostate, lung, colorectal and skin cancers. Early detection and appropriate screening can improve the chances of successful treatment for several types of cancer.
- Follow Us :


© $2026 Times Horizon Private Limited