
- Health Conditions A-Z
- Health & Wellness
- Nutrition
- Fitness
- Health News
- Ayurveda
- Videos
- Medicine A-Z
- Parenting
Is It Safe To Get A Mammogram During Pregnancy?
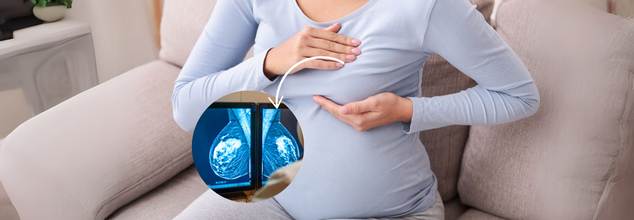
Image Credit: Health and me
Pregnancy is accompanied by a lengthy list of do's and don'ts—take prenatal vitamins, no alcohol, exercise carefully, and eat well. But what about when an unplanned health issue presents itself, such as the necessity for a mammogram? For most women, this might not even be something they think about until they are in a position where breast cancer screening is an option.
Perhaps you're over 40 and in need of your yearly mammogram, or perhaps you have a history of breast cancer in your family and you want to keep your screenings current. More emergently, you've found a lump in your breast. So, can you have a mammogram when pregnant? The answer is yes, but there are several things to consider.
Pregnancy creates substantial hormonal changes that affect the body, as well as breast tissue. Estrogen and progesterone's rise causes the breasts to expand and condition to produce milk, which results in denser tissue. This increased density is more challenging to detect any abnormalities with using mammograms. Even post-delivery, should the woman be breastfeeding, milk-filled glands can also make the breasts denser and, as a result, make mammogram readings less clear.
While 3D mammograms have improved imaging technology to help navigate dense breast tissue, doctors often suggest postponing routine screening mammograms until after pregnancy if there are no symptoms or high-risk factors. However, if a lump or abnormality is found, your doctor may recommend immediate diagnostic imaging.
When Is a Mammogram Necessary During Pregnancy?
Mammograms are not done routinely if a woman becomes pregnant, yet there are specific situations where one might be unavoidable. Breast cancer in pregnancy does occur—1 in 3,000 times—but it's not common. If a lump is detected by a woman, she has constant breast pain and no explanation, or she is at high risk (e.g., strong history of breast cancer in her family or genetic defect such as BRCA1 or BRCA2), a physician will order a mammogram.
The process itself takes very little radiation exposure. The radiation employed by a mammogram is concentrated on the breast, and there is little to no radiation that reaches other areas of the body. A lead apron is also placed over the belly to shield the unborn child.
Alternative Breast Imaging Options During Pregnancy
For pregnant women requiring breast imaging, physicians may initially suggest an ultrasound. In contrast to a mammogram, an ultrasound is not done with the use of radiation and is deemed safe for pregnant women.
An ultrasound of the breast can establish whether a lump is a fluid-filled cyst or a solid tumor that needs further investigation. Yet ultrasounds are not always diagnostic, and in certain instances, a mammogram or biopsy is needed to determine or rule out cancer.
Magnetic Resonance Imaging (MRI) is also an imaging choice but has some drawbacks. The majority of breast MRIs employ a contrast material called gadolinium, which is able to pass through the placenta and to the fetus. Although risks are not entirely clear, physicians usually do not use MRI with contrast unless necessary. Some practitioners may offer an MRI without contrast as an option.
What If You Find a Lump In Your Breast During Pregnancy?
Breast changes throughout pregnancy are normal, but finding a lump should never be taken lightly. If you notice a lump, alert your medical provider right away. They will conduct a clinical breast exam and potentially have you get an imaging study such as an ultrasound or mammogram to see whether anything needs to be done.
If imaging indicates a suspicious mass, a biopsy can be suggested. Core needle biopsy is the most frequently used and is safe during pregnancy. It consists of numbing the skin with local anesthetic and inserting a hollow needle into the area to obtain a small sample of tissue to be tested.
Breast Cancer Treatment During Pregnancy
In the extremely uncommon event of a diagnosis of breast cancer while pregnant, therapy will be determined by the nature and extent of cancer and by how far along in pregnancy one is. The most frequent form of treatment is surgery—either mastectomy (surgical removal of the entire breast) or lumpectomy (surgical removal of the lump)—which is usually safe while pregnant.
Chemotherapy is also possible but usually only attempted after the first trimester, when it can damage developing fetal tissue. Radiation therapy is not used during pregnancy and is typically deferred until after giving birth. Hormonal therapy and targeted therapies are also omitted until after giving birth.
Can I Get a Mammogram While Breastfeeding?
Yes, you can have a mammogram while you are breastfeeding. The radiation in a mammogram does not impact breast milk or hurt the baby. But breast density is still high during lactation, and this might complicate detection of abnormalities. To enhance image quality, physicians usually advise breastfeeding or pumping 30 minutes prior to the mammogram.
Routine screening mammograms are usually delayed in pregnancy unless there is a high-level concern.
If a lump is detected, an ultrasound is typically the initial imaging study done, with a mammogram being a consideration if additional assessment is necessary.
- Pregnancy mammograms utilize minimal radiation and are safe when required.
- Breast MRI with contrast is usually avoided in pregnancy.
- Breast biopsy, when necessary, is safe during pregnancy.
If breast cancer does develop during pregnancy, there are available treatment options that can be adjusted to keep the mother and infant safe.
Pregnancy is a period of significant change, and health issues particularly those involving breast health, are anxiety-provoking. Routine mammograms are typically postponed until after giving birth, but diagnostic testing can be done if necessary. The best you can do is discuss changes you notice in your breasts with your healthcare provider in an open manner. Early detection and prompt treatment can make a very big difference in the health of both mother and fetus.
E. Coli Toxin Linked To Bowel Cancer Among Under-50s: Top UK Scientists Raise Alarm Over Food Poisoning Bug
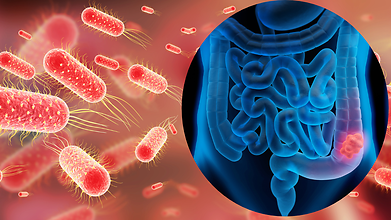
Credit: iStock
A toxin produced by certain strains of E. coli, commonly associated with food poisoning, has emerged as a leading suspect behind rising bowel cancer cases among people under 50, UK scientists have told British MPs.
Speaking to the Science and Technology Committee, Dr Karl Smith-Byrne, a senior molecular epidemiologist at the University of Oxford, said exposure to the toxin could help explain the rise in early-onset bowel cancer.
Obesity, ultra-processed foods, smoking and alcohol are established risk factors, but scientists believe they may explain only around half of the cases.
In the UK, bowel cancer diagnoses among under-50s are around 50% higher than they were 30 years ago.
What Is The E. Coli Toxin Linked To Bowel Cancer?
E. coli can spread through contaminated food or water, contact with animals and transmission between people. It is a major cause of food poisoning in the UK, with around 44,000 people in Britain experiencing a significant infection last year.
Dr Smith-Byrne pointed to colibactin, a toxin produced by certain strains of E. coli living in the gut responsible for bowel cancer not all, the Daily Mail reported.
Research published last year identified colibactin as a potential driver of early-onset colorectal cancer. The toxin damages DNA, creating mutations that may contribute to cancer development.
These characteristic mutations were more than three times as common in tumours from people under 40 than in those from people over 70.
"If it is causing [DNA] mutations, it's causing mutations at a sensitive period earlier in life," said Dr Smith-Byrne, a survivor of early-onset rectal cancer.
"That can give that person's colon or their rectum a head start on its journey towards being cancerous or developing these tumours."
Dr Smith-Byrne told MPs that increased exposure to colibactin was "probably the leading explanation at the moment".
How Could Colibactin Increase Bowel Cancer Risk?
Read More: AI Creates 16 Viruses To Kill Drug-Resistant E. coli, Raises Biosafety Concerns
Scientists suspect early-life exposure to colibactin could leave lasting DNA damage in bowel cells, increasing cancer risk decades later.
Professor Elio Riboli, a cancer epidemiologist at Imperial College London, told MPs that colibactin-producing E. coli strains are typically found in people born after 1960.
"Something has happened in the E. coli bacteria," he said. "There must have been a mutation, and there is a new bacteria."
Professor Helen Coleman, a cancer epidemiologist at Queen's University Belfast, called colibactin "the first new clue that we've had in quite some time".
She cautioned that exposure could occur much earlier than the eventual cancer diagnosis.
"Even though we're talking about adults that are being diagnosed with cancer between 18 and 49, it's quite likely to be very early life exposures," she said.
"It could be something you were exposed to in very early childhood, possibly even in the prenatal period, and that makes it very difficult to study."
Can Bowel Cancer Risk Be Reduced?
Bowel cancer is the third most common cancer worldwide, accounting for approximately one in 10 cancer cases. Also known as colorectal cancer, it starts in the large intestine (colon) or rectum. It often develops from small growths called polyps on the inner lining of the bowel, which can turn cancerous over time.
Symptoms of bowel cancer can easily be mistaken for common digestive complaints, making early diagnosis challenging. Symptoms to be aware of include:
- Persistent constipation or alteration in bowel habits
- Blood in stool or rectal bleeding
- Abdominal pain, bloating, or a palpable lump
- Unintentional weight loss or weakness.
While researchers investigate colibactin, experts recommend following established ways to reduce bowel cancer risk.
Professor Riboli said a fibre-rich diet, regular physical activity, limiting alcohol, stopping smoking and reducing red and processed meat consumption can help.
"The quick win could come from applying what we know," he said. "We could prevent about 60 per cent of the cancers occurring now, but we are not applying in society what we know."
Can Unhappy Marriages Increase Dementia Risk? Study Finds 38% Chance

Credit: AI
Researchers have not been able to pin down one single cause of dementia. From genetics to ageing, there are several factors that come into play when it comes to the risk of degenerative neurological disorders like dementia.
Apart from known factors, a recent study has emerged, suggesting that an individual's social connections with their spouse, family, or other loved ones may influence dementia risk. The study suggests that the quality of social connections, rather than simply whether someone lives alone, may impact dementia risk.
Researchers from the University of Bordeaux in France found that older adults who experience long-term loneliness had a 38% higher risk of developing dementia than those who don't feel lonely. Additionally, occasional loneliness did not have a significant impact on dementia risk.
The findings, published in the journal Aging & Mental Health recently suggest that perpetual feelings of social disconnection may play a role in someone's dementia risk.
Loneliness & Dementia Risk
The researchers studied data from 3,777 adults aged 65 and older who participated in the French PAQUID study between 1988 and 2018. During the first eight years, participants were examined for loneliness and grouped into three categories:
- Never lonely: People who did not report loneliness at any time.
- Occasionally lonely: People who reported loneliness at one or two assessments.
- Chronically lonely: People who reported loneliness at three or four assessments.
Researchers then examined dementia diagnoses over a period of 20 years. By the beginning of this second phase, 1,540 participants remained eligible for the analysis. Out of these, at least 560 people developed dementia during follow-up.
The incidence of dementia was the highest among those experiencing chronic loneliness. Around 49.1% of this group developed dementia, compared to 33.1% of those who never reported loneliness. Among participants who experienced occasional loneliness, 34.5% developed dementia.
After accounting for other factors, chronic loneliness was reported to have a 38% higher risk of dementia compared to never experiencing loneliness. Occasional loneliness, however, showed no significant link.
Loneliness Among Those Who Didn't Live Alone
One of the study's main findings was that living with someone does not always guard against loneliness.
Nearly 30% of participants classified as chronically lonely did not live alone. This suggests that people can experience loneliness while living with a spouse, partner or other family members.
Lead author Yvanna Simon said this vulnerability could also arise from unsatisfying relationships, burden of caregiving or a lack of meaningful, satisfying activities.
Impact Of Loneliness On Brain Health
The researchers suggested several possible ways in which chronic loneliness could impact dementia risk.
Perpetual loneliness may activate the body's stress response over prolonged periods, contributing to inflammation and changes in immune activity.
It may also be contribute to physical inactivity and poor dietary habits, which can increase the risk of cardiovascular disease and diabetes. Both conditions are proven risk factors for dementia.
Less social interaction could also mean fewer opportunities for cognitive stimulation, while prolonged social stress could contribute to biological wear and tear.
It must be understood that the study merely identified a possible connection between chronic loneliness and dementia risk. Another limitation was that loneliness was assessed using a single question about whether participants had felt lonely during the previous week. This may not capture the full complexity of someone's relationships or social experiences.
Can Poor Sleep and Irregular Bedtimes Increase Stroke Risk?

Credit: iStock
Sleep is not simply a period of rest. It is an important part of how the body regulates blood pressure, metabolism and cardiovascular function. Consistently getting too little sleep, having fragmented sleep or following highly irregular sleep and wake times has been associated with poorer cardiovascular health, including risk factors linked to stroke.
Blood pressure normally falls during sleep, giving the cardiovascular system a period of relative rest. Poor or disrupted sleep may interfere with this normal pattern and is associated with problems such as high blood pressure and impaired glucose regulation. These conditions are established risk factors for stroke. The relationship is complex, however: poor sleep does not automatically lead to a stroke, and an association does not by itself prove that one directly causes the other.
One sleep disorder that deserves particular attention is obstructive sleep apnoea. In this condition, the upper airway repeatedly narrows or closes during sleep, disrupting breathing and sleep quality. Loud snoring, witnessed pauses in breathing, gasping or choking during sleep, and excessive daytime sleepiness can be warning signs. Untreated sleep apnoea is associated with high blood pressure and an increased risk of cardiovascular problems, including stroke. People with these symptoms should discuss them with a healthcare professional; a sleep assessment may be needed.
Irregular bedtimes should therefore be taken seriously as one part of overall sleep health, but they should not be presented as an independently proven, direct cause of stroke. Research increasingly links sleep regularity and timing with cardiovascular health, while more evidence is needed to establish how much changing these patterns alone reduces stroke risk.
Building healthier sleep habits
For most adults, aiming for seven to nine hours of sleep each night is a useful guide. Duration is only one part of healthy sleep: regularity, continuity, quality and how alert a person feels during the day also matter.
A few practical steps can help: keep bedtime and wake-up time reasonably consistent, including on weekends; avoid caffeine late in the day if it affects your sleep; reduce bright screens and stimulating activities close to bedtime; get regular physical activity and daytime light; and keep the bedroom quiet, dark and comfortable.
Persistent difficulty sleeping, loud snoring, pauses in breathing during sleep or excessive daytime sleepiness warrant medical advice—particularly in someone who also has high blood pressure, diabetes or other cardiovascular risk factors. These symptoms may point to a treatable sleep problem.
Poor sleep does not mean that a person will inevitably have a stroke. But sleep deserves a place alongside the better-known prevention measures: controlling blood pressure and diabetes, staying physically active, eating a balanced diet, avoiding tobacco and following medical advice about cardiovascular risk.
(By Dr. Kaushik Sundar, Stroke Neurologist, Narayana RN Tagore Hospital, Mukundapur, Kolkata)
- Follow Us :


© $2026 Times Horizon Private Limited