
- Health Conditions A-Z
- Health & Wellness
- Nutrition
- Fitness
- Health News
- Ayurveda
- Videos
- Medicine A-Z
- Parenting
How Safe Is It To Use Microwave For Reheating Food?

Microwaves are a common appliance in every household now. You will see it in kitchens of not just houses, but offices, cafeterias, and co working space. However, there are studies that show that heating food in a microwave could be a health concern. While it does come handy, there are questions about harmful radiation and nutrient loss and heating safety that still linger.
Does Microwave Destroy The Nutrients In Food While Heating?
Some research suggests that microwaving may cause nutritional loss, particularly in vegetables. For example, studies have shown that microwaving broccoli with water diminishes its flavonoid content, which are anti-inflammatory compounds. However, experts note that cooking method and duration have a significant influence on nutrient retention.
Surprisingly, several studies indicate that microwaving preserves more nutrients than traditional cooking methods. A study comparing microwaved versus oven-cooked ready meals found that the microwaved version contained somewhat more vitamin C. Another study discovered that microwaving some vegetables, such as broccoli and green beans, may retain more beneficial compounds than boiling.
Ultimately, the nutrient loss really vary on the type of food which is being heated and how it is being cooked. Experts also recommend using minimal water and shorter cooking times to maximize the nutrient retention.
Is Heating In Plastic Safe?
Plastic containers and heating food in it, has always been a topic of debate. While containers do come with microwave-safe stamps, is it really safe to heat them with food?
According to research, when certain plastics are subjected to heat, they produce compounds such as phthalates and bisphenol A (BPA). These substances have been associated to hormonal disturbance, metabolic problems, and perhaps reproductive concerns.
A study also took in account over 400 plastic food containers that were microwave-safe and found that most of them leaked hormone-disrupting chemicals. These are phthalates, warn experts, which are commonly used in food packaging and can interfere with body's hormonal balance, and increase risk of diabetes or even high blood pressure.
Additionally, BPA exposure has been associated with fertility issues and immune system disruptions.
So, what can be done instead?
To minimize this risk, experts recommend using glass or ceramic container when microwaving foods. If you must use a plastic container, make sure the container is not damaged or old, as they are more prone to leach harmful chemicals.
What About The Radiation?
Concerns about microwave radiation have been largely debunked by decades of research. Microwaves use non-ionizing radiation, which does not have enough energy to damage DNA or cause cancer. The electromagnetic waves used in microwaves are similar to those from radios and light bulbs.
Experts emphasize that microwave ovens are designed to contain radiation, preventing exposure. As long as the microwave is in good condition and the door seals properly, there is no significant health risk from microwave radiation.
Other Concerns
Microwaving food could sometimes also lead to uneven cooking and it can create some risks to food safety. Thus, experts advertise to use microwave only to reheat the food and not to actually cook raw food. For safe reheating, food should reach at least 82°C (176°F) throughout to kill bacteria.
Patients Treated By Female Doctors Have Lower Risk Of Death, Study Finds

Credit: iStock
Does a patient’s chances of serious outcomes differ if they are treated by a female doctor? A recent study looks into this hypothesis to ascertain the difference between chances of a patient dying under a male and a female doctor.
According to the study, hospitalised patients treated by female doctors have a lower risk of dying within 30 days. They are also less likely to be re-hospitalised than those treated by male doctors. The study is published in JAMA Network Open.
"Past research has largely focused on surgical patients and the admitting physician only. Our findings add to the growing body of research examining the relationship between physician sex and patient outcomes, broadening the evidence beyond surgical care to a wider range of medical conditions and other physicians," says Dr. Angela Jerath, an ICES scientist, and Associate Professor, Department of Anesthesiology & Pain Medicine at the University of Toronto's Temerty Faculty of Medicine.
After analysing the health records of 958,150 adults admitted to hospitals in Ontario, Canada, between 2008 and 2022, researchers found that the 30-day mortality rate was 12.3% among patients treated by female physicians, compared to 13.7% among those treated by male physicians.
The findings also show a small difference in hospital readmissions. The 30-day readmission rate was 18.6% for patients treated by female doctors and 18.9% for those treated by male doctors.
The researchers examined outcomes across seven common medical conditions, including heart attacks, pneumonia and other acute illnesses.
They also considered the number of hospital days during which patients received care from female doctors, recognising that several doctors may be involved in a patient's treatment during an admission.
Patients Treated By Female Doctors Are Less Likely To Die In A 30-Day Period
Also read: Manosphere Is A Public Health Concern: Lancet Report Says Online Misogyny Harms Men's Mental Health
After accounting for patient, physician and hospital characteristics, treatment by a female physician was linked with 12% lower adjusted odds of death within 30 days compared to treatment by a male physician.
The researchers also found that for every 10% increase in the proportion of hospital days managed by female physicians, the adjusted odds of 30-day mortality decreased by 7%. This was observed for most medical conditions that were studied. Atrial fibrillation was the only exception.
The difference in mortality was also seen at longer follow-up periods. Patients treated by female physicians had lower mortality at 90 days and one year.
The findings were observed among both male and female patients. Female patients treated by female physicians had the lowest adjusted 30-day mortality rate in the analysis.
Why Patients May Have Better Outcomes With Female Doctors?
The study did not establish why patients treated by female physicians experienced better outcomes. However, the researchers discussed possible differences in clinical practice and communication.
Female physicians may be more likely to engage in patient-focused communication, spend more time with patients, follow clinical guidelines and involve colleagues in decision-making.
These practices could influence how symptoms are studied, treatment decisions are made and coordinated during hospitalisation.
"The goal is not to favour one group of physicians over another but to identify practices and behaviours that may help improve care across the health system," says Jerath.
"An important strength of this study is that, unlike surgical care, patients admitted to hospital for medical conditions are generally assigned physicians based on rotating schedules rather than patient or referring physician preferences, helping to minimize referral bias."
Retatrutide Vs Ozempic: Eli Lilly’s Experimental Drug Delivers More Than Double The Weight Loss
Credit: AI
Eli Lilly's experimental weight-loss drug retatrutide, being referred to as ‘Godzilla’, continues to outperform its rivals like Ozempic.
According to a recent head-to-head Phase 3 clinical trial involving adults with type 2 diabetes, it delivered more than twice the average weight loss achieved with Ozempic.
Ozempic Vs Retatrutide
Participants who took the highest dose of retatrutide lost an average of 20.9% of their body weight over 80 weeks, compared to 9.4% among those receiving Ozempic's highest approved dose for type 2 diabetes.
The trial, called TRANSCEND-T2D-2, involved more than 1,000 adults with type 2 diabetes. It compared once-weekly injections of retatrutide at doses of 9 mg and 12 mg with semaglutide, the active ingredient in Ozempic, at 2 mg.
At the end of 80 weeks, participants taking retatrutide 9 mg lost an average of 44.3 pounds (20.1 kg), while those receiving the 12 mg dose lost 47.4 pounds (21.5 kg). The Ozempic group lost an average of 20.9 pounds (9.5 kg).
The findings mark the first Phase 3 head-to-head comparison of retatrutide with another medicine in this class.
Also read: ‘Godzilla’ Drug Retatrutide Reverses Sleep Apnea In 1 In 4 Diabetes Patients
Retatrutide Also Improved Blood Sugar
The trial found that retatrutide also resulted in produced greater reductions in HbA1c, a measure of average blood glucose over approximately three months.
At 80 weeks, participants taking either dose of retatrutide recorded an average HbA1c reduction of 2.2%, compared to 1.8 % among those receiving Ozempic.
The experimental drug also resulted in greater improvements in cardiovascular risk factors like non-HDL cholesterol, triglycerides and systolic blood pressure.
Side Effects Of Retatrutide
The most commonly reported side effects of retatrutide were gastrointestinal symptoms like diarrhoea, nausea, constipation, vomiting and indigestion.
Diarrhoea was reported in 28.3% of participants receiving the 9 mg dose and 32.7% receiving 12 mg, compared to 26.4% in the Ozempic group. Nausea occurred in 21.2%, 23.8% and 21.3% of participants, respectively.
Researchers also reported a higher incidence of dysesthesia, an abnormal sensation that can include tingling, burning or skin sensitivity, among participants taking retatrutide.
Treatment discontinuation because of side effects occurred in 4.8% of the 9 mg group and 7.9% of the 12 mg group, compared to 2.7% of the Ozempic group.
More About Retatrutide
Retatrutide is a once-weekly injectable drug that targets three hormone receptors involved in regulating appetite, blood sugar and metabolism. They are GLP-1, GIP and glucagon.
GLP-1 helps regulate appetite and blood sugar while slowing the process of stomach emptying. GIP also plays a role in glucose regulation and insulin release. Glucagon is involved in controlling blood glucose and energy metabolism.
Ozempic, manufactured by Novo Nordisk, acts on the GLP-1 receptor. Eli Lilly's Mounjaro and Zepbound, which contain tirzepatide, target both GLP-1 and GIP receptors.
Retatrutide remains an investigational drug and has not been approved by the US Food and Drug Administration (FDA) or other regulatory authorities.
Eli Lilly plans to submit the drug for FDA approval in early 2027. The company said detailed results from the trial would be presented at a future medical meeting and published in a peer-reviewed journal.
Could GLP-1 Drugs Help Prevent Rupture Of Abdominal Aortic Aneurysm? Study Finds 46% Reduction In Risk
Credit: AI
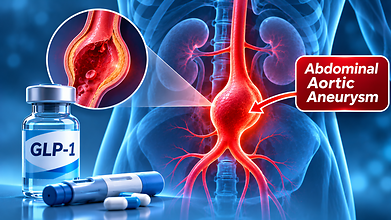
The hype around GLP-1 weight loss drugs keeps growing due to numerous new benefits as well as side effects that are discovered every other day. A recent study found that the risk of aortic aneurysm rupture is significantly less among GLP-1 users. The study was published in the Journal of Vascular Surgery.
GLP-1 receptor agonists is a a class of medicines that is widely used to treat type 2 diabetes and obesity. Users have reported substantial weight loss results with the help of these medicines like Ozempic, Mounjaro, Zepbound and others.
Now, researchers have found that people with abdominal aortic aneurysms who used GLP-1 drugs had a 46% lower risk of rupture over five years compared with those who did not use these medicines. This means that GLP-1 drugs may also have cardiovascular benefit apart from diabetes and obesity.
The study analysed health records from 123 healthcare organisations in the US. It is based on more than 412,000 people diagnosed with abdominal aortic aneurysms who underwent imaging surveillance every six months.
After matching patients based on factors like age, sex, diabetes, high blood pressure, smoking, heart disease and kidney disease, the researchers compared 13,722 GLP-1 receptor agonist users with an equal number of non-users.
GLP-1 Drugs Linked To Fewer Aortic Aneurysm Ruptures
Also read: ‘Godzilla’ Drug Retatrutide Reverses Sleep Apnea In 1 In 4 Diabetes Patients
After five years, aortic aneurysm rupture was recorded in about 1.6% of people taking GLP-1 drugs, compared to 2.4% of those who were not taking them.
The researchers reported a hazard ratio of 0.538, indicating a 46.2% lower risk of rupture among GLP-1 drug users after adjustment.
The difference was also observed at the two-year mark, when rupture occurred in 1.1% of GLP-1 users compared to 1.8% of non-users.
People taking GLP-1 drugs also had fewer elective aneurysm repairs. At five years, 2.1% of users underwent elective repair compared to 3% of non-users.
The study further found lower rates of major cardiovascular events like heart attacks, strokes and heart failure, as well as lower all-cause mortality among GLP-1 users.
What Is An Abdominal Aortic Aneurysm?
An abdominal aortic aneurysm (AAA) occurs when a section of the aorta, the body's largest artery, becomes enlarged or bulges due to weakening of its wall. It develops in the part of the aorta that passes through the abdomen.
Many abdominal aortic aneurysms do not cause symptoms and are detected during tests. However, as the aneurysm enlarges, its risk of rupture increases.
A ruptured aneurysm is considered to be a medical emergency as it can cause severe internal bleeding. Symptoms may include sudden, severe abdominal or back pain, dizziness, fainting and a rapid heartbeat.
Smoking, older age, high blood pressure, atherosclerosis and a family history of aneurysms are among the risk factors.
GLP-1 Drugs & Lower Risk Of Aortic Aneurysm Rupture Risk
GLP-1 receptor agonists work by mimicking the naturally occurring GLP-1 hormone. They help regulate blood sugar by stimulating insulin release when glucose levels are high, slowing the emptying of stomach and reducing appetite.
Some of their effects may also impact blood vessel health. Abdominal aortic aneurysms develop through several processes, including inflammation, damage to vascular smooth muscle cells and changes in the proteins that maintain the artery wall.
GLP-1 drugs have shown anti-inflammatory and cardiovascular benefits in older research. The researchers suggest these effects may help explain the lower rates of aneurysm-related complications observed in the study.
The findings are promising but do not conclusively prove that GLP-1 medicines prevent aneurysm rupture. This was a retrospective observational study, meaning researchers examined existing health records rather than randomly assigning patients to receive the drugs.
One important limitation was that aneurysm size was not included among the matching variables. Since aneurysm size is a major determinant of rupture risk, differences between the groups could have impacted the findings.
- Follow Us :


© $2026 Times Horizon Private Limited