
- Health Conditions A-Z
- Health & Wellness
- Nutrition
- Fitness
- Health News
- Ayurveda
- Videos
- Medicine A-Z
- Parenting
How Can I Treat My Cold Sores?

Credits: Canva
Cold sores are a common and often frustrating skin issue. While they may look like harmless blisters, cold sores are actually caused by the herpes simplex virus (HSV).
What Causes Cold Sores?
Cold sores are caused by the herpes simplex virus (HSV), which comes in two types: HSV-1 and HSV-2.
HSV-1 is the primary cause of cold sores, usually appearing around the mouth.
HSV-2 generally causes genital herpes but can also lead to cold sores.
While the appearance of cold sores caused by both HSV-1 and HSV-2 can look similar, their locations tend to differ. However, it is possible for HSV-1 to cause sores on the genitals and for HSV-2 to appear on the mouth.
How Do Cold Sores Spread?
Cold sores are highly contagious and can spread easily. The virus can be passed on through:
- Kissing or skin contact
- Sharing food, drinks, or cosmetics (such as lip balm)
- Oral sex, which can spread both cold sores and genital herpes
Even when a cold sore isn’t visible, the virus can still be spread through close contact. This makes prevention and management key to reducing outbreaks and the risk of infecting others.
Once someone contracts HSV, it stays in the body for life. While the virus remains dormant most of the time, it can reactivate and cause new sores, especially during periods of:
- Stress
- Illness
- A weakened immune system
Unfortunately, there’s no cure for the herpes virus, but the symptoms can be managed.
Symptoms of Cold Sores
Cold sores don’t just appear out of nowhere. Before the sore is visible, you may notice a tingling or burning sensation around the lips or face, which can occur several days before the sore forms. This is the best time to begin treatment to shorten the outbreak.
When a cold sore does appear, it often looks like a red, raised blister filled with fluid. The blister can be painful to touch, and there may be more than one. Cold sores usually last around two weeks and are contagious until they crust over and heal.
The Five Stages of a Cold Sore
Cold sores go through distinct stages as they develop and heal:
- Tingling and itching: You may feel these symptoms about 24 hours before the blister appears.
- Blisters: Small, fluid-filled blisters form, typically around the mouth.
- Bursting: The blisters burst and form painful sores.
- Scabbing: The sores dry out, scab over, and may itch or crack.
- Healing: The scab falls off, and the cold sore heals.
Risk Factors for Cold Sores
Certain factors can trigger the reactivation of HSV, leading to cold sores. These include:
- Infection, fever, or cold
- Sun exposure
- Stress
- Menstruation
- Dental work or injury
- Weakened immune system due to conditions like HIV/AIDS, eczema, or chemotherapy
Managing and Treating Cold Sores
There’s no cure for cold sores, but several treatments can ease the symptoms and help manage outbreaks.
Topical Ointments and Creams
Over-the-counter antiviral creams like docosanol (Abreva) or prescription ointments like penciclovir (Denavir) can help reduce the duration of an outbreak, especially if applied at the first sign of a cold sore.
Oral Medications
Prescription antiviral medications like acyclovir, valacyclovir, and famciclovir can also help, particularly for people who have frequent or severe outbreaks. Your doctor may recommend taking these medications regularly to prevent future outbreaks.
Home Remedies
There are also some home remedies that may provide relief, such as:
- Applying ice or a cold washcloth to the sore
- Using aloe vera gel or lemon balm lip balms
- Applying petroleum jelly to ease discomfort
Canker Sores vs. Cold Sores: What's the Difference?
While cold sores and canker sores may seem similar, they are quite different:
Cold sores are caused by the herpes virus, appear around the mouth, and are contagious.
Canker sores are not contagious and appear as ulcers inside the mouth or throat.
Preventing the Spread of Cold Sores
To avoid spreading cold sores:
- Wash your hands frequently
- Avoid close contact with others during an outbreak
- Don’t share food, drinks, or personal items like lip balm
Cold sores can be a persistent issue, but with proper care and management, you can reduce the frequency of outbreaks and prevent spreading the virus to others.
IBS Is Not Just A Gut Problem: Lancet Review Explains The Gut-Brain Connection
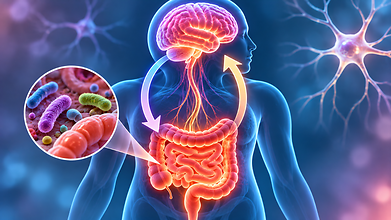
Credit: AI
Irritable bowel syndrome (IBS) is often characterised by digestive symptoms like abdominal pain, bloating, constipation and diarrhoea. However, the condition involves more than the digestive system.
A new review published in The Lancet explains how interactions between the gut and brain, changes in the gut microbiome, immune activity and the body's response to pain can contribute to the development of symptoms.
The review, titled Irritable bowel syndrome and related disorders of gut-brain interaction, brings focuses on biological and psychological evidence behind IBS. Researchers describe it as a disorder of gut-brain interaction, in which signals between the digestive system and the central nervous system affect gut function.
The authors also discuss chronic constipation and functional diarrhoea, which belong to the bigger group of disorders related to gut-brain interaction. These conditions may affect an estimated 20% of the global population.
What Is The Gut-Brain Connection In IBS?
Also read: Olympian Ciara Mageean Dies At 34 After Bowel Cancer Battle: Warning Signs In Young Adults
The gut and brain communicate continuously through a complex network that involves the central nervous system, autonomic nervous system, enteric nervous system and hypothalamic-pituitary-adrenal (HPA) axis.
The brain can influence intestinal movement, secretion and sensitivity, while signals from the gut can affect how the brain processes pain and other sensations.
In people with IBS, this communication may become disrupted. The result can be changes in bowel movements, more sensitivity to normal digestive processes and abdominal discomfort.
The authors said, “These central and peripheral mechanisms can act in an integrated way to cause IBS symptoms, via the gut-brain axis.”
For instance, a person with IBS may experience pain or bloating even when the amount of gas or intestinal movement would not cause discomfort in someone without the condition. This is due to a condition called visceral hypersensitivity, in which the nerves supplying the digestive organs become unusually sensitive to internal sensations.
The review explains that changes in both peripheral mechanisms within the gut and central mechanisms involving the brain can contribute to symptoms.
Gut Bacteria And Inflammation May Contribute To IBS
Also read: Can Coffee Trigger Irritable Bowel Syndrome?
The gut microbiome, which consists of microorganisms living in the digestive tract, is another important part of the gut-brain connection.
Changes in the composition and activity of gut bacteria may impact intestinal function, immune responses and communication with the nervous system. The review identifies the following:
- Gut infections: Gastrointestinal infections can trigger IBS symptoms in some people, even after the initial infection has subsided.
- Altered gut microbiome: Changes in intestinal bacteria may affect digestion, immune activity and gut function.
- Increased intestinal permeability: Changes in the intestinal barrier may allow substances to pass through more easily, potentially contributing to immune activation.
- Low-grade inflammation: Mild inflammation in the intestinal lining and changes in immune function may contribute to symptoms.
- Abnormal gut movement: Changes in gastrointestinal motility can cause food and waste to move through the digestive tract too quickly or too slowly.
- Visceral hypersensitivity: Increased sensitivity in the gut can make normal digestive processes feel painful.
Mental Health And IBS
Psychological health is another component of the gut-brain axis. Stress, anxiety and other psychological difficulties can influence how the brain processes pain and communicates with the digestive system.
The HPA axis, which helps regulate the body's response to stress, plays a role in this process . Changes in stress levels can affect gut movement, secretion and sensitivity.
Currently, there is no single biomarker that can diagnose IBS. Doctors assess symptoms, medical history and clinical findings, while using tests to rule out other conditions.
The review highlights that some underlying mechanisms can already be measured through approved tests and questionnaires. These include abnormal bile acid metabolism, accelerated movement of contents through the colon and psychological conditions.
Patients Treated By Female Doctors Have Lower Risk Of Death, Study Finds

Credit: iStock
Does a patient’s chances of serious outcomes differ if they are treated by a female doctor? A recent study looks into this hypothesis to ascertain the difference between chances of a patient dying under a male and a female doctor.
According to the study, hospitalised patients treated by female doctors have a lower risk of dying within 30 days. They are also less likely to be re-hospitalised than those treated by male doctors. The study is published in JAMA Network Open.
"Past research has largely focused on surgical patients and the admitting physician only. Our findings add to the growing body of research examining the relationship between physician sex and patient outcomes, broadening the evidence beyond surgical care to a wider range of medical conditions and other physicians," says Dr. Angela Jerath, an ICES scientist, and Associate Professor, Department of Anesthesiology & Pain Medicine at the University of Toronto's Temerty Faculty of Medicine.
After analysing the health records of 958,150 adults admitted to hospitals in Ontario, Canada, between 2008 and 2022, researchers found that the 30-day mortality rate was 12.3% among patients treated by female physicians, compared to 13.7% among those treated by male physicians.
The findings also show a small difference in hospital readmissions. The 30-day readmission rate was 18.6% for patients treated by female doctors and 18.9% for those treated by male doctors.
The researchers examined outcomes across seven common medical conditions, including heart attacks, pneumonia and other acute illnesses.
They also considered the number of hospital days during which patients received care from female doctors, recognising that several doctors may be involved in a patient's treatment during an admission.
Patients Treated By Female Doctors Are Less Likely To Die In A 30-Day Period
Also read: Manosphere Is A Public Health Concern: Lancet Report Says Online Misogyny Harms Men's Mental Health
After accounting for patient, physician and hospital characteristics, treatment by a female physician was linked with 12% lower adjusted odds of death within 30 days compared to treatment by a male physician.
The researchers also found that for every 10% increase in the proportion of hospital days managed by female physicians, the adjusted odds of 30-day mortality decreased by 7%. This was observed for most medical conditions that were studied. Atrial fibrillation was the only exception.
The difference in mortality was also seen at longer follow-up periods. Patients treated by female physicians had lower mortality at 90 days and one year.
The findings were observed among both male and female patients. Female patients treated by female physicians had the lowest adjusted 30-day mortality rate in the analysis.
Why Patients May Have Better Outcomes With Female Doctors?
The study did not establish why patients treated by female physicians experienced better outcomes. However, the researchers discussed possible differences in clinical practice and communication.
Female physicians may be more likely to engage in patient-focused communication, spend more time with patients, follow clinical guidelines and involve colleagues in decision-making.
These practices could influence how symptoms are studied, treatment decisions are made and coordinated during hospitalisation.
"The goal is not to favour one group of physicians over another but to identify practices and behaviours that may help improve care across the health system," says Jerath.
"An important strength of this study is that, unlike surgical care, patients admitted to hospital for medical conditions are generally assigned physicians based on rotating schedules rather than patient or referring physician preferences, helping to minimize referral bias."
Retatrutide Vs Ozempic: Eli Lilly’s Experimental Drug Delivers More Than Double The Weight Loss
Credit: AI
Eli Lilly's experimental weight-loss drug retatrutide, being referred to as ‘Godzilla’, continues to outperform its rivals like Ozempic.
According to a recent head-to-head Phase 3 clinical trial involving adults with type 2 diabetes, it delivered more than twice the average weight loss achieved with Ozempic.
Ozempic Vs Retatrutide
Participants who took the highest dose of retatrutide lost an average of 20.9% of their body weight over 80 weeks, compared to 9.4% among those receiving Ozempic's highest approved dose for type 2 diabetes.
The trial, called TRANSCEND-T2D-2, involved more than 1,000 adults with type 2 diabetes. It compared once-weekly injections of retatrutide at doses of 9 mg and 12 mg with semaglutide, the active ingredient in Ozempic, at 2 mg.
At the end of 80 weeks, participants taking retatrutide 9 mg lost an average of 44.3 pounds (20.1 kg), while those receiving the 12 mg dose lost 47.4 pounds (21.5 kg). The Ozempic group lost an average of 20.9 pounds (9.5 kg).
The findings mark the first Phase 3 head-to-head comparison of retatrutide with another medicine in this class.
Also read: ‘Godzilla’ Drug Retatrutide Reverses Sleep Apnea In 1 In 4 Diabetes Patients
Retatrutide Also Improved Blood Sugar
The trial found that retatrutide also resulted in produced greater reductions in HbA1c, a measure of average blood glucose over approximately three months.
At 80 weeks, participants taking either dose of retatrutide recorded an average HbA1c reduction of 2.2%, compared to 1.8 % among those receiving Ozempic.
The experimental drug also resulted in greater improvements in cardiovascular risk factors like non-HDL cholesterol, triglycerides and systolic blood pressure.
Side Effects Of Retatrutide
The most commonly reported side effects of retatrutide were gastrointestinal symptoms like diarrhoea, nausea, constipation, vomiting and indigestion.
Diarrhoea was reported in 28.3% of participants receiving the 9 mg dose and 32.7% receiving 12 mg, compared to 26.4% in the Ozempic group. Nausea occurred in 21.2%, 23.8% and 21.3% of participants, respectively.
Researchers also reported a higher incidence of dysesthesia, an abnormal sensation that can include tingling, burning or skin sensitivity, among participants taking retatrutide.
Treatment discontinuation because of side effects occurred in 4.8% of the 9 mg group and 7.9% of the 12 mg group, compared to 2.7% of the Ozempic group.
More About Retatrutide
Retatrutide is a once-weekly injectable drug that targets three hormone receptors involved in regulating appetite, blood sugar and metabolism. They are GLP-1, GIP and glucagon.
GLP-1 helps regulate appetite and blood sugar while slowing the process of stomach emptying. GIP also plays a role in glucose regulation and insulin release. Glucagon is involved in controlling blood glucose and energy metabolism.
Ozempic, manufactured by Novo Nordisk, acts on the GLP-1 receptor. Eli Lilly's Mounjaro and Zepbound, which contain tirzepatide, target both GLP-1 and GIP receptors.
Retatrutide remains an investigational drug and has not been approved by the US Food and Drug Administration (FDA) or other regulatory authorities.
Eli Lilly plans to submit the drug for FDA approval in early 2027. The company said detailed results from the trial would be presented at a future medical meeting and published in a peer-reviewed journal.
- Follow Us :


© $2026 Times Horizon Private Limited