
- Health Conditions A-Z
- Health & Wellness
- Nutrition
- Fitness
- Health News
- Ayurveda
- Videos
- Medicine A-Z
- Parenting
HIV vs. AIDS: What You Should Know About These Commonly Confused Terms

World Aids Day
The global challenge of HIV/AIDS remains one of the most pressing public health issues today. According to the latest data from UNAIDS, around 38.4 million people worldwide are living with HIV/AIDS, underlining the need for not only medical intervention but also comprehensive awareness, education, and social change. Despite the significant strides made in treatment and prevention, the confusion surrounding the relationship between HIV and AIDS still persists.
Young people have become influential advocates in the fight against HIV/AIDS. Research from UNICEF shows that youth-led initiatives can lower HIV transmission rates by as much as 45% in targeted communities. These young activists utilize digital platforms and peer-to-peer education to dispel myths, promote safe practices, and foster supportive environments for those affected by HIV/AIDS.
Dr Gowri Kulkarni, an expert in Internal Medicine, explains that while the terms HIV and AIDS are often used interchangeably, they are distinctly different. "HIV (Human Immunodeficiency Virus) is a virus that attacks the immune system, whereas AIDS (Acquired Immunodeficiency Syndrome) is a condition that occurs when HIV severely damages the immune system," she clarifies. To understand the implications of these differences, it's important to explore the fundamental distinctions between the two.
1. HIV is a Virus; AIDS is a Syndrome
HIV is the virus responsible for attacking the body’s immune system, specifically targeting CD4 cells, which are crucial for the body’s defense against infections. As HIV progresses, it destroys these cells, weakening the immune system over time. If left untreated, this continuous damage can lead to AIDS.
AIDS, on the other hand, is a syndrome, not a virus. Dr Kulkarni further elaborates that AIDS is a collection of symptoms and illnesses that emerge when the immune system is severely compromised due to prolonged HIV infection. It represents the most advanced stage of HIV, and is characterized by very low CD4 counts or the onset of opportunistic infections like tuberculosis, pneumonia, or certain cancers.
2. Not Everyone with HIV Develops AIDS
A key distinction to remember is that not everyone with HIV will progress to AIDS. Thanks to advancements in medicine, particularly antiretroviral therapy (ART), individuals living with HIV can manage the virus and maintain a healthy immune system for many years, or even decades, without ever developing AIDS. ART works by suppressing the virus to undetectable levels, effectively preventing the damage HIV would otherwise cause to the immune system.
Without treatment, however, HIV progresses through three stages:
- Acute HIV Infection: This stage occurs shortly after transmission and may include symptoms like fever, fatigue, and swollen lymph nodes.
- Chronic HIV Infection: Often asymptomatic or mildly symptomatic, the virus continues to damage the immune system but at a slower rate.
- AIDS: This is the final stage, marked by severe immune damage and the presence of infections that take advantage of the compromised immune defenses.
3. HIV is Transmissible; AIDS is Not
Another key distinction between HIV and AIDS is the way in which they are transmitted. HIV is highly contagious and can be transmitted through the exchange of bodily fluids such as blood, semen, vaginal fluids, and breast milk. It is primarily spread through unprotected sexual contact, sharing needles, or from mother to child during childbirth or breastfeeding.
AIDS, however, is not transmissible. It is not a disease that can be passed from one person to another. Rather, AIDS is the result of untreated, advanced HIV infection and is a direct consequence of the virus’s damage to the immune system.
4. Diagnosis Methods Differ
HIV and AIDS are diagnosed through different methods. HIV is diagnosed through blood tests or oral swabs that detect the presence of the virus or antibodies produced by the immune system in response to the virus. Early detection of HIV is crucial, as it allows for timely intervention and treatment, which can prevent the virus from progressing to AIDS.
AIDS, on the other hand, is diagnosed using more specific criteria. Dr Kulkarni notes that the diagnosis of AIDS is made when the individual’s CD4 cell count falls below 200 cells/mm³, or when opportunistic infections or certain cancers (such as Kaposi's sarcoma or lymphoma) are detected. Diagnosing AIDS involves a more thorough assessment of the individual’s immune function and overall health, as opposed to just the detection of HIV.
5. Treatment Goals Are Different
The treatment goals for HIV and AIDS differ significantly, although both involve antiretroviral therapy (ART). For HIV, the primary treatment goal is to suppress the virus to undetectable levels, thus maintaining a strong immune system and preventing further transmission of the virus. People living with HIV can often live long, healthy lives if they adhere to ART.
For individuals diagnosed with AIDS, the treatment plan becomes more complex. While ART remains an essential part of managing the virus, treatment for AIDS also focuses on addressing the opportunistic infections and secondary health complications associated with severe immune suppression. The goal of treatment for AIDS is not only to manage the HIV virus but also to improve the quality of life and extend survival by treating these secondary health issues.
Role of Community Engagement in Combatting HIV/AIDS
While the medical community has made great strides in managing HIV, the battle to curb its transmission is also a social and cultural issue. Dr Daman Ahuja, a public health expert, highlights that HIV/AIDS awareness and education are vital to reducing transmission rates and supporting those affected by the virus. "Young people, especially, have become key advocates in the fight against HIV/AIDS," says Dr Ahuja. "Research from UNICEF shows that youth-led initiatives can lower HIV transmission rates by as much as 45% in targeted communities."
Additionally, grassroots activism plays a significant role in raising awareness and addressing stigma. As the World Health Organization reports, community-based interventions have been proven to increase HIV testing rates and improve treatment adherence, which are crucial in the fight against the pandemic.
The ultimate goal of organizations like UNAIDS is to eliminate the HIV/AIDS pandemic by 2030. Achieving this requires global collaboration, from medical treatment advancements to public health strategies, education, and advocacy. Dr Kulkarni’s insight underscores the importance of early detection, treatment adherence, and community support in the fight against HIV/AIDS.
Dr Gowri Kulkarni is Head of Medical Operations at MediBuddy and Dr Daman Ahuja, a public health expert and has been associated with Red Ribbon Express Project of NACO between 2007-12.
Early Adulthood Obesity Linked To Thyroid, Ovarian And Endometrial Cancers: Study Of 6.3 Million
Credit: AI
Obesity during the 20s and 30s can fuel the risk of many lifestyle disorders like type 2 diabetes, cardiovascular diseases, metabolic syndrome, non-alcoholic fatty liver disease, sleep apnea and many others.
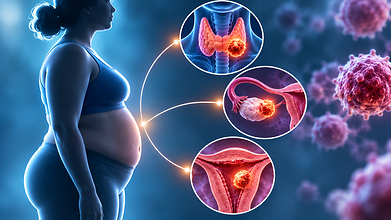
But according to a large study published in Annals of Internal Medicine, obesity could also increase the risk of developing cancer before midlife. The study identified higher chances of thyroid, endometrial and ovarian cancers.
How Was The Study Conducted?
Researchers examined health records of 6,313,338 adults in South Korea, aged between 20 to 39 years, who had no previous history of cancer.
Participants were followed for an average of 11.2 years to study the relationship between body weight and cancer risk.
During the follow-up period, 151,893 cancer cases were recorded. The findings showed that cancer risk increased in people with higher body mass index (BMI).
The researchers found that the 10-year total incidence of cancer was 1.84% among people with normal body weight. This increased to 2.24% among those with class I obesity and 2.62% among those with class II obesity.
In other words, the 10-year cancer incidence was approximately 0.78 percentage points higher among people with class II obesity than among those with normal weight.
The researchers also found that people with abdominal obesity were at higher cancer risk than those who didn’t have.
Among people with class I obesity, the 10-year cancer incidence was 2.45% in those with abdominal obesity, compared with 2.13% in those without it.
“Because abdominal obesity may be an important indicator for distinguishing cancer risk, it is important to manage waist circumference along with weight from a young age,” the authors wrote.
Also read: High-Fibre Diet Outperforms Metformin In Blood Sugar Control And Weight Loss, Study Finds
Three Cancers Linked To Early Adulthood Obesity
The study identified particularly strong associations between obesity and cancers involving the thyroid and female reproductive system.
Thyroid cancer: Excess body weight has previously been linked with changes in metabolic and hormonal changes that may affect thyroid cancer development.
Endometrial cancer: Obesity can increase oestrogen levels because fat tissue produces this hormone. Prolonged exposure to excess oestrogen can stimulate the growth of the uterine lining and increase the risk of endometrial cancer.
Ovarian cancer: The relationship between obesity and ovarian cancer is complex and may involve inflammation, insulin resistance and hormonal changes.
Also read: Warren Buffett Says He Hasn't Drunk Water In 48 Years: What Happens If You Replace It With Coke?
Obesity & Cancer Risk
Obesity causes several biological changes that may contribute to cancer development. One of them is chronic inflammation.
Excess fat tissue can fuel inflammation that may create an favourable environment for abnormal cell growth.
Obesity can also lead to insulin resistance, in which the body’s cells respond less effectively to insulin. This can cause higher insulin levels, which may fuel cell growth and proliferation.
Hormonal changes are also a factor. Fat tissue produces oestrogen, and higher levels of this hormone have been linked with cancers like endometrial and ovarian.
The study authors wrote, "Some cancers have recently become more common even among younger people, and this study confirmed that obesity in young adults is significantly associated with the development of these cancers."
Scientists Find New Way To Fight Bad Cholesterol: Could It Offer An Alternative To Statins?

Credit: iStock
Scientists have discovered a previously unknown mechanism that could explain why high cholesterol diet makes it challenging for the liver to remove bad cholesterol from the bloodstream. Researchers have also identified an experimental drug that blocks this process, offering a new method for treating high cholesterol.
The findings are published in the journal Nature by researchers from the University of California San Diego School of Medicine. Their experiments showed that blocking a specific enzyme called cathepsin A (CTSA) helped retain the liver's ability to clear low-density lipoprotein (LDL), commonly known as bad cholesterol.
In mice, inhibiting this enzyme stabilised LDL receptors in liver cells, reducing LDL cholesterol.
"We've known for a long time that a high-cholesterol diet reduces the liver's ability to clear cholesterol from the blood, but we didn't fully understand why," said senior author Alan Saltiel, professor of medicine at UC San Diego School of Medicine. "This new discovery explains a critical piece of that puzzle."
More About The Experiment
The liver plays a key role in regulating cholesterol levels. It uses LDL receptors located on the surface of liver cells to capture LDL cholesterol from the bloodstream.
When fewer of these receptors are available, the liver becomes less efficient at removing LDL cholesterol, allowing it to increase in the bloodstream. The researchers discovered that consuming high amounts of dietary cholesterol activates a protein called Ral. This increases the activity of CTSA, an enzyme that breaks down LDL receptors.
As these receptors are lost, the liver's ability to clear bad cholesterol declines. When researchers blocked CTSA using a small molecule inhibitor, LDL receptors became more stable and LDL cholesterol levels decreased dramatically in mice.
Experimental Drug That Can Help Lower Cholesterol
The discovery has sparked interest as researchers have identified an experimental drug that targets CTSA. The drug was originally developed as a possible treatment option for heart failure. Although its development for that purpose was discontinued for other reasons, it had already completed a Phase 1 clinical trial, which evaluated its safety in humans.
This previous test could help researchers move towards studying its ability as a cholesterol treatment. However, the drug has not yet been shown to lower LDL cholesterol in humans.
"There's still a real need for new cholesterol-lowering options, since some people can't get to safe levels even with the drugs we have now," Saltiel said.
He added, "This new pathway we discovered is completely separate from anything that existing drugs target, so it gives us a new opportunity to fill that gap."
The researchers hope to test the experimental CTSA inhibitor in a Phase 2 clinical trial to determine whether it can safely and effectively lower cholesterol in people. If successful, the approach could offer another option for people who struggle to control LDL cholesterol despite using existing treatments.
Saltiel said, "Luckily, there's an experimental drug sitting on the shelf that's already been shown to be safe in humans."
"We hope to test whether this might be effective by conducting a clinical trial -- which could potentially bring a new treatment option to patients much sooner than would have been expected."
IBS Is Not Just A Gut Problem: Lancet Review Explains The Gut-Brain Connection
Credit: AI
Irritable bowel syndrome (IBS) is often characterised by digestive symptoms like abdominal pain, bloating, constipation and diarrhoea. However, the condition involves more than the digestive system.
A new review published in The Lancet explains how interactions between the gut and brain, changes in the gut microbiome, immune activity and the body's response to pain can contribute to the development of symptoms.
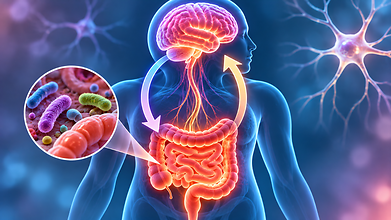
The review, titled Irritable bowel syndrome and related disorders of gut-brain interaction, brings focuses on biological and psychological evidence behind IBS. Researchers describe it as a disorder of gut-brain interaction, in which signals between the digestive system and the central nervous system affect gut function.
The authors also discuss chronic constipation and functional diarrhoea, which belong to the bigger group of disorders related to gut-brain interaction. These conditions may affect an estimated 20% of the global population.
What Is The Gut-Brain Connection In IBS?
Also read: Olympian Ciara Mageean Dies At 34 After Bowel Cancer Battle: Warning Signs In Young Adults
The gut and brain communicate continuously through a complex network that involves the central nervous system, autonomic nervous system, enteric nervous system and hypothalamic-pituitary-adrenal (HPA) axis.
The brain can influence intestinal movement, secretion and sensitivity, while signals from the gut can affect how the brain processes pain and other sensations.
In people with IBS, this communication may become disrupted. The result can be changes in bowel movements, more sensitivity to normal digestive processes and abdominal discomfort.
The authors said, “These central and peripheral mechanisms can act in an integrated way to cause IBS symptoms, via the gut-brain axis.”
For instance, a person with IBS may experience pain or bloating even when the amount of gas or intestinal movement would not cause discomfort in someone without the condition. This is due to a condition called visceral hypersensitivity, in which the nerves supplying the digestive organs become unusually sensitive to internal sensations.
The review explains that changes in both peripheral mechanisms within the gut and central mechanisms involving the brain can contribute to symptoms.
Gut Bacteria And Inflammation May Contribute To IBS
Also read: Can Coffee Trigger Irritable Bowel Syndrome?
The gut microbiome, which consists of microorganisms living in the digestive tract, is another important part of the gut-brain connection.
Changes in the composition and activity of gut bacteria may impact intestinal function, immune responses and communication with the nervous system. The review identifies the following:
- Gut infections: Gastrointestinal infections can trigger IBS symptoms in some people, even after the initial infection has subsided.
- Altered gut microbiome: Changes in intestinal bacteria may affect digestion, immune activity and gut function.
- Increased intestinal permeability: Changes in the intestinal barrier may allow substances to pass through more easily, potentially contributing to immune activation.
- Low-grade inflammation: Mild inflammation in the intestinal lining and changes in immune function may contribute to symptoms.
- Abnormal gut movement: Changes in gastrointestinal motility can cause food and waste to move through the digestive tract too quickly or too slowly.
- Visceral hypersensitivity: Increased sensitivity in the gut can make normal digestive processes feel painful.
Mental Health And IBS
Psychological health is another component of the gut-brain axis. Stress, anxiety and other psychological difficulties can influence how the brain processes pain and communicates with the digestive system.
The HPA axis, which helps regulate the body's response to stress, plays a role in this process . Changes in stress levels can affect gut movement, secretion and sensitivity.
Currently, there is no single biomarker that can diagnose IBS. Doctors assess symptoms, medical history and clinical findings, while using tests to rule out other conditions.
The review highlights that some underlying mechanisms can already be measured through approved tests and questionnaires. These include abnormal bile acid metabolism, accelerated movement of contents through the colon and psychological conditions.
- Follow Us :


© $2026 Times Horizon Private Limited