
- Health Conditions A-Z
- Health & Wellness
- Nutrition
- Fitness
- Health News
- Ayurveda
- Videos
- Medicine A-Z
- Parenting
From Health Struggles to Bodybuilding Champion: Story Of A YouTuber Who Lost 150 Pounds!

Extreme Transformation Of Simon Lafontant (Credit-goliath_gg/Instagram)
We often see celebrities go through weight loss transformations, with side-by-side comparisons of the before and after weight loss. But people often do not feel inspired or drawn to their stories as we all know that they have access to great personal trainers, high-end food products as well as better access to healthcare. But one story that was highlighted by Men’s Health in their ‘First Steps’ series can inspire many with the story of Simon Lafontant, who lost 150 pounds and went on to become a body builder.
Simon Lafontant, a 32-year-old from Calgary, had to deal with some serious health problems for a long time. These included low testosterone and Crohn's disease, which made his life difficult. But Simon decided he wanted to make a change. He got medical help for his low testosterone and then set a big goal for himself: to compete in a bodybuilding competition. He used social media to keep himself on track, and he ended up losing over 150 pounds and even winning the competition! His story is about how he went from struggling with his health to becoming a bodybuilding champion.
How A Disease Can Become A Turning Point
Simon talks about how he used to have bad habits and wasn't living a healthy lifestyle. This led to him feeling down, gaining weight, and losing motivation. Things got really serious in 2020 when his Crohn's disease caused him to be in the hospital for seven whole months. According to Mayo Clinic Crohn’s disease is a type of inflammatory bowel disease that is inflammation in your digestive tract which can be very painful and can cause people to need long term remission and time to heal the inflammation. Simon spoke about how he realized his poor lifestyle choices and being obese had made his symptoms worse!
While you may not wish to become a bodybuilder, there are many other aspects you can take away from the Simon’s story! Another trip to the doctors revealed that he had very low testosterone levels, which explained his lack of energy. This was a major turning point for him, as he finally understood some of the reasons behind his struggles.
What Role Does Testosterone Play?
One thing that made a huge difference in Simon’s weight loss journey was getting the TRT treatment for his low testosterone which had an almost immediate effect on him. He felt good, started enjoying things again, like going outside and working out. He also remembered how much he loved powerlifting and Strongman competitions, so this helped him get on to his path to bodybuilding and weight training!
Low testosterone affects both men and women, but in different ways. In women, it can cause low sex drive, tiredness, muscle weakness, trouble getting pregnant, irregular periods, vaginal dryness, mood changes like depression or anxiety, hair thinning, dry skin, and sleep problems. In men, low testosterone can lead to reduced sex drive, erectile dysfunction, hair loss, smaller testicles, hot flashes, and infertility. Other symptoms in men include feeling down, trouble concentrating or remembering things, and increased body fat. If you're experiencing any of these symptoms, it's a good idea to talk to a doctor.
That Small Shadow On The Lung: Why Finding Out Matters
Credit: iStock
She came to the hospital because of a cough that would not go away. The cough was eventually found to be nothing serious. But her CT scan revealed something unexpected — a 12 mm nodule in the outer part of her right lung.
She had never smoked. She felt completely well.
Yet that tiny shadow raised a big question: was it an old tuberculosis scar, a harmless growth, or an early lung cancer?
A CT scan can show us that a nodule is there. It cannot always tell us what it is.
This is an increasingly familiar situation. As CT scans have become more widely used, particularly after the COVID-19 pandemic, doctors are finding small lung nodules in people being scanned for entirely different reasons. Most turn out to be benign. Some, however, need closer assessment.
India has another challenge. Tuberculosis and its scars are common, and a lung shadow can sometimes be attributed to TB without tissue confirmation. While treating tuberculosis promptly is important, assuming that every suspicious nodule is TB can occasionally delay the diagnosis of something else, including cancer.
The answer, when appropriate, is to obtain a tissue sample.
Traditionally, a small nodule deep in the lung could be difficult to reach. A needle biopsy through the chest can be effective but carries a risk of a collapsed lung. Conventional bronchoscopy is excellent for the larger airways but becomes more challenging as the target gets smaller and farther towards the edge of the lung. Surgery may sometimes be necessary.
Newer techniques are changing the picture.
Navigation bronchoscopy uses the patient's CT scan to create a three-dimensional map of the airways and guide a thin catheter towards the nodule. Cone Beam CT adds real-time three-dimensional imaging during the procedure, allowing the doctor to check where the instruments are in relation to the lesion before taking the biopsy.
In simple terms, navigation helps us find the way; Cone Beam CT helps us confirm we are there.
The tissue can then be examined immediately where appropriate, helping determine whether the sample is adequate and whether additional material is needed for advanced testing.
Importantly, not every nodule needs a biopsy. Many are best managed through carefully planned follow-up scans. The decision depends on the nodule's size and appearance, previous scans, and the patient's overall risk.
For patients, the message is reassuring: a lung nodule does not mean cancer. But it should not be ignored either.
Keep previous scans. Ask what the likely possibilities are. Understand why your doctor recommends surveillance or biopsy — and make sure the follow-up happens.
Today, advanced bronchoscopy is helping doctors turn a worrying shadow into something much more useful: an answer.
(By Dr Shyam Krishnan, Intervention Pulmonologist, CMRI)
How Does Second-hand Smoke Exposure Increase The Risk Of Lung Cancer In People Who Have Never Smoked Themselves?
Credit: AI
Second-hand smoke increases the risk of lung cancer in people who have never smoked because it contains harmful chemicals, including known cancer-causing agents. When someone who does not smoke is around a person who is smoking they breathe in smoke from the burning cigarette and the smoke that the smoker breathes out. This mix of smoke is called second-hand smoke or environmental tobacco smoke.
How Second-Hand Smoke Damages Lung Cells And DNA
Even though the non-smoker does not light a cigarette they still take in dangerous substances. These chemicals can irritate the lungs. Cause inflammation. They also create stress, which means the body’s natural defenses are overwhelmed by harmful molecules. Over time this damage can harm the DNA inside lung cells.
When DNA is damaged the cells may start to change in ways. These abnormal cells can grow out of control. Turn into cancer. The longer and more intense the exposure to second-hand smoke the higher the risk becomes. For example, people who live with a smoker or work in places where smoking is allowed may get exposure over time.
Second-hand smoke also makes it harder for the body to fix cells. It keeps the lungs in a state of inflammation. This ongoing irritation helps create a condition where cancer can start and grow.
There is no level of exposure to tobacco smoke. Even small amounts can add to the risk. Some people are especially at risk like children, pregnant women and those with asthma or other breathing problems.
How Can Non-Smokers Reduce Their Exposure?
The best way to prevent lung cancer from second-hand smoke is to reduce exposure. This means keeping homes, cars and workplaces completely smoke-free. It also means supporting smoke- policies and encouraging people to quit smoking. Protecting non-smokers from second-hand smoke is a step, in reducing lung cancer rates.
Dr Saket Kumar, Senior Consultant – Physician & Pulmonology, Sterling Hospitals, Bhayli, Vadodara
World Lung Day: Dry Cough, Breathlessness May Not Always Be Asthma — Could It Be ILD?
Credit: Guy's and St. Thomas Specialist Care
Dry cough and breathing difficulty aren’t always caused by asthma, COPD, or infections. They can also be signs of interstitial lung disease (ILD), a group of lung conditions that can cause inflammation and scarring and, in some cases, progressive loss of lung function.
ILD can go unnoticed in its early stages because its symptoms are often mistaken for more common respiratory conditions. By the time a patient undergoes a CT scan and reaches an ILD clinic, significant lung scarring may have already developed — and some of that damage may be irreversible.
Millions May Be Living With ILD Worldwide
A Global Burden of Disease Study 2023 analysis, published in December 2025, estimated that 4.58 million people were living with ILD and pulmonary sarcoidosis worldwide in 2023, with 112,650 deaths attributed to the conditions that year.
“The true global burden of ILD is higher than currently reported, particularly in underserved populations and low- and middle-income countries,” Prof. Marlies Wijsenbeek-Lourens, Pulmonologist and Head of the Center for Interstitial Lung Diseases and Sarcoidosis at Erasmus University Medical Center, Netherlands, told HealthandMe.
The global expert said most available epidemiological data come from Europe, North America, Japan, South Korea and Australia, where access to specialist care, multidisciplinary diagnosis and high-resolution CT imaging is generally more available.
“As a result, large parts of Africa, South America, South and Southeast Asia remain underrepresented in current estimates. In these regions, more limited access to diagnostic facilities, fewer ILD specialists and under-recognition of disease undoubtedly result in substantial underdiagnosis.”
Even in high-income countries, she added, some patients with ILD likely remain undiagnosed because symptoms such as breathlessness and cough are often attributed to more common conditions.
What Is Interstitial Lung Disease?
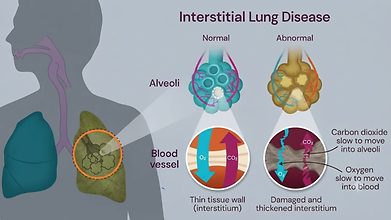
ILD is not a single disease but a group of more than 200 lung conditions. The disease affects the interstitium, the tissue surrounding and supporting the lungs’ air sacs, or alveoli. In ILD, this tissue can become inflamed and/or scarred.
As scarring progresses, the lungs can become stiffer, making it harder for them to expand and reducing the efficiency of oxygen transfer. As the disease progresses, the lung shrinks, making it difficult for the patient to breathe.
According to Prof. Marlies, there is a rise in ILD diagnoses due to several factors, such as:
- Better awareness
- More HRCT scans
- Better diagnosis
- Ageing populations
- Autoimmune disease
- Environmental and occupational exposure.
When Should Doctors Suspect ILD?
Some forms of ILD can be treated more effectively when identified early, before permanent lung damage occurs.
“Unfortunately, many patients still reach an ILD specialist late. Breathlessness and cough may initially be treated as asthma, infection or sometimes even tuberculosis. By the time a CT scan is done and the patient reaches an ILD clinic, significant scarring may already have developed,” Dr Asmita Mehta, Professor and Head, Department of Respiratory Medicine at Amrita Institute of Medical Sciences, Kochi, told HealthandMe.
“A dry cough and gradually progressive breathlessness lasting for more than three months, particularly breathlessness while walking or climbing stairs, should raise suspicion of ILD rather than simply being attributed to asthma, infection or ageing,” she added.
Read More: US Cancer Death Rates Fall For Men, Women: Lung Cancer Progress Drives Decline
Doctors should think of ILD especially when these symptoms do not improve with usual treatment, when fine crackling sounds are heard in the lungs, or when oxygen levels fall during walking.
It is also important to ask about joint pain, skin changes, dry eyes or mouth, and exposure to birds, mould, biomass smoke or occupational dust. Sometimes the clue to ILD is outside the lungs, the expert said.
ILD And COVID-19
Pre-existing ILD was associated with worse outcomes during COVID-19. Now, six years later, some patients who had severe COVID-19 also continue to show persistent lung abnormalities.
“The reassuring part is that not every abnormal CT after COVID means progressive lung fibrosis. In many patients, the lung changes gradually improve or remain stable. Some patients who had very severe COVID, prolonged ICU admission, or required ventilation may be left with persistent scarring and may need longer follow-up,” Dr Asmita said.
What Does ILD Look Like In India?
Common ILD diagnoses seen in India include connective tissue disease-associated ILD (CTD-ILD), hypersensitivity pneumonitis (HP), idiopathic pulmonary fibrosis (IPF), sarcoidosis and idiopathic nonspecific interstitial pneumonia (NSIP).
Dr Asmita said that, apart from idiopathic pulmonary fibrosis, ILD related to autoimmune diseases and environmental exposures is also commonly seen in India. These exposures can include birds, mould, biomass smoke and certain occupations.
Epidemiological reviews estimate the overall prevalence of ILD in India to range between 49.0 and 98.1 per 100,000 people, with an annual crude incidence rate of 10.1 to 20.2 per 100,000 population.
India is also building a larger national evidence base through the ICMR-led Indian Network of Pulmonary Fibrosis (INPF) registry.
Biggest Challenges For ILD Patients In India
- Delayed diagnosis: Symptoms can be mistaken for asthma, infections, or tuberculosis.
- Limited specialist access: ILD specialists and advanced diagnostic facilities are concentrated in larger centres.
- High treatment costs: Medicines, investigations, oxygen, and pulmonary rehabilitation can be expensive.
- Limited transplant access: Lung transplantation remains available only to a limited number of eligible patients.
- Low awareness: Many patients and families are unfamiliar with ILD and its long-term nature.
“We therefore need not only earlier diagnosis, but better awareness, affordable treatment, wider access to ILD specialists and stronger advanced-care and transplant programs,” Dr Asmita said.
- Follow Us :


© $2026 Times Horizon Private Limited