
- Health Conditions A-Z
- Health & Wellness
- Nutrition
- Fitness
- Health News
- Ayurveda
- Videos
- Medicine A-Z
- Parenting
Flu Symptoms You May Be Experiencing Could Be Something Much Worse!

Many diseases share the same symptoms, causing people to get confused and either undermine or overwhelm themselves with worries. With the current flu season on the rise, people in the United States are being very careful about their health and are taking necessary precautions to make sure they do not catch any more respiratory illnesses. Often these diseases show symptoms like coughing and wheezing, nothing that warrants anything more than a general doctor’s visit, sometimes people even think it it is a simple cold, but it could be something worse!
The Centers For Disease Control and Prevention (CDC) report on 28 February, last Friday on Respiratory Virus Activity Levels reported a moderate number of people are seeking medical help for respiratory illnesses. The flu is sending many people to the emergency room, RSV Respiratory syncytial virus has been sending many people to the ER along with COVID-19.
While flu test results are slightly less positive than last week, COVID-19 and RSV test results are about the same. In our community's wastewater, the flu virus is still very high, COVID-19 is moderate, and RSV is low. Looking forward, we expect COVID-19 emergency room visits to stay low. While flu visits are still high, they should start to go down soon.
So, even though it might feel like winter is ending, these viruses are still active, and we need to be careful. They are not going away quickly and can still spread easily. Here are some symptoms that should be treated with urgency right now.
Severe Dehydration
When you're really sick, you might not feel like eating or drinking. This can lead to dehydration, which is when your body doesn't have enough water. If your pee is dark yellow, or you feel dizzy, you might be dehydrated. If you pass out, get confused, or your heart beats really fast, you need to go to the hospital right away. Healthcare professionals can give you fluids through a needle to help you feel better. Being dehydrated is very dangerous, and it is important to take it seriously.
Breathing Difficulties
If you're having trouble breathing, or if you're breathing really fast, that's a big sign. It could mean that you have pneumonia or that your body isn't getting enough oxygen. Shortness of breath is always a reason to go to the emergency room. Your body is telling you that something is seriously wrong. It is very important to seek help right away. Do not wait it out at home.
Low Oxygen Levels
If your lips or fingers start to turn blue, that means you're not getting enough oxygen. Also, if you're so tired that you can barely get out of bed, that's another sign that you need to go to the hospital. These are serious symptoms that mean your body needs help right away.
Who’s Most at Risk for Severe Symptoms?
Some people are more likely to get very sick from these viruses. Pregnant people, little kids, and older adults are at higher risk. Also, people who have health problems like heart or lung disease, or people with weak immune systems, are more likely to have serious problems. Older adults are often hospitalized with the flu, COVID, and RSV. These groups need to be extra careful to avoid getting sick. It is very important that these groups get vaccinated.
RSV is especially dangerous for babies and young children. It's one of the main reasons why young kids end up in the hospital. This virus can make it very hard for them to breathe. It is very important to protect young children from this virus, especially in the first few years of their lives.
Scientists Find New Way To Fight Bad Cholesterol: Could It Offer An Alternative To Statins?

Credit: iStock
Scientists have discovered a previously unknown mechanism that could explain why high cholesterol diet makes it challenging for the liver to remove bad cholesterol from the bloodstream. Researchers have also identified an experimental drug that blocks this process, offering a new method for treating high cholesterol.
The findings are published in the journal Nature by researchers from the University of California San Diego School of Medicine. Their experiments showed that blocking a specific enzyme called cathepsin A (CTSA) helped retain the liver's ability to clear low-density lipoprotein (LDL), commonly known as bad cholesterol.
In mice, inhibiting this enzyme stabilised LDL receptors in liver cells, reducing LDL cholesterol.
"We've known for a long time that a high-cholesterol diet reduces the liver's ability to clear cholesterol from the blood, but we didn't fully understand why," said senior author Alan Saltiel, professor of medicine at UC San Diego School of Medicine. "This new discovery explains a critical piece of that puzzle."
More About The Experiment
The liver plays a key role in regulating cholesterol levels. It uses LDL receptors located on the surface of liver cells to capture LDL cholesterol from the bloodstream.
When fewer of these receptors are available, the liver becomes less efficient at removing LDL cholesterol, allowing it to increase in the bloodstream. The researchers discovered that consuming high amounts of dietary cholesterol activates a protein called Ral. This increases the activity of CTSA, an enzyme that breaks down LDL receptors.
As these receptors are lost, the liver's ability to clear bad cholesterol declines. When researchers blocked CTSA using a small molecule inhibitor, LDL receptors became more stable and LDL cholesterol levels decreased dramatically in mice.
Experimental Drug That Can Help Lower Cholesterol
The discovery has sparked interest as researchers have identified an experimental drug that targets CTSA. The drug was originally developed as a possible treatment option for heart failure. Although its development for that purpose was discontinued for other reasons, it had already completed a Phase 1 clinical trial, which evaluated its safety in humans.
This previous test could help researchers move towards studying its ability as a cholesterol treatment. However, the drug has not yet been shown to lower LDL cholesterol in humans.
"There's still a real need for new cholesterol-lowering options, since some people can't get to safe levels even with the drugs we have now," Saltiel said.
He added, "This new pathway we discovered is completely separate from anything that existing drugs target, so it gives us a new opportunity to fill that gap."
The researchers hope to test the experimental CTSA inhibitor in a Phase 2 clinical trial to determine whether it can safely and effectively lower cholesterol in people. If successful, the approach could offer another option for people who struggle to control LDL cholesterol despite using existing treatments.
Saltiel said, "Luckily, there's an experimental drug sitting on the shelf that's already been shown to be safe in humans."
"We hope to test whether this might be effective by conducting a clinical trial -- which could potentially bring a new treatment option to patients much sooner than would have been expected."
IBS Is Not Just A Gut Problem: Lancet Review Explains The Gut-Brain Connection
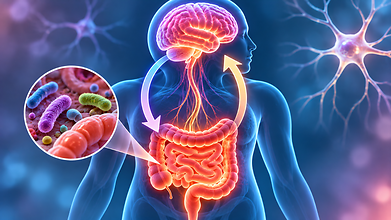
Credit: AI
Irritable bowel syndrome (IBS) is often characterised by digestive symptoms like abdominal pain, bloating, constipation and diarrhoea. However, the condition involves more than the digestive system.
A new review published in The Lancet explains how interactions between the gut and brain, changes in the gut microbiome, immune activity and the body's response to pain can contribute to the development of symptoms.
The review, titled Irritable bowel syndrome and related disorders of gut-brain interaction, brings focuses on biological and psychological evidence behind IBS. Researchers describe it as a disorder of gut-brain interaction, in which signals between the digestive system and the central nervous system affect gut function.
The authors also discuss chronic constipation and functional diarrhoea, which belong to the bigger group of disorders related to gut-brain interaction. These conditions may affect an estimated 20% of the global population.
What Is The Gut-Brain Connection In IBS?
Also read: Olympian Ciara Mageean Dies At 34 After Bowel Cancer Battle: Warning Signs In Young Adults
The gut and brain communicate continuously through a complex network that involves the central nervous system, autonomic nervous system, enteric nervous system and hypothalamic-pituitary-adrenal (HPA) axis.
The brain can influence intestinal movement, secretion and sensitivity, while signals from the gut can affect how the brain processes pain and other sensations.
In people with IBS, this communication may become disrupted. The result can be changes in bowel movements, more sensitivity to normal digestive processes and abdominal discomfort.
The authors said, “These central and peripheral mechanisms can act in an integrated way to cause IBS symptoms, via the gut-brain axis.”
For instance, a person with IBS may experience pain or bloating even when the amount of gas or intestinal movement would not cause discomfort in someone without the condition. This is due to a condition called visceral hypersensitivity, in which the nerves supplying the digestive organs become unusually sensitive to internal sensations.
The review explains that changes in both peripheral mechanisms within the gut and central mechanisms involving the brain can contribute to symptoms.
Gut Bacteria And Inflammation May Contribute To IBS
Also read: Can Coffee Trigger Irritable Bowel Syndrome?
The gut microbiome, which consists of microorganisms living in the digestive tract, is another important part of the gut-brain connection.
Changes in the composition and activity of gut bacteria may impact intestinal function, immune responses and communication with the nervous system. The review identifies the following:
- Gut infections: Gastrointestinal infections can trigger IBS symptoms in some people, even after the initial infection has subsided.
- Altered gut microbiome: Changes in intestinal bacteria may affect digestion, immune activity and gut function.
- Increased intestinal permeability: Changes in the intestinal barrier may allow substances to pass through more easily, potentially contributing to immune activation.
- Low-grade inflammation: Mild inflammation in the intestinal lining and changes in immune function may contribute to symptoms.
- Abnormal gut movement: Changes in gastrointestinal motility can cause food and waste to move through the digestive tract too quickly or too slowly.
- Visceral hypersensitivity: Increased sensitivity in the gut can make normal digestive processes feel painful.
Mental Health And IBS
Psychological health is another component of the gut-brain axis. Stress, anxiety and other psychological difficulties can influence how the brain processes pain and communicates with the digestive system.
The HPA axis, which helps regulate the body's response to stress, plays a role in this process . Changes in stress levels can affect gut movement, secretion and sensitivity.
Currently, there is no single biomarker that can diagnose IBS. Doctors assess symptoms, medical history and clinical findings, while using tests to rule out other conditions.
The review highlights that some underlying mechanisms can already be measured through approved tests and questionnaires. These include abnormal bile acid metabolism, accelerated movement of contents through the colon and psychological conditions.
Patients Treated By Female Doctors Have Lower Risk Of Death, Study Finds

Credit: iStock
Does a patient’s chances of serious outcomes differ if they are treated by a female doctor? A recent study looks into this hypothesis to ascertain the difference between chances of a patient dying under a male and a female doctor.
According to the study, hospitalised patients treated by female doctors have a lower risk of dying within 30 days. They are also less likely to be re-hospitalised than those treated by male doctors. The study is published in JAMA Network Open.
"Past research has largely focused on surgical patients and the admitting physician only. Our findings add to the growing body of research examining the relationship between physician sex and patient outcomes, broadening the evidence beyond surgical care to a wider range of medical conditions and other physicians," says Dr. Angela Jerath, an ICES scientist, and Associate Professor, Department of Anesthesiology & Pain Medicine at the University of Toronto's Temerty Faculty of Medicine.
After analysing the health records of 958,150 adults admitted to hospitals in Ontario, Canada, between 2008 and 2022, researchers found that the 30-day mortality rate was 12.3% among patients treated by female physicians, compared to 13.7% among those treated by male physicians.
The findings also show a small difference in hospital readmissions. The 30-day readmission rate was 18.6% for patients treated by female doctors and 18.9% for those treated by male doctors.
The researchers examined outcomes across seven common medical conditions, including heart attacks, pneumonia and other acute illnesses.
They also considered the number of hospital days during which patients received care from female doctors, recognising that several doctors may be involved in a patient's treatment during an admission.
Patients Treated By Female Doctors Are Less Likely To Die In A 30-Day Period
Also read: Manosphere Is A Public Health Concern: Lancet Report Says Online Misogyny Harms Men's Mental Health
After accounting for patient, physician and hospital characteristics, treatment by a female physician was linked with 12% lower adjusted odds of death within 30 days compared to treatment by a male physician.
The researchers also found that for every 10% increase in the proportion of hospital days managed by female physicians, the adjusted odds of 30-day mortality decreased by 7%. This was observed for most medical conditions that were studied. Atrial fibrillation was the only exception.
The difference in mortality was also seen at longer follow-up periods. Patients treated by female physicians had lower mortality at 90 days and one year.
The findings were observed among both male and female patients. Female patients treated by female physicians had the lowest adjusted 30-day mortality rate in the analysis.
Why Patients May Have Better Outcomes With Female Doctors?
The study did not establish why patients treated by female physicians experienced better outcomes. However, the researchers discussed possible differences in clinical practice and communication.
Female physicians may be more likely to engage in patient-focused communication, spend more time with patients, follow clinical guidelines and involve colleagues in decision-making.
These practices could influence how symptoms are studied, treatment decisions are made and coordinated during hospitalisation.
"The goal is not to favour one group of physicians over another but to identify practices and behaviours that may help improve care across the health system," says Jerath.
"An important strength of this study is that, unlike surgical care, patients admitted to hospital for medical conditions are generally assigned physicians based on rotating schedules rather than patient or referring physician preferences, helping to minimize referral bias."
- Follow Us :


© $2026 Times Horizon Private Limited