
- Health Conditions A-Z
- Health & Wellness
- Nutrition
- Fitness
- Health News
- Ayurveda
- Videos
- Medicine A-Z
- Parenting
Fight, Flight Or Freeze: How Do You Respond To Stress?

Image Credit: Canva
Stress is an unavoidable part of life, and while it often carries a negative connotation, it is actually a fundamental survival mechanism. When faced with a perceived threat, whether physical or emotional, the body instinctively reacts to protect itself. This automatic response is commonly known as the "fight, flight, or freeze" response. While it serves an essential function in dangerous situations, chronic activation of this response due to daily stressors can have significant consequences for mental and physical health.
The body’s response to stress is rooted in human evolution. When our ancestors encountered a predator, their nervous systems immediately prepared them to either confront the threat (fight), escape to safety (flight), or become still and unnoticed (freeze). While modern-day stressors may not include wild animals, our nervous system reacts similarly to job pressures, financial worries, or social conflicts.
According to the Cleveland Clinic, stress is the body's response to change, activating a physiological reaction that helps us adapt and protect ourselves. While short-term stress can be beneficial, prolonged exposure can lead to an overactive stress response, negatively impacting overall well-being.
The Three Stress Responses: Fight, Flight, and Freeze
1. Fight
The fight response prepares the body for direct action. When triggered, the nervous system releases adrenaline, increasing heart rate, blood pressure, and muscle tension. While this reaction once helped early humans fend off predators, today it manifests as irritability, frustration, or aggression.
For instance, the employee who has experienced too much workload may work extremely long hours just to succeed. In short term, the action may produce good results but mostly ends in burnout, anxiety, and physical illness, for example, tension headache or digestion problems.
2. Fight
The flight response triggers an intense need to remove oneself from a stressful situation. Just as our ancestors would flee from danger, modern individuals may avoid conflict, quit jobs impulsively, or detach from relationships when overwhelmed.
Flight mode is linked with restlessness and anxiety. Individuals may have a sense of needing to get up and go-pacing, changing environments constantly, or avoiding tasks that seem too overwhelming. Someone with a flight response might have the desire to change jobs constantly, relocate constantly, or become reclusive in order to avoid perceived dangers.
3. Freeze
The freeze response occurs when the nervous system perceives a threat as too overwhelming to fight or flee. Rather than taking action, individuals shut down, feeling numb, disconnected, or paralyzed by fear.
Unlike fight or flight, which involve heightened activation, freeze mode slows down physiological functions. A person experiencing freeze mode may feel physically unable to move, struggle to make decisions, or find themselves dissociating from their emotions. This can manifest in situations such as public speaking anxiety, where someone might "blank out" or feel stuck in the moment.
What Happens in the Body During A Stressful Event?
When faced with a stressor, the autonomic nervous system (ANS) activates, triggering physiological changes, including:
- Increased heart rate and breathing: The body pumps more oxygen to muscles and the brain in case action is needed.
- Muscle tension: The body prepares for movement, sometimes causing trembling or stiffness.
- Dilated pupils: Vision sharpens to detect potential threats.
- Dry mouth: Saliva production decreases as the body redirects energy to essential functions.
- Changes in skin tone: Blood flow is directed to vital organs, sometimes making the skin appear pale or flushed.
For those experiencing the freeze response, the body undergoes a different reaction, often reducing heart rate and causing physical immobility rather than heightened activation.
Strategies for Coping and Managing the Stress Response
While the stress response is necessary for survival, frequent activation due to daily stressors can take a toll on health. Recognizing your default response—whether fight, flight, or freeze—can help in developing effective coping mechanisms.
1. Moving to a Safe Space
If possible, changing your environment can help signal to your brain that the threat has passed. Stepping outside for fresh air, finding a quiet place, or distancing yourself from overwhelming stimuli can help regulate emotions.
2. Practicing Controlled Breathing
Deep, slow breathing can be used to counteract the stress response by engaging the parasympathetic nervous system, which promotes relaxation. Techniques such as diaphragmatic breathing or the 4-7-8 method (inhale for four seconds, hold for seven, exhale for eight) can be particularly effective in calming the body.
3. Engaging in Physical Activity
This helps release pent-up energy and aids in the endorphin cascade, natural boosters for our mood.
4. Seeking Social Support
Relieving oneself from stress can come in many ways, but sharing it with trusted friends, a family member, or a good therapist will sure give that psychological boost of hope. Social support is an especially effective way of cushioning people against the stressors that they are subjected to in chronic forms.
When to Seek Professional Help
While occasional stress is normal, chronic activation of the fight, flight, or freeze response can indicate underlying mental health concerns, such as anxiety disorders or post-traumatic stress disorder (PTSD). If stress is affecting daily life—leading to sleep disturbances, difficulty concentrating, or persistent feelings of fear—it may be time to consult a mental health professional.
Jessie J 'Healing' After 2nd Breast Reconstruction Surgery: Why Some Patients Need Multiple Procedures
Credit: Jessie J/ Instagram
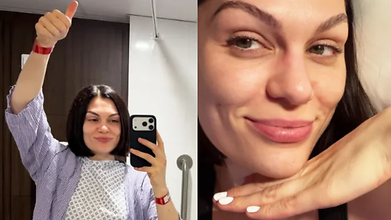
British pop star Jessie J has shared an update on her recovery after undergoing a second breast reconstruction surgery.
The 38-year-old singer-songwriter took to Instagram to share a series of photos, including one taken after her latest surgery. In the picture, she is seen wearing a hospital gown and giving a thumbs-up, with the caption, “to healing.”
The post marks Jessie’s first update since September, when she announced she would be taking a break from social media ahead of her surgery.
Jessie was diagnosed with early-stage breast cancer in 2025 and underwent a mastectomy. She announced in May 2026 that she was cancer-free.
Sharing the emotional news on Instagram, she admitted she "sobbed for hours and then exhaled for the first time in a year."
Jessie J’s Breast Cancer Diagnosis
Also read: World Breast Cancer Day 2026: Life After Breast Cancer, The Fear No One Sees
Jessie announced her diagnosis in June 2025, shortly after performing at Capital’s Summertime Ball at London’s Wembley Stadium. She spoke candidly about her diagnosis and the surgery she would undergo.
In a video message, she shared that she had been “in and out of tests” before receiving a diagnosis of early breast cancer.
“Cancer sucks in any form,” she said, adding that she was holding on to the word “early.”
Using her characteristic dark humor, she described the surgery as “a very dramatic way to get a boob job” and told her followers, “I will come back with massive boobs and more music.”
However, she also spoke openly about the emotional toll of the diagnosis, saying, “I need to process it and talk about it” and “I need a hug.”
What Is Breast Reconstruction Surgery?
Breast reconstruction surgery aims to restore the shape and contour of the breast after a mastectomy, which involves removing the entire breast. Depending on the cancer and the treatment plan, nearby skin and lymph nodes may also be removed.
Following a mastectomy, patients may choose breast reconstruction to restore breast shape and symmetry. The procedure can be performed at the same time as the mastectomy or at a later date, depending on the patient's circumstances and treatment plan.
Read More: Experts Explain Most Overlooked Breast Changes That Can Delay Diagnosis In Men
Why Do Some Patients Need Multiple Breast Reconstruction Surgeries?
According to the American Cancer Society, breast reconstruction often involves more than one operation. The number and type of procedures depend on the reconstruction method, the patient's needs and the desired outcome.
There are two main types of breast reconstruction:
- Implant reconstruction: A saline or silicone implant is used to rebuild the breast.
- Tissue flap reconstruction: Tissue taken from another part of the body is used to reconstruct the breast.
In some cases, surgeons combine the two approaches.
Reconstruction may be immediate, taking place during breast cancer surgery, or delayed until a later date. Both implant-based and tissue flap reconstruction can be performed using either approach.
After the initial reconstruction, some patients may undergo additional procedures to refine the breast's appearance or feel. These may include fat grafting, scar revision or procedures to recreate the nipple and areola, sometimes using medical tattooing.
Benefits And Risks Of Breast Reconstruction
Breast reconstruction can help restore breast shape and symmetry after a mastectomy. For some patients, it may also improve body image, confidence and emotional well-being. However, the benefits vary from person to person.
As with other surgical procedures, breast reconstruction carries potential risks and complications, including:
- Infection
- Fluid or blood accumulation
- Delayed wound healing
- Changes in sensation
- Implant-related complications
- Capsular contracture
- Blood clots, including deep vein thrombosis and pulmonary embolism
- Psychological effects.
Can Low-Dose Naltrexone Ease Long COVID Symptoms? New Study Examines The Evidence

Credit: iStock
Low-dose naltrexone has received plenty of attention as a strong candidate for treating people with chronic fatigue after COVID-19. But a new randomised clinical trial has found no significant improvement in fatigue, pain or any other symptoms when compared to a placebo.
The study, posted on medRxiv, examined low-dose naltrexone (LDN) in adults with post-COVID fatigue syndrome. The findings challenge hopes that an existing repurposed drug could provide relief for people whose symptoms have not subsided months after infection.
The paper has not yet undergone peer review, which means its findings have not been independently evaluated in a formal manner.
Study Based On 160 Adults With Long COVID
160 adults aged 19 to 69 from British Columbia and Ontario, Canada participated in the trial. Participants had developed symptoms that resembled myalgic encephalomyelitis/chronic fatigue syndrome (ME/CFS) after a SARS-CoV-2 infection.
Researchers randomly assigned participants either low-dose naltrexone or a placebo for 16 weeks. The naltrexone dose began at 1 milligram daily and increased to a maximum of 4.5 milligrams, depending on how participants tolerated the treatment.
The main outcome was fatigue severity, which was measured using the Fatigue Severity Scale. At the end of the study, the average fatigue score was 4.2 in the LDN group and 4.4 in the placebo group.
The difference between the groups was not statistically significant, meaning the trial proved that the drug did not improve fatigue.
Researchers also found no significant differences between the groups in pain, overall ME/CFS symptoms, daily step counts or any other health aspects related to quality of life.
These results suggest that LDN did not provide any measurable benefit for the participants. The study also found that LDN was generally well tolerated over the 16-week period.
However, adverse events classified as grade 3 or higher were reported in five participants in the LDN group, or 6.2%, compared with three participants in the placebo group or 3.8%.
Why Has Low-Dose Naltrexone Attracted Interest?
Also read: 'I Never Recovered From That Crash': US Physicist Recalls Her Years-Long Battle With Long COVID
Naltrexone is an established medicine used at standard doses to treat alcohol use disorder and opioid use disorder. At much lower doses, it has been tested for conditions involving chronic pain, inflammation and fatigue.
LDN’s effects on immune signalling and inflammatory conditions have sparked interest in its potential use for long COVID, a condition that can involve fatigue, cognitive difficulties, pain, breathlessness and symptoms affecting several biological functions.
Researchers Caution
The findings apply specifically to adults with post-COVID fatigue syndrome who met the study’s criteria for ME/CFS-like symptoms.
Long COVID refers to symptoms that occur after a SARS-CoV-2 infection and cannot be explained by another diagnosis. Symptoms vary widely and may include fatigue, cognitive difficulties, breathlessness, sleep disturbances and problems with everyday activities.
Some people improve over time, while others experience prolonged illness that affects their ability to lead routine lives.
The results do not mean that long COVID symptoms are untreatable. Instead, they highlight how difficult it can be to identify effective treatments for a condition with varied symptoms.
There are currently no FDA-approved medicines specifically for long COVID, and care often focuses on managing individual symptoms.
People taking or considering naltrexone should discuss its benefits and risks with a healthcare professional rather than starting or changing treatment on their own.
Low-Dose Aspirin Shows At Least 70% Lower Dementia Risk In Older Adults But A Serious Complication Still Remains
Credit: iStock
Low-dose aspirin could play a key role in lowering the risk of dementia significantly in some older adults, according to a new genetic analysis. However, the benefit does not come without a complication: major bleeding.
The study, led by researchers at Monash University in Australia, is based on data from more than 13,500 participants in the ASPREE trial, which investigated the effects of low-dose aspirin in older adults. The study was published in Alzheimer’s & Dementia: The Journal of the Alzheimer’s Association.
Researchers found that the benefit was mostly seen among people with a specific genetic trait linked with platelet count.
70% Lower Dementia Risk Was Seen Among Older Adults
Platelets are small blood components that help form clots and stop bleeding. Researchers have previously examined how aggregation of platelets might contribute to dementia, but the role of genetically influenced platelet counts still remains unclear.
The researchers examined genetic scores related to platelet count and compared dementia results among participants who were either assigned aspirin or placebo.
Among people in the highest 20% of platelet count genetic scores, dementia developed in 1% of those taking aspirin, compared with 3.3% of those receiving a placebo. This represented approximately a 70% lower risk.
Lead author Dr Peter Fransquet, a research fellow at Monash University's School of Public Health and Preventive Medicine, said, “Previous trials found aspirin didn't prevent dementia when everyone was considered together.”
“Our findings suggest there may be more to the story,” he said.
Risk Of Bleeding Increased
Also read: Trump Says He ‘Psychologically’ Needs To Pop Aspirin Every Day: But Is It Actually Safe?
The benefit was accompanied by a safety concern. Among participants in the same genetic subgroup, major bleeding occurred in 4.4% of those assigned to aspirin, compared to 2.1% of those given a placebo. That is a difference of 2.3 percentage points in both dementia cases and major bleeding events. In other words, the lower dementia rate cannot be considered in isolation from the increased bleeding risk.
Aspirin reduces the ability of platelets to form clots. This can be useful for certain people who need to take precaution against cardiovascular events, but it can also increase the risk of serious bleeding, including bleeding in the gastrointestinal tract or brain.
The study therefore does not prove that aspirin offers a favourable overall balance of benefits and harms for people with this genetic profile.
Could This Help Personalise Dementia Prevention?
The researchers found that the genetic signal was not linked to established genetic risk factors for Alzheimer's disease and dementia. Instead, it pointed towards platelet factor as a possible direction for further research.
“What's particularly interesting is that the signal wasn't linked to the established genetic risk factors for Alzheimer's disease and dementia,” Fransquet said. “Instead, it's pointing us towards platelet biology and gives us a new avenue to investigate.”
The findings could contribute to more personalised approaches to dementia prevention, in which treatments are tailored to characteristics that influence how individuals respond. But the results need to be replicated in other populations and tested in a clinical trial specifically designed for people with the identified genetic profile.
Fransquet said, “People shouldn’t start taking aspirin to prevent dementia on the basis of this study without consulting with their doctor, particularly given the increased risk of serious bleeding,” he said.
- Follow Us :


© $2026 Times Horizon Private Limited