
- Health Conditions A-Z
- Health & Wellness
- Nutrition
- Fitness
- Health News
- Ayurveda
- Videos
- Medicine A-Z
- Parenting
Ever Had Numb Legs After Using The Toilet? Here’s What It Means

Image Credit: Canva
We've all been there, you use the toilet, try to stand up, and suddenly your legs go numb. That odd pins-and-needles feeling can be surprising and uncomfortable. Though it might feel like a small inconvenience, it does have a scientific explanation. The numbness, also called transient paresthesia, happens when pressure blocks blood flow or presses on nerves in your lower extremities. It is normally harmless, but frequent occurrences can be signs of underlying health issues or poor toilet habits that must be addressed.
That weird numbness you experience after going to the bathroom is typically just a temporary annoyance, most often due to bad posture, straining, or sitting for an extended period. But if the numbness continues or gets worse, it is important to get medical guidance to make sure there are no underlying health issues. We discovered the top three reasons that could be responsible for this tingling and how can you avoid it? Let's dissect.
3 Reasons Your Legs Go Numb on the Toilet
1. You’re Straining Too Much
Struggling to push during a bowel movement can put excessive pressure on your abdomen and spine. This increased pressure can shift spinal discs, pressing against nerves that extend into your legs and feet. The result? A temporary loss of sensation, tingling, or weakness in your lower limbs.
Straining usually results from constipation, which in turn can be caused by a low-fiber diet, dehydration, or inactivity. If you notice that you're straining frequently, perhaps it's time to change your eating and drinking habits to help move your bowels more easily.
2. Inadequate Sitting Posture
The way you sit on the toilet can also be a cause of that numbness in your legs. Most people are prone to hunching over when they are using their phones, reading, or just focusing too intensely. But this position can compress nerves and blood vessels in your pelvis, causing tingling or numbness.
When you sit slumped forward, you cut off blood supply to the lower half of your body, compressing nerves that travel from your pelvis to your toes. That's why the numbness will often radiate past your thighs and into your toes.
Also Read: NYC Legionnaires Disease Outbreak 2025: 108 Cases, 5 Deaths in Harlem - Latest Updates & Safety Info
3. Sitting for Too Long
The more time you spend sitting on the toilet, the higher your chance of getting numb legs. Protracted sitting continually puts pressure on the nerves within your lower limbs, slowing blood flow and leaving you with the familiar pins-and-needles feeling.
If you habitually stay on the toilet for a long time, either from digestive problems or distractions such as browsing your phone, you may find that there is more numbness over the course of time. If constipation is leaving you on the toilet longer than normal, diet changes can calm your system.
How to Stop Your Legs from Falling Asleep on the Toilet
Although periodic tingling is not a health issue, recurring numbness is a problem that needs to be addressed. Below are some professional-recommended ways of preventing it:
1. Proper Posture
Being seated with your knees higher than your hips can make all the difference. Sitting this way enables your colon to unwind, facilitating smooth bowel movements while minimizing pressure on the lower parts of your body.
Don't slouch, as this squishes nerves and blood vessels, making numbness more likely. If necessary, lean your back against the toilet tank or wall to keep your posture good.
2. Don't Spend Too Long on the Toilet
Specialists recommend five to ten minutes of toilet time per visit. If you are straining, stand up, walk around, and try later. Forcing the bowel movement can cause more damage than benefit, putting greater pressure on your spine and worsening numbness.
If constipation is a chronic problem, being hydrated and consuming fiber foods such as fruits, vegetables, and whole grains can get your digestive system back in working order.
3. Use a Toilet Stool
Raising your feet using a toilet stool may position your body for a more natural and strain-free bowel movement. A squatting position keeps the rectal canal open, minimizing the need to push and reducing the risk of leg numbness.
4. Try a Padded Toilet Seat
Hard toilet seats can restrict circulation in your lower body, increasing the risk of numbness. A cushioned or padded toilet seat can provide better support, improving blood flow to the legs and feet while reducing pressure on the pelvis.
When to Seek Medical Advice
While it's normal to have some numbness in your legs from time to time when sitting on the toilet, ongoing tingling or numbness in your lower extremities may be a symptom of an underlying medical condition. If you find yourself experiencing:
- Bathroom-use-independent frequent numbness
- Muscle weakness
- Pain or discomfort in legs or lower back
- Loss of bladder or bowel control
It's best to see a healthcare expert to exclude conditions such as nerve compression, circulatory disorder, or spinal condition.
Inflammation May Be Quietly Changing Your Heart: Study Finds 43% Higher Risk Of Heart Attack & Stroke
Credit: AI
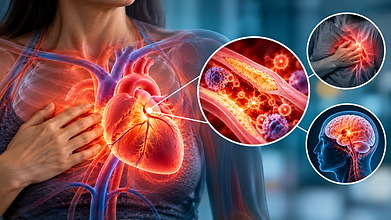
You can feel fine and still have a heart that is slowly changing. Researchers at Imperial College London and the MRC Laboratory of Medical Sciences say millions of people could be living with hidden inflammation that does exactly that. They say the changes can start years before any symptoms show up.
"Our study, which is the largest of its kind, suggests that millions of people could be living with hidden inflammation, which is slowly changing their heart and causing long-term damage," said Professor Declan O'Regan, British Heart Foundation Chair of Cardiovascular AI at Imperial College London.
What The Study Found
The study was published in the European Journal of Preventive Cardiology. The team looked at data from nearly 480,000 adults in the UK Biobank, a large health database, Imperial says. They measured a blood marker called glycoprotein acetyls, or GlycA for short, which the paper uses to measure chronic inflammation. They also used heart scans and genetic data.
People with the highest levels of inflammation, the top 20%, had a 43% higher risk of heart attack and stroke than those with the lowest levels, the bottom 20%, according to Imperial.
Imperial adds that higher levels also went with changes in the heart itself. These included thicker heart walls, smaller heart chambers and poorer filling of the heart. The researchers say such changes can build quietly for years before possibly leading to heart failure.
Read More: Childhood Vaccine Rates Decline Across Europe, Lancet Study Finds
Where The Inflammation Comes From
Chronic inflammation is a long-term, low-level activation of the immune system, Imperial explains. It has been linked to cancer and diabetes, and is increasingly seen as a driver of heart disease.
According to Imperial, higher inflammation was strongly linked to poorer social and economic circumstances and to mental distress, as well as to smoking and excess body fat.
"The surprising thing was how much social factors and mental health are linked to inflammation and damage to the heart, as well as more well-known risk factors like smoking and inactivity," O'Regan said. He added that there was also a strong genetic factor, "with some people being naturally more resilient or susceptible to the inflammatory damage that comes from different lifestyles."
What Could Come Next
The study named proteins from the interleukin-1 and TNF families as likely drivers of the damage, Imperial says. Several are already targeted by drugs in clinical trials, which Imperial says raises hopes that anti-inflammatory treatments could help prevent heart disease before symptoms begin. The researchers say combining inflammation blood tests with genetic risk scores could help find the people who would benefit most from early action.
There is earlier proof that this idea can work. In the 2017 Canakinumab Anti-inflammatory Thrombosis Outcomes Study, or CANTOS trial for short, led by Paul Ridker and published in the New England Journal of Medicine, 10,061 people who had already had a heart attack, and had high inflammation, were given canakinumab or a placebo. The paper concluded that at the 150 mg dose, given every three months, canakinumab led to fewer repeat cardiovascular events than the placebo, independent of any drop in cholesterol. But those were heart attack survivors, not people without symptoms.
What to keep in mind
The study reports links, and the researchers describe inflammation as one possible pathway to heart damage. They also stress that being genetically susceptible, or living in hard circumstances, does not mean a person will develop heart disease, and that much can be done to prevent long-term inflammation.
Sudden Floaters, Flashes Or Blurred Vision? When Should You Seek Emergency Care For Retinal Changes
Credit: AI
A few floaters, a brief flash of light or mild blurring across your vision may seem harmless at first. But when these changes appear suddenly without any probable cause, they may signal a bigger problem. On World Retina Day, experts explain when your retina needs urgent medical attention.
The retina is the light-sensitive layer at the back of the eye, which plays a crucial role in maintaining healthy eyesight. Some retinal conditions may develop without obvious symptoms in early stages, while others can present suddenly and threaten your eyesight if treatment is delayed.
“Retinal health is fundamental to maintaining clear vision and preserving quality of life, yet many retinal conditions can develop silently, without obvious warning signs in their early stages,” Dr Rajesh Kapoor, Medical Director, Suruchi Eye Hospital, Navi Mumbai told HealthandMe.
“By the time a person begins to notice blurred or distorted vision, dark spots, flashes, floaters, or other visual changes, the condition may already require urgent medical attention. This is why we need to shift our approach from waiting for symptoms to prioritizing awareness, regular comprehensive eye examinations and timely consultation with an ophthalmologist.”
What Are Floaters And Flashes?
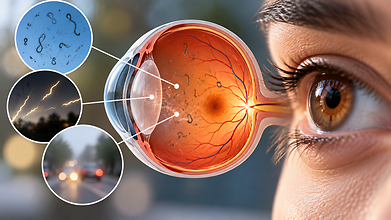
Floaters can look like tiny dots, lines, specks or cobweb-like shapes moving across your field of vision. They are easier to notice when looking at a bright background.
Flashes, on the other hand, can look like brief streaks or bursts of light. They may occur even when there is no actual source of light around you.
Occasional floaters can occur for reasons that are not always serious. However, a sudden increase in floaters or the sudden appearance of flashes should not be dismissed, especially if there are other changes in vision. One of the conditions doctors want to rule out in such situations is retinal detachment.
Also read: Ferritin Face: Can Pale Skin Signal Iron Deficiency?
What Is Retinal Detachment?
“Retinal detachment is a serious condition which requires urgent medical attention and occurs when the retina, the light sensitive layer at the back of the eye pulls away from its normal position,” Dr Mudit Tyagi, Scientific Chair, VRSI and Head, Smt Kanuri Santhamma Center for VitreoRetinal Diseases, L V Prasad Eye Institute, Hyderabad told HealthandMe.
There are several possible causes of retinal detachment. According to Dr. Tyagi, they include injury to the eye, high myopia and certain eye diseases.
When the retina separates from its normal position, its ability to function properly can be affected. The longer the condition remains untreated, the greater the concern about permanent vision loss.
Sudden Flashes And A Curtain Or Shadow Over Your Vision
The symptoms of retinal detachment can vary, but certain changes should warrant immediate medical attention.
A dark curtain or shadow across the field of vision is concerning because it can represent a portion of the visual field being lost.
Dr. Tyagi said, “The urgency of recognising retinal detachment can’t be overstated. If you have sudden flashes of light, a dramatic increase in floaters, or a dark shadow or curtain across your field of vision, don’t ignore it, even if there is no pain.”
The absence of pain should not be misconstrued as a non-emergency. A retinal problem can occur without the kind of discomfort people usually associate with an eye emergency.
Also read: The 5 Climate-Related Eye Risks Every Indian Should Know
Timing Is Key
Retinal detachment is not a condition where it is advisable to wait and see whether symptoms settle on their own. “Retinal detachments, if detected in time and operated early enough can result in a good recovery of vision,” Dr Tyagi said.
He added, “It is important, therefore, to be vigilant and see an eye care specialist as early treatment can help avoid preventable loss of vision. So, timely recognition and diagnosis followed by right treatment can help save vision.”
This is why sudden visual changes deserve attention even if they seem minor initially.
Who Is At Risk?
Some people may need to be particularly proactive about retinal health. Dr. Kapoor said individuals with diabetes, increasing age, a family history of retinal disease or other risk factors that may affect retinal health should be more careful and alert.
Diabetes can affect the blood vessels supplying the retina and lead to diabetic retinal disease. Regular eye examinations can help identify changes before vision is significantly affected. Dr Kapoor also stressed that screening should not necessarily wait until symptoms appear.
“Advances in retinal imaging, diagnostics and treatment today provide ophthalmologists with valuable opportunities to identify and manage several retinal conditions at an earlier stage. However, technology can make its greatest impact when people seek eye care at the right time.”
A sudden change in vision does not automatically mean that a person has retinal detachment. But because some retinal conditions can progress rapidly, it is important to have sudden symptoms assessed rather than trying to determine their cause on your own.
Dr Kapoor said: “Through greater public awareness and proactive screening, we can encourage people to take retinal health more seriously. Protecting sight begins with understanding that healthy vision should never be taken for granted—because when it comes to the retina, we should not wait for a problem to become noticeable before taking action.”
Radiotherapy Cuts Risk Of Atypical Meningioma Recurrence By Nearly Half: Lancet Study
Credit: AI
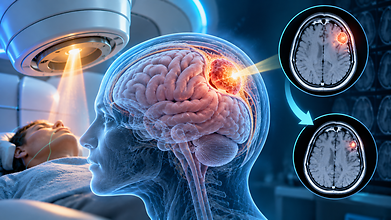
After surgery, radiotherapy could significantly decrease the chances of an atypical meningioma returning, according to a new international phase 3 trial published in The Lancet.
The findings come from the ROAM/EORTC-1308 trial, the first randomised controlled trial to directly test whether patients with a completely removed atypical meningioma benefit from receiving radiotherapy or whether regular scans and observation are enough.
The results could help settle a treatment question that has remained uncertain for years.
What Is An Atypical Meningioma?
Meningiomas are the most common brain tumours in adults. They develop from the meninges, the protective membranes surrounding the brain, and spinal cord.
An atypical meningioma is classified as a WHO grade 2 tumour. Unlike grade 1 meningiomas, that generally grow slowly, grade 2 tumours are more likely to grow again after surgery.
Even when surgeons manage to remove the entire visible tumour, microscopic tumour cells may remain, sparking a risk of recurrence.
Also read: The Gynecological Cancer Symptoms Women Often Mistake for “Normal” Ageing Like
What Did The Lancet Study Find?
The ROAM/EORTC-1308 trial enrolled 157 patients whose atypical meningiomas had been completely removed surgically. They were randomly assigned to either:
- Radiotherapy: 78 patients received 30 sessions of radiotherapy
- Observation: 79 patients underwent regular imaging surveillance
After a median follow-up of about five years, the difference in recurrence was significant. 14% of patients in the radiotherapy group experienced a recurrence, compared to 30% in the observation group. In other words, the risk of recurrence was reduced by nearly half with postoperative radiotherapy.
Additionally, at five years, about 80% of patients receiving radiotherapy remained free of recurrence, compared to about 64% of those who were monitored without immediate radiotherapy.
Also read: After 70% of His Tongue Was Removed For Cancer, Lawyer Regains Speech & Returns To Court
The Trial Cements Necessary Evidence
Until now, doctors have had to weigh two approaches after complete surgical removal of an atypical meningioma.
One option is to give radiotherapy immediately, hoping to destroy microscopic tumour cells that surgery may have missed. The other is to monitor the patient with regular brain scans and use radiotherapy if the tumour returns.
The uncertainty existed as strong randomised evidence showing whether immediate radiotherapy actually reduced recurrence had been lacking. The trial helps cement that evidence.
Who Needs Radiotherapy After Surgery?
The researchers say that treatment decisions still need to be made jointly by doctors and patients, taking into account possible side effects and the long-term consequences of radiation treatment. Serious radiation-related complications were uncommon in the trial.
The study also did not establish whether the recurrence benefit extends beyond five years. This means that longer follow-up will be needed to gather more evidence. According to the researchers, the findings are expected to shape national and international treatment guidelines.
The options may extend for patients who have undergone complete removal of a WHO grade 2 atypical meningioma. Rather than contemplating “Should we simply watch and wait?”, they can consider moving to a more evidence-based discussion about whether postoperative radiotherapy should be offered upfront.
- Follow Us :


© $2026 Times Horizon Private Limited