
- Health Conditions A-Z
- Health & Wellness
- Nutrition
- Fitness
- Health News
- Ayurveda
- Videos
- Medicine A-Z
- Parenting
Can Music Reconnect With Memories In Elders With Dementia? Expert Says Especially If It's In Their Mother Tongue

Dementia (Credit: Canva)
Music therapy taps into long-term memory, which remains intact longer than short-term memory in dementia patients.
"One of our patients struggles to recall much from his past. He has Dementia. However, whenever he listens to songs in his mother tongue, it boosts his mood and reconnect with his memories," Neha Sinha, Dementia Specialist, Psychologist, CEO & Co-founder of Epoch Elder Care told me recently.
This made me wonder if music can really help elderly patients with complex neurodegenerative diseases like Parkinson's, Dementia and Multiple Sclerosis. Turns out that it can. While it does not specifically treat them, music definitely helps stabilize symptoms, fostering emotional well-being and improving the quality of life for patients.
Music And Memories To Treat Physical Symptoms
Behavioural challenges, such as aggression, anxiety, and social disinhibition, are common in patients with Dementia. Music therapy addresses these issues by creating a calming atmosphere and making them more open to treatment. "Listening to or engaging with music can soothe anxiety, regulate sleep patterns, and encourage them to be more receptive to assistance in performing their activities of daily life (ADL) more comfortably. Moreover, Reminiscence therapy, which helps recall events and discuss past events to improve their well-being, is known to be profoundly effective in treating such conditions.
Music therapy also taps into long-term memory, which remains intact longer than short-term memory in those suffering from Dementia. Familiar tunes or songs from childhood can stimulate certain neural connections, particularly if they are in their mother tongue. This soothes their anxiety, provides comfort and even prompts them to engage in social conversations.
Additionally, music therapy aids motor coordination, which is particularly helpful to those with Parkinson's. Incorporating rhythmic movements like walking or light dancing to music can improve muscle relaxation and enhance motor abilities. While there is no direct evidence linking music therapy to alleviating physical symptoms, its positive impact on mood and cognitive function makes patients more receptive to medical treatment.
Music Therapy Has Shown Significant Benefits
Healing with music is believed to date back to ancient Greece when music was used in an attempt to cure mental disorders. Throughout history, music has been used to boost morale in military troops, help people work faster and more productively, and even ward off evil spirits by chanting.
Music therapy does not involve specialists in most cases. It involves:
- listening to music
- singing along to music
- moving to the beat of the music
- meditating
- playing an instrument
Hot Flashes To Night Sweats: Leading US OB-GYN Group Updates Menopause Treatment Guidance After 12 Years

Credit: iStock
Menopause is gradually finding its well-deserved place in mainstream media. For the first time in a dozen years, the American College of Obstetricians and Gynecologists (ACOG) has revised its clinical guidance on treating key menopause symptoms like including hot flashes, night sweats, sleep disturbances and mood swings.
The new guidance, released in October 2026, talks about hormone therapy as the most effective treatment for moderate to severe hot flashes.
It also highlights non-hormonal options like cognitive behavioural therapy, mindfulness and clinical hypnosis for women who do not want to opt for hormone therapy.
The update comes after certain boxed safety warnings on hormone-based products were removed by the US Food and Drug Administration (FDA).
Hormone Therapy Recommended For Women With Menopause
Also read: Beyond “Just Ageing”: Why Menopause Deserves a Place in India’s Mainstream Healthcare Conversation
Menopausal hormone therapy (MHT) is the most effective treatment for vasomotor symptoms, which include hot flashes and night sweats. These symptoms occur as changing hormone levels affect the body's temperature.
ACOG recommends systemic hormone therapy containing oestrogen and a progestogen for women with a uterus. Women who do not need endometrial protection may receive oestrogen alone.
The guidance also suggests considering hormone therapy for sleep disturbances, which is also one of the vasomotor symptoms.
However, hormone therapy may not be a viable option for everyone. Decisions should be made jointly by patients and their doctors, which may be taken after taking into account age, medical history, cardiovascular disease risk, breast cancer risk and the risk of venous thromboembolism, or blood clots.
ACOG also recommends starting treatment before the age of 60 or within 10 years of the onset of natural menopause for.
Women Who Cannot Take Hormone Therapy
Women who cannot take hormone therapy have several other non-hormonal options. ACOG recommends selective serotonin reuptake inhibitors (SSRIs) and serotonin-norepinephrine reuptake inhibitors (SNRIs), which are antidepressant medicines that can also help manage hot flashes.
Another option is neurokinin receptor antagonists. These medicines act on pathways involved in regulating body temperature and can reduce hot flashes and night sweats. Fezolinetant and elinzanetant are examples of medicines in this category.
Gabapentin may also be considered when other non-hormonal medicines are ineffective .
Lifestyle And Behavioural Changes
The updated guidance also recognises lifestyle and behavioural changes for managing menopause symptoms. ACOG suggests cognitive behavioural therapy (CBT) to help with hot flashes, sleep disturbances and mood symptoms.
Mindfulness-based interventions and physical exercise may help improve sleep and mood, while clinical hypnosis may reduce hot flashes and improve sleep and anxiety symptoms.
Acupuncture is also an option that may help tackle vasomotor symptoms and improve sleep and mood.
These alternative options can be used alone or alongside medication, depending on a woman's symptoms and treatment preferences.
Menopause can affect several aspects of health and daily life. Hot flashes and night sweats can disrupt sleep, while mood changes and other symptoms may affect work, relationships and overall quality of life.
For a long time, concerns about the risks of hormone therapy have influenced how patients and doctors approach treatment.
The new guidance reinforces that hormone therapy remains an effective option for many women, while stressing the importance of individual risk assessment and preference.
Perimenopause Is Not Just About Periods: The Metabolic Changes Women Should Know About
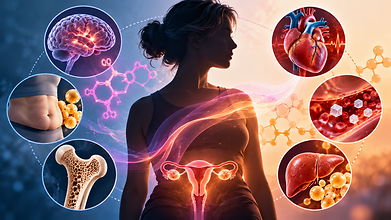
Credit: AI
When we think of perimenopause, irregular periods, hot flashes and mood changes usually come to mind. But the transition to menopause is not limited to the menstrual cycle. Behind the scenes, changing ovarian hormones—particularly fluctuating and eventually declining estrogen—can influence body composition, insulin sensitivity, cholesterol levels, bone health and cardiovascular risk.
For many women, these metabolic changes begin years before their final menstrual period.
Why does weight suddenly behave differently?
A common concern during perimenopause is: “I haven’t changed my diet, so why am I gaining weight around my abdomen?”
Ageing itself contributes to gradual loss of muscle mass and changes in energy expenditure. At the same time, the menopausal transition is associated with a shift in fat distribution, with a greater tendency to accumulate visceral or abdominal fat.
This matters because visceral fat is metabolically active. An increase in abdominal fat can be associated with insulin resistance, abnormal cholesterol levels and a higher risk of metabolic disease. So, the change in waist circumference may sometimes tell us more about metabolic health than the number on the weighing scale alone.
Also read: After Menopause, These Breast Changes Shouldn’t Be Ignored
Blood sugars may raise up too
Estrogen interacts with several pathways involved in glucose and fat metabolism. During midlife, changes in body composition, reduced physical activity, sleep disturbance and hormonal changes can collectively make insulin sensitivity less favourable.
This does not mean every woman going through perimenopause will develop diabetes. However, women who already have risk factors—such as overweight or obesity, prediabetes, a history of gestational diabetes or a strong family history of type 2 diabetes—should be particularly mindful.
Cholesterol and heart health deserve attention
The menopausal transition can also be accompanied by unfavourable changes in the lipid profile, including changes in LDL cholesterol. Cardiovascular risk increases with age, and menopause is an important time to reassess risk factors such as blood pressure, glucose, cholesterol, smoking, physical activity and body composition.
Women often spend years focusing on reproductive health while overlooking these equally important metabolic markers.
Also read: World Menopause Day: Is It Empty Nest Syndrome Or Menopause Symptoms? Expert Explains
Muscles and bones need attention as well
Midlife is also an important period for protecting muscle and bone. Declining estrogen after menopause accelerates bone loss, while ageing contributes to loss of muscle mass.
Resistance training therefore becomes especially valuable. Adequate protein intake, regular weight-bearing exercise, sufficient calcium and vitamin D, good sleep and avoiding smoking can support healthier ageing.
What should women do?
Perimenopause should not be viewed as a disease, nor should every symptom or kilogram gained in midlife automatically be blamed on hormones. Instead, it is an opportunity for a metabolic health check.
Women should discuss appropriate screening for blood pressure, blood glucose or HbA1c, lipid profile, weight and waist circumference monitoring , DEXA scan for bone health, depending on their individual risk factors.
Most importantly, don’t wait for menopause to start thinking about metabolic health. The perimenopausal years can be an important window to build muscle, improve fitness, optimise nutrition and identify metabolic risk early.
Perimenopause is more than a change in periods—it is a transition in whole-body health. Understanding these changes early can help women enter the next phase of life stronger, healthier and better prepared.
(By Dr. Seema Daksh, MBBS, MD (Internal Medicine), DM (Endocrinology), Consultant Endocrinologist,Kailash Hospital, Greater Noida)
Loud Snoring Is Not Always Harmless: Sleep Apnoea can Become a Stroke-Risk Concern

Credit: iStock
Loud habitual snoring is often dismissed as a nuisance or simply a part of sleeping. For some people, it may be an early warning sign of obstructive sleep apnoea, a condition in which breathing repeatedly slows or stops during sleep. When left unaddressed, sleep apnoea can quietly strain the heart and blood vessels, increasing the risk of blood pressure, irregular heart rhythms, heart attack and stroke.
Snoring happens when relaxed tissues in the throat vibrate as air moves through a narrowed airway. Not everyone who snores has a problem and occasional snoring is common. However loud and regular snoring, especially when a bed partner notices pauses in breathing, choking or gasping should not be ignored. It may indicate sleep apnoea, where the airway collapses repeatedly during sleep.
Each time breathing stops, oxygen levels drop. The brain briefly wakes the body up to restart breathing. Most people do not remember these interruptions but their body feels the effects. Over time, this cycle can disturb sleep, raise blood pressure, increase inflammation and put pressure on the cardiovascular system.
Also read: ‘Godzilla’ Drug Retatrutide Reverses Sleep Apnea In 1 In 4 Diabetes Patients
Risk factor & symptoms
Sleep apnoea is increasingly recognised as a risk factor for stroke. It can worsen hypertension. Contribute to atrial fibrillation, an irregular heartbeat that raises the likelihood of a stroke. The concern becomes greater in people who already have conditions such as diabetes, obesity, high cholesterol or a family history of heart disease.
For them, untreated sleep apnoea may add to the strain on the heart and blood vessels. A landmark study by the All India Institute of Medical Sciences (AIIMS) New Delhi estimates that roughly 104 million Indians suffer from Obstructive Sleep Apnea (OSA), with about 47 million cases classified as moderate to severe.
There are also signs that should prompt a conversation with a doctor. Waking up unrefreshed despite spending hours in bed, feeling excessively sleepy during the day, experiencing morning headaches, and struggling to concentrate or becoming unusually irritable can all be linked to poor-quality sleep caused by sleep apnoea. If snoring is accompanied by any of these symptoms a sleep study may be recommended to confirm whether it is snoring or a more serious breathing disorder.
Remedies
The reassuring part is that sleep apnoea is treatable. Depending on its cause and severity, doctors may suggest weight management where relevant, avoiding alcohol and sedatives close to bedtime, treating congestion, changing sleep position, using an oral appliance or undergoing CPAP therapy, which keeps the airway open during sleep.
The message is not to worry about every snore but to take loud snoring seriously particularly when it comes with breathing pauses or daytime tiredness. Early diagnosis can improve sleep, energy and overall quality of life while helping reduce long-term risks to the heart and the brain.
- Follow Us :


© $2026 Times Horizon Private Limited