
- Health Conditions A-Z
- Health & Wellness
- Nutrition
- Fitness
- Health News
- Ayurveda
- Videos
- Medicine A-Z
- Parenting
Calcium, Vitamin D Do Not Guarantee Protection From Fractures And Falls, These 8 Things Do!

Bone Health In Older Adults (Credit-Canva)
Strengthening your bones is not something that can happen overnight, it takes years for your body to build strong bones and even then, it is natural for them to lose their dexterity. All you can do is keep your body healthy to make sure it is prepared for any unexpected situations. For years, many older adults have been told to take vitamin D and calcium supplements to keep their bones strong and prevent falls. However, a new report from U.S. Preventive Services Task Force (USPSTF) is changing that advice. This report suggests that for most older people, these supplements don't actually prevent falls or broken bones. This might be surprising news, we must understand why falls happen more often as we age, what vitamin D and calcium do in the body, and most importantly, what you can do to stay safe and prevent fractures.
What the Report Says
According to the report, vitamin D supplements don't seem to help prevent falls or broken bones for most people over 60. They also found that these supplements, especially with calcium, might increase the risk of kidney stones. This report doesn't mean people with weak bones (osteoporosis), low vitamin D, or who take vitamin D for other health reasons shouldn't take it. It just means that for most healthy older people, these supplements don't prevent falls and fractures.
Why Older People Fall and Break Bones More Easily
There are many reasons why older people are more prone to breaking their bones. Our bones are strongest when we're in our 20s and 30s, and they get weaker as we age so naturally, they can break easily. It can also be harder to move around as we get older, sometimes because of problems like arthritis this can affect how we walk and make us less steady.
There are also different issues like neuropathy, which is a nerve problem that can also make it harder to feel your feet and keep your balance. Eyesight is also a culprit as it can cause you to feel dizzy and fall. Some medicines can also make people feel unsteady, and older people often take more medicines than younger people. Low vitamin D itself can also increase the risk of falls, so keeping vitamin D levels up is still important.
Better Ways To Protect Your Bone Health
USPSTF recommends a few better ways to protect your bone health and prevent broken bones and falls.
Walk Regularly
Regular walks strengthen your muscles and bones, which helps you stay steady on your feet. It is as simple as practice makes perfect so the more you walk, the better it is. Walking also improves your balance, making you less likely to fall.
Do Strength Training
Strength training, like lifting weights or using resistance bands, makes your bones stronger and helps prevent fractures if you do fall. It is like a safety cushion, but you must be careful while doing so because it can lead to injuries if done too much.
Practice Balance
Activities like tai chi, Pilates, and yoga can improve your balance and coordination, making you more stable and less prone to falls. These can also help you improve your muscle flexibility and strength that in turn helps your body be stronger.
Check Your Medicines
If you have osteoporosis, talk to your doctor about medications that can help strengthen your bones and lower your risk of fractures. Many medications can also have unsavory side effects like weakened joints, losing muscle strength, etc.
Eat Enough Protein
A proper diet goes a long way when it comes to your entire body health. So to keep up with your body’s nutrition and muscle health, eat more protein along with a balanced meal that includes loads of fiber, healthy fats and carbs.
Get Your Eyes Checked
Having poor eyesight can be difficult, not only does it make life difficult without glasses, but it also increases the possibilities of getting into minor accidents like bumping into people and missing objects placed in front of us.
Get Enough Sleep
Getting enough sleep is also important because when you are not sleeping, you get disoriented and can ignore even obvious things like the last stair in the staircase. Make sure you get enough sleep to keep you fresh and focused.
Make Your Home Safe
There are many things that can cause you to have accidents, even in your home. To avoid such falls, make sure there are no lose ends like crooked floor panels, rugs that are sticking out or protruding furniture that can hurt your knees
Migraine Is More Than A Headache: Lancet Review Explains What Happens In The Brain During Attacks
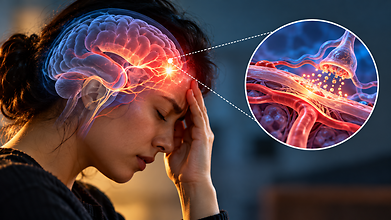
Credit: AI
A migraine attack is characterised by nausea, vomiting and sensitivity to light and sound. But early symptoms may surface long before the headache itself. Signs like fatigue, mood changes, food cravings and difficulty focusing may appear hours or even days before the pain.
The symptoms that occur during the attack reflect a complex neurological process that involves several interconnected brain networks, rather than just a headache.
A new Lancet Seminar review, looks deeper into how migraine develops, why its symptoms extend beyond head pain and how the better understanding of its biology are affecting treatment.
The study authors describe migraine as a chronic neurovascular disorder shaped by genetic susceptibility and interactions between the brain’s sensory networks, nerves, and blood vessels.
What Happens In The Brain During A Migraine Attack?
Also read: These Yoga Asanas Could Cure Your Migraine
Migraine is the result of the interaction of multiple systems responsible for processing sensory information and transmitting pain. Researchers are focusing more on other factors that drive migraine rather than just blood vessel narrowing or widening.
An important concept is the trigeminovascular system, which is a network involving the trigeminal nerve, tissues sensitive to pain that surrounds the brain and blood vessels. When this system gets activated, the patient experiences the peculiar head ache.
Chemical messengers called neuropeptides also play a key role. One of the most important is calcitonin gene-related peptide (CGRP), which participates in pain signalling in migraine. Treatments that target CGRP is an important development in migraine treatment and management.
The condition also involves changes in how the brain processes sensory information. This explains why light, sounds or smells can become intolerable during an migraine attack, and why some patients experience nausea, dizziness or difficulty concentrating along with severe headache.
Not an isolated abnormality triggering every symptom, migraine involves interactive neurological and vascular processes whose contributions can vary between individuals and across different phases of an attack.
Symptoms May Begin Before The Headache
Also read: Saba Ali Khan Opens Up About Brain Tumour: Can It Go Unnoticed If You Walk, Talk And Work Normally?
Migraine attacks typically occurs through several phases mostly:
1. Prodrome: Hours or days before the pain
The earliest phase can involve fatigue, yawning, mood changes, food cravings, neck stiffness and difficulty concentrating. The involvement of brain regions linked with homeostasis, including the hypothalamus, may help explain why an approaching attack can affect sleep, appetite, mood and other bodily functions.
2. Aura: Temporary neurological symptoms
Some people experience an aura before or during the headache. This can include flashing lights, zigzag patterns, blind spots, tingling or temporary difficulties with speech. Aura is associated with a phenomenon called cortical spreading depression, a wave of changing electrical activity that moves across the brain’s cortex.
3. Headache: Pain and sensory sensitivity
During the headache phase, activation of the trigeminovascular system contributes to pain signalling. Patients may experience moderate-to-severe, often throbbing pain, alongside nausea, vomiting and sensitivity to light, sound or smells.
Movement can aggravate the pain, making routine activities difficult. The headache phase can last several hours to as long as 72 hours.
4. Postdrome: After the pain subsides
The end of an attack does not necessarily mean the attack is over. Some people experience exhaustion, dizziness, body aches and difficulty concentrating for hours or days afterwards. These phases can overlap, and their timing and severity differ from person to person.
The Lancet review also highlights the role of genetic and epigenetic factors that contribute to migraine risk. They interact with complex neurological networks, helping explain why some people experience occasional attacks while others develop frequent or chronic migraine.
Episodic migraine is characterised by fewer than 15 headache days per month. Chronic migraine involves headaches on at least 15 days per month for more than three months, including migraine features on at least eight days each month.
Breast Cancer: Know the Risks, Recognise the Signs & Get Checked
Credit: AI
Breast cancer is the most common cancer among women in India. According to various estimates, it accounts for about 26% of all cancers diagnosed among women, with nearly 2,00,000 new cases estimated in India each year.
Family history is not the only risk
Family history is an important risk factor, as some women inherit genetic changes that can increase their risk of developing breast cancer. Hereditary breast cancers can result from inherited genetic susceptibility, including mutations in high- or moderate-penetrance genes. BRCA1 and BRCA2 are among the best-known genes associated with hereditary breast cancer. Therefore, knowing family history is important.
But the absence of a family history does not mean that women are free from risk. In fact, around 80-85% of breast cancer cases occur in women with no known family history. These are generally referred to as sporadic cases.
The risk factors
Breast cancer risk factors can broadly be divided into those that cannot be changed and those that can potentially be modified.
Among the non-modifiable factors are age and certain reproductive and hormonal factors. Longer lifetime exposure to hormones such as oestrogen and progesterone can increase breast cancer risk. Early menstruation, later menopause and having a first pregnancy at a later age are some factors associated with longer hormonal exposure.
Potentially modifiable risk factors are largely lifestyle-related and include alcohol consumption, physical inactivity, excess body weight (particularly after menopause) and tobacco exposure. Maintaining a healthy weight, staying physically active, avoiding tobacco and limiting alcohol can help reduce the risk.
Also read: Amanda Peet’s Breast Cancer Wasn’t A Lump: What Was Her First Sign?
Five signs that should never be ignored
The five important warning signs include:
- A new, hard lump in the breast or armpit, particularly if it is increasing in size.
- A change in the size or shape of one breast, especially when it creates a new difference in breast symmetry.
- Unusual nipple discharge, particularly spontaneous discharge that is clear or bloody.
- Changes involving the nipple, such as a newly inverted nipple.
- Changes in the breast skin, including thickening, dimpling, puckering or a change in its appearance or texture.
These signs do not automatically mean cancer. But they should not be ignored.
Also read: Mammogram May Spot Hidden Heart Risk That Doctors Miss In Women
Get checked if you notice a change
If you notice any of these signs, particularly a new or persistent change in your breast, do not ignore it or try to diagnose it yourself. Seek medical evaluation promptly. A doctor will assess the breast and, if necessary, recommend what is known as a triple assessment: a clinical examination, breast imaging such as ultrasound or mammography, and tissue diagnosis when required. In selected cases, an MRI may also be recommended.
Tissue sampling may involve Fine Needle Aspiration Cytology or a core/true-cut biopsy. Together, these assessments help determine whether a breast abnormality is benign or malignant. It is important to distinguish this from screening. Screening is done in women who do not have symptoms, with the aim of detecting breast cancer at an early stage. When a woman has a symptom or notices a new breast change, she needs diagnostic evaluation rather than simply screening.
Don't panic: most breast lumps are benign
Finding a lump can understandably cause anxiety. However, most breast lumps, particularly in younger women, are benign. Common causes include fibroadenomas, breast cysts and fibrocystic changes.
Fibrocystic changes are often influenced by hormonal fluctuations. A lump may become more prominent or painful one to two weeks before menstruation and become smaller or less uncomfortable after the period. Some women may also experience a feeling of heaviness or tenderness in the breast.
An injury to the breast can also result in tissue damage and inflammation, producing a lump-like area. Therefore, a lump should not be assumed to be cancer, but neither should it be dismissed without appropriate evaluation.
Early detection can make a significant difference in the successful management of breast cancer. Women should remember that having no family history does not mean they are not at risk. At the same time, a breast lump or other change does not necessarily indicate cancer. The key is to know your own breasts, be aware of the warning signs and seek timely medical evaluation whenever a new or persistent change is noticed.
By Dr Megha B - Surgical Oncologist in Trichy - Breast, GI & Cancer Surgery Specialist, Kauvery Hospital
Attention Deficit May Be The Wrong Way To Understand ADHD, Says US Psychiatrist

Credit: iStock
ADHD may be less about an inability to pay attention and more about difficulties sustaining engagement with tasks, according to a US psychiatrist who has questioned whether the condition's name adequately captures its symptoms.
Attention-deficit/hyperactivity disorder (ADHD) is a neurodevelopmental condition that affects attention, executive function, impulse control, and activity levels. It typically begins in childhood, with symptoms appearing before age 12, and frequently persists into adulthood.
What Are The Symptoms Of ADHD?
According to the National Institute of Mental Health, ADHD symptoms fall into two primary categories:
Inattention: Difficulty sustaining focus, missing details, making careless mistakes, forgetfulness in daily routines, and struggling to stay organized.
Hyperactivity and impulsivity: Fidgeting, excessive talking, restlessness (including internal restlessness in adults), interrupting others, and acting without thinking.
However, Dr. Awais Aftab, a psychiatrist in Cleveland, Ohio, and clinical associate professor of psychiatry at Case Western Reserve University, has questioned whether the term “attention deficit” adequately captures the condition.
“The condition’s name notwithstanding, ‘attention deficit’ may be the wrong conceptual framing for ADHD,” he wrote in an article in The New York Times.
Also read: ADHD: Your Pupils May Explain How The Brain Handles Attention, Says New Indian Study
ADHD May Be More About Sustained Engagement
Aftab argued that ADHD may involve difficulties with the brain's ability to assign importance to a task and sustain the effort needed to complete it, rather than simply an inability to filter out distractions.
People with ADHD can often concentrate on activities that interest them. The difficulty may arise when they need to maintain attention and effort over time, particularly when tasks are repetitive or offer little immediate reward.
“If attention is about the mind homing in on what’s relevant in a given moment, engagement is about keeping that spotlight pointed at the same target over time,” Aftab wrote.
His argument offers a different way of thinking about some of the everyday challenges associated with ADHD, including starting tasks, staying organized, and following through on activities that require sustained mental effort.
What Do ADHD Medications Do?
ADHD is often treated with stimulant medications, such as Adderall, which can help reduce symptoms and improve attention and impulse control.
Aftab argued that the effects of these medications may extend beyond attention itself.
“Stimulants create what looks like improved attention and focus, but they really do so by enhancing the salience of mundane activities – tricking the brain into assigning greater worth and significance to things like math homework and laundry,” he said.
Citing a study published in Cell that examined the effects of stimulants on the brain, Aftab suggested that the medications' effects on brain networks could support a broader understanding of ADHD. However, findings about how stimulants affect the brain do not, by themselves, establish that ADHD is primarily a problem of motivation or task engagement rather than attention.
Aftab also suggested that some patients may rely on medication to keep up with lifestyles that are not suited to their needs. This raises broader questions about how treatment, daily demands, and individual needs intersect, rather than suggesting that medication is unnecessary.
He also emphasized evidence linking ADHD medication use with lower risks of adverse outcomes, including death, self-harm, transport accidents, criminality, and addiction-related problems.
- Follow Us :


© $2026 Times Horizon Private Limited