
- Health Conditions A-Z
- Health & Wellness
- Nutrition
- Fitness
- Health News
- Ayurveda
- Videos
- Medicine A-Z
- Parenting
Woman Left Screaming In Pain After Sex Toy 'Pulled Through Body' During MRI Scan
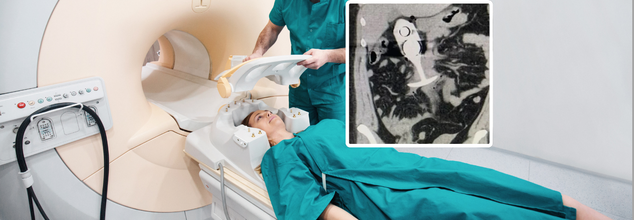
MRI scans are strong diagnostics with high-definition images of what lies inside a body. Strong magnetic fields require precaution, as brought out by an instance where a young woman suffered very serious injuries due to an oversight in a metallic core within a silicone sex toy that she happened to have before the MRI scan. This makes a stark reminder about the potentially deadly consequences of missing metal objects when such procedures are being performed. In April 2023, a 23-year-old woman went into an MRI with a silicone plug containing a metal core that was not known.
She thought that the item is made entirely out of silicone according to the advertising. However, the strong magnetic field of the MRI machine interacted with the hidden metal, dragging the object through her body and causing excruciating pain. According to reports from the U.S. Food and Drug Administration (FDA), the scene was harrowing, with the woman screaming in agony and requiring immediate hospitalization. Despite pre-scan screenings, which are routine prior to a scan, the patient did not inform the facility that the object existed because he presumed it was purely non-metallic. This caused serious injuries that led to the patient's law suit against the manufacturer for deceitful misrepresentations of material content.
MRI machines employ magnets between 0.5 to 3 Tesla (T). This is thousands of times stronger than the Earth's magnetic field. The tremendous force causes ferromagnetic materials, like iron and nickel, to be magnetized quickly and become strongly attracted toward the magnet. Objects as small as hairpins or paper clips will accelerate at 40 miles per hour inside the magnetic field.
The force can lead to catastrophic injuries in items lodged within the body, such as metallic implants or foreign objects. Metallic cores within devices, like pacemakers or intrauterine devices, must be disclosed to radiologists to prevent such complications.
How Metal Objects Interact with MRI Fields?
On these claims, Dr. Adam Taylor, a specialist in human anatomy, weighed his words in a international health website and added that the distance away and mass of this object would increase its velocity towards that of sound, "The acceleration would be phenomenal, but with a metallic core, it can't go anywhere near supersonic speeds. As for the size, the magnetic acceleration to the internal soft tissues would ensure that there could be severe intracranial trauma."
The injuries inflicted in this case likely involved damage to major blood vessels, nerves, or organs, highlighting the devastating impact of even minor oversight during an MRI scan.
This is not an isolated case. There are documented cases of metallic objects causing serious damage during MRI scans with a 65-year-old man with schizophrenia swallowed metal objects, including sockets and a hinge pin. The powerful magnetic field during an MRI scan caused the objects to rupture his stomach, resulting in serious injuries.
A toddler who ingested 11 small magnets perforated his bowel while undergoing a scan, making his case unique. In another deadly but extremely rare incident, there have been people who hide a firearm on themselves during MRI procedures. Magnetic attraction can trigger a discharge in a weapon and has led to some fatal injuries.
These cases emphasize the very strong need for adequate screening and patient education prior to an MRI.
Preventing MRI-Related Incidents
Medical professionals have been trained to avoid risks. This is by properly screening a patient for metallic objects. In general, most pre-scan protocols include:
- Patients are interrogated about implants, recent surgery or exposures at work related to metals.
- Radiologists sometimes use handheld metal detectors to search for hidden items.
- People who work with metal, like welders or machinists, will need additional testing to detect microscopic metal fragments within soft tissues or eyes.
The case emphasizes the importance of product labeling by manufacturers, especially those products that are likely to unintentionally cause harm to health. The patient's assumption that her device was 100% silicone points to a larger problem in consumer markets with misinformation.
It also reminds the patients to report any possible dangers to the medical professionals, no matter how the objects look non-metallic. In sensitive cases, patients can request private discussions with healthcare providers to ensure safety without discomfort.
In the end, it is a joint effort from manufacturers, healthcare professionals, and patients that can prevent such tragedies. Manufacturers must ensure truthful marketing, while healthcare providers should educate patients about the dangers of metal objects in MRI settings. For patients, understanding the risks and actively participating in pre-scan disclosures can be lifesaving.
This young woman's experience is a sobering example of the unforeseen dangers posed by MRI machines when precautions are overlooked. It serves as a wake-up call to address gaps in patient awareness, medical protocols, and product transparency. By learning from this incident, the medical community and the public can work together to ensure MRI scans remain a safe and effective diagnostic tool.
New Chinese Weight-Loss Injection Ribupatide Shows Over 17% Weight Loss In 48 Weeks: Could It Rival Mounjaro?
Credit: AI-generated image
An experimental weight loss injection developed in China has produced an average weight reduction of 17.7% over 48 weeks in adults who are overweight or obese, raising the possibility of another contender entering in the rapidly expanding obesity drug market.
The drug, called ribupatide, was evaluated in a Phase 3 clinical trial published in JAMA recently. Researchers found that participants receiving the highest dose lost nearly one-fifth of their starting body weight in 11 months.
How Much Weight Did Participants Lose?
The randomised trial involved 567 adults with overweight or obesity across 55 medical centres in China. Participants did not have diabetes and their average age was 34 years.
Researchers randomly assigned them to receive once-weekly injections of ribupatide at doses of 2 mg, 4 mg or 6 mg, or a placebo. All participants also received lifestyle counselling. After 48 weeks, the average weight reduction was:
- 2 mg dose: 10.7%
- 4 mg dose: 16.4%
- 6 mg dose: 17.7%
- Placebo: 1.4%
The researchers also examined how many participants lost at least 5% of their starting weight. This threshold was achieved by 68.1% of those receiving 2 mg, 88% in the 4 mg group and 85.7% in the 6 mg group, compared with 16% of participants receiving placebo.
Notably, weight loss had not clearly plateaued in the two higher-dose groups by the end of the study. This suggests that a longer treatment period may reveal further reductions.
More About Ribupatide
Ribupatide, also known as HRS9531, is a dual-acting injectable medication that targets the GLP-1 and GIP hormones. These gut hormones help regulate appetite, digestion and blood glucose levels. By activating their receptors, the drug helps reduce hunger and increase feelings of fullness, helping people consume fewer calories.
This is similar to that of tirzepatide, the active ingredient in Eli Lilly's Mounjaro and Zepbound. Both medicines target GLP-1 and GIP receptors.
Could Ribupatide Rival Mounjaro?
The trial results have drawn comparisons with existing weight loss drugs like Mounjaro and Wegovy. However, the comparisons need to be interpreted carefully.
In the SURMOUNT-1 trial, tirzepatide produced average weight loss of up to 20.9% after 72 weeks in adults with obesity or overweight without diabetes. Semaglutide 2.4 mg, marketed as Wegovy, produced an average reduction of 14.9% after 68 weeks in the STEP 1 trial.
Ribupatide's highest-dose group recorded 17.7% weight loss after 48 weeks. But these results come from separate clinical trials. A direct comparison would be needed to determine how ribupatide performs against tirzepatide or semaglutide.
Side Effects Of Ribupatide
Digestive problems were the most frequently reported side effectsin the ribupatide trial. Gastrointestinal side effects occurred in 47.9% of participants receiving the 2 mg dose, 58.2% in the 4 mg group and 63.1% in the 6 mg group. This compared to 23.1% of those receiving placebo.
Reported problems included nausea, vomiting and diarrhoea. Most were mild or moderate according to the findings.
The study had its limitations as the participants were relatively young, which means the findings may not apply equally to older adults. Additionally, the 48-week treatment period may not have captured the full effects of the higher doses. The study's smaller body-composition assessment also did not measure muscle strength.
Ribupatide is an investigational treatment and is not yet an approved weight-loss medication for routine use.
US Loses Measles Elimination Status After 26 Years: What Does It Mean?
Credit: AI-generated image
The United States has lost its measles elimination status after more than a year of sustained transmission, marking a major setback for a public health achievement the country obtained in 2000.
The decision by the Pan American Health Organization (PAHO) comes after a sharp rise in infections as the US reported more than 5,400 measles cases in 2026. PAHO is expected to formally announce the decision on November 17.
According to the US Centers for Disease Control and Prevention (CDC), the country had recorded 5,412 cases as of November 15, resulting in more than 590 hospitalisations and at least six deaths. Some states have reported additional fatalities. Cases have been confirmed in 45 states and Washington, DC.
The United States had maintained its measles elimination status for more than 25 years. However, outbreaks that began in 2025 continued spreading into 2026. Approximately one-third of this year's cases were linked to those ongoing outbreaks.
What Does Losing Measles Elimination Status Mean?
Measles elimination does not mean a country has no cases of the disease. It means that local transmission has been interrupted and that occasional outbreaks do not lead to sustained community spread.
Under the World Health Organization's definition, a country loses elimination status when it cannot stop continuous local transmission for at least 12 months.
The United States first achieved measles elimination status in 2000, after decades of vaccination efforts dramatically reduced infections. Imported cases and smaller outbreaks still occurred, but public-health measures and vaccination coverage helped contain them.
The current situation is different because the virus has continued circulating through communities for more than a year, creating ongoing chains of transmission.
CBS News medical correspondent Dr Céline Gounder explained the implications, "It means that we're at risk of being exposed to measles and getting measles if we're not vaccinated," Gounder said. "It means ERs and pediatricians need to consider measles in anyone with a fever and rash, whether they've traveled overseas or not. And we may now become an exporter of measles to other countries."
Measles Cases Are Rising In The US
Also read: US Measles Cases Cross 5,000 For First Time Since 1991; Country Risks Losing Elimination Status
Declining childhood vaccination coverage has left more communities vulnerable to outbreaks. Measles is among the most contagious infectious diseases, and the virus can spread rapidly when it enters populations with gaps in immunity.
According to CDC data, 96% of people infected in 2026 were either unvaccinated or had an unknown vaccination status. Only 2% of reported cases were among people who were fully vaccinated.
The country recorded 2,242 cases in 2025, its highest annual total in more than three decades at the time. The number has more than doubled in 2026.
Pennsylvania has reported the largest outbreak, with more than 1,500 cases and seven deaths this year. Wisconsin has reported two child deaths, while New York recorded its first measles death in more than 30 years.
How Can US Regain Measles Elimination Status?
People who have not received the measles vaccine are at the greatest risk of infection. However, infants who are too young to be vaccinated, pregnant women and people with weakened immune systems are the most vulnerable.
Measles can cause complications like pneumonia and encephalitis or inflammation of the brain. In some cases, it can lead to permanent neurological complications, hearing loss and death.
Children who have not received the recommended doses of the measles, mumps and rubella (MMR) vaccine are especially vulnerable.
The CDC recommends two doses of the MMR vaccine. According to the public health experts, two doses are approximately 97% effective against measles.
Losing elimination status does not mean the country cannot regain it. However, sustained efforts to interrupt transmission will be necessary.
PAHO recommends maintaining measles vaccination coverage of at least 95%, alongside strong disease surveillance, laboratory testing and rapid outbreak response. Dr Omer Awan, an epidemiologist and public health contributor for Forbes, explained the importance of vaccination.
"It's frustrating and heartbreaking ... because we have the tools to fight this. The tool is the MMR vaccine, which we know is 97% effective at preventing the onset of measles," Awan said.
Lilly's Obesity Drugs: Foundayo Becomes First GLP-1 Pill Approved In China, Experimental Combo Shows Promise
Credit: AI-generated image
Eli Lilly is rapidly expanding its presence in the global obesity treatment market. Its oral weight-loss drug Foundayo has received approval in China, becoming the first GLP-1 pill to get approved in the country.
In another development, its experimental drug combination of eloralintide and tirzepatide recently reported substantial weight loss in an early-stage clinical trial.
The developments come as pharmaceutical companies compete to develop more convenient treatments for obesity, including oral alternatives to injections and dual and triple-acting medicines.
Foundayo Weight Loss Pill Gets Approval In China
RecnChina approved orforglipron, marketed as Foundayo in the US, making it the first GLP-1 medication in pill form approved for weight management in the country. Until now, Chinese regulators had authorised GLP-1 medicines for obesity treatment only as injections.
The approval gives Lilly an early advantage over its rival Novo Nordisk, which has also applied to market its oral Wegovy treatment in China.
Foundayo contains orforglipron, an oral, small-molecule GLP-1 receptor agonist. GLP-1 medicines mimic the action of a naturally occurring gut hormone involved in appetite regulation and blood sugar control.
Unlike injectables like Wegovy and Zepbound, Foundayo is taken once daily as a tablet. It can also be taken without restrictions on food and water intake, which may make it a more convenient option for people who prefer not to use injections.
In separate clinical trials, Foundayo produced an average weight reduction of approximately 11% over 72 weeks, while oral Wegovy achieved around 14% over 64 weeks. These results come from different studies.
Experimental Combination EloraTZP Shows Up To 23.3% Weight Loss
Also read: Stopping Mounjaro & Zepbound May Trigger Hallucinations, Mania & Other Psychiatric Symptoms
In another development announced on November 14, Lilly reported promising Phase 2 results for EloraTZP, an experimental combination of eloralintide and tirzepatide.
The combination brings together two medicines that act on appetite and metabolism differently. Tirzepatide, the active ingredient in Zepbound, activates GIP and GLP-1 receptors. Eloralintide is an investigational drug that acts on amylin receptors, which are involved in regulating appetite and feelings of fullness.
In adults with obesity and type 2 diabetes, participants receiving EloraTZP achieved weight loss of up to an average of 23.3% after 48 weeks. Their average starting weight was 232.4 pounds (approximately 105.4 kg). Up to 60% of participants no longer met the BMI criteria for obesity at the end of the study.
The combination also reduced the average blood glucose levels over approximately three months, by up to 2.9 percentage points. Up to 77% of participants achieved normal blood sugar levels, according to Lilly.
However, these are Phase 2 findings reported by Lilly, and the full trial results have not yet been published. Larger studies will be needed to establish the combination's safety and effectiveness in obesity treatment.
More Updates From Lilly
Lilly's latest update included findings from its Phase 3 SURMOUNT-ADOLESCENTS trials, which evaluated Zepbound in adolescents aged 12 to under 18 with obesity.
Participants experienced an average BMI reduction of 21.4% after 72 weeks. More than half no longer met the BMI criteria for obesity. They also reported improvements in aspects of quality of life due to weight reduction, including physical comfort and better body image.
Separately, the company reported Phase 3 findings for retatrutide, an experimental once-weekly medicine that activates three hormone receptors: GIP, GLP-1 and glucagon.
In trials involving adults with obesity, it reduced the severity of obstructive sleep apnoea and knee osteoarthritis pain. Retatrutide, an investigational drug, is not approved for general medical use.
- Follow Us :


© $2026 Times Horizon Private Limited