
- Health Conditions A-Z
- Health & Wellness
- Nutrition
- Fitness
- Health News
- Ayurveda
- Videos
- Medicine A-Z
- Parenting
'We Have The Means To Prevent 80% Heart Attacks And Strokes', Expert Urges NHS To Give 'Polypill'
Image Credits: Canva
Heart attacks and strokes are among the leading causes of death globally, with millions suffering from cardiovascular diseases (CVD) every year. There are more than seven million people in the UK alone, with about 100,000 patients experiencing heart attacks annually. However, a group of researchers at University College London (UCL) estimate that one 'polypill' taken daily day could eliminate a majority of these cases dramatically lowering death tolls.
The proposed polypill, a combination of a statin and three blood pressure-lowering drugs, has been under study for over two decades. Experts argue that introducing this pill universally for individuals aged 50 and above could be more effective than the current NHS Health Check, which assesses risk factors every five years for those aged between 40 and 74.
Studies have repeatedly proven the effectiveness of the polypill in preventing CVD. A groundbreaking 2019 study in The Lancet found that five years' use of the polypill cut the risk of heart attack and stroke by a third. In addition, previous modelling analyses have estimated that if given universally to people over 55, the polypill might be able to prevent 80% of heart attacks and strokes.
Today, the NHS Health Check follows a risk-based model in which patients are tested for CVD risk factors and treated with drugs accordingly. Yet, as per UCL's study, this system has serious flaws:
Low Uptake: Just 40% of those eligible for the NHS Health Check choose to have it, leaving a considerable number of at-risk patients undiagnosed and untreated.
Ineffective Prediction of Risk: The majority of heart attacks and strokes happen to people at average risk levels, thus making it challenging to identify the need for intervention effectively.
Limited Effectiveness: Even at maximum take-up, the NHS Health Check programme is predicted to have fewer health impacts compared to a polypill initiative applied to the whole population.
Simplicity and Affordability of the Polypill Strategy
One of the big benefits of the polypill is that it is so easy. In contrast to the existing screening-based model, the polypill scheme would not involve complicated medical tests or lengthy risk assessments. Instead, people reaching 50 would just have to fill out a few questions to determine possible side effects before they were prescribed.
Professor Aroon Hingorani of the UCL Institute of Cardiovascular Science, one of the strongest proponents of this scheme, says:
"Finally, the time is now to do much better on prevention. A population approach would prevent a lot more heart attacks and strokes than is done today with a strategy of trying to target a smaller group only."
Aside from the possible health implications, the polypill is also an economic solution. The drugs used are off-patent, thus cheap to produce and distribute. With the vast economic cost of managing CVD-related illnesses, a preventive model could result in substantial cost-saving for the NHS in the future.
The polypill has been proven to be effective by numerous international trials. In 2019, a randomised trial in rural Iran discovered that participants who took the polypill for five years had a 34% reduced risk of having a heart attack or stroke compared to non-participants.
Likewise, modelling research has indicated that even if only 8% of people aged over 50 took up the polypill regimen, it would still be more beneficial to their health than the NHS Health Check programme.
Is This a Case of Over-Medicalisation?
One of the main objections to the polypill strategy is the suggestion that it might result in the unnecessary medicalisation of a significant proportion of the population. But, it is argued, it should be considered as a preventative measure, not as mass medication.
Professor Sir Nicholas Wald of UCL's Institute of Health Informatics explains:
"Instead of being a 'medicalisation' of a significant proportion of the population, a polypill programme is a prevention measure to prevent an individual from becoming a patient."
He compares it with public health measures like water fluoridation or compulsory seatbelts—interventions that have been shown to have a significant impact in reducing public health danger at low individual cost.
With the evidence in favour of the polypill's effectiveness and viability overwhelming, experts are calling on the NHS to act now. It is their belief that substituting the NHS Health Check with a polypill-based prevention program could be the UK government's flagship policy under its pledge to put disease prevention ahead of cure.
As Professor Hingorani points out, "The status quo is not a justifiable option." With CVD still a major cause of death globally, taking a population-wide polypill approach could be a turning point for preventative medicine, potentially saving thousands of lives annually. The question now is whether the NHS will take up this call and establish a policy with the potential to transform the prevention of cardiovascular disease on a national level.
Mississippi Student Deaths Put Kratom Under Scrutiny: How Dangerous Is It?

Credit: iStock
The deaths of two University of Mississippi students whose toxicology reports reportedly detected synthetic kratom-related substances have renewed concerns about the gas-station supplement and calls for a nationwide ban.
Kratom is banned in at least eight US states: Alabama, Arkansas, Connecticut, Indiana, Louisiana, Tennessee, Vermont and Wisconsin. Several others, including Iowa and Idaho, are considering restrictions.
What Happened In Mississippi?
Aidan Hamilton, 18, and Robert Strang, 20, died in separate incidents on September 21. Investigators found packaging associated with kratom-related products, including SMAX Pseudo-DHM, at both locations, according to court documents.
A defense attorney for one of two men accused of selling narcotics connected to at least one death told a Mississippi federal court that one student died from the combined effects of multiple substances, including cough syrup, while the other died from inhalation asphyxiation, Action News 5 reported.
Court records reportedly showed that both students had mitragynine pseudoindoxyl, MGM-15 and 7-hydroxymitragynine (7-OH) in their systems. However, the presence of these substances alone does not establish that they caused the deaths.
Kratom Use And Related Health Concerns Are Growing
Kratom comes from the leaves of the Mitragyna speciosa tree, native to Southeast Asia. Traditionally used for its stimulant and pain-relieving effects, it is now sold in the US as powders, capsules, teas and extracts.
US poison centers recorded 3,434 kratom exposure reports in 2025, up from 258 in 2015, according to CDC data.
Legislative efforts to restrict kratom have also intensified. An analysis by The Washington Post found that, among roughly 400 related bills considered across states, 108 proposed bans on kratom or related synthetic chemicals, while 258 focused on measures such as age limits, licensing and potency restrictions.
Can Kratom Be Addictive?
Kratom contains alkaloids, primarily mitragynine. At lower doses, it can increase alertness and energy; at higher doses, it can produce sedative and opioid-like effects by interacting with opioid receptors in the brain.
Regular use can lead to physical dependence. Withdrawal symptoms may include irritability, restlessness, muscle aches, fatigue and sweating.
The US Food and Drug Administration (FDA) says evidence suggests that some people develop substance use disorder after using kratom, although its potential for abuse has not been fully characterized in well-designed human studies.
Why Are Concentrated 7-OH Products Concerning?
7-hydroxymitragynine, or 7-OH, occurs naturally in trace amounts in kratom leaf. Some commercial products contain concentrated levels and are sold as tablets, gummies and drink shots.
The FDA has warned that these products have not been demonstrated to be safe or effective for any medical use. The American College of Medical Toxicology has highlighted concerns about opioid-like intoxication, respiratory depression, dependence and withdrawal.
Kratom-Related Hospitalizations Are Rising
According to a University of Virginia study, hospitalizations linked solely to kratom rose from 43 in 2015 to 538 in 2025.
Poison centers recorded 901 exposures involving 7-OH between January and June 2026, compared with 593 during all of 2025.
Although these figures highlight growing concerns, they do not establish that concentrated 7-OH products caused the increase in kratom-related hospitalizations.
Kratom is not an FDA-approved treatment for pain, opioid withdrawal or any other medical condition. Its long-term health effects remain incompletely understood.
China Issues Plague Risk Alert After Suspected Death In Russia: Which Countries Are On Guard?

Credit: AFP
China has issued a plague-risk alert following the suspected plague-related death of a 28-year-old researcher at a laboratory in Irkutsk, Siberia. However, Russia maintains that no plague outbreak has occurred.
According to state-run newspaper Global Times, the Hulunbuir Center for Disease Control and Prevention (CDC) in China's Inner Mongolia Autonomous Region issued a plague-prevention notice on Sunday. Hulunbuir shares a border with Russia.
The advisory cited international attention surrounding the Russian case and the region's history of natural plague activity, while noting that the cause of the researcher's death has not been officially confirmed.
The Hulunbuir CDC said the city last recorded human plague cases in 1927. Routine surveillance in recent years has also detected no plague outbreaks among local rodent populations. Based on its risk assessment, the likelihood of a local outbreak remains low.
What Did Hulunbuir CDC Advise?
Also read: The Black Death Bacterium Still Exists: From Medieval Europe To Modern-Day Outbreaks
The authority advised people arriving from plague-endemic areas in Russia's Far East to monitor their health and seek prompt medical attention if they develop suspected symptoms. Travelers should disclose their travel history to facilitate diagnosis and treatment.
Residents were also urged to follow preventive measures, including routine health monitoring, environmental disinfection and prompt reporting of suspected symptoms.
Earlier, Hunan province, which does not border Russia, also released recommendations on plague symptoms and prevention.
What Happened In Russia?
Darya Shipilova, a 28-year-old researcher at the Anti-Plague Research Institute in Irkutsk, was hospitalized with severe pneumonia on September 29 and died on October 2, according to media reports.
Reports raised concerns about possible pneumonic plague, caused by Yersinia pestis. However, Russian authorities have said that tests did not detect plague or other dangerous pathogens.
On October 8, regional governor Igor Kobzev said quarantine measures and medical monitoring of contacts had been completed. Nearly 5,000 laboratory tests had found no dangerous pathogenic microorganisms, according to reports.
What Has The WHO Said?
Read More: Russia Plague Scare: WHO Reiterates Biosafety Rules Despite No Confirmed Lab Accident
The World Health Organization (WHO) said in a Disease Outbreak News update published on October 10 that the overall public health risk remained low, based on the information available.
The agency found no evidence of ongoing transmission of pneumonic plague linked to the incident. However, the cause of the researcher's fatal pneumonia remains unexplained.
The WHO noted that the absence of a confirmed diagnosis remained a key uncertainty. Given the researcher's employment at an institution handling high-risk pathogens, the agency said a laboratory-associated exposure could not be fully excluded.
Which Other Countries Are Taking Precautions?
Several countries have reportedly strengthened border surveillance and public-health precautions following the Russian case.
Kazakhstan, Kyrgyzstan, Tajikistan and Uzbekistan have announced measures to prevent the potential introduction of highly dangerous infectious diseases, according to regional reports and official statements.
Kyrgyzstan's Health Ministry said border checkpoints had been placed on heightened alert. Sanitary and epidemiological surveillance covers people, vehicles and cargo crossing the country's borders to prevent the entry and spread of infectious diseases.
Uzbekistan's Sanitary-Epidemiological Committee also announced enhanced preparedness among relevant services to prevent the entry and spread of highly dangerous infectious diseases.
READ: Russia Plague Scare: Could It Trigger A New Pandemic? Experts Explain
European Union And United States
The European Centre for Disease Prevention and Control (ECDC) is monitoring the situation. According to its assessment, the limited information available indicates no reported secondary cases and no evidence of sustained human-to-human transmission that could drive further spread.
US officials are also monitoring the case. CDC Director Erica Schwartz said the agency was prepared to monitor and screen travelers.
Secretary of State Marco Rubio said Washington was watching reports of possible plague but that the situation was not a “cause for alarm.”
“We're watching and monitoring it closely. I don't think it's cause for alarm – but it is cause for focus and a cause to just keep an eye on it. And we're doing that,” Rubio said.
'Humanity Can Still Act': Lancet Warns Of 17 Global Health Threats By 2100

Credit: iStock
Climate change, antimicrobial resistance (AMR) and obesity are among 17 threats that could cause massive losses of healthy life by 2100, according to a new report by The Lancet Commission on 21st Century Global Threats to Health.
Launched at the World Health Summit 2026 in Berlin, the report draws on risk analysis across 204 countries and territories to identify threats that could have catastrophic consequences for global health.
“Humanity still has the agency to act,” said Commission co-chair Professor Christopher JL Murray, director of the Institute for Health Metrics and Evaluation (IHME) at the University of Washington, warning that delays would increase future costs.
What Are The 17 Global Health Threats?
Also read: Over 2 Hours of Daily Screen Time Linked to Depression, Obesity In Young People: Lancet
The Commission classified a threat as catastrophic if it could account for at least one billion disability-adjusted life years (DALYs) by 2100, could be modelled using available data and offered scope for policy intervention.
DALYs measure healthy years lost to illness, disability or premature death.
The 17 threats are:
- Obesity
- Low educational attainment
- Income inequality
- Malicious use of artificial intelligence (AI)
- Nuclear conflict
- Poor mental health
- Unhealthy ageing
- Smoking
- Conventional conflict
- High blood pressure
- Antimicrobial resistance
- High alcohol use
- Pandemics
- Climate change
- Air pollution
- Collapse of development assistance for health
- Childhood malnutrition
These estimates reflect potential health losses that interventions could avert, not the urgency or priority of each threat. Risks with lower estimated burdens may still require urgent action because of their potential consequences.
“The estimates highlight how much health loss could be avoided in each area,” Murray said, noting that the threats are interconnected and must be addressed together rather than in isolation.
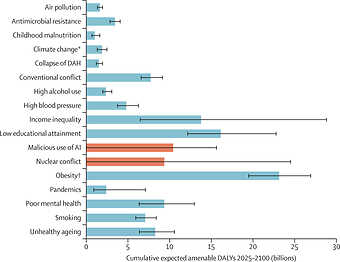
Obesity Could Cost 23.1 Billion Healthy Life-Years
Obesity represents the largest estimated burden of potentially avoidable health loss among the 17 threats, with 23.1 billion DALYs projected between 2025 and 2100 under the Commission's assessment.
The obesity risks linked high body mass index, poor diet and physical inactivity.
Other estimates include 16.1 billion DALYs associated with low educational attainment, 13.8 billion with income inequality, 10.4 billion with malicious use of AI and 9.4 billion with nuclear conflict.
Climate Change Could Cost Billions Of Healthy Life-Years
Limiting global warming to around 1.8°C, rather than allowing it to reach 4.4°C, could prevent an estimated 1.89 billion healthy life-years from being lost to causes including extreme heat and air pollution.
The estimate excludes some harder-to-measure impacts, such as displacement, drought, economic disruption and mental health problems, meaning the overall burden could be greater. Without substantial emissions cuts, climate-related health losses could accumulate beyond 2100 and worsen other global health threats.
“This Lancet Commission offers a radical conceptual shift in the way we think about future threats to human survival,” said Dr Richard Horton, editor-in-chief of The Lancet, calling for coordinated action across sectors.
The Commission's Call To Action
The Commission calls for sustained investment, stronger preparedness and regular risk monitoring. It urges governments and other stakeholders to coordinate action across sectors to reduce preventable health losses.
The report brings together 35 commissioners from health, economics, security, governance and technology to assess threats to global health over 2025–2100.
- Follow Us :


© $2026 Times Horizon Private Limited