
- Health Conditions A-Z
- Health & Wellness
- Nutrition
- Fitness
- Health News
- Ayurveda
- Videos
- Medicine A-Z
- Parenting
Ministry Issues Warning Against 'Very High' UV Index In Canary Island, Know Why It Matters

Credits: Canva
When the sun is out after a long winter, every one loves it. But not the people of Canary Islands. Tourists there are being warned about the "unusually high risk" of UV rays this week. The Ministry of Health for this holiday destination has urged both, residents and visitors to take extra precautions and preventative measures to limit the impact of sun exposure over their body and skin.
The Ministry observed Aemet, Spain's national weather agency for the forecast which showed higher than normal UV or ultraviolet radiation levels in the region. It is in this backdrop that everyone in the region are requested to be extra careful when they are out in the sun. UV levels are set to reach 7, which is a 'high risk' in La Palma, El Hierro, La Gomera and Gran Canaria. Other regions like Tenerife, Fuerteventura and Lanzarote are expected to reach a level 6, which is also classed as 'high risk'.
UV Index Explained
As per the World Health Organization (WHO), a UV index is a measure of the level of UV radiation, which ranges from zero upward. The higher the UVI, the greater potential for damage to skin and eye and the less time it takes for harm to occur, notes WHO.
The range 1 to 2 represents a low risk, 2 to 5 is moderate, 6 to 7 is at high risk, 8 to 10 is at very high and anything over 11 is extremely risky for anyone to stay out.
UV radiation levels fluctuate throughout the day, with the highest values occurring during the four-hour period around solar noon. The reported UV Index (UVI) typically reflects this daily peak. Depending on geographic location and the use of daylight saving time, solar noon falls between 12 p.m. and 2 p.m. In some countries, sun protection advisories are issued when UV levels are expected to reach 3 or higher, as exposure at these levels increases the risk of skin damage, making protective measures essential.
What happens to you when you are out in sun for too long?
While sun bathing is good, being out in the sun when the UVI indicates a high or very high risk, may cause you health concerns. It can lead to sunburn, premature skin aging, incresed risk of skin cancer, eye damage and in severe cases, heat related disease.
Sunburn
It is one of the most common skin injury which happens when there is excess exposure to UV radiation from the sun. This happens when the UV radiation directly damages the DNA skin cells. These damaged cells die and shed, this is why people experience peeling after getting a sunburn.
Dehydration
This is also a common occurrence when your body loses too many fluids or electrolytes. It can also interfere with your normal body functions. You may feel dehydrated, especially when you are out in the sun, but not well hydrated. The most common symptoms are dizziness, fatigue and headache on hot days.
Hyponatremia
This is an electrolyte disorder in which your body experiences low sodium in blood. The symptoms could lead to nausea, confusion and even weakness. There are extreme cases when one may have seizures, slip into coma or die.
Heat Exhaustion
This is one of the most common consequence of being out under the hot sun. Dehydration with prolonged heat exposure can lead to heat exhaustion.
Heatstroke
When you are out under the sun and your body's core temperature cross 104°, heatstroke may occur. This is also known as sunstroke. As per the Centers for Disease Control and Prevention (CDC), it causes more than 600 deaths each year in the United States.
Russia Plague Scare: What Black Death and Anthrax Outbreaks Teach Us About Lab Safety
Credit: iStock/X
The suspected pneumonic plague case in Russia has revived memories of the Black Death and the 1979 Sverdlovsk anthrax outbreak.
While Russia has denied any plague outbreak, the death of a young laboratory worker and reports of nearly 200 people being placed under medical observation have raised questions about laboratory safety and what may have happened.
Moscow told the World Health Organization (WHO) that no plague cases have been detected in Irkutsk and that the deceased woman’s contacts tested negative for dangerous pathogens. COVID-19 and rhinovirus were detected in some people under observation.
Russia Says No Plague Cases Detected
Russian authorities told the WHO that there was “no case of this dangerous disease” in Irkutsk, WHO spokesperson Christian Lindmeier said at a Geneva briefing.
Russia also said contacts of the deceased tested negative for dangerous infectious pathogens.
The circumstances of the death have nevertheless raised questions about laboratory safety and possible pathogen exposure.
Also read: Russia Plague Scare: Could It Trigger A New Pandemic? Experts Explain
From Black Death to Pneumonic Plague
The Black Death swept across Eurasia and North Africa between 1346 and 1353, killing an estimated 30% to 60% of Europe’s population.
It was caused by Yersinia pestis, the same bacterium responsible for plague today. The pandemic was primarily associated with bubonic plague, although pneumonic plague also occurred.
Bubonic plague is mainly spread through infected flea bites, while pneumonic plague affects the lungs and can spread between people through respiratory droplets during close contact. Modern antibiotics can treat plague, particularly when given early.
The 1979 Sverdlovsk Anthrax Outbreak
The circumstances surrounding the Russian lab worker’s death have also revived memories of the anthrax outbreak in Sverdlovsk, then part of the Soviet Union, in April and May 1979.
Soviet authorities initially blamed contaminated meat, while US officials attributed the outbreak to anthrax spores accidentally released from a military microbiology facility.
The distribution of human and animal cases along a path extending from the facility was consistent with an airborne release.
The incident remains an important example of the consequences of an accidental biological-agent release.
Why Has the Russia Case Raised Questions?
Read More: Russia Plague Scare: Is Pneumonic Plague Deadlier Than Bubonic & Septicemic Plague?
The cause of the laboratory worker’s death and the circumstances of any possible exposure remain unclear.
The reported quarantine of nearly 200 people has also raised questions about the scale of the response.
Dr. Ashish Jha, former dean of Brown University’s School of Public Health, said the case had raised several “red flags.”
He questioned whether a laboratory worker handling plague would have been vaccinated or received antibiotics promptly after a suspected exposure, and why so many people were placed under quarantine.
Jha also pointed to Russia’s history of biological weapons research and expressed concern about the lack of information from Russian authorities.
There is currently no evidence, however, that the death was linked to a biological weapons programme or that a laboratory leak occurred.
How Safe Are Plague Laboratories?
Javier Pizarro-Cerda, head of the Yersinia Research Unit at the Institut Pasteur in Paris, told CNBC that he was “very surprised” by the reported death because laboratories handling plague generally use strict protective measures.
“You work with a full body suit. You work with masks. You work with gloves. So even if you break a tube, normally you should be protected,” he said.
Pizarro-Cerda also said Russia has a plague vaccine, although he described its protection as low and transient compared with standards elsewhere.
What Could Confirm Plague?
Pizarro-Cerda said plague testing can be performed rapidly and that an autopsy should provide evidence if the woman had pulmonary plague.
The laboratory worker reportedly died on October 2, giving authorities several days to conduct diagnostic tests.
Still, there is no confirmation that pneumonic plague caused her death or that a laboratory accident occurred.
Key questions remain whether Yersinia pestis was detected, whether there was evidence of laboratory exposure, and whether genetic testing can establish the source of any infection.
Cladophialophora bantiana: US CDC Flags Surge In Deadly Brain Fungus Cases
Credit: Wikimedia/iStock
A deadly fungal infection that can cause brain abscesses has shown a sharp increase in detections in the US, according to a new report from the US Centers for Disease Control and Prevention (CDC).
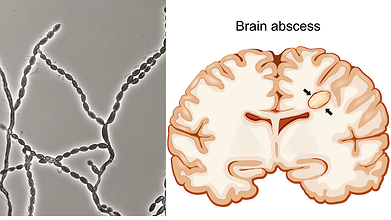
The CDC’s latest Morbidity and Mortality Weekly Report flagged a substantial rise in detections of Cladophialophora bantiana, a neurotropic fungus associated with a 60%–70% case-fatality rate, even with aggressive treatment. The fungus can also infect people without known immune problems.
How Were the Cases Detected?
A clinical reference laboratory at the University of Washington identified 48 confirmed cases and one probable case of C. bantiana infection from January 2009 through July 2026.
Annual case counts ranged from one to five between 2009 and 2023 before rising to eight in 2024 and 14 in 2025.
Among the 49 cases, 43 (88%) were detected in intracranial central nervous system (CNS) tissue specimens, while six (12%) were found in lung specimens. The presence of the fungus in lung specimens supports a presumed respiratory route of infection.
The detection rate also increased sharply. Between 2017 and 2023, an average of 8.4 cases were detected per 1,000 CNS specimens submitted for fungal PCR testing at the University of Washington. By 2025, this had increased by 210% to 26 cases per 1,000 specimens.
The cases were reported from 21 US states and the District of Columbia, with the highest numbers coming from California, Florida, Texas and Pennsylvania.
Also read: Candida auris: US CDC Reports 3,437 Cases of Deadly Superbug In 27 States
Why Is the Fungus Increasing?
The CDC said the reason for the apparent increase is unknown. The agency called for further research into possible epidemiologic risk factors and whether changes in the fungus, including potentially increased virulence, could be contributing to the rise.
The CDC also noted that there is no routine surveillance system for C. bantiana. Available information largely comes from case reports and retrospective studies, making it difficult to assess how widespread the infection is or whether its epidemiology is changing.
The report recommended that clinicians consider C. bantiana in patients with brain abscesses. Prompt antifungal treatment is required, while surgical removal of the abscess may improve outcomes.
What Is Cladophialophora bantiana?
Read More: Russia Plague Scare: Could It Trigger A New Pandemic? Experts Explain
C. bantiana is a highly virulent, neurotropic dematiaceous mold that predominantly causes brain abscesses.
It is a rare and life-threatening collection of pus enclosed in the brain tissue that creates dangerous pressure inside the skull.
It can infect both immunocompromised people and those without known immune problems. About half of reported patients have no preceding immunocompromising condition.
The presumed route of infection is inhalation or direct inoculation following a skin injury. The fungus can then enter the bloodstream and spread to the brain.
Rare pulmonary and skin infections have also been reported, but most cases involve the brain, often without evidence of infection elsewhere in the body or a clear source of exposure.
The fungus has only rarely been isolated from environmental sources, and researchers have not identified consistent exposure histories or risk factors among patients.
What Are the Symptoms?
Symptoms primarily reflect brain involvement, including fungal brain abscesses and increased pressure inside the skull.
Common symptoms include:
- Headache, often progressive or persistent
- Hemiparesis, or weakness on one side of the body
- Seizures
- Confusion, lethargy or altered consciousness
- Nausea and vomiting
- Fever
- Speech problems, including difficulty speaking
- Visual disturbances and other neurological deficits
Because C. bantiana commonly affects the brain, symptoms can vary depending on the location of the abscess and the extent of inflammation or pressure inside the skull.
How Is the Infection Treated?
Treatment requires prompt antifungal therapy, although there is no established optimal regimen for C. bantiana infection.
The CDC noted that surgical excision or drainage of brain abscesses may improve outcomes. A 2024 study involving 23 patients in France found more favorable outcomes among patients who underwent surgical treatment.
When possible, surgical removal of the abscess may therefore be considered alongside combination antifungal therapy.
The most effective antifungal combination remains uncertain. Treatment approaches have included liposomal amphotericin B, posaconazole or voriconazole, and flucytosine.
Russia Plague Scare: Is Pneumonic Plague Deadlier Than Bubonic & Septicemic Plague?

Credit: AI
A suspected case of pneumonic plague in Siberia has triggered quarantine measures after a laboratory worker at Russia’s Irkutsk Anti-Plague Research Institute died following severe pneumonia.
Russian health authorities have not yet confirmed that the 28-year-old died due to plague. Rospotrebnadzor has described the illness as pneumonia of unknown origin and said tests have found no evidence linking her death to pathogens at the institute.
Reportedly, around 200 people who may have had contact with her have been placed under medical observation.
As of October 5, Russian health authorities said about 60% of contacts had completed observation successfully and no one reported symptoms of plague infection.
The incident has attracted international attention as unconfirmed reports claimed that the woman may have developed pneumonic plague after she accidentally broke a test tube at the research facility. Russian authorities have denied that there was a laboratory accident. The hospital where she died has also been placed under quarantine.
Pneumonic vs Bubonic vs Septicemic Plague: Which Is Deadlier?
Bubonic plague is the most common form. It accounts for most number of naturally occurring human plague infections.
It usually develops after an infected flea bite. The bacteria this case travels to nearby lymph nodes and causing the characteristic painful swelling known as a bubo. If diagnosed early, it can be successfully treated with antibiotics.
Septicemic plague occurs when the bacteria enter the bloodstream. It can develop as a complication of bubonic plague, but it can also occur as a primary infection.
Because the bacteria are circulating throughout the body, patients can rapidly develop shock, bleeding and tissue death.
Pneumonic plague is the most dangerous from a transmission standpoint. It infects the lungs and can develop after inhaling Y. pestis or when infection spreads to the lungs from another form of plague.
Unlike bubonic and septicemic plague, pneumonic plague can spread directly from one person to another through respiratory droplets.
The CDC describes pneumonic plague as the most serious form of plague and says untreated pneumonic plague is almost always fatal. It can also progress rapidly, making early diagnosis and antibiotic treatment critical.
There isn’t a definitive answer to which one is deadlier as we have no simple ranking based purely on fatality percentage because outcomes depend heavily on how quickly treatment begins.
But pneumonic plague is generally regarded as the most dangerous form because it can be rapidly fatal and can spread directly between people.
The World Health Organization says untreated bubonic plague has a case-fatality rate of around 30% to 60%, while pneumonic and septicemic plague can be 100% fatal without treatment. Its incubation period is sometimes as short as one day.
Bubonic plague is less transmissible between humans and is usually more treatable when identified early.
Septicemic plague can also become rapidly life-threatening because the infection has entered the bloodstream.
Russia Plague: Updates
Regarding Russia’s plague scare, the concern around pneumonic plague is not only its severity, but the possibility of respiratory transmission if a case were ever confirmed. No plague infection has been confirmed in the reported Russian case so far.
Russian authorities have repeatedly said there is no confirmed plague outbreak and urged people to rely on official information rather than rumours. The Kremlin has also said the situation is under control.
The WHO has said, based on unofficial information, that the risk to the general public appears to be low.
Meanwhile, the US State Department says it is monitoring the situation. Secretary of State Marco Rubio said the possibility of an infectious disease spreading from a laboratory was being watched closely, while stressing that it was not currently a cause for alarm.
There are also reports that preventive measures have been introduced in the region, including isolation of hospital contacts and mask use at a nearby aluminum plant.
- Follow Us :


© $2026 Times Horizon Private Limited