
- Health Conditions A-Z
- Health & Wellness
- Nutrition
- Fitness
- Health News
- Ayurveda
- Videos
- Medicine A-Z
- Parenting
Measles Outbreak Cases Cross 100 Mark In US, Australia Sees Sudden Surge Of The Infectious Disease
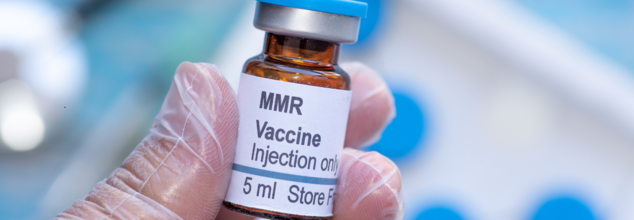
(Credit-Canva)
The current measles outbreak has gripped US states like Texas and New Mexico leaving people worried whether it would become a new pandemic. According to the Texas Department of State Health Services as of February 21, 90 cases were diagnosed in the last month in the South Plains area, with at least 77 of them were reported in children and teens under 17.
Measles is highly contagious and can be deadly. The outbreak, which started spreading in late January, has resulted in multiple hospitalizations, with at least nine confirmed cases and three probable cases as of early February. Health officials caution that at least one in five infected individuals will have to be hospitalized, highlighting the severity of the situation.
Misinformation surrounding vaccines and with the new Trump administration anti-vaccine campaigs, has causing parents to hesitate or refuse vaccination.
Furthermore, the country down under Australia is also witnessing a surge in measles cases as health officials in Sydney have issued an urgent alert, urging residents to watch for measles symptoms after an infected individual visited several places in Sydney over the last seven days.
Authorities report that the traveller had returned from South East Asia where there are ongoing outbreaks of measles.
What Are The Symptoms Measles?
Key symptoms of measles include fever, a runny nose, sore eyes, and a cough. Typically, a red, blotchy rash appears three to four days later, spreading from the head down to the body. Symptoms can manifest between 7 and 18 days after exposure.
Anyone who experiences these symptoms after potential exposure should immediately contact their doctor or emergency department. It is crucial to call ahead before visiting to avoid potentially exposing others in the waiting room. Dr. Selvey also highlighted that ongoing measles outbreaks are occurring in various parts of the world, making awareness and prompt action essential.
Why It Is Important To Get Vaccinated?
According to CDC everyone should get the MMR vaccine. It protects you from measles, mumps, and rubella. Getting vaccinated helps stop these diseases from spreading. There are two safe MMR vaccines available. They work the same way, so it doesn't matter which one you get. Kids can also get a shot that protects against chickenpox too, but this is only for children.
Who Should Get Vaccinated?
Kids Need Two Shots
All children should get two MMR shots. The first shot should be given when they are between 12 and 15 months old. The second shot should be given when they are between 4 and 6 years old. If needed, the second shot can be given earlier, but it must be at least 28 days after the first shot.
College Students Need to Be Protected
Students going to college or other schools after high school, need two shots if they are not already immune. The shots must be at least 28 days apart.
Adults Need at Least One Shot
Most adults need at least one MMR shot. Some adults need two shots, especially those who work in healthcare, travel a lot, or go to college. These people should get two shots, with 28 days between them.
Travelers Need to Be Extra Careful
Anyone traveling to other countries should make sure they are protected. Babies 6 to 11 months old should get one shot before traveling. Kids 12 months and older, teens, and adults need two shots, with 28 days between them.
Healthcare Workers Must Be Immune
People who work in healthcare should have proof that they are immune to measles, mumps, and rubella. If they are not immune, they need two MMR shots, spaced 28 days apart.
Women Thinking About Having Babies
Women who might get pregnant should talk to their doctor about the MMR vaccine. It's safe to get the shot while breastfeeding.
Pope Leo XIV, Diagnosed With Lung Cancer, Undergoes Surgery As His Brother Battles Relapsed Multiple Myeloma

Credit: X
Days after announcing that Pope Leo XIV will have surgery to have a lung nodule removed, he got a confirmed diagnosis of lung cancer. According to reports, he underwent surgery to have the lower lobe of his right lung removed.
The update comes as the 71-year-old pontiff's older brother, Louis Prevost, is undergoing treatment for relapsed multiple myeloma. The developments have brought attention to two different cancers affecting the papal family.
Pope Leo XIV's Lung Cancer Diagnosis
The pope underwent the procedure at Rome's Gemelli Hospital on October 13. According to the Vatican, tests confirmed lung adenocarcinoma, a type of cancer that develops in the cells lining the lungs.
The Vatican said in a medical bulletin, "The surgery was successful, and there were no complications."
The operation lasted approximately 90 minutes, and the pope subsequently returned to his hospital room. Pope Leo had announced on October 11 that doctors had discovered a lung nodule during routine medical examinations. He said the abnormality was detected early and that doctors recommended surgery to remove it.
"Dear friends, during some recent medical examinations, the doctors found a small, localized nodule in my lung. It was detected at a very early stage and is well-localized," he said.
He added, “The doctors believe it is advisable to intervene, so, following their advice, I have decided to undergo surgery to remove it. The operation is already scheduled for the next few days.”
The Vatican has not yet disclosed Pope Leo's cancer's stage or whether it has metastatised to other parts of the body. Further testing, including examination of the lymph nodes, will help doctors determine the extent of the disease and whether additional treatment is necessary.
Also read: Pope Leo XIV Will Undergo Lung Nodule Surgery: When Does Removal Become Necessary
What Is Lung Adenocarcinoma?
Lung adenocarcinoma is the most common type of lung cancer. It develops in glandular cells that produce substances like mucus. It is classified as a non-small cell lung cancer.
Although it is frequently linked with smoking, it can also occur in people who have never smoked. Other risk factors include exposure to radon, second-hand smoke and certain workplace carcinogens.
Symptoms may include a persistent cough, coughing up blood, chest pain, breathlessness and unexplained weight loss. Early-stage disease may cause no noticeable symptoms but it can be detected through imaging and scans.
Treatment largely depends on the cancer's stage, location and characteristics of the tumour. Surgery to remove the affected portion of the lung is a common treatment strategy when the tumour is localised. Chemotherapy, immunotherapy or targeted therapies may be considered depending on further findings.
In Pope Leo's case, the lower lobe of his right lung was removed. The results of further tests will help establish whether surgery alone is sufficient.
Pope's Brother Louis Prevost's Multiple Myeloma Relapsed
Meanwhile, the pope's older brother, Louis Prevost, is receiving treatment for multiple myeloma, a blood cancer that affects plasma cells in the bone marrow. His wife, Deborah Prevost, told CBS News that he was first diagnosed in 2017.
Treatment in 2019, which included stem cell treatment and participation in a clinical trial, helped keep the disease at a "very low level".
However, she said he "fell out of remission" approximately three months ago. He is now participating in another clinical trial at a local hospital in Florida.
Multiple myeloma develops when abnormal plasma cells multiply in the bone marrow, interfering with normal blood cell production and damaging bones and kidneys.
Symptoms can include bone pain, fatigue, frequent infections, anaemia and kidney problems.
Unlike lung adenocarcinoma, which forms a solid tumour in lung tissue, multiple myeloma is a cancer of plasma cells. It is generally considered treatable but not usually curable, and the disease can return after periods of remission.
Speaking about the family's situation, Deborah said, "We keep praying, keeping spirits up for both of them."
Congo's Ebola Death Toll Tops 4,300, Cases Cross 9,000; Kenya Reports No New Cases After 293 Tests
Credit: iStock
The Ebola outbreak in the Democratic Republic of Congo (DRC) has surpassed 9,000 confirmed cases and 4,300 deaths, making it the deadliest outbreak in the country's history. Meanwhile, Kenya has reported no new infections after testing 293 samples following its first confirmed case linked to the outbreak.
According to data released by Congo's public health institute on October 13, the country has recorded 9,066 confirmed Ebola cases and 4,381 deaths.
Health authorities continue to struggle to contain transmission across multiple hotspots in the country. The outbreak, declared in May 2026, is caused by the Bundibugyo strain of the Ebola virus, which has no approved vaccine or specific treatment yet. The epidemic has surpassed Congo's previous worst outbreak, which occurred between 2018 and 2020.
The outbreak is now the second-largest Ebola epidemic globally, after the 2014-2016 West African outbreak, which infected more than 28,600 people and killed over 11,000 across Guinea, Liberia and Sierra Leone.
Kenya Reports No New Cases
Kenya confirmed its first imported case of Ebola on October 6, after a Kenyan national who had travelled from Congo through Uganda died in Nairobi on October 5.
According to Health Minister Aden Duale, the patient fell ill about a month ago and was treated at several hospitals in the DRC before traveling to Nairobi. The patient died days after arriving in the Kenyan capital, according to Reuters.
Kenyan health authorities have placed the country on high alert and are monitoring for possible additional cases. At least 28 contacts, including family members and healthcare workers who cared for the patient, have been identified.
The country's Ministry of Health said on October 11 that 293 samples had been tested since the patient's death and no new infections were detected. The tests covered 289 alerts and only the initial confirmed case tested positive.
Authorities have continued contact tracing and monitoring people who may have been exposed to the virus. Kenya is also strengthening surveillance and public health measures to prevent further transmission.
Also read: Congo Ebola Cases Top 8,000; Deaths Near 4,000 As Treatment Delays Remain A Concern
A Challenging Outbreak
The spread of Ebola has been difficult to contain amid Congo's fragile healthcare infrastructure, insecurity, population movement and challenges in implementing response measures. Health officials are also concerned about transmission in communities outside treatment centres.
The outbreak has affected multiple provinces in eastern Congo, raising concerns about further international spread. Uganda previously reported cases linked to the epidemic but was declared Ebola-free in August.
Although Kenya's latest testing results offer some reassurance, authorities continue to monitor high-risk contacts.
What Is Bundibugyo Virus Disease?
Bundibugyo virus disease is a rare and deadly illness that has caused outbreaks in several African countries in the past.
It is distinctly different from other known ebolaviruses like the Zaire ebolavirus or Sudan ebolavirus. The 2007 outbreak, where Bundibugyo was detected for the first time, resulted in over 100 cases and was officially declared over in early 2008.
According to the US CDC, the Bundibugyo strain is spread by contact with the blood or body fluids of a person who is infected with or has died from BVD.
It is also spread by contact with contaminated objects (such as clothing, bedding, needles, and medical equipment), or by contact with animals, such as bats and nonhuman primates, that are infected with BVD.
Symptoms include fever, headache, muscle pain, weakness, diarrhea, vomiting, stomach pain, and unexplained bleeding or bruising (a late stage of illness).
West Nile Virus Claims Two Lives In North Carolina: Why The Mosquito-Borne Infection Can Turn Severe

Credit: iStock
Two adults in central North Carolina have died after contracting West Nile virus, prompting health authorities to urge residents to take precautions against mosquito bites as cases continue to rise across the United States.
The North Carolina Department of Health and Human Services confirmed the deaths on October 9, warning that senior citizens and people with underlying health conditions face a higher risk of developing severe illness from the virus.
The US Centers for Disease Control and Prevention (CDC) has reported 11 human cases of West Nile virus in North Carolina this year. The state’s first human case of 2026 was identified in a Gaston County resident in August.
Dr Cameron Wolfe, an infectious disease expert with Duke Health, told WRAL that people infected with the virus may not realise they have it. “If you get West Nile, you probably won't know it,” he said.
Symptoms Of West Nile Virus
West Nile virus circulates in the environment between mosquitoes, and the species is called Culex. It also circulates via birds. People become infected when the mosquitoes feed on infected birds and then bite people.
The CDC says that people are dead-end hosts, because unlike birds, they do not develop high enough levels of virus in their bloodstream and cannot pass the virus on to other biting mosquitoes.
The virus is rarely transmitted from person-to-person by blood transfusion, organ transplantation, and mother to baby, during pregnancy, delivery, or breastfeeding.
Because the virus can be transmitted through blood and organ transplantation, persons who were recently diagnosed with West Nile virus infection should not donate blood or bone marrow for 120 days following infection.
Symptoms can include fever, headache, body aches, joint pain, vomiting, diarrhoea and rash. In rare cases, the infection can become severe and affect the brain and nervous system, leading to encephalitis or meningitis.
Encephalitis is the inflammation of the brain can cause confusion, altered consciousness, seizures and, in severe cases, coma.
Meningitis is the inflammation of the membranes surrounding the brain and spinal cord can cause severe headaches, fever and neck stiffness.
Acute flaccid paralysis, also one of the complications, occurs when the virus can damage nerve cells controlling muscles, causing sudden weakness or paralysis. In severe cases, respiratory muscles can be affected, leading to breathing failure.
Older adults and people with conditions such as diabetes, high blood pressure, cancer or weakened immunity are at greater risk of developing severe disease.
There is currently no vaccine to prevent West Nile virus infection in humans, and no antiviral treatment is available. Care for severe cases focuses on managing symptoms and complications.
How To Prevent?
Health officials continue to emphasize simple prevention measures as the best defense against WNV. These are:
- Using EPA-approved insect repellents
- Wearing long-sleeved shirts and pants outside
- Adding screens on windows and doors to prevent mosquitoes from entering
- Eliminating standing water within homes, such as flowerpots, gutters, and bird baths
By doing these, residents will be able to drastically lower their chances of infection, particularly when it comes to the active mosquito season.
- Follow Us :


© $2026 Times Horizon Private Limited