
- Health Conditions A-Z
- Health & Wellness
- Nutrition
- Fitness
- Health News
- Ayurveda
- Videos
- Medicine A-Z
- Parenting
Matthew Perry Investigation: Can Ketamine Kill Someone?

Credits: IMDb
“I'm not great at the advice. Can I interest you in a sarcastic comment?”

This is what ‘Friends’ actor Matthew Perry’s character Chandler Bing was known for. He was known for being funny. However, he had his own struggles in his personal life and those struggles were acute depression. He was treating it with ketamine infusion therapy which is legal in the US and the UK.
What is Ketamine infusion therapy?
Ketamine is an anaesthetic used to treat depression, anxiety and pain under supervised and controlled medical settings. However, it does have its side effects, which can lead to distortion of sight, sound and time. It can also produce calming and relaxing effects.
Ketamine increases a person’s heart rate and blood pressure. If overdosed, it can leave users confused and agitated and can cause them to hurt themselves without even realising it. It can also lead to liver damage and bladder problems.
However, when used in moderation and under the supervision of medical doctors, it can treat depression where traditional antidepressants have failed.
Prof Rupert McShane, a University of Oxford psychiatrist who runs an NHS ketamine treatment clinic told BBC that ketamine “probably turns off the area of the brain that is involved in disappointment.”
Can Ketamine Infusion Therapy Kill Someone?
In simple terms, it cannot, be if the dosage is given in a controlled setting and as prescribed. Ketamine infusion therapy uses drugs in small doses than those used for anaesthesia. It acts faster than traditional anti-depressants, but the effects also wear off way quickly. Which is why it is important to monitor patients’ mental state for relapsing back into depression and discouraging them from overdosing on it.
There are ways of giving people ketamine. One of the ways is through “infusing”, which means to use an IV drip. However, injections, nasal sprays and capsules are also methods used to give people ketamine.
Since the dosage of ketamine used in the infusion treatment is small, it being the reason of actor Perry’s death was ruled out. The medical examiner also noted that Perry’s last ketamine infusion therapy session happened more than a week before his death, which means by the time he had died, it must have worn off.
So, What Happened To Perry?
Though Perry’s last session was more than a week before, his post-mortem showed that his blood contained a high concentration of ketamine. He had died of the “acute effects” of ketamine.
If it was not his session, then how did he get ketamine?
Prosecutors alleged that his assistant gave him at least 27 shots of ketamine in four days before his death, reported BBC.
Perry has been open about his personal struggles and this is what the doctors and dealers used against him. Martin Estrada, the US attorney for California’s Central District told the BBC that people took advantage of his condition. They charged him 165 times more than what vials of ketamine cost.
Names that have come up include Dr Salvador Plasencia, drug dealers “Ketamine Queen” aka Jasveen Sangha and Eric Fleming, and Perry’s live-in assistant Kenneth Iwamasa.
Who Are These Names And What Did They Do?
Ketamine Queen or Sangha supplied drugs that led to Perry’s death. Her home was a “drug-selling emporium,” said Estrada. More than 80 vials of ketamine, and thousands of pills including methamphetamine, cocaine and Xanax were allegedly found in her house known as the “Sangha Stash House.”
Sangha is known to deal with high-end celebs and was a “major source of supply for ketamine to others as well as Perry,” said Estrada.
Dr Plasencia called Perry a “moron” while charging him $2,000 for vials that cost only $12. He sold Perry 20 vials of ketamine between September and October 2023, costing $55,000.
He was the one who taught Iwamasa, who had no medical knowledge to inject the drug. This is after he knew that “Perry’s ketamine addiction was spiralling out of control,” as per what the investigators told the BBC.
Another dealer Fleming was told by Sangha to “delete all our messages.” While Fleming pleaded guilty to conspiring to distribute drugs unlawfully, he also allegedly messaged Sangha: “Please call...Got more info and want to bounce ideas off you. I’m 90% sure everyone is protected. I never dealt with [Perry] only his assistant. So the assistant was the enabler.”
The court documents also revealed that he asked Sangha on whether the ketamine stays in your system or “is it immediately flushed out.”
Dr Pepper, Bots, Cans
The people who allegedly exploited Perry used coded language for ketamine and called it “Dr Pepper”, “bots”, or “cans.”
Selling overpriced drugs, taking advantage of Perry’s mental condition and falsifying medical records to make the drugs given to him look legitimate by Dr Plasencia is what took Perry’s life.
Iwamasa is said to have administered more than 20 shots of ketamine and three on the day Perry died. Whereas ketamine is only administered by a physician. Authorities also found that weeks before Perry’s death, Dr Plasencia allegedly bought 10 vials of ketamine and intended to sell to Perry.
He also injected Perry with a large dose, two days later. This caused him to “freeze up” and spiked his blood pressure.
When I Die, I Want Helping Others To Be The First Thing That’s Mentioned
Perry had always been open about his drug addictions, struggles with alcohol and his depression. He said that his openness would help others who are also struggling and wanted to be remembered by his quote which also is on the homepage of the Mattew Perry Foundation that helps others struggling with the disease of addiction: “When I die, I want helping others to be the first thing that’s mentioned.”
Five arrests have been made in the case so far.
Indian Medical Industry Backs Maharashtra FDA Crackdown On Device Markups
Credit: iStock
India’s medical industry has backed Maharashtra Food and Drugs Administration (FDA) Commissioner Tukaram Mundhe’s concerns about the sharp gap between procurement prices and maximum retail prices (MRPs) of several medical devices and hospital consumables, with patients ultimately bearing the burden.
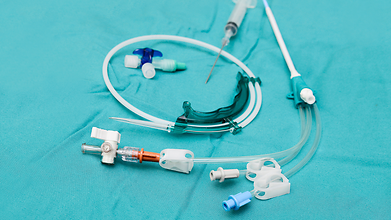
IV Set: At Rs 11.05, MRP Rs 325
In a post on social media platform X, Mundhe said the most expensive part of a hospital bill may never touch the hospital, but patients bear the brunt as they have the least information to evaluate, compare prices, or seek alternatives.
This is because “a patient admitted for care has no way of knowing whether the price on a medical consumable reflects its actual cost or a markup fixed long before it ever reached the ward," said the IAS officer, who has previously led several food safety enforcement measures in the country.
He flagged the information gap as a core public health issue.
He shared how a survey of hospital consumables in Maharashtra found an IV infusion set with a trade price of Rs 11.05 carrying a printed MRP of Rs 325, a markup of 2,841%. A syringe procured at Rs 6.75 carried an MRP of Rs 57.20, while a catheter procured at Rs 29.41 carried an MRP of Rs 310.
He noted that “the MRP is often fixed upstream by manufacturers and distributors, disconnected from the trade price by a wide, unexplained margin. The result is a system where the party bearing the cost has the least information to evaluate it”.
Also read: High Sugar, Salt Or Fat? India May Mandate Red Hexagon Labels On Food Packs
Experts Call For Scientific Costing
“Piecemeal assessment of pricing will not serve any purpose. Hospitals get reimbursed under CGHS and PMJAY for procedures at below operating cost. We do not look at that. It is time that we carry out a scientific costing exercise on delivery of healthcare,” Dr Girdhar Gyani, AHPI Director, told HealthandMe.
“Patients deserve fair prices, not 2,800% markups, and ethical manufacturers deserve a level playing field and a fair opportunity to provide affordable, fair-priced medical devices,” added Rajiv Nath, Forum Coordinator, Association of Indian Medical Device Industry (AiMeD).
Maharashtra FDA Flags Regulatory Gap
Mundhe also flagged the structural regulatory gap. He noted that “scheduled medicines are capped under the Drugs (Prices Control) Order, 2013. Most medical devices and consumables are not leaving both the pricing and the information around it almost entirely unmonitored”.
He called on the Department of Pharmaceuticals and the NPPA to “review” these findings and lay down “clear guidelines on the permissible gap between trade procurement price and declared MRP”.
“It's a step toward closing not just a pricing gap, but the information gap patients are left to bear alone”.
Industry Seeks Fair Pricing Policy
Welcoming the timely intervention by Mundhe, AiMeD said it has consistently cautioned that the current regulatory framework under the Drugs (Prices Control) Order, 2013 is inadequate for medical devices.
“Patients, who cannot bargain or choose devices, are left vulnerable to inflated MRPs, while ethical manufacturers and importers are forced to either play within a distorted system or exit the market. This situation penalises both consumers and responsible suppliers, eroding trust and competitiveness”, it said.
AiMeD has long advocated for a Fair Pricing Policy tailored to medical devices, with transparent trade-margin caps based on ex-factory or landed import prices. Such a system would ensure affordability for patients, encourage ethical competition and strengthen the “Make in India” vision.
US FDA Launches Expedited IND Pilot To Speed Up Drug Trials

Credit: iStock
The US Food and Drug Administration (FDA) today launched a pilot program aimed at speeding up early-stage drug research and reducing delays before potential new medicines enter human trials.
Called the Expedited Investigational New Drug (IND) Pilot, the program is part of the US Department of Health and Human Services’ (HHS) Operation TrailBlazer, launched in June.
The initiative aligns with the Trump Administration’s efforts to accelerate clinical trials and drug research in the US and maintain American leadership in medical innovation, particularly ahead of China.
“The pilot not only pairs industry innovators with top research institutions to accelerate high-quality data being submitted to the FDA, it also tests if the partnership can accelerate what happens after the FDA allows a clinical trial to proceed,” said Acting FDA Commissioner Kyle Diamantas, J.D.
How Will the Pilot Work?
Also read: Robert F. Kennedy Jr. Launches Reforms To Speed Up Early Drug Research In US
The pilot aims to shorten the time between identifying a potential drug and starting a first-in-human clinical trial by pairing drug companies with qualified research institutions (QRIs).
These institutions will provide scientific expertise to support the preparation of Investigational New Drug (IND) applications.
The FDA said first-in-human clinical trials can currently take up to two years to complete in the US. Similar trials are completed faster in China and Australia, raising concerns about America's position in global scientific innovation.
The FDA will accept applications to participate in the pilot until October 30, 2026.
Review of IND Applications
Under the pilot, selected QRIs will support the IND application preparation process. This will allow the FDA to review and accept individual components of an application on a rolling basis during the pre-IND phase, rather than waiting for all components before beginning review.
The approach is intended to help identify and resolve issues with an IND application sooner and reduce the risk of the FDA placing a first-in-human clinical trial on hold during the 30-day IND period.
Read More: 18-Year-Old Dies From Rare Measles Brain Complication As Pennsylvania Death Toll Hits 4
The FDA said the goal is to make the path from scientific discovery to first-in-human trials faster, more predictable and more collaborative.
The federal agency said earlier planning and coordination could reduce unnecessary delays between the start of IND preparation and the beginning of first-in-human studies.
“The pilot hopes to utilize the American innovation ecosystem to accelerate the time to first-in-human clinical trials,” said Karim Mikhail, Director of the Center for Biologics Evaluation and Research (CBER).
Who Can Apply?
Drug sponsors and prospective QRIs will apply as a pair, with drug sponsors submitting applications to the FDA.
Applications will be reviewed by FDA scientific experts. The agency expects to select 8–10 Sponsor-QRI pairs for the initial pilot cohort.
READ: Fall Vaccines 2026: US Doctors Issue COVID, Flu And RSV Jab Guidance
What Is Operation TrialBlazer?
While launching Operation TrialBlazer, Robert F. Kennedy Jr., in a Fox News op-ed, said, “America should continue to lead the world in clinical research and medical innovation. Instead, we are losing ground.”
He cited a study showing that China now conducts more early-stage clinical trials than the United States.
In 2025, Chinese companies accounted for nearly half of global pharmaceutical licensing deal activity. “Those trends should concern every American,” Kennedy said, stressing that “the future of medicine should be built in America.”
According to the FDA, Operation TrialBlazer will help shorten development timelines by six to 12 months through a series of measures, including pairing drug developers with qualified academic centers and contract research organizations to prepare first-in-human trial applications.
RFK Jr-Backed ‘Wolverine’ Peptide Use Surges: Why Are People Taking An Unapproved Drug For Injury Recovery?
Credit: AI
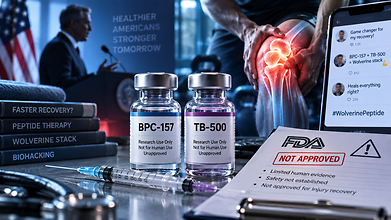
The use of an experimental peptide, popularly known as part of the 'Wolverine stack', has surged significantly in the US, despite limited evidence that it actually helps people recover from injuries.
A new study based on more than 15 million medical records found that documented use of BPC-157, an unapproved peptide promoted online for pain relief, healing and performance enhancement, increased 33-fold between 2020 and 2026.
The findings were reported as US Health Secretary Robert F. Kennedy Jr. has backed efforts to make the peptide available through compounding pharmacies.
BPC-157 is often combined with TB-500, a peptide derived from thymosin beta-4, in what users call the 'Wolverine stack'. The combination is marketed online as a way to accelerate tissue repair and recovery from muscle, tendon and other injuries.
Why Are People Taking BPC-157?
Researchers identified 1,039 patients with documented BPC-157 use. Among 644 patients, the peptide was taken for conditions ranging from sports injuries and chronic pain to gastrointestinal problems.
Pain and gastrointestinal symptoms were among the most common reasons for starting BPC-157. Many users obtained it through compounding pharmacies or grey-market peptide vendors.
The appeal comes largely from claims that BPC-157 can promote tissue repair and accelerate recovery. But these claims have not been established through the kind of controlled human trials normally required to demonstrate that a treatment works.
Also read: Bouncy Castles Linked To MRSA Outbreak In 48 Children In Ireland
Effect Of BPC-157 On Injury Recovery
The new analysis was based on real-world medical records, rather than a randomised clinical trial. Only around one-third of patients had documented responses to treatment. Some doctors recorded improvements, but patients were frequently taking other drugs or undergoing other treatments at the same time for recovery.
Dr Flynn McGuire of the University of Utah, who was not involved in the research, said, “There was no placebo or untreated comparator, and there was no standardized indication, formulation, dose, route, treatment duration, or outcome assessment.”
That makes it impossible to determine whether reported improvements came from BPC-157, another treatment, natural recovery or placebo effects. McGuire said randomised controlled trials are needed to establish whether the peptide produces meaningful clinical improvement.
Also read: BORG Drinking Trend: Why These Viral Alcohol Jugs Can Be Dangerous
Concern About Its Safety
BPC-157 is not approved by the US FDA for medical use. The FDA has previously raised concerns about the peptide, including the possibility of immune reactions and problems related to peptide impurities and product quality.
The agency says it has limited safety information for BPC-157 in humans and lacks enough information to determine whether some routes of administration could cause harm.
The FDA has also reported adverse events in its database involving reactions at the injection site, shortness of breath and skin or gum pigmentation changes, although it cautions that these events cannot necessarily be attributed to BPC-157.
In July, an FDA advisory committee considered whether BPC-157 and other peptides should be permitted as bulk substances for compounding. The process does not mean BPC-157 has been approved as a drug.
- Follow Us :


© $2026 Times Horizon Private Limited