
- Health Conditions A-Z
- Health & Wellness
- Nutrition
- Fitness
- Health News
- Ayurveda
- Videos
- Medicine A-Z
- Parenting
Marburg Virus Outbreak: Rwanda Reports 20 Cases

Credits: Canva
After mpox outbreak, Africa is under the threat of yet another virus outbreak, this is the Marburg virus outbreak in Rwanda. So far, six people have died from the outbreak, confirmed the health minister. Most victims were the healthcare workers in the hospital's intensive care unit. As per reports, 20 cases have been identified since the outbreak was confirmed on Friday.
What Is Marbug Virus?
With the fatality rate of 8% it is the same virus family as Ebola. The main carrier is from fruit bats which spreads to humans then through the contact of bodily fluids of infected individuals, it spreads to others.
Common Signs And Symptoms
The common signs and symptoms of the Marburg virus include fever, pain, diarrhoea, vomiting and in the case of extreme blood loss, death too can happen.
So far, there is no specific treatment or vaccine for the virus. However, treatments like drugs and immune therapy are being developed as per the World Health Organisation (WHO).
Call Of Action
Rwanda says that it has intensified its contact tracing, surveillance and testing to contain the spread. It has also tracked about 300 people who had come into contact with individuals affected by the Marburg virus.
The health minister has urged people to stay vigilant and avoid any physical contact and to wash their hands with clean water, soap or sanitiser and report any suspected case.
As of now, most of the cases have spread to the capital in Kigali. In light of this, the US Embassy in the city has advised its employees to work remotely for the next week.
This is the first time Rwanda has confirmed for Marburg cases, before this, in 2023, Tanzania confirmed the outbreak, whereas three people had died of this in Uganda in 2017.
History Of Marburg
As per WHO, this virus kills half of the people it infects. In the previous outbreaks, it has killed between 24% to 88% of the patients.
The virus was first detected in 1976 after 31 people were infected, out of which 7 died in simultaneous outbreak in Marburg and Frankfurt in Germany, and Belgrade in Serbia.
The source was traced to African green monkeys who were imported from Uganda. However, other animals too are linked to the virus spread, including bats.
In the past, the virus outbreaks have happened in countries like Equatorial Guinea, Ghana, the Democratic Republic of the Congo, Kenya, South Africa, Uganda, and Zimbabwe. In 2005, this virus killed 300 people in Angola.
However, for the rest of the world, only two people have died from the virus in the rest of the world, with one of them being in Europe, and the other in the US. These both have been on expeditions to caves in Uganda.
73% Of Mouth Cancers In Indian Women Linked To Smokeless Tobacco, Men Accounted For More Than 57%: Study
Credit: AI
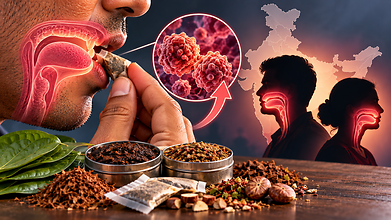
Smokeless tobacco accounted for 57.3% of mouth cancers among men in India, while tobacco in any form estimated to be at least 73.4% of mouth cancers among women, according to a new study published in the Indian Journal of Medical Research.
The study, Head and Neck Cancer Burden Attributable to Tobacco Use in India: National and Region-wise Estimates, sheds light on the differences in tobacco-related cancer risks by sex, cancer site and region. The findings also bring attention to the role of smokeless tobacco products and their contribution to head and neck cancer burden in India.
The researchers estimated that eliminating tobacco exposure could prevent a bulk proportion of these cancers.
Smokeless Tobacco Linked To Mouth And Lip Cancers
Researchers studied records of 11,285 patients diagnosed with head and neck cancers and 7,154 people with non-cancerous conditions who visited the Regional Cancer Centre in Thiruvananthapuram, Kerala, India between 2019 and 2024.
Among men, smokeless tobacco accounted for 61.8% of lip cancers, 30.7% of tongue cancers and 57.3% of mouth cancers.
On the other hand, almost 40.2% of cancers of the base of the tongue, tonsils and oropharynx, 45.7% of hypopharyngeal cancers and 38.4% of laryngeal cancers were attributed to smoking.
The authors highlighted how smoking and smokeless tobacco expose oral tissues to carcinogens. The authors wrote, “This may be because smokeless tobacco directly contacts the oral cavity, causing prolonged exposure of the tongue to carcinogens, whereas smoking produces more diffuse and less concentrated exposure.”
The study also found that 55.3% of men with mouth cancer used smokeless tobacco, compared to 17.5% of men in the comparison group. Among men diagnosed with hypopharyngeal cancer, 85% smoked.
High Burden Of Tobacco-Related Mouth Cancer Among Women
Among women, smokeless tobacco accounted for around 68.8% of lip cancers and 68% of mouth cancers. Smoking accounted for 41% of oropharyngeal cancers and 34% of hypopharyngeal cancers.
The researchers estimated that the odds of mouth cancer among women who used smokeless tobacco were 17.6 times those among non-users. Among men, the corresponding odds ratio was 5.5.
Tobacco Cancer Risks Across States
The study also shows differences in tobacco-related cancer risks between states. Among men, the estimated proportion of mouth cancers due to smokeless tobacco was 71% in Jharkhand and 70.3% in Odisha.
In southern India, the estimates were 50.2% in Karnataka, 35.1% in Tamil Nadu, 33.9% in Telangana, 25.6% in Andhra Pradesh and 25.1% in Kerala.
Among women, the estimated proportion of mouth cancers due to smokeless tobacco exceeded 80% in Chhattisgarh, Odisha and several Northeastern states. In Tripura, it was around 90.4%.
The authors said that these differences could be due to regional variations in tobacco consumption and the products used.
However, the study used cancer risk estimates derived from hospital-based data in Kerala and applied them nationally because state-specific risk estimates were unavailable.
The authors addressed this limitation, stating, “In this study, due to limited State-specific data, cancer risk from tobacco exposures was assumed uniform nationwide.”
The researchers stressed the need for prevention by improving access to tobacco cessation services, especially in regions with high estimated burdens of tobacco-related cancers.
“The findings emphasise the need to strengthen tobacco cessation services, especially for high-risk men in regions with elevated population attributable fractions,” the authors wrote.
Retatrutide Driving Peptide-Linked Emergency Hospital Admissions In Australia: What Are The Risks?
Credit: iStock
Health authorities in Australia's New South Wales have warned against unapproved peptide products after emergency department presentations linked to their use surged.
NSW Health recorded 1,180 peptide-related hospital presentations between July 2025 and September 2026, with about a quarter involving young people aged 16 to 24.
Retatrutide Accounts For 71% ER Visits
Retatrutide accounted for 71% of peptide-related emergency hospital admissions. Products described generically as “peptides” or by other names accounted for another 38%, while 8% involved combinations of products, News.com.au reported.
Peptides have gained popularity through social media, where influencers promote them for weight loss, muscle growth, injury recovery and anti-aging. However, unapproved products may have uncertain composition, quality and safety.
Peptide-Related Emergency Visits Rise 4,240%
Monthly hospital emergency visits rose from five in July 2025 to 217 in September 2026, an increase of 4,240%. New South Wales Health Minister Ryan Park warned that unapproved substances posed health risks and placed additional pressure on public hospitals.
“Even when a product looks professional or comes in convincing packaging, that does not guarantee it is safe for use,” Park said.
Young people aged 16 to 24 accounted for about a quarter of presentations. Those aged 25 to 34 made up 32%, while 26% were aged 35 to 44. Men accounted for 51% of cases.
Health Risks Of Using Unapproved Peptides
Patients presenting to emergency departments after adverse reactions reported symptoms including
- abdominal pain,
- nausea,
- vomiting,
- chest pain,
- anaphylaxis
- allergic reactions.
Australia's Therapeutic Goods Administration (TGA) approves some peptide-based products, but many promoted online are not approved and may be unlawful to import, supply or advertise. These include BPC-157, GHK-Cu, TB-500, retatrutide and CJC-1295.
NSW Health Chief Health Officer Dr. Kerry Chant cautioned that products sold under the same label could vary in composition and strength.
“A professional looking website, a label, purity claim, reviews, or influencer endorsement is not proof of what is inside the product,” Chant said.
She urged people to consult their general practitioner about potential risks and safer, evidence-based alternatives.
Read More: GLP-1 Weight Loss Drugs Ozempic, Wegovy, Mounjaro Tied To Over 60 Reported Deaths In Australia
What Is Retatrutide, And What Are The Risks?
Retatrutide is an investigational obesity drug developed by Eli Lilly. It targets three hormone receptors involved in appetite, blood sugar and energy balance: GIP, GLP-1 and glucagon.
In a Phase 2 trial published in the New England Journal of Medicine, participants receiving the highest dose lost an average of 24.2% of their body weight over 48 weeks. A Phase 3 trial published in The Lancet reported nearly 21% average weight loss among participants with type 2 diabetes and obesity.
Despite these results, retatrutide remains investigational and is not yet FDA-approved.
There have been several unbranded, generic copies of the Retatrutide chemical sequence manufactured by unregulated chemical labs and sold online. It may not have verified composition, quality or strength.
The drug has been dubbed the “Godzilla” of weight-loss jabs. A recent report by the Daily Mail showed 129 symptoms associated with its use, including skin-burning sensations, panic attacks, a racing heartbeat and depression.
Professor Naveed Sattar, professor of cardiometabolic medicine at the University of Glasgow, warned against purchasing unlicensed weight-loss products online. “I would urge people to avoid buying unlicensed weight-loss products online,” he said, according to Daily Mail. “There is no certainty about what these products contain, and without proper regulatory oversight there is a risk of adverse effects.”
137 Cancer Drugs To Cost Up To 70% Less From November 9: NPPA Caps Trade Margins

Credit: AI
The National Pharmaceutical Pricing Authority (NPPA) has capped trade margins on 137 non-scheduled anti-cancer drugs at 30%. The move is expected to reduce the maximum retail prices (MRPs) of the cancer medicines by up to 70%.
Announced by the Department of Pharmaceuticals under the Ministry of Chemicals and Fertilizers, the measure aims to curb excessive mark-ups in the distribution and sale of cancer medicines.
It covers a range of anti-cancer drugs, including patented treatments, and is intended to ease the financial burden on patients and their families.
The revised prices is reported to come into effect on November 9, 2026. Manufacturers have been directed to submit revised prices to the NPPA within seven days of the notification.
Indian Government Caps Trade Margins On Cancer Drugs
Also read: Dr Rachna Shroff: Indian-American Cancer Researcher Who Turned Her Diagnosis Into Advocacy
Trade margins are the difference between the price at which a medicine enters the distribution chain and the price charged as it moves further along that chain. These margins reflect in the final cost of the medicines to the patients.
According to the government, an analysis of market data found that non-scheduled anti-cancer medicines had an average trade mark-up of around 170%, some even reaching as high as 700%.
Non-scheduled medicines are drugs that do not fall under the scheduled list of medicines subject to specific ceiling prices under the Drug Price Control Order.
The latest intervention uses the government's powers under Paragraph 19 of the Drugs (Prices Control) Order, 2013, to cap trade margins in the affordable healthcare in serious illnesses like cancer.
By limiting these margins, the government expects to bring down prices of these medicines and help patients to avoid switching to different medicines solely because of cost.
The list includes 137 non-scheduled anti-cancer drugs recommended by an expert committee under the Directorate General of Health Services (DGHS). The committee included oncologists, medical specialists, hospital experts and government officials. The medicines covered include pembrolizumab, ribociclib and abemaciclib, which are used in the management of certain cancers. Other medicines on the list include atezolizumab and bevacizumab.
Expected Savings Of Nearly ₹2,500 Crore For Patients
Also read: H. pylori And Cancer: US Gastroenterologist Explains How A Common Stomach Infection Raises Risk
With this measure, the government expects to generate annual savings of approximately ₹2,500 crore for patients. The expected reduction in MRP ranges roughly from 20% to 70%, depending on the medicine.
This is not the first the government has intervened in the pricing of anti-cancer drugs. In 2019, trade margins on 42 anti-cancer drugs were capped at 30%. After that, the MRPs of 526 brands of non-scheduled anti-cancer medicines were reduced by up to 90%, which generated annual estimated annual savings of ₹984 crore.
The latest measure expands the rule to a larger group of medicines to improve affordability and better access to cancer treatment.
NPPA's Directives To Drug Manufacturers
The NPPA has asked drug manufacturers to submit revised MRPs within seven days of the announcement and make the updated prices available through their websites, hospital pharmacies and retailers.
From November 9, hospitals and pharmacies must sell the cancer medicines at the revised prices without fail. Hospitals and retailers who sell anti-cancer medicines in substantial amounts everyday have specifically been asked to comply with the notification.
The government has also asked manufacturers to maintain production and supply levels to prevent shortages after the price changes. State drug controllers will monitor compliance among manufacturers, distributors, retailers and healthcare institutions.
Patients must confirm the exact brand, strength and formulation prescribed, as prices can differ across products from November 9. They should not change or discontinue cancer treatment on their own without consulting their oncologist.
- Follow Us :


© $2026 Times Horizon Private Limited