
- Health Conditions A-Z
- Health & Wellness
- Nutrition
- Fitness
- Health News
- Ayurveda
- Videos
- Medicine A-Z
- Parenting
Is The Viral 'Quad-demic' Still Swirling? Know The Good, Bad And Ugly
Image Credit: Health and me
There's been an alarming increase of respiratory and gastrointestinal viruses in the United States lately, causing anxiety about a so-called "quad-demic". According to surveillance reports, influenza, COVID-19, RSV and norovirus are at very high levels everywhere. While the surge aligns with patterns typical for this season, several epidemiologists view simultaneous infections of such proportions to pose risks not only to individual healthcare but public health.
The incidence of the quad-demic should vary with seasonal patterns, vaccination rates, and public health interventions. Each virus alone is relatively easy to manage; however, the effect of all together could lead to overburdening of health care facilities and increase risks for those at higher risk. Continuing surveillance, early testing, and proactive prevention measures will play an important role in the control of these infections going forward.
While the term "quad-demic" sounds daunting, it must be taken into perspective. For years, we have had all these viruses together, and we have the capabilities to mitigate some of the risk. Vaccination, proper hygiene and using common sense helps individuals get through the season unscathed. Is the quad-demic a permanent fixture or just another seasonal wave? Let's break this down.
What is the Quad-demic?
Typically, flu, COVID-19, and RSV have been the primary culprits behind seasonal respiratory infections. However, norovirus, a highly contagious stomach bug, has emerged as a fourth significant player, inducing fears of a more severe and widespread viral outbreak. According to the Centers for Disease Control and Prevention (CDC), the U.S. recorded nearly 500 norovirus outbreaks between August and December 2023, a substantial rise from the previous year’s numbers.
While the term "quad-demic" may sound ominous, the seriousness and consequences of such infections should be weighed in light of the U.S. healthcare system's experience with managing viral surges since the start of the COVID-19 pandemic.
1. Influenza (Flu)
Flu continues to be one of the most common and alarming seasonal illnesses. In the period spanning from 2023 to 2024, there were approximately 40 million cases of flu, and thousands of hospitalizations along with reported 47 deaths have been reported this season. Flu symptoms include fever, chills, cough, sore throat, muscle pain, and fatigue, with most recovering within a week or two but risky factors for severe illness effects occur in young children, elderly, and people with chronic conditions.
2. Covid-19
Despite its reduction from the first pandemic peak, COVID-19 is still rampant. The CDC estimates that alone between October and December 2023, there were between 2.7 and 5 million cases in the U.S. Hospitalization has increased by cities such as Los Angeles, Chicago, and New York. Symptoms are closely similar to the flu, fever, cough, and fatigue but uniquely presents in some cases as loss of taste and smell.
3. RSV
RSV is the most common cause of lower respiratory infections in infants, older adults, and immunocompromised individuals. While RSV peaked late in 2023 and early 2024, it continues to be a threat because it can lead to bronchiolitis and pneumonia. It is very similar to the common cold, presenting with symptoms such as congestion, runny nose, coughing, and fever, which can make it difficult to differentiate from flu or COVID-19 without testing.
4. Norovirus
Norovirus, also called the "stomach flu," is a highly contagious infection of the gastrointestinal tract, not a respiratory virus. It transmits quickly from contaminated food and water and contact with contaminated surfaces, causing such symptoms as diarrhea, vomiting, nausea, and stomach pain. Cases have shot up, the CDC said Monday, with reports of outbreaks surging compared with last year.
Is There a Challenge In Diagnosis Due to Overlapping Symptoms?
The greatest challenge during the quad-demic is how the four viruses are alike and thus make identification very hard with no testing applied. Most cases present symptoms common to all viruses: fever, tiredness, body pains, and respiratory, which includes coughing and congestions for influenza, COVID-19, and RSV; the other would be norovirus symptoms as nausea and vomiting can appear even in extreme influenza and COVID-19. This overlap increases the risk of misdiagnosis and delayed treatment, hence the need for early testing and proper medical guidance.
Also Read: Is US Preparing For A Quad- demic 2025?
Effective Prevention Strategies That Work
The best defense against these viruses is a combination of vaccines, hygiene, and lifestyle precautions. While lifestyle modifications are highlighted as part of the constant need to eat healthy, ensure daily movement and drinking adequate amount of fluids. There is a sure short two preventive strategies that are effective:
Vaccination
- Flu vaccine: Annual flu shots reduce the severity of infection, allergic flare ups and hospitalizations.
- COVID-19 vaccine: Though COVID-19 cases have declined, vaccination remains critical in preventing severe outcomes.
- RSV vaccine: Available for those aged 60 years and older, especially those with underlying conditions.
- Norovirus vaccine: No vaccine is yet available, but mRNA vaccine research is in progress.
Hygiene and Sanitation
- Washing hands frequently with soap and water for at least 20 seconds, especially after public exposure.
- Disinfect frequently touched surfaces regularly, use sanitiser when outside.
- Avoid close contact with infected people and wear masks.
Do You Need To Wear A Mask All The Time?
While debates on masked wear continue on, experts on mask-wear affirm that this does not only have a historical precedent but works towards reducing airborne viruses spreading within the environments. Hospitals, though, ensure masking in key sections of themselves. Publicized mask-wear remains a discretion, though massing indoors still goes a longer way in cases like peak flu seasons.
If you notice the symptoms of these viruses, then it's best to be confined at home and avoid having face-to-face interaction with others and seek immediate attention from your physician if your condition worsens. Quarantining for some days can decrease the spread of infection.
As we move into the first half of 2025 and beyond, staying informed and proactive is the best strategy for maintaining health and avoiding unnecessary panic. The key takeaway? Stay vigilant, but don’t be alarmed—these viruses are here, but so are the means to fight them.
WHO Sets 2027 Flu Vaccine Strains; US States Can Now Order Free COVID Shots For Kids

Credit: iStock
The World Health Organization (WHO) today announced its recommendations for the viral composition of influenza (or “flu”) vaccines for the 2027 southern hemisphere influenza season.
The announcement comes as US states can now order free COVID-19 vaccines for eligible children through the federal Vaccines for Children (VFC) program, following a nearly month-long delay.
Why WHO Is Updating Flu Vaccine Strains
Seasonal influenza causes substantial illness and hospitalizations each year. Because influenza viruses continually evolve, vaccine compositions need to be regularly updated.
WHO recommendations guide national vaccine regulators and manufacturers in developing and licensing vaccines for the following flu season.
"For nearly 75 years, the WHO Global Influenza Surveillance and Response System has demonstrated the power of global solidarity in public health," said Dr Maria Van Kerkhove, WHO's Director for Epidemic and Pandemic Management.
"The commitment of countries and laboratories to share data, viruses and expertise enables WHO to make timely vaccine recommendations, strengthening our collective ability to detect and respond to emerging influenza threats. This is global public health collaboration at its best," she added.
Also read: Fall Vaccines 2026: US Doctors Issue COVID, Flu And RSV Jab Guidance
What Are The 2027 Flu Vaccine Strains?
From February through August 2026, influenza A(H1N1)pdm09, A(H3N2) and influenza B viruses circulated across regions. Influenza A viruses predominated in most regions, while influenza B dominated in Northern and Western Africa, North America and Eastern Asia.
WHO recommends the following strains for the 2027 southern hemisphere influenza season:
Egg-based vaccines
- A/Missouri/11/2025 (H1N1)pdm09-like virus
- A/Darwin/1454/2025 (H3N2)-like virus
- B/Tokyo/EIS13-175/2025 (B/Victoria lineage)-like virus
Cell culture-, recombinant protein- or nucleic acid-based vaccines
- A/Missouri/11/2025 (H1N1)pdm09-like virus
- A/Darwin/1415/2025 (H3N2)-like virus
- B/Pennsylvania/14/2025 (B/Victoria lineage)-like virus
WHO also reviewed influenza viruses circulating in animals because of their potential to cause human infections and pandemics.
Free COVID Vaccines For US Children
Read More: COVID-19 Rising In 35 US States: Sore Throat, Diarrhea Among Key Symptoms
The VFC program provides free immunizations to more than half of U.S. children, including those covered by Medicaid, uninsured or underinsured children, and Native Americans and Alaska Natives.
The FDA approved the updated COVID-19 vaccines on August 27, but access through the VFC program was delayed.
Although overall COVID-19 hospitalization rates remain low, they have been rising since mid-June. According to the CDC, hospitalization rates are highest among babies younger than 1 year old and adults aged 65 and older.
States Can Now Order COVID Vaccines
Public health officials from multiple states confirmed that they can now order the free vaccines.
South Carolina’s health department “was alerted yesterday afternoon by the CDC that COVID vaccines would be available for order today,” Casey White, a department spokeswoman, told CIDRAP News.
“Announcements will be shared with VFC providers and health departments to communicate the opening of ordering for all respiratory immunizations.”
WHO said it will issue its recommendation for vaccines for the 2027–28 northern hemisphere influenza season in February 2027.
New York Assisted Suicide Law: Nearly 20 People Reportedly Died Since August
Credit: iStock
Nearly 20 prescriptions for life-ending medication were reportedly issued in New York during the first month of its Medical Aid in Dying (MAiD) law, according to a Columbia University bioethics expert.
However, state health officials have not yet released data showing how many patients actually used the medication.
New York’s Medical Aid in Dying Act took effect on August 5, making it the 14th US state to legalize medical aid in dying.
David Hoffman, assistant professor of professional practice in bioethics at Columbia University, told The New York Post that conversations with doctors, hospitals and organizations indicated that about 20 prescriptions had been issued since the law took effect.
“The state will have the data on a rolling basis. It’s an after-the-fact analysis,” Hoffman told The Post.
The New York State Department of Health has yet to release precise figures on the program’s use.
New York Assisted Suicide Law: Why Is It Controversial?
Read More: Supreme Court Allows 1st Passive Euthanasia For Man In Vegetative State For 13 Years
The lack of publicly available data has drawn criticism from lawmakers who opposed the law. Upstate Republican Assemblyman Andrew Molitor told The New York Sun that New Yorkers should know how many people have requested and used medical aid in dying.
He said information should include patients’ socioeconomic status, insurance coverage, terminal condition, when prescriptions were filled and where the medication was administered.
Western New York Republican state Sen. George Borrello also criticized the wait for the state’s first annual report.
Critics have additionally raised concerns about whether the law could eventually be expanded. Borrello pointed to Canada, where medical assistance in dying was legalized in 2016.
Medical aid in dying remains controversial because it raises ethical, religious and moral questions. Critics warn about the potential coercion of vulnerable patients, while supporters emphasize personal autonomy and relief from prolonged, incurable suffering.
Medical aid in dying generally involves a patient voluntarily taking lethal medication prescribed by a doctor. Euthanasia, by contrast, involves a healthcare professional administering the lethal medication at the patient’s request.
Who Can Qualify For Medical Aid In Dying In New York?
Under New York’s law, patients must:
- Be at least 18 years old.
- Be a New York resident.
- Have a terminal illness with six months or less to live.
- Have the capacity to make an informed healthcare decision.
- Be physically capable of self-administering the medication.
- Receive approval from two physicians.
- Undergo a psychiatric evaluation when required to assess decision-making capacity.
- Make an oral request and provide an audio or video recording of that request.
The law also requires a five-day waiting period between obtaining and dispensing the prescription.
Medical aid in dying requires the patient to take the prescribed medication themselves. This differs from euthanasia, in which a healthcare professional administers the life-ending medication.
How Will New York Track The Program?
Also read: Can Right To Die Be Practiced By Non-Terminally Ill Patients?
The law requires the state health commissioner to submit an annual report to the Legislature detailing the program’s use.
Hoffman noted that doctors report when medication is prescribed, but the state may not immediately know whether a patient ultimately takes it.
A New York State Department of Health spokesperson told The Post that the department will publish an annual report with utilization data as required by law.
Health Commissioner Dr. James McDonald said end-of-life decisions are “deeply personal” and should be made individually in consultation with patients, doctors, families and loved ones. The department has also issued guidance and proposed regulations intended to prevent misuse or inappropriate application of the law.
Assisted-Dying Laws In Other Countries
The debate over medical aid in dying extends beyond New York and the US.
France’s National Assembly recently gave final approval to a bill that would allow certain adults with incurable illnesses to receive lethal medication, following years of debate over end-of-life care.
Assisted-dying legislation is also being debated in the UK, where a bill covering England and Wales is returning to Parliament.
Thyroid Medicine Recall Gets US FDA’s Highest Risk Rating: What To Know
Credit: FDA/iStock
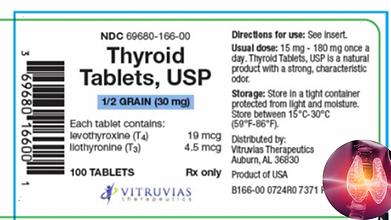
Vitruvias Therapeutics’ thyroid medication, recalled nationwide in August, has been elevated to the highest risk level by the US FDA.
The recall was issued because the medication may be superpotent, potentially causing hyperthyroidism (overactive thyroid).
On Wednesday, the FDA updated the recall to Class I, its most serious recall classification. It applies when there is a “reasonable probability that the use of or exposure to a violative product will cause serious adverse health consequences or death.”
Which Thyroid Tablets Have Been Recalled?
Also read: US Cancer Death Rates Fall For Men, Women: Lung Cancer Progress Drives Decline
The affected product is:
- Vitruvias Thyroid Tablets USP 30 mg
- Lot number: 504950
- Expiration date: September 30, 2026
In its August 24 recall notice, the company said the tablets were potentially superpotent.
Risks of Superpotent Thyroid Medicines
Millions of people with hypothyroidism rely on thyroid tablets every day to replace hormones their bodies cannot produce.
However, taking superpotent thyroid tablets can cause hyperthyroidism (overactive thyroid). It can force the body's metabolism into overdrive, speeding up organs and bodily functions.
Left untreated, this constant strain can cause serious health complications across multiple systems in the body.
In addition, people taking the medication can be at risk of
- weight loss,
- heat intolerance,
- fatigue,
- nervousness,
- muscle weakness,
- hypertension,
- chest pain,
- rapid heart rate,
- heart rhythm disturbances.
The lot was distributed nationwide in the US to Vitruvias Therapeutics’ direct accounts between January 31 and September 30, 2025. Of 3,655 units released, 1,955 were sold.
Read More: FDA Recalls Popular Thyroid Medication: What Levothyroxine Users Need to Know
Who Is At Greater Risk?
The company identified the following groups as being at greater risk from superpotent thyroid tablets:
- Elderly people
- Pregnant women
- Infants
Excess thyroid hormones in older adults have been associated with adverse outcomes, particularly those affecting the heart.
Vitruvias Therapeutics said it has not received any reports of adverse events known to be linked to the recall.
The company is notifying wholesalers to stop distributing the recalled product and arranging for its destruction.
What Should Patients Do?
Patients taking Thyroid, USP from Lot 504950 should not stop taking it without first contacting their healthcare provider for guidance and/or a replacement prescription.
Hypothyroidism vs Hyperthyroidism
Speaking to HealthandMe, Dr Shruti Kotangale, Consultant Gynaecologist, Obstetrician and Infertility Expert at AIMS Hospital, Dombivli, explained that both conditions are commonly seen in women.
Hypothyroidism occurs when the thyroid is underactive. Symptoms can include tiredness, weight gain, dry skin, hair fall, constipation, feeling cold, a slow heartbeat and low mood or depression.
Hyperthyroidism occurs when the thyroid is overactive. Symptoms may include weight loss, a fast heartbeat, sweating, anxiety, tremors, irritability, frequent bowel movements and difficulty sleeping.
Women should seek medical attention and manage these symptoms without delay.
Common Symptoms Of Thyroid Disorders
Thyroid disorders may cause a range of symptoms, including:
- Fatigue
- Cognitive changes
- Gastrointestinal problems
- Sensitivity to cold
- Skin and hair changes
- Weight changes
How Is Thyroid Disease Diagnosed?
Diagnosis may involve:
- Physical examination: To check for swelling or nodules in the neck.
- Blood tests: These may measure TSH, T4 and T3 levels, along with thyroid antibodies when conditions such as Hashimoto’s disease or Graves’ disease are suspected.
- Ultrasound or thyroid scans may also be used to assess the thyroid’s structure.
- Follow Us :


© $2026 Times Horizon Private Limited