
- Health Conditions A-Z
- Health & Wellness
- Nutrition
- Fitness
- Health News
- Ayurveda
- Videos
- Medicine A-Z
- Parenting
Having Trouble Quitting Smoking? Cigarettes With Low Nicotine Levels Could Be The Solution

Cigarettes with ultralow nicotine levels are now being called the game-changer in the fight against smoking. If you are having trouble in quitting smoking, then, it is for you, that soon the Biden White House is expected to formally propose a plan that will order cigarette nicotine levels to be reduced, reports The Washington Post. For now though, it has been a failure, as these cigarettes, also known as VLN cigarettes that stands for very low nicotine are only available in 5,100 stores in 26 states. This is a very small fraction of the overall market for cigarettes. The company that makes it, 22nd Century, is struggling not because of the low supply, but also from the advocates who have long believed slashing nicotine levels altogether.
The Advent and ideation
Nicotine is a chemical that is produced naturally from tobacco that makes the cigarette and also keeps people hooked. While it is believed that it makes people alert, and get the "hit" to keep them going, it exposes the users to harmful substances, carcinogens, and increases the risk of heart disease, lung cancer, and other illness.
Ultralow-nicotine cigarettes, like the VLN brand, contain about 95% less nicotine than the regular cigarettes. The idea is quite simple: without the addictive grip of nicotine, smokers will find it easier to quit. Research too has shown some promise. For instance, the studies funded by the National Institute on Drug Abuse revealed that very low nicotine cigarettes reduced addiction potential significantly without having users to increase their smoking frequency. However, the problem is, why would anyone choose for a low-nicotine that does not make them feel the same way, when the high-nicotine cigarette is right next to it, making them feel the same way, with the same alertness, sold at the same price.
“It’s very hard to imagine someone actively choosing to continue to use a low-nicotine product for the same price when a high-nicotine product is right next to it,” said Eric Donny, a Wake Forest University School of Medicine nicotine researcher.
No wonder, the experiment with low nicotine product by Philip Morris' Next cigarettes in the 1980s and Vector Tobacco's Quest brand in the early 2000s, flopped.
FDA's Role in the Push
The Food and Drug Administration (FDA) has supported the development of such products, even allowing VLN cigarettes to be marketed as lower-risk options. However, these products remain a niche market, available in only a fraction of U.S. stores.
Recently, the Biden administration has considered a bold step—mandating a dramatic reduction in nicotine levels for all cigarettes sold in the United States. Supporters believe this move could save millions of lives, while critics, including tobacco companies, warn of potential unintended consequences.
What Could Be The Challenges?
Resistance from Big Tobacco Companies: They could argue that slashing nicotine levels could backfire. Their claim is, smokers will turn to black markets or smoke more to satisfy their cravings, which may lead to greater exposure to harmful substances.
Consumer Reluctance: History is proof to the instances of smokers being hesitant to embrace the low-nicotine products.
Political Hurdle: It may face political roadblocks, as under the Trump administration, plans to cut nicotine were shelved.
Could Low-Nicotine Cigarettes Be The Solution?
Advocates believe that ultralow-nicotine cigarettes could be a game-changer, comparing them to decaf coffee or non-alcoholic beer—products that reduce harm while offering a similar experience.
Some experts warn that a black market for traditional cigarettes could undermine these efforts. They also stress the need for safer alternatives, such as vaping products, to support smokers transitioning away from traditional cigarettes.
World's First Patient Receives Pioneering Stem Cell Treatment For Parkinson's In Japan
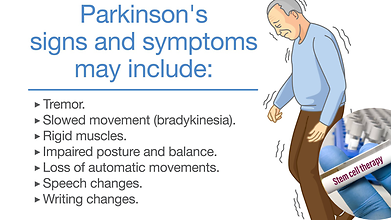
Credit: iStock
A patient has received a pioneering stem cell treatment for Parkinson's disease in Japan, marking a world first following the therapy's conditional approval in the country.
Developed by Japanese drugmaker Sumitomo Pharma in collaboration with Dr Jun Takahashi at Kyoto University, the therapy, Amchepry (also known as raguneprocel), is the world's first induced pluripotent stem cell (iPSC)-based treatment for Parkinson's disease. It received conditional approval in March 2026 following successful clinical trial results.
The first transplant was performed at Kyoto University Hospital in October, the company said on Friday in an earnings press release, without providing further details, AFP reported.
How Does the Parkinson's Stem Cell Treatment Work?
Also read: Parkinson’s at 40: Why Younger Adults Are Being Diagnosed Earlier Than Before
The treatment uses iPSCs obtained from healthy donors, which are developed into precursors of dopamine-producing neurons and transplanted into the brain to replace cells lost due to Parkinson's disease.
iPSCs are created by reprogramming mature, specialised cells to return to an earlier state, allowing them to develop into different cell types.
Stem cell therapy, also known as regenerative medicine, uses stem cells or their derivatives to repair or replace damaged tissues.
What Did the Clinical Trial Find?
During the clinical trial, seven patients aged between 50 and 69 received implants of either five million or 10 million cells on both sides of the brain.
The patients were monitored for two years. Researchers found no major adverse effects, while four participants showed improvements in their symptoms, AFP reported.
Sumitomo Pharma said it plans to perform transplants in 20 to 30 patients by March 2029. The company is also conducting a clinical trial of the treatment in the United States.
The therapy will receive full approval in Japan if its safety and effectiveness are confirmed over the next seven years, according to local media reports.
Read More: Parkinson’s Disease: Women Have More Motor Complications, Depression
Japan Also Approves Stem Cell Therapy for Heart Failure
The announcement comes a month after a hospital in Osaka performed the world's first surgery using sheets of heart muscle cells derived from iPSCs.
The sheets are designed to promote new blood vessel formation and help restore heart function. The treatment also received conditional approval in Japan in March.
Conditional approval allows these therapies to be used clinically while additional data on their safety and effectiveness are collected.
What Is Parkinson's Disease?
Parkinson's disease is a progressive neurodegenerative disorder caused by the loss of dopamine-producing brain cells. It primarily affects people over the age of 60 and is estimated to affect more than 10 million people worldwide, according to the Parkinson's Foundation.
Dopamine plays an important role in controlling movement. Its loss can cause symptoms such as:
- Tremors, often beginning in one hand, foot or the jaw.
- Muscle stiffness and slowed movement.
- Difficulty maintaining balance, increasing the risk of falls.
- Changes in speech, including softer or slurred speech.
- Difficulty swallowing.
The disease can also cause cognitive decline, depression and anxiety. Currently available treatments help manage symptoms but do not stop or reverse disease progression, according to the Parkinson's Foundation.
Baby Formula Nutrition: US FDA Proposes Changes to Vitamins A, D, Iodine and Manganese – What Parents Must Know

Credit: iStock
For the first time in nearly three decades, the US Food and Drug Administration (FDA) is proposing changes to nutrient requirements for infant formula. The proposed changes cover vitamins A and D, iodine and manganese under the Trump administration's Operation Stork Speed initiative, announced in March 2025.
The FDA’s first phase of a three-phase review covers eight of the 30 nutrients required in infant formula. It proposes revising requirements for four nutrients and reaffirming existing limits for the other four. It is also seeking public input on nutrients commonly added by manufacturers but not currently required. The agency is accepting comments for 120 days.
“Parents deserve confidence in every bottle they feed their baby,” US Health and Human Services Secretary Robert F. Kennedy Jr. said in a statement.
What Are The Proposed Changes?
Also read: Major FDA Study Confirms Baby Formula In US Safe, Testing to Continue
The FDA's first phase covers eight nutrients. It proposes changes to four and retaining existing limits for the other four.
1. Iodine
- Minimum: Increased from 5 to 15 µg/100 kcal.
- Maximum: Reduced from 75 to 50 µg/100 kcal.
2. Manganese
- Minimum: Reduced from 5 to 1 µg/100 kcal.
- Maximum: A new limit of 50 µg/100 kcal.
3. Vitamin A
- Measurement unit changed from IU to micrograms of retinol activity equivalents (µg RAE).
- Minimum: Reduced from 250 IU (75 µg RAE) to 70 µg RAE/100 kcal.
- Maximum: Reduced from 750 IU (225 µg RAE) to 120 µg RAE/100 kcal.
- Only preformed vitamin A, not beta-carotene, will count towards the limits.
4. Vitamin D
- Measurement unit changed from IU to micrograms (µg).
- Minimum: Increased from 40 IU (1 µg) to 2 µg (80 IU)/100 kcal.
- Maximum: Increased from 100 IU (2.5 µg) to 3 µg (120 IU)/100 kcal.
The FDA also proposes updating formula labelling requirements to reflect the changes.
Which Nutrient Limits Will Remain Unchanged?
Read More: New International Food Pyramid Highlights Plant Foods, Counters Trump’s Meat-Heavy Diet Advice
The FDA proposes retaining existing levels for:
- Chloride: 55–150 mg/100 kcal.
- Potassium: 80–200 mg/100 kcal.
- Selenium: 2–7 µg/100 kcal.
- Sodium: 20–60 mg/100 kcal.
What Do Parents Need To Know?
The FDA says formulas currently sold in the US remain safe for babies. The proposed changes are not prompted by safety concerns but aim to align standards with current scientific evidence.
Parents do not need to change the formula they currently use.
When Will The Changes Take Effect?
The FDA is reviewing all 30 nutrients in three phases. The first covers eight, with the remaining 22 to follow.
The final rule will take effect 60 days after publication in the Federal Register. Manufacturers will have three years from that date to reformulate and relabel their products.
This means the proposed changes will not appear on formula packaging immediately.
Dr Steven Abrams, a paediatrician and professor at the University of Texas' Dell Medical School, called the update overdue. He described the first phase as “really well done” and “very well thought-out”, CNN reported.
However, he said the phased approach means manufacturers could take several years to implement the changes.
“These changes that they're recommending today are not going to be something that'll show up on the can of formula potentially for several years,” Abrams said.
He identified the proposed vitamin D increase as the most consequential change in this phase.
Meanwhile, the FDA is also seeking input on making commonly added nutrients such as DHA, ARA and L-carnitine mandatory. These are not currently required in infant formula.
Ebola 2026 Outbreak: Death Toll Nears 5,000; Kenya, Nigeria Cases Linked to Congo
Credit: iStock
The Ebola outbreak in the Democratic Republic of Congo (DRC), officially declared a Public Health Emergency in May 2026, has surpassed 10,000 cases and is approaching 5,000 deaths, making it the fastest-growing Ebola outbreak in history.
Driven by the Bundibugyo Ebola virus, the outbreak has spread beyond the DRC to Uganda, Kenya and Nigeria, raising concerns about cross-border transmission. There is currently no licensed vaccine against this strain, although candidates are in development.
More than 1,000 children have died, accounting for over one-quarter of recorded fatalities, according to Save the Children.
“It's extraordinarily serious. Over 1,000 children have died of Ebola,” Greg Ramm, Save the Children's Country Director in the DRC, told the media.
“The world needs to start paying attention. We will break 15,000 deaths by the new year. And just because Ebola isn’t going to become a pandemic doesn’t mean it is not a global health security threat as well as a humanitarian disaster,” Dr Angela Rasmussen, a virologist, warned in a post on X.
Africa CDC Warns of Wider Global Risk
Africa CDC Director-General Dr Jean Kaseya has warned that the outbreak's unprecedented geographical spread could put countries beyond Africa, including the UK, at risk.
“The geographic extension of this outbreak is unprecedented,” he said, noting that three African regions had been affected. Drawing parallels with COVID-19, he warned: “We don’t want to see the UK and other countries become the hotspot,” The Guardian reported.
In response, the UK Health Security Agency's (UKHSA) Dr Sam Collins stressed that the risk to the UK remains low and that the country “is well prepared to respond safely and effectively to the risk of imported cases arising here”.
Genetic Analysis Links Kenya, Nigeria Cases to Congo
Scientists have linked Ebola viruses detected in Kenya and Nigeria to those circulating in Beni, eastern DRC, raising questions about a possible shared transmission chain or an unidentified source, Bloomberg reported.
“Genomic sequencing shows that the Ebola virus from Nigeria’s recently reported only imported case is highly similar to that from Kenya’s first imported case, differing by only one mutation,” Muhammad Ali Pate, Nigeria's Coordinating Minister of Health and Social Welfare, said in a post on X.
How Was The Genetic Analysis Conducted?
Scientists from four countries, led by Congolese virologist Jean-Jacques Muyembe, analysed 1,126 viral genomes after an Ebola case was detected in Abuja, Nigeria.
The Beni samples share a distinctive genetic signature, including a mutation absent from other sequenced viruses from Congo.
The viruses also lack genetic markers associated with Uganda's documented Ebola transmission chains from May and June, suggesting they did not descend from those previously identified outbreaks.
Researchers have yet to establish where the patients contracted the virus or whether they were infected through the same transmission chain. Genetic sequencing alone cannot prove direct transmission.
Travel Histories Point To Possible Congo Uganda Connection
Investigators are examining the patients' movements through Uganda during their potential exposure periods.
The Nigerian patient was in Uganda from September 15 to October 3 and developed symptoms three days after returning to Abuja. The Kenyan patient travelled from Congo through Uganda between October 1 and 3 before flying to Nairobi from Entebbe.
Both patients reportedly travelled on flights on October 3. Authorities are checking their travel records for possible overlap and tracing potentially exposed passengers.
Nigeria, Kenya Step Up Ebola Response
Nigeria has traced 62 contacts of the infected woman, NCDC Director-General Jide Idris said. Of these, 50 are in isolation, five are being monitored at home and seven remain unlocated.
Uganda recorded 20 confirmed cases and two deaths before declaring the outbreak over in June.
Kenya has reported nine cases and two deaths. Seven patients, including three family members and four healthcare workers, are receiving treatment and responding well. Authorities have traced all 135 contacts linked to the first case, according to official data.
- Follow Us :


© $2026 Times Horizon Private Limited