
- Health Conditions A-Z
- Health & Wellness
- Nutrition
- Fitness
- Health News
- Ayurveda
- Videos
- Medicine A-Z
- Parenting
Five Common Symptoms Of Stomach Cancer That Should Not Be Ignored
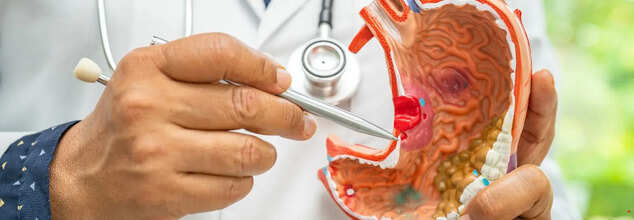
Stomach cancer (credit: canva)
Stomach cancer is a type of cancer that develops in the lining of the stomach. Also, known as Gastric cancer, it affects the elderly more than the adult. According to the American Cancer Society, about 6 of every 10 people diagnosed with stomach cancer each year are 65 or older. Also, the lifetime risk of developing stomach cancer is higher in men (about 1 in 101) than in women (about 1 in 155).
A health expert, speaking to a leading media house, emphasized five common symptoms of stomach cancer that should not be ignored:
1. Unexplained weight loss: Losing weight without trying or experiencing an unexplained drop in appetite, which may signal cancer progression.
2. Pain in the upper part of the abdomen: Persistent or occasional pain in the stomach area, often after eating, can become more severe as the condition progresses.
3. Frequent vomiting after meals: Nausea, sometimes accompanied by vomiting, may occur especially after meals and is linked to cancer blocking or irritating the stomach.
4. Vomiting blood, which may appear coffee-colored: This can indicate bleeding in the stomach, often caused by ulcers or tumors, and requires immediate medical attention.
5. Black, tarry stools: This occurs when blood from the stomach is digested and passed through the intestines, signaling potential internal bleeding
There are also other concerning signs that should not be overlooked such as jaundice, unexplained weight loss, early onset of diabetes, dark stools, and loss of appetite. Health experts strongly advise seeking immediate medical attention if you notice any of these symptoms. If you or a loved one experience these signs, it's crucial to visit a physician for a thorough evaluation to rule out serious underlying health conditions.
How Does Stomach Cancer Spread?
Oncologist Dr Pankaj Kumar Pande, Director–Surgical Oncology, Max Super Specialty Hospital, Shalimar Bagh, Delhi explained that this form of cancer spreads through three main pathways: Direct spread, lymphatic spread, and bloodstream.
1. Direct Spread: In its early stages, stomach cancer can invade nearby tissues and grow into the deeper layers of the stomach or spread to surrounding organs such as the oesophagus, liver, pancreas, or intestines.
2. Lymphatic Spread: Cancer cells can travel through the lymphatic system. The most common areas affected are the regional lymph nodes near the stomach, particularly those around the liver and diaphragm.
3. Bloodstream: "Cancer cells can enter the bloodstream and travel to distant parts of the body," which is a common route for stomach cancer to metastasize to distant organs.
He further explained that cancerous cells spread from the original tumour to other parts of the body through a process called Metastasis. The most common sites for the spread are the liver, lymph nodes, peritoneum, lungs, bones, and ovaries.
Trials For Deadly Childhood Brain Cancer Stalled After Trump Administration Shuts Down 27-Year Research Consortium

Credit: AI-generated image
Clinical trials investigating experimental treatments for rare, aggressive childhood brain cancers have been disrupted after the closure of a US research consortium that was in operation for 27 years.
The shutdown of the Pediatric Brain Tumor Consortium (PBTC), after the National Cancer Institute (NCI) declined to renew its funding, has caused significant delays and rendered desperate families searching for alternative treatment options.
The consortium was composed of 16 leading children's hospitals and academic medical centres across the US, aiming to investigate new treatments for aggressive brain tumours, including diffuse intrinsic pontine glioma (DIPG) and ependymoma.
The NCI informed consortium leaders about the decision in August 2025, ending its approximately $4 million annual grant. Eight ongoing clinical trials were subsequently halted, according to The New York Times.
The consortium formally dissolved in September 2026. Researchers say the disruption has affected not only ongoing studies but also the infrastructure and resources needed to develop new treatments for childhood brain cancers.
DIPG Is One Of The Most Aggressive Childhood Brain Cancers
Also read: Losing Balance While Walking? Doctors Explain When It Could Be A Neurological Warning Sign
DIPG is a rare, aggressive brain tumour that usually affects children between four and 10 years of age. It develops in the pons, a part of the brainstem which is responsible for essential functions like breathing, heart rate, coordination and balance.
Since the tumour grows within critical brain tissue and spreads through the brainstem, it cannot be removed through surgery. Clinicians describe it “like sand in grass”.
Radiation therapy is commonly used to fight the tumour but its benefits are temporary. There is currently no established treatment. The average survival after diagnosis is approximately nine to 12 months.
With limited treatment options, clinical trials investigating experimental therapies are a need of the hour for children suffering from DIPG.
Research And Clinical Trials That Were Affected Due To Funding Closure
Also read: AIIMS Delhi Performs India's First Open Fetal Surgery To Repair Spina Bifida
The closure disrupted several studies exploring experimental treatments for childhood brain tumours.
One of the affected studies, PBTC-059, was a Phase 1 trial investigating CAR-T cell therapy in children with ependymoma. CAR-T therapy entails modifying a patient's immune cells to identify and attack cancer cells.
Another study, PBTC-N14, was discontinued too. Researchers at Memorial Sloan Kettering Cancer Center were investigating whether cerebrospinal fluid samples could provide genetic information similar to that obtained through an invasive brain biopsy, reducing the need for surgery in some children.
Researchers were also exploring other experimental options for DIPG, including cancer vaccines and devices that can deliver electrical stimulation to the brain.
According to the NCI's updated information, some paused trials are expected to reopen to patient enrolment in late 2026 or early 2027. But the interruption has created a significant gap and delay for families who were previously able to access these trials.
27 Years Of Research Data At Stake
The consequences of the consortium's closure extend well beyond clinical trial enrolment and patient welfare. At St. Jude Children's Research Hospital, 27 years of research data involving more than 2,000 children with rare brain tumours had to be archived.
Hundreds of biological samples, including tumour tissue, blood and spinal fluid collected from patients, also had to be returned to hospitals or destroyed if they could not be retained.
Researchers have raised concerns that losing the consortium's dedicated infrastructure and centralised data-access system could make it harder for scientists to resume these studies and build on previous findings.
Ira Dunkel, a paediatric oncologist at Memorial Sloan Kettering Cancer Center and former chair of the consortium, described the closure as “catastrophic” and one of the worst professional moments of his career.
Why Did The US Government Shut Down PBTC?
The NCI said the decision was taken to improve efficiency by moving the consortium's data into the larger Pediatric Early Phase Clinical Trials Network. The institute also said enrolment in some consortium studies had slowed.
But researchers argued that the smaller patient populations and the highly targeted nature of experimental treatments make specialised research areas particularly important.
After the decision, NCI announced that approximately $4 million would be allocated to the larger network to strengthen paediatric brain tumour research and accelerate Phase 1 clinical trials.
The $4 million grant also seemed insufficient compared to the $732 million that the NIH spends annually on childhood cancer. But according to Dunkel, it was “hugely important”.
But researchers and patient support groups have questioned whether the larger network can immediately and effectively replace the consortium's specialised expertise, proven collaborations and research infrastructure.
A bipartisan group of lawmakers from New York called wrote to Health and Human Services Secretary Robert F. Kennedy Jr., urging to reverse the decision. “We cannot afford to take this step backward,” the group said.
Families dealing with aggressive childhood brain cancers are helpless in the light of consortium closure. With some children having less than a year after diagnosis, such setbacks mean losing access to potentially life-saving or extending experimental treatment opportunities that may not become available again in time.
India Moves Into The Trajectory Of Developed World, Doubles Social Security Expenditure In A Decade

Credit: AI Image
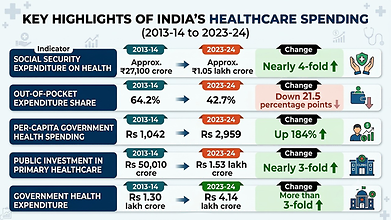
India’s social security expenditure on health nearly doubled as a share of Total Health Expenditure, rising from 6% in 2013–14 to 11% in 2023–24, according to the Union Health Ministry. The spending, estimated to have crossed Rs 1 lakh crore, aims to protect individuals and families against the financial risks associated with medical treatment.
This growth has been led by whopping contributions of the government's flagship health insurance schemes such as Ayushman Bharat – Pradhan Mantri Jan Arogya Yojana (AB PM-JAY), state-specific health insurance schemes, social health insurance and medical expenditure for government employees.
Private health insurance expenditure also increased, rising from 3.4% of Total Health Expenditure in 2013-14 to 10.2% in 2023-24.
Government Health Expenditure Triples In A Decade
Also read: Ayushman Bharat Turns 8: PM Modi Highlights Record Savings On Medical Expenses
According to the National Health Accounts (NHA) Estimates for India 2023-24, released by the Ministry of Health and Family Welfare, India’s government health expenditure nearly tripled over the past decade, increasing from Rs 1,29,778 crore in 2013-14 to Rs 4,14,196 crore in 2023-24.
The government’s share of Total Health Expenditure (THE) increased by 14.9 percentage points over the decade, representing a rise of nearly 52%.
The report also highlighted an increase in per-capita government health expenditure and a decline in households’ out-of-pocket spending on healthcare.
“A healthier India. Lower financial burden. Stronger healthcare for all!” Union Health Minister JP Nadda said in a post on X while sharing the data.
"The National Health Accounts 2023–24 tell a powerful story of India’s healthcare transformation over the last decade," he added.
Per-Capita Government Health Spending Rises 184% In A Decade
Per-capita government health expenditure increased by 184% over the decade, nearly tripling from Rs 1,042 in 2013-14 to Rs 2,959 in 2023-24.
Spending crossed Rs 2,000 in 2019-20, reaching Rs 2,014, and rose further to Rs 2,328 in 2020-21.
The highest per-capita expenditure was recorded in 2021-22 at Rs 3,169, driven by emergency COVID-19 spending. It subsequently declined by 12.1% to Rs 2,786 in 2022-23 before increasing by 6.2% to Rs 2,959 in 2023-24.
The year-on-year growth rate peaked at 36.1% in 2021-22. Among the years that recorded an increase, the lowest growth was 6.2% in 2023-24.
“These are not just numbers. They reflect a decade of sustained efforts to make quality healthcare more affordable,” Nadda said.
He attributed the progress to initiatives such as Ayushman Bharat and Ayushman Arogya Mandirs under Prime Minister Narendra Modi. He also highlighted expanded access to free medicines and diagnostics as part of efforts to strengthen healthcare delivery.
"Our commitment is simple: No family should have to choose between its health and its financial well-being. A Swasth Bharat is the foundation of a Viksit Bharat!" Nadda said.
Public Investment In Primary Healthcare Triples
Public investment in primary healthcare also nearly tripled over the decade, rising from Rs 50,010 crore in 2013-14 to Rs 1,52,771 crore in 2023-24, according to the NHA estimates.
Out-Of-Pocket Health Expenditure Falls
Read More: India Digitalizes Health Records Of 100 Crore People Under Ayushman Bharat
The share of out-of-pocket expenditure (OOPE) in Total Health Expenditure declined from 64.2% in 2013-14 to 42.7% in 2023-24, a drop of 21.5 percentage points.
This indicates that households are paying a smaller share of overall healthcare costs directly, while other financing sources, including government spending and health insurance, account for a larger share.
Government Initiatives Expanding Access To Affordable Healthcare
The Ministry also highlighted several initiatives aimed at improving access to affordable healthcare across the country. These include:
- Free Drugs and Diagnostics Initiatives
- Pradhan Mantri National Dialysis Programme
- Pradhan Mantri Bhartiya Janaushadhi Pariyojana
- Affordable Medicines and Reliable Implants for Treatment (AMRIT) pharmacies.
'Viagra For The Brain': New Pill Slows Decline in Memory, Thinking By 31% In Some Alzheimer's Patients
Credit: iStock
A new once-daily experimental pill slowed the decline in memory, thinking, and everyday functioning by 31% in some people with Alzheimer's disease in a Phase 3 trial.
Developed by South Korean pharmaceutical company AriBio, the drug, AR1001 (mirodenafil), slowed disease progression by the equivalent of 3.5 months over one year.
Unlike existing dementia drugs, which primarily alleviate symptoms, AR1001 has shown potential to slow disease progression.
However, the benefit was significant only among patients who were not taking other dementia medications.
The company announced that "the trial had met its primary endpoint" at the Clinical Trials on Alzheimer's Disease (CTAD) conference in Boston, US.
What Did The Phase 3 Trial Find?
Also read: Normal Ageing or Alzheimer's? Doctors Explain Six Key Differences to Watch For
The global trial involved 1,535 people with Alzheimer's disease across 230 sites in 13 countries.
Researchers assessed participants using the Clinical Dementia Rating–Sum of Boxes (CDR-SB), which measures memory, judgment and the ability to perform everyday activities.
The findings showed:
- 31% slower decline: Among 604 patients taking AR1001 without other dementia medications, disease progression was 31% slower than in the placebo group.
- 3.5-month delay: The difference was equivalent to delaying disease progression by approximately 3.5 months over one year.
- No significant benefit in the overall group: Among all 1,535 participants, the benefit was 7% and was not statistically significant.
The findings suggest that AR1001's effectiveness may depend on whether patients are taking other Alzheimer's medications.
Dr Richard Oakley, Associate Director for Research and Innovation at Alzheimer's Society, described the results as encouraging.
"These topline results are an encouraging sign that we could have a new treatment for early Alzheimer's disease that tackles its causes, not just its symptoms," Dr Richard said, the Daily Mail reported.
"Over the year of the trial, the drug was able to slow down people's decline in memory and thinking by nearly a third," he added.
Why Is AR1001 Being Called 'Viagra For The Brain'?
Read More: India Gets Its First Alzheimer’s Drug: Know All About Eli Lilly’s Lormalzi
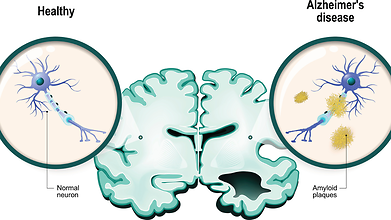
AR1001 works differently from existing Alzheimer's treatments, such as lecanemab and donanemab, which target amyloid plaques in the brain.
Its active ingredient, mirodenafil, belongs to the same class of drugs as sildenafil, the compound used in Viagra to treat erectile dysfunction.
Both drugs inhibit an enzyme called phosphodiesterase-5 (PDE5). This helps relax blood vessels and improve blood flow.
Researchers believe AR1001 may have several effects in the brain, including:
- Improving blood flow.
- Reducing inflammation.
- Protecting nerve cells.
- Supporting cellular processes involved in brain function.
Unlike some existing disease-modifying treatments that require infusions or injections, AR1001 is designed as a once-daily oral medication.
However, the drug is from the same family of medicines as Viagra and is being developed specifically for Alzheimer's disease. People should not take Viagra to try to treat Alzheimer's.
Are there Any Side Effects?
Most side effects reported during the trial were mild to moderate. Common side effects included diarrhoea, falls and dizziness.
Severe adverse events occurred in 10% of the treatment group and 9.8% of the placebo group.
Researchers also reported changes in biomarkers associated with Alzheimer's disease. Levels of the protein p-tau217 decreased in the monotherapy group, while cerebrospinal fluid cGMP levels increased in both treatment groups.
These findings offer clues about the drug's biological activity, although further research is needed to establish its effects.
However, the lack of a statistically significant benefit among people taking other Alzheimer's medications, adding that this required further investigation.
AR1001 is not yet available to the public and must undergo regulatory assessment before it can be prescribed.
Regulatory approval will depend on further evaluation, including whether the FDA considers the monotherapy results sufficient to support the drug's approval.
- Follow Us :


© $2026 Times Horizon Private Limited