
- Health Conditions A-Z
- Health & Wellness
- Nutrition
- Fitness
- Health News
- Ayurveda
- Videos
- Medicine A-Z
- Parenting
FDA Has Approved A New Medication Treatment For Migraines In Adults

(Credit-Canva)
Headaches are a common symptom of a stressful lifestyle, your body not feeling well and other issues. While headaches can be dealt with easily, migraines are not so easy to handle. Migraines are a type of headache that feels like severe throbbing and pulsing sensation, almost like you are hearing your own heartbeat in your brain, usually on one side of the brain. Many people believe that migraines are not that big of a deal because you just have to deal with the pain, but that is not all migraine is, some people find it very difficult to do their daily tasks as they experience dizzying spells, nausea and extreme sensitivity to light and sound! These attacks can last hours and make it difficult for people to go about their daily lives as well. While there are medications available for migraine patients, these medications need time to take effect, so you may be in a lot of pain, but there are not many quick reliefs you can have in place other than learning the symptoms of a migraine attack and taking medication before it happens. But a new approval by the FDA may change this!
The U.S. Food and Drug Administration (FDA) has approved Symbravo, a new medicine to treat acute migraine attacks in adults. This means adults can now use Symbravo to get relief from their migraine symptoms. The FDA's decision was based on the results of three big studies, called Phase 3 trials. These trials involved over 21,000 migraine attacks, so the FDA has a lot of information about how well Symbravo works and how safe it is. The FDA only approves medicines that have been shown to be both safe and effective through a thorough testing process.
Importance of New Treatment Option
"Migraine attacks can happen suddenly and really mess up people's lives. It's estimated that over 39 million people in the U.S. alone get migraines," said Herriot Tabuteau, M.D., CEO of Axsome Therapeutics told US News. This shows how common migraines are and how important it is to have good treatments. "Symbravo gives patients and doctors a new option that can quickly stop a migraine attack, keep it away, and let people get back to their normal activities, all with just one dose." Having a medicine that can give fast and long-lasting relief from migraine pain is a big deal for millions of people. This new treatment is a real step forward in how we treat migraines.
Symbravo Trial Results, How Was It Approved
The trials took place in 3 steps, the Momentum trial study focused on people whose migraines had moderate to severe pain. The results showed that a lot more people taking Symbravo felt pain-free two hours after taking the medicine compared to those who took a placebo which is a dummy pill. Even better, many people felt relief for up to 24 and even 48 hours after just one dose. This long-lasting relief is really important for people with migraines because it means they can get back to their normal lives without worrying about the pain coming back. The study also looked at how many people were free from their worst symptom, like sensitivity to light or sound, or nausea. Symbravo worked better than the placebo in this area too.
While the intercept trial looked at people who took Symbravo when their migraine pain was still mild. Even when the pain was just starting, Symbravo was effective. The results were similar to the MOMENTUM trial, with many people getting pain relief and relief from their worst symptoms. Treating migraines early is often better because it can stop the pain from getting really bad.
And lastly the Movement trial which was to see how safe the medication is when people take it regularly. This study followed 706 people who had at least two migraines a month. The most common side effects people experienced were sleepiness and dizziness. While these side effects are important to know about, the study showed that Symbravo is generally safe for people to use on a regular basis.
Anthropic, OpenEvidence Expand Clinical AI Globally: WHO Warns of Ethics Risks

Credit: iStock
As artificial intelligence (AI) rapidly reshapes health research and clinical care, Anthropic and medical knowledge platform OpenEvidence have announced a collaboration to provide AI-powered clinical decision support to healthcare providers in dozens of low- and middle-income countries.
OpenEvidence answers doctors’ clinical questions using peer-reviewed research and treatment guidelines. The platform, already free to clinicians in the US and Europe, will now be extended to providers in countries where access to medical literature, specialist expertise and continuing education may be limited.
The initiative is being rolled out in about 100 countries, including Uganda, Angola, Sudan, Haiti and Mongolia, according to a list provided by OpenEvidence.
“Access to medical knowledge shouldn’t depend on geography,” OpenEvidence founder Daniel Nadler said.
How Can Clinical AI Help Doctors?
Rajeev Jayadevan, former president of IMA Cochin and convener of the Research Cell, Kerala, told HealthandMe that doctors in Western countries already have access to OpenEvidence, which has also been incorporated into electronic medical records at major US hospitals.
He said the platform could help doctors quickly access medical evidence at the point of care.
“The advantage is that the doctor will have instant access to relevant research papers published in multiple journals, all at once, while asking a specific question about a patient while at the bedside,” Dr Rajeev said.
He called it “a major time-saving step for the busy clinician, who may not have the time to go to the library, sit down with medical journals or textbooks, or even do internet-based searches to look for relevant papers”.
Dr Rajeev also said wider access to medical information could help reduce inequalities in healthcare.
“Medical information that directly helps patients must be available to the doctor free of charge,” he said.
However, AI-based clinical tools also have limitations, particularly when used across different healthcare systems.
“Potential disadvantages include the need for doctors to be trained in digital health literacy and the fact that the answer provided by AI algorithms heavily depends on what the doctor asked for, and in what format,” Dr Rajeev said.
“Some of these issues can be ironed out by using templates, so that important information or keywords are not missed by the doctor who enters the query. Other risks include relying on data from other countries and treatment options that are unavailable or expensive for the local community,” he added.
What Are the Ethical Risks of Clinical AI?
The expansion of AI in healthcare comes as the WHO has separately called for stronger ethics oversight of AI-related health research.
In a report published this week, WHO warned that rapid advances in AI are creating challenges around privacy, bias, fairness, transparency and accountability. It said existing research ethics systems may need additional expertise to assess risks associated with AI and large datasets.
Dr Rajeev said AI-driven research, particularly when it involves large datasets crossing national borders, may require ethics committees to include experts in computer science, data ethics and bioinformatics.
“Ethics Committees by themselves will need to be upgraded to incorporate computer scientists, data ethicists, and bioinformaticians.”
WHO also said oversight should extend beyond ethics committees to researchers, funders, scientific journals, data governance bodies, professional societies and regulators.
Why This Matters
For low- and middle-income countries, clinical AI could help bridge gaps in access to medical literature and specialist knowledge. At the same time, WHO has highlighted the need for local capacity and safeguards to ensure that AI systems developed largely in higher-income settings are appropriate for different healthcare systems and do not introduce new inequities.
Urine & Vaginal Samples May Help Detect Womb Cancer: Lancet Study Suggests Less Invasive Way To Triage Patients
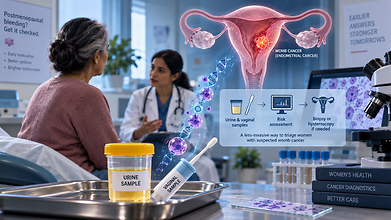
Credit: AI
Postmenopausal bleeding is one of the key warning signs that needs medical intervention as it can be an indicator of endometrial, or womb, cancer. But most women who develop postmenopausal bleeding do not have cancer but still are required undergo several invasive tests to get a clean bill of health.
According to a new study published in The Lancet Obstetrics, Gynaecology & Women’s Health, cells from urine and vaginal fluid could help identify women who need further investigation and reduce the need for unnecessary and uncomfortable invasive procedures. However, the test is not yet accurate enough to replace biopsies or other standard tests these types of cancers.
Cells From Endometrial Tumour May Show Up In Urine And Vaginal Samples
Doctors usually recommend women with postmenopausal bleeding to undergo transvaginal ultrasound, endometrial biopsy and hysteroscopy.
These procedures can be uncomfortable, painful and costly, and some women may need repeat these tests. In the study, only 5.3% of women had endometrial cancer, despite all of them being referred for these tests due to postmenopausal bleeding.
The researchers said that cells shed by an endometrial tumour can travel into the lower genital tract and could be collected through vaginal fluid or urine. Previous research has already indicated that cancer cells could be detected in these samples.
The DETECT study was designed to determine how accurately this approach could detect cancer.
Also read: Endometriosis Can Take Years To Diagnose But This AI Tool Can Identify Its Signs In 18 Milliseconds
About The Study
The study is based on 1,864 women with postmenopausal bleeding from seven hospitals in northwest England between September 2018 and March 2021.
The participants gave their urine and vaginal fluid samples before their routine cancer investigations. Specialist cytopathologists, who were not aware of the women's cancer diagnoses, examined the samples for malignant cancerous cells.
The results were then compared to the women's clinical diagnoses and, where available, tissue histopathology. Among them, 99 had endometrial cancer and 16 had other pelvic cancers, including cervical, ovarian, bladder and colorectal cancers. The test also detected about 8 in 10 womb cancers
When urine and vaginal cytology were combined, the test detected 80.8% of endometrial cancers and correctly identified 92.6% of women who did not have the disease. Its negative predictive value was 98.8%.
In this particular study population, that means a woman with a negative combined result was highly unlikely to have endometrial cancer. But the test was not equally effective at detecting every type of cancer.
It detected 95.8% of high-grade cancers and 96.4% of stage 2 or more advanced cancers. It was more likely to miss low-grade, early-stage tumours. According to the researchers, the urine and vaginal fluid samples may miss early-stage tumours as they may shed fewer cancer cells. The sensitivity of the test was lower than that of transvaginal ultrasound and endometrial biopsy when sufficient tissue was obtained.
Also read: Urine Leakage When You Cough, Sneeze Or Exercise? It Could Be Pelvic Floor Dysfunction, Say Experts
This May Reduce Invasive Tests For Cancers
The study does not suggest that this test could replace conventional methods of diagnosis. It is merely an effective triage tool that could help screen patients and help healthcare providers decide who should actually get invasive tests done.
In the study, 99.1% of women underwent an attempted transvaginal ultrasound, 61.1% underwent an attempted endometrial biopsy and 48.2% underwent hysteroscopy. The failure rate was 25.7% for endometrial biopsy and 17.8% for hysteroscopy, with cervical stenosis and intolerable pain among reported reasons.
The test also produced false positives. Its positive predictive value for endometrial cancer was 38.1%, meaning a positive result would still require further investigation.
The researchers say further studies will establish how the test performs in standard healthcare systems, different populations, and other relevant settings. They also note that highly trained specialist cytopathologists interpreted the samples and helped provide diagnoses, so it remains uncertain whether the same accuracy can be achieved elsewhere.
Another interesting finding from the study is that among 10 women whose initial cytology missed cancer and who underwent repeat sampling, four tested positive on repeat testing, suggesting repeated sampling could improve detection.
The researchers also propose exploring artificial intelligence and image-recognition technology to supplement cytological analysis.
Ayushman Bharat Turns 8: PM Modi Highlights Record Savings On Medical Expenses

Credit: iStock
As India marks eight years of Ayushman Bharat Pradhan Mantri Jan Arogya Yojana (AB PM-JAY), Prime Minister Narendra Modi highlighted the scheme’s expansion and its role in reducing the financial burden of medical treatment.
Launched on September 23, 2018, AB PM-JAY provides cashless hospitalisation cover of up to Rs 5 lakh per family annually to economically vulnerable citizens. It is now implemented across all 36 States and Union Territories in India.
Over 60 Crore People Covered
In a post on X, PM Modi said more than 60 crore people are covered under the scheme.
“Eight years ago, Ayushman Bharat was rolled out with the idea that every Indian should have access to top-quality and affordable healthcare. Today, more than 60 crore beneficiaries have access to Rs. 5 lakh annual health cover, making it the largest healthcare scheme in the world. It has enabled record savings on medical expenses, thus benefitting the poor and middle class,” PM Modi said.
He emphasised that “healthcare is moving closer to every doorstep,” with Ayushman Arogya Mandirs strengthening primary healthcare at the grassroots and recording over 500 crore visits.
Also read: India Launches Biovigilance Program To Strengthen Organ Transplant Safety
Ayushman Bharat: Key Numbers
As of September 21, 2026:
- 60 crore+ people covered under AB PM-JAY
- 48.54 crore+ Ayushman cards created
- 13 crore+ people availed free treatment
- Rs 2 lakh crore+ worth of hospitalisation and treatment provided
- 38,000+ public and private hospitals empanelled
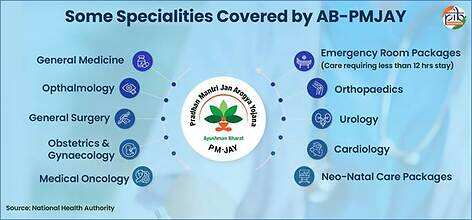
- 1,961 procedures covered across 27 medical specialties
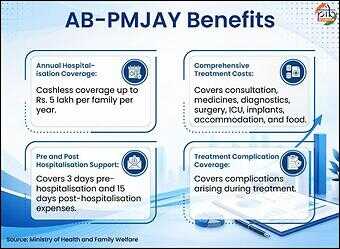
Union Health Minister JP Nadda said, “behind every number is a story” — including families protected from medical debt and patients receiving timely treatment without the fear of financial hardship.
What Is Ayushman Bharat PM-JAY?
AB PM-JAY is the financial protection component of Ayushman Bharat, covering secondary and tertiary hospitalisation.
As of September 21, more than 48.51 crore people, or about 33% of India's population, held Ayushman cards.
As of August 31, the scheme had funded 13.25 crore hospital admissions worth Rs 2.03 lakh crore through more than 38,000 empanelled hospitals.
Ayushman Arogya Mandirs Expand Primary Care
Ayushman Arogya Mandirs form the primary healthcare component of Ayushman Bharat.
They have recorded more than 540 crore visits, while over 50 crore teleconsultations have been conducted as of September 17.
ABHA IDs Cross 97 Crore
Under the Ayushman Bharat Digital Mission, more than 97.61 crore ABHA IDs were operational as of September 17, with over 119.95 crore health records linked to them.
The platform also had more than 5.78 lakh healthcare facilities and 11 lakh healthcare professionals registered.
PM-ABHIM Strengthens Health Infrastructure
The Pradhan Mantri Ayushman Bharat Health Infrastructure Mission (PM-ABHIM) has a budget of Rs 64,180 crore for 2021-2026, focusing on health infrastructure, disease surveillance and health research.
Expansion of AB PM-JAY
In March 2024, AB PM-JAY was expanded to around 37 lakh families of ASHAs, anganwadi workers and anganwadi helpers. More than 44.81 lakh Ayushman cards had been created for them as of September 21.
The scheme was also expanded in September 2024 to cover all senior citizens aged 70 years and above. More than 1.36 crore Ayushman Vay Vandana cards had been issued as of September 21.
- Follow Us :


© $2026 Times Horizon Private Limited