
- Health Conditions A-Z
- Health & Wellness
- Nutrition
- Fitness
- Health News
- Ayurveda
- Videos
- Medicine A-Z
- Parenting
Centre Has Banned 156 Medicines, Including Paracetamol, Due To Increasing Health Risk

Banned medicine (Credit-Canva)
The Union Health Ministry implemented a ban on 156 "irrational" FDC medicines, effective immediately. These medicines, including widely used antibiotics, painkillers, and multivitamins, were commonly used to treat fever, cough, and infections. The ban was imposed due to the associated health risks and lack of therapeutic justification for the ingredients in these FDCs.
What are FDC medicines?
FDCs or fixed-dosed combinations, also known as "cocktail drugs," are medications that combine multiple drugs in a single pill. They are designed to treat multiple symptoms or conditions simultaneously. While they offer convenience, they can pose significant risks. These risks include the possibility of overdose, adverse interactions between the drugs, and the development of antibiotic resistance. Additionally, many FDC medicines lack sufficient scientific evidence to support their safety and efficacy.
Expert opinions on FDC medicines
Experts have raised concerns about the use of FDC medicines. They believe that many of these combinations lack sufficient scientific evidence to support their safety and effectiveness. Additionally, the combination of multiple drugs in a single pill can increase the risk of adverse side effects and interactions with other medications.
Experts have also found that FDC medicines may not be as effective as individual drugs in treating certain conditions. It is important to note that safer and more effective alternatives are available for most of the medical conditions that FDC medicines were used to treat. One particular concern is the inclusion of antibiotics in some FDCs. Overuse of antibiotics can contribute to the development of antibiotic resistance, a major public health threat.
The risks of FDC medicines
The use of FDC medicines can lead to adverse effects, including serious ones. Additionally, safer alternatives, tested in clinical trials, are available to treat the same medical conditions. Experts recommend prescribing drugs individually based on a patient's clinical symptoms rather than combining them in FDCs.
The ban on irrational FDC medicines by the Union Health Ministry can be seen as a positive step towards promoting rational drug use and protecting public health. The goal is to eliminate unnecessary and potentially harmful drug combinations. This is a step forward in reducing the risks associated with medication and ensure safer and more effective treatment options for patients.
Could A Longer Endoscopy Help Spot More Gastric Cancers? WCOG 2026 Highlights Significance Of Early Detection
Credit: AI
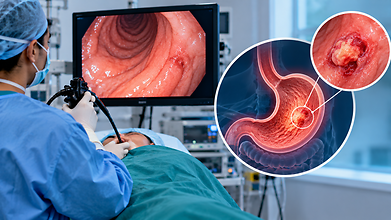
A few extra minutes during an upper gastrointestinal endoscopy may help doctors detect more gastric cancers and precancerous alternations, according to research recently discussed at the World Congress of Gastroenterology (WCOG) 2026 in New Delhi.
At WCOG, it was discussed that the quality and duration of an endoscopic examination can influence the chances of finding early cancer. An inspection time of an additional at least seven minutes was linked with about 3.4 times higher detection of gastric cancer and dysplasia.
The finding comes as gastrointestinal cancers continue to increase, contributing to a growing global health burden. GI cancers currently account for around one in four cancer cases and one in three cancer deaths worldwide. The overall burden of the disease is projected to nearly double by 2050.
Dr. Pramod Garg, Professor & Head, Department of Gastroenterology and Human Nutrition, AIIMS, New Delhi; President, Indian Society of Gastroenterology and Co-Chair, Steering Committee, WCOG 2026, said, “Earlier detection depends on both identifying people at risk and ensuring that diagnostic procedures are performed to the highest possible standard. High-quality endoscopy can create an important opportunity to identify disease at a stage when intervention can make a greater difference.”
Could Endoscopy Time Affect Cancer Detection?
Also read: WCOG 2026: How Infections, Metabolic Disease Are Changing Digestive Health
An upper gastrointestinal endoscopy allows doctors to examine the lining of the oesophagus, stomach, and upper part of the small intestine using a flexible camera device.
Simply inserting the scope and looking quickly may not be enough to identify subtle abnormalities. A more systematic examination allows the endoscopist more time to examine the stomach lining, identify suspicious areas, improve mucosal visualisation and document findings accordingly.
The WCOG discussion therefore puts focus on not just whether endoscopy is performed, but also on how long and how well it is performed.
The reported 3.4 times association highlights the value of a careful, detailed examination that could help detect changes related to cancer early, prompting timely treatment.
Also read: Fatty Liver, Chronic Gut Diseases And Worm Infections: India’s Changing Disease Burden
India's GI Cancer Burden
The changes in India's gastrointestinal cancer burden were also discussed, including growing concern around early-onset colorectal cancer. Researchers are examining whether genetics, environmental exposures and changes in the gut microbiome could be contributing to colorectal cancer appearing at younger ages.
WCOG 2026 also included concerns related gallbladder cancer, liver cancer and the rising role of metabolic risk factors. Discussions also focused on the use of AI in gastrointestinal diagnosis and the importance of validating these tools before introducing them in standard practice.
Dr. Govind Makharia, Professor, Department of Gastroenterology and Human Nutrition, AIIMS, New Delhi and Chairman, Local Organising Committee, WCOG 2026, said, “AI has the potential to strengthen diagnosis and decision-making across gastroenterology, while advanced endoscopy is expanding what can be treated through minimally invasive approaches. The next step is ensuring that these technologies are supported by robust evidence and integrated responsibly into clinical practice.”
H. pylori was also addressed as a preventable risk factor for gastric cancer.
Dr Barry Marshall, Nobel Laureate in Physiology or Medicine, said, “H. pylori is much more than an ulcer organism. If the infection persists for many years, it can cause chronic inflammation in the stomach and increase the risk of gastric cancer. That gives us an opportunity because this is a potentially preventable cause of cancer.”
Advances in minimally invasive procedures like POEM, endoscopic submucosal dissection and therapeutic EUS were also discussed, although access to advanced GI care remains uneven.
Trump Says He ‘Psychologically’ Needs To Pop Aspirin Every Day: But Is It Actually Safe?

Credit: X
The President of the United States, Donald Trump, has revealed that he takes aspirin every day, sharing that he has been doing so for decades because he believes it helps keep his blood “thin”.
He said it while discussing his aspirin use and the bruising that was recently seen on his knuckles. He also said that doctors have advised he take a lower dose.
“I take an aspirin a day. I don’t know if it works but psychologically I need it. It thins the hell out of your blood I guess. I don’t know if it works or not but I’ve been doing it for a long time. And here I am making speeches. I like Bayer aspirin. And I take the big one. They want me to go down to the 80. I take the 386. I don’t know what the hell it is. It’s a monster. They said, ‘Sir, you don’t need that!’ I said, do me a favor, I’ve been doing okay for 35 years. Leave me alone.”
So, does taking an aspirin every day actually protect the heart? And if yes, does a higher dose necessarily provide better results?
Aspirin Reduces Blood Clot Formation
Aspirin affects platelets, which are tiny components of blood that help form clots. By making platelets less likely to clump together, aspirin can reduce the formation of blood clots that could block an artery supplying the heart or brain.
This is why doctors may prescribe daily aspirin to people who have already had a heart attack, stroke, or procedures like coronary stent placement.
But aspirin does not make the blood “thin” in a literal sense. It changes the way blood platelets clot. The US Food and Drug Administration (FDA) says daily aspirin can help people with cardiovascular disease or those who have already had a heart attack or stroke, but daily use is not suitable for everyone.
Aspirin can reduce the risk of certain blood clot formations, but it can also increase the risk of unwanted bleeding. The FDA warns that aspirin can lead to serious side effects like bleeding in the stomach and brain.
It recommends that people do not take daily aspirin without discussing it first with their healthcare professionals.
Mayo Clinic also says that daily aspirin is not right for everyone. Regular use can increase the risk of gastrointestinal bleeding and stomach ulcers, while in some people it can also increase the risk of a bleeding stroke.
Who Should And Shouldn't Take It?
For people who have never had a heart attack or stroke or any other type of cardiovascular disease, taking aspirin routinely to prevent a cardiovascular event is generally not recommended.
The American Heart Association says routine daily aspirin is not recommended for most healthy adults without cardiovascular disease because its benefit can be offset by the risk of serious bleeding.
The FDA also says that for people without cardiovascular disease risk, the risks of long-term aspirin use may be greater than the benefits.
For someone who has already had a heart attack, stroke or any other cardiovascular event, doctors may prescribe daily aspirin because preventing another clot-related event can outweigh the bleeding risk.
According to Mayo Clinic, this is a secondary method of prevention. It says that the benefit of daily aspirin in this group is well established. This does not mean that patients should start, stop or change their aspirin dose on their own.
Also read: White House Chief Of Staff Susie Wiles Reveals Brutal Toll Of Fighting Cancer
Is A Bigger Aspirin Dose Better For Heart?
A higher dose does not automatically provide better protection against heart attacks. Low-dose aspirin prescribed for cardiovascular health is usually around 75 to 100 mg, with 81 mg frequently used.
Mayo Clinic says that the appropriate dose depends on the individual and should be discussed with a healthcare professional.
Taking higher doses of aspirin can increase the risk of bleeding. People with a history of stomach ulcers or gastrointestinal bleeding, bleeding disorders or aspirin allergy may also face greater risks.
The risk of bleeding also increases with age. The American Heart Association says routine aspirin for primary prevention is generally not recommended for healthy adults over 70.
Global Life Expectancy Returns To Pre-Pandemic Levels, But NCDs Resulted In 8 Out 10 Deaths: WHO

Credit: AI
According to the World Health Organisation, the global life expectancy has recovered to almost pre-pandemic levels, a significant public achievement, but the world is facing a growing burden from chronic diseases,
WHO's latest health estimates, which released recently, offer a glimpse into the pattern of life expectancy and disease burden between 2000 and 2023. It also says that while damages due to COVID-19 have been reversed, the world is grappling with a growing burden of noncommunicable diseases (NCDs).
Global Life Expectancy Is Almost Back To 2019 Levels
Global life expectancy reached 73.3 years in 2023, compared to 73.4 years in 2019, just before the COVID-19 pandemic hit. However, the pace at which healthy life expectancy has recovered has been slow and steady. It stood at 62.8 years in 2023, which was still 0.4 years below the 2019 level.
This means people are living almost as long as they were before the pandemic, but the number of years they can expect to live in good health has not fully recovered.
Dr Alain Labrique, Director of WHO’s Department of Data, Digital Health, Analytics and AI said, "Living longer is one of the great achievements of public health. The next challenge is to ensure that those additional years are lived in good health, while health systems are equipped to respond to the changing needs of populations."
NCDs Account For 74% Of Global Deaths
The WHO data also depicted a growing share of deaths caused by NCDs. In 2023, NCDs accounted for 74% of all deaths globally, compared to 58% in 2000.
In fact, eight of the world's 10 leading causes of death were NCDs in 2023. These include cardiovascular diseases, cancer, diabetes and chronic respiratory diseases.
The change is not limited to wealthier countries. The shift in NCD-related deaths was visible across all income levels.
In 2023, for the first time, communicable diseases accounted for less than half of all deaths in low-income countries, showing how disease patterns are changing even in populations that have traditionally carried a higher burden of infectious diseases.
Also read: Japan Has 107,677 Centenarians; 88% Are Women: Challenges Of An Aging Population
Heart Disease Remains The World's Biggest Killer
Cardiovascular disease continues to be the leading cause of death worldwide. Ischaemic heart disease alone caused about 9.5 million deaths in 2023, along with an estimated 210 million disability-adjusted life years, a measure that combines years lost because of premature death and years lived with disability.
While there has been progress in reducing the burden of ischaemic heart disease in many parts of the world since 2000, the WHO noted increases in individual-level cardiovascular risk in the South-East Asia and Western Pacific regions.
This highlights continuing differences in cardiovascular health between populations.
Also read: Blue Zones Diets: What the World’s Longest-Livers Eat
Diabetes And Dementia Also Among Major Contributors
The WHO estimates point to growing concerns around other chronic conditions like diabetes and dementia. The risk of dying from diabetes has increased substantially since 2000, especially in South-East Asia.
Dementia has also landed among major causes of death globally. Alzheimer disease and other dementias became the fifth leading cause of death worldwide in 2023, compared to 19th in 2000. Global deaths from dementia tripled between 2000 and 2023, according to the WHO.
Mental Health Adds To The Burden
Between 2019 and 2023, the global age-standardised DALY (disability-adjusted life year) rate increased by approximately 20% for depressive disorders and nearly 45% for anxiety disorders. Together, these conditions were responsible for an estimated 110 million years of healthy life lost through premature death and disability in 2023.
Drug use disorders have also been observed across different trends across regions. Between 2000 and 2023, the WHO Region of the Americas recorded the largest increases in the risk of death linked to these disorders, while the Western Pacific region saw declines.
In a nutshell, the world has largely recovered the ground lost in overall life expectancy during the pandemic. But simply living longer does not necessarily mean we are living healthier. As populations age and infectious diseases account for a smaller share of deaths in many regions, health systems are increasingly required to manage conditions that often need long-term prevention, diagnosis, treatment and care.
“The value of these estimates is not only in the numbers themselves,” said Dr Labrique. “By showing how causes of death and disease burden are changing over time and across populations, they give countries evidence to help shape health policies and priorities.”
“These capabilities are critical to better enable targeted, effective interventions and ultimately further improving health and well-being for all.”
- Follow Us :


© $2026 Times Horizon Private Limited