
- Health Conditions A-Z
- Health & Wellness
- Nutrition
- Fitness
- Health News
- Ayurveda
- Videos
- Medicine A-Z
- Parenting
Can Weight Loss Drugs Curb Alcoholism? See What Study Says

Credits: Canva
Until law, GLP-1 drugs were used to treat diabetes, obesity and even the recent evidences suggest that it could as well be used to treat chronic kidney problems. There is yet another research, published in JAMA Psychiatry on February 25, titled Once-Weekly Semaglutide in Adults With Alcohol Use Disorder: A Randomized Clinical Trial that explores if GLP-1 receptor agonist semaglutide reduce alcohol consumption and cravings in adults with alcohol use disorder.
What Do Studies Say?
The research was conducted over a period of 9 weeks, where in the randomized clinical trial, the participants who were administered semaglutide, it led to reductions in some but not all measures of weekly consumptions. It also reduced weekly alcohol and craving related to placebo, and also led to a greater relative reduction in cigarettes per day.
The research also found that weekly injections of semaglutide, which is the active ingredient in weight loss drugs like Wegovy also helped reduce cravings in people with alcohol use disorder.
The lead author Christian Hendershot said that these findings will help in developing new approaches to treat alcoholism. "Two drugs currently approved to reduce alcohol consumption aren't widely used. The popularity of Ozempic and other GLP-1 receptor agonists increases the chances of broad adoption of these treatments for alcohol use disorder," said Hendershot in news release by the University of Southern California's Institute for Addiction Research, where he is the director.
The study is government-funded research and was funded by the National Institute on Alcohol Abuse and Alcoholism, part of the National Institutes of Health.
How Was The Study Conducted?
The study was small, and took in account for only 48 adults over two months, thus experts say that it is not yet clear how safe these drugs are for people who do not need to lose weight. Though the results do add up with the evidence form animal studies on drugs like Ozempic and Wegovy on how it helps manage cravings, not just for food, but also for tobacco and alcohol. Scientists are also studying these drugs on smokers, people with opioid addiction and cocaine users.
Co-author Dr Klara Klein of the University of North Carolina at Chapel Hill who treats people with obesity and diabetes said, "This is such promising data. And we need more of it. We frequently will hear that once people start these medications that their desire to drink is very reduced, if not completely abolished."
Why Does It Work So Well Against Alcoholism?
The GLP-1 receptor agonists work by mimicking hormones GLP-1 in the gut and brain that regulates appetite and feelings of fullness. This response is what helps one lose weight, and what helps one curb their craving for alcohol. These drugs that mimic the functioning of your brain, which is responsible to tell your body when to stop consuming, are the same hormones that tell your body about other kinds of consumptions, including alcohol. Therefore by consuming the weight loss drugs one can treat alcohol use disorder.
However, the researchers have pointed out on the limited data on the research and have suggested to continue using the three approved drugs by the National Institute on Alcohol Abuse and Alcoholism and Substance Abuse and Mental Health Services Administration, namely, Disulfiram, Naltrexone, and Acamprosate to treat alcohol use disorder until large studies confirm these findings.
Pancreatic Cancer Breakthrough? New Drug Combo Controls Tumour Growth In 90% Of Patients
Credit: AI image
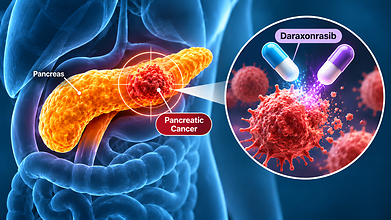
In what can be described as a major breakthrough, a new treatment combination has shown tremendous promise in advanced pancreatic cancer treatment. A recent early-stage clinical trial showed that the combo shrank tumours in more than 60% of patients and controlled disease progression in 90% of patients.
The findings raise hope for pancreatic cancer, which is often diagnosed late as well as has limited treatment options. Despite positive outcomes, larger trials are needed to establish how much the treatment improves survival.
More About The Pancreatic Cancer Treatment Trial
Also read: Experimental Vaccine For Blood Cancer Cuts Death Risk By 41% In Trial: How Does It Work?
The combination includes daraxonrasib, an experimental targeted cancer drug, alongside two chemotherapy medicines, gemcitabine and nab-paclitaxel.
The updated results from the Phase 1/2 RMC-GI-102 trial were presented at the EORTC-NCI-AACR Symposium on Molecular Targets and Cancer Therapeutics in Barcelona.
The study involved 61 patients with metastatic pancreatic adenocarcinoma who had not previously received treatment for their metastatic disease. Participants received the combination and were followed for a median of 18.3 months.
A 90.2% control in disease was reported, meaning the cancer either shrank or remained stable. The objective response rate, which measures tumours that shrank significantly or disappeared, was 60.7%. This included complete responses in 8.2% of patients, whose tumours were no longer detected.
Median progression-free survival was 12.8 months, meaning patients lived a median of nearly 13 months without their cancer progressing or dying. The estimated proportion of patients alive at one year was 76.6%.
Dr Wungki Park, a gastrointestinal medical oncologist at Memorial Sloan Kettering Cancer Center in New York, who presented the findings, said “this is the closest to cure”. He also said that he had never seen so many tumours disappear in patients whose cancer had spread.
He also said, “We are beginning to see not only a higher percentage of tumour response rates, but also deeper responses and a near doubling in the duration of disease control, which may eventually translate into longer survival."
He added, “The median follow-up is 18 months. Just imagine, in an average of 18 months your disease just disappears on the CT scan … that’s closest to complete remission … it’s incredible.”
How Does The New Drug Combination Work?
Also read: Daraxonrasib: Europe Approves First RAS-Targeted Drug For Metastatic Pancreatic Cancer
Daraxonrasib, also known as RASONQUE, targets RAS, which drives cell growth. Mutations in RAS, especially KRAS, can keep these growth signals on, allowing pancreatic cancer cells to multiply uncontrollably.
The drug is designed to inhibit active RAS proteins and disrupt the signals that cancer cells depend on for growth and survival. Researchers are combining it with chemotherapy to attack the cancer through different mechanisms.
Gemcitabine interferes with cancer cell DNA synthesis, while nab-paclitaxel disrupts microtubules, structures essential for cell division. Combining these drugs with targeted RAS inhibition could produce more sustained responses.
A Major Breakthrough
Pancreatic cancer remains one of the most difficult cancers to treat once it has spread beyond the pancreas. Many patients are diagnosed at an advanced stage, when surgery may no longer be possible.
The RAS signalling mechanism has long been considered a challenging target for cancer treatment. The development of drugs capable of fighting this has therefore opened a new avenue of research, especially pancreatic cancers driven by RAS mutations.
The trial's response rates and duration of disease control are encouraging. However, it was a small, open-label study without a chemotherapy comparison group.
Researchers cannot determine yet how much of the benefit came from daraxonrasib rather than chemotherapy or whether the combination will significantly extend survival.
Daraxonrasib is being investigated in larger clinical trials to determine its effectiveness and safety. A Phase 3 trial, RASolute 303, is comparing daraxonrasib alone, daraxonrasib combined with gemcitabine and nab-paclitaxel, and chemotherapy alone in patients with previously untreated metastatic pancreatic cancer.
These results will help establish whether the promising early findings translate into a meaningful improvement in survival and whether the combination could become a new treatment option.
PJ.2.1 Is Now Variant Under Monitoring After Detection In 18 Countries: Should You Worry About Its 24 Mutations?
Credit: iStock
The World Health Organization (WHO) has designated COVID-19 variant PJ.2.1, a descendant of the JN.1 lineage with 24 spike protein changes, as a Variant Under Monitoring (VUM). As of November 8, the variant had been detected in 18 countries, with its share of reported sequences increasing particularly in Canada and the United States.
"Considering the available evidence, the additional public health risk posed by PJ.2.1 is evaluated as low at the global level, with low confidence," the WHO said in its initial risk evaluation published by its Technical Advisory Group on Virus Evolution (TAG-VE).
Laboratory findings suggest that the variant does not show substantial additional antibody escape compared with other circulating variants. Blood samples from recipients of LP.8.1- and XFG-adapted vaccines were also able to neutralize it in laboratory tests.
However, there is insufficient clinical data to determine whether PJ.2.1 causes more severe illness.
What Is COVID Variant PJ.2.1? How Widely Has It Spread?
Also read: New COVID Variant PJ.2.1 Spreading Globally: Is India At Risk, Are There New Symptoms?
According to the WHO report, "PJ.2.1 is a highly mutated variant with 24 amino acid differences in the Spike protein alone."
First identified in Canada, laboratory studies indicate that it binds more strongly to human ACE2 receptors, which the virus uses to enter cells. However, stronger receptor binding does not necessarily mean faster transmission between people.
The WHO noted that increased receptor binding "may contribute to the observed growth, but do not directly establish increased transmissibility in humans."
The proportion of PJ.2.1 among available global sequences increased from 1% in epidemiological week 33 to 11.6% in week 41, according to the WHO.
As of November 8, 2026, 722 sequences had been submitted to the GISAID, an open access database, from 18 countries.
Can Existing Vaccines Protect Against PJ.2.1?
Read More: New COVID-19 Variant PJ.2.1 Spreads Globally: WHO Says Symptoms Resemble Cold, Flu
In a study involving plasma from 36 recipients of an LP.8.1-adapted vaccine, researchers found no greater antibody evasion against PJ.2.1 than against most tested variants.
Another study involving 22 participants found that neutralisation titres against PJ.2.1 increased 2.8-fold, from 228 before vaccination to 642, at a median of 14 days after an XFG-adapted mRNA vaccine.
These findings suggest that vaccine-induced antibodies can neutralize PJ.2.1 in laboratory tests. However, they do not establish real-world vaccine effectiveness against infection or severe disease, the WHO report said.
Does PJ.2.1 Cause More Severe Disease?
"There is currently no evidence establishing greater disease severity associated with PJ.2.1, although comparative clinical data remain limited," the WHO said.
The agency has called for further studies to assess vaccine effectiveness, compare hospitalisations and severe disease outcomes, evaluate antiviral susceptibility and strengthen genomic surveillance.
Dr Gopakumar, Senior Consultant and Head of the Department of Internal Medicine at Apollo Adlux Hospital, Kerala, said the number of mutations alone does not determine how dangerous a variant is.
"The emergence of the new COVID-19 variant PJ.2.1 highlights the virus’s continued ability to evolve. While the reported 24 mutations, particularly in the spike protein, have attracted attention, the number of mutations alone does not determine how dangerous a variant is. What matters clinically is whether these changes make the virus more transmissible, help it evade existing immunity or increase the risk of severe illness," he told HealthandMe.
Dr Navneet Sood, Associate Director and Senior Consultant, Pulmonology, Dharamshila Narayana Superspeciality Hospital, Delhi, added that current evidence does not indicate an increased impact on disease severity compared with previous variants.
"While it is safe to say that the evidence currently shows that there is no increased impact of PJ.2.1 compared to previous variants in disease severity, the WHO's variant surveillance system is still monitoring the potential for new variants to emerge and experts have emphasized the need for genomic monitoring. Public awareness should be centred on identifying respiratory symptoms, testing if required, and taking additional precautions for vulnerable people," he told HealthandMe.
Should You Be Worried?
The WHO currently assesses the additional global public health risk from PJ.2.1 as low, although confidence in this assessment remains limited.
There is no need to panic, but experts advise people to remain vigilant. Older adults, immunocompromised individuals and those with chronic illnesses should take particular care. Maintaining respiratory hygiene, ensuring adequate ventilation and seeking medical advice if respiratory symptoms develop remain sensible precautions.
Antibiotics Are Not Painkillers: Why You Shouldn't Take Them For Fever Or Viral Infections
Credit: iStock
Fever, body ache, sore throat or cough? Taking an antibiotic may seem like a quick fix, but it can do more harm than good. Antibiotics treat bacterial infections, not viral illnesses such as colds and flu.
During World Antimicrobial Resistance (AMR) Awareness Week, experts have warned against self-medication, buying antibiotics over the counter and changing prescribed treatment without medical advice. Such practices fuel antimicrobial resistance (AMR), making infections harder to treat.
Dr Jatin Ahuja, Consultant, Infectious Diseases, Indraprastha Apollo Hospital, Delhi, told HealthandMe that resistance is making common bacterial infections increasingly difficult to treat.
"When bacteria develop resistance to multiple classes of antibiotics, fewer effective treatment options remain. This can delay recovery, increase complications and prolong hospital stays. Pneumonia, urinary tract infections and bloodstream infections become particularly challenging when bacteria do not respond to commonly used drugs," he said.
Can Antibiotics Treat Fever, Cold, Flu Or Body Ache?
Fever, pain or a sore throat does not automatically mean you need antibiotics.
"Taking antibiotics for viral infections, particularly coughs, colds and flu, does not help recovery," Dr Ahuja said.
Dr Sumit Jain, Director – Internal Medicine, Paras Health, Panchkula, said antibiotics are ineffective against viral infections.
"People will often think that antibiotics are the answer to a fever, body ache, cold, cough or sore throat. They're not. Antibiotics only work against bacterial infections and are of no use at all against viral infections (i.e. the common cold, flu and most of the seasonal respiratory infections)," he told HealthandMe.
Dr Atul Kakar, Chairperson, Internal Medicine, Sir Ganga Ram Hospital, explained that the common cold, flu, most sore throats and many cases of acute bronchitis are caused by viruses.
Viral fevers are generally self-limiting and may resolve within three to seven days with rest, hydration and symptom relief. Antibiotics do not speed up recovery, he told HealthandMe.
How Does Antibiotic Misuse Cause Drug Resistance?
Read More: 98 Years After Penicillin: Are We Running Out Of Effective Antibiotics?
Antibiotic resistance develops when bacteria evolve to survive medicines designed to kill them or stop their growth. Inappropriate antibiotic use accelerates this process.
Dr Ahuja warned that resistance to multiple antibiotics leaves doctors with fewer treatment options, increasing the risk of complications and prolonged hospital stays.
Dr Kakar added that resistant bacteria can spread between people at home, in workplaces and in hospitals, making AMR a wider public health threat.
Drug-Resistant Infections Raise Mortality Risk
A recent Indian Council of Medical Research (ICMR) study across 20 tertiary-care hospitals found that 61.1% of confirmed infections caused by four major Gram-negative bacteria were carbapenem-resistant.
Published in The Lancet Regional Health – Southeast Asia, the study analysed nearly 1.6 lakh hospitalised patients between April 2022 and April 2025. Patients with resistant infections faced higher mortality, longer hospital stays and substantially higher treatment costs.
The global picture is equally concerning. According to the World Health Organization (WHO), one in six laboratory-confirmed bacterial infections worldwide is already resistant to antibiotics. If current trends persist, drug-resistant infections could contribute to more than 39 million deaths by 2050.
When Should You Take Antibiotics?
Antibiotics should be taken only when a doctor diagnoses or strongly suspects a bacterial infection.
Dr Ahuja recommended clinical assessment and culture and sensitivity testing, wherever indicated, to identify the bacteria and determine which medicines are likely to work.
Vaccination, hand hygiene and infection-control measures can also help prevent infections and reduce antibiotic use.
What Are The Risks Of Taking Antibiotics Without A Prescription?
Self-medicating, using leftover antibiotics or taking them without a prescription can accelerate resistance and make future bacterial infections harder to treat.
Dr Jain also warned of side effects, including diarrhoea, allergic reactions and disruption of normal gut flora.
He advised against self-medication and recommended consulting a doctor if symptoms persist or worsen.
Antibiotics are not a quick fix for every fever, cough or body ache. Use them only when medically necessary to help keep these medicines effective.
- Follow Us :


© $2026 Times Horizon Private Limited