
- Health Conditions A-Z
- Health & Wellness
- Nutrition
- Fitness
- Health News
- Ayurveda
- Videos
- Bizz Impact
- Medicine A-Z
- Parenting
Can Loneliness & Depression Harm Your Heart? Here's What Experts Say

Depression and heart health (Credit: Canva)
Heart disease is often linked to high cholesterol, obesity, or lack of exercise. However, there is mounting evidence that suggests that mental health plays a crucial role in cardiovascular well-being. Stress, anxiety, and depression can silently strain the heart, increasing the risk of serious complications.
A recent study, published in Nature Human Behaviour, showed that loneliness has a significant impact on proteins present in a person's blood. For the study, researchers used data from more than 42,000 participants to explore whether the 9.3% who reported social isolation and 6.4% who reported loneliness had different levels of proteins in their blood compared with those who did not. The researchers then studied data that tracked the health of participants over an average 14-year period.
"We found around 90% of these proteins are linked to the risk of mortality," Dr Chun Shen, Fudan University in China, who is also the lead researcher said. "In addition, about 50% of the proteins were linked to cardiovascular disease, type 2 diabetes and stroke," he added.
Dr Shrey Kumar Srivastav, senior consultant at Sharda Hospital, said that subtle symptoms of heart disease, such as fatigue, shortness of breath, swelling in the lower legs, dizziness, and jaw pain, are often overlooked or attributed to stress and ageing. "Women, in particular, may experience atypical signs like extreme fatigue, indigestion, or upper abdominal pain instead of classic chest pain, leading to delayed diagnosis," he added.
Can Mental Health Issues Trigger Heart Diseases?
Chronic stress can trigger harmful cardiovascular effects, including elevated blood pressure, increased heart rate, and inflammation—key contributors to heart disease. Anxiety and depression further impact heart health by disrupting sleep patterns, raising stress hormone levels, and encouraging unhealthy habits like poor diet and inactivity.
Mental health issues like depression and anxiety have a profound impact on the heart. They don’t just affect emotions but can increase inflammation and put extra strain on the cardiovascular system, warns Dr Srivastav.
Certain risk factors, such as obesity and diabetes, disproportionately affect women, making them more vulnerable to heart failure with preserved ejection fraction (HFpEF). However, due to gender-specific symptom variations, heart disease in women often goes undiagnosed for longer.
Obesity is more prevalent in women than men and is a major risk factor for heart failure. Diabetes, too, has a greater impact on women’s heart health, yet diagnosis and treatment delays are common. Addressing this gap requires increasing awareness, training healthcare providers, and promoting early diagnostic tools,” explains Dr Srivastav.
How Can You Protect Your Heart?
A simple yet effective way to support heart health is by committing to a brisk 30-minute walk daily. Walking not only helps regulate blood pressure and manage weight but also improves circulation and reduces stress.
"Regular physical activity, paired with a heart-healthy diet rich in fruits, vegetables, whole grains, and lean proteins, significantly lowers cardiovascular risks," advises Dr Srivastav.
Heart disease can often go undetected until a major event occurs, making routine screenings essential.
- For women: Begin screenings around age 30 and continue with regular checkups.
- For men: Start screenings at age 35.
Health screenings, including blood pressure checks, cholesterol tests, and electrocardiograms (ECGs), are critical for early detection of silent heart conditions.
Does Experimental Obesity Drug Petrelintide Cause Fewer GI Side Effects Than Ozempic? Lancet Study Shows Promise
Credit: AI
A new experimental obesity drug could offer an alternative to GLP-1 medicines for people who struggle with their gastrointestinal side effects.
Petrelintide, a once-weekly injectable drug that works on the hormone amylin, helped people with obesity lose more than 10% of their body weight in a Phase 2 trial.
Published in The Lancet Diabetes & Endocrinology, the drug showed a relatively low rate of gastrointestinal side effects.
The study, however, did not directly compare petrelintide with drugs like semaglutide or tirzepatide.
So, while the results suggest it may be better tolerated, researchers cannot yet say that it causes fewer side effects than GLP-1 drugs.
Petrelintide Works Differently From Ozempic And Mounjaro
Petrelintide is a long-acting amylin analogue. Amylin is a hormone produced by the pancreas alongside insulin and helps control appetite and food intake.
A yet-to-be approved drug, unlike Ozempic and Wegovy, which target the GLP-1 hormone, petrelintide focuses on amylin.
It is being developed by Danish drugmaker Zealand Pharma with Roche.
Also read: CSIR-CCMB Scientists Find Flu & COVID Viruses May Affect A Protein Linked To Parkinson’s Disease
Petrelintide’s Effect On Weight Loss
The Phase 2 ZUPREME-1 trial included 485 people who received at least one dose of petrelintide or placebo, with everyone also receiving lifestyle advice.
After 42 weeks, average weight loss ranged from 8.7% to 10.7%, depending on the petrelintide dose.
The group receiving placebo lost about 1.7% of their body weight. The 5 mg dose produced the largest average reduction, at 10.7%.
At 28 weeks, weight loss across the petrelintide groups ranged from about 7.9% to 9.8%, compared with 1.7% with placebo.
Also read: Type 1 Diabetes: Student Nearly Dies After Diet Advice To Stop Insulin; Why Insulin Is Essential
Petrelintide Shows Promise In Terms Of Tolerability
This is perhaps one of the biggest attractions of petrelintide. Nausea was the most common side effect, affecting 20% of people compared to 6% in the placebo group.
However, vomiting was uncommon, occurring in 3% of the petrelintide group compared with 6% of the placebo group. Diarrhoea occurred in 7% and constipation in 7% of those receiving petrelintide. Researchers also reported that most gastrointestinal side effects were mild.
This is a well-tolerated medication," lead investigator Dr. Timothy Garvey of the University of Alabama at Birmingham told HCPLive . Approved GLP-1 drugs have produced larger average weight loss in their own trials, but Garvey said "This current level of 10-15% is sufficient to treat a large number of patients who have obesity.
Three serious adverse events were considered related to petrelintide, including two cases of gallstones and one case of obstructive pancreatitis, according to an independent expert assessment of the study.
Petrelintide Vs Ozempic
One may be inclined to compare petrelintide's side-effects with that of GLP-1 drugs like Ozempic, Wegovy, Zepbound and Mounjaro, but the trial was designed to compare petrelintide with placebo, not with semaglutide or tirzepatide.
Dr Marie Spreckley of the University of Cambridge cautioned that the comparison with GLP-1 medicines is too strong because “the trial did not test petrelintide against any of those medicines, so we cannot say from these results that it causes fewer side effects.”
That means more investigation will be needed to compare petrelintide’s tolerability and existing obesity treatments.
However, the results have prompted further development of petrelintide, with Phase 3 trials planned. Researchers are particularly interested in whether the drug can provide sustained weight loss while allowing people to remain on treatment without gastrointestinal symptoms.
CSIR-CCMB Scientists Find Flu & COVID Viruses May Affect A Protein Linked To Parkinson’s Disease
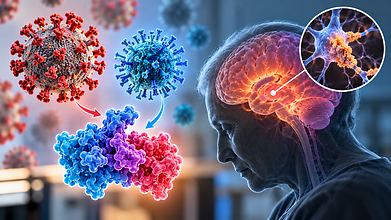
Credit: AI
Repeated viral infections may play a key role in shaping Parkinson’s disease risk. A new study by researchers at CSIR-Centre for Cellular and Molecular Biology (CCMB), Hyderabad, has found that RNA viruses like influenza and even SARS-CoV-2 can interact with a protein called alpha-synuclein, accelerating the formation of abnormal protein clumps associated with Parkinson’s.
Published in Cell Reports, the study, which was led by Dr Swasti Raychaudhuri’s laboratory at CCMB, also identified a cellular protein that appears to act as a defense against this process.
What Is Alpha-Synuclein?
Alpha-synuclein is a protein that is naturally found in nerve cells. In Parkinson’s disease, the protein can accumulate into abnormal clumps called amyloid aggregates.
These aggregates are a characteristic feature of Parkinson’s and can interfere with the normal functioning of neurons.
The new study looked at what happens to alpha-synuclein when a cell is infected by an RNA virus.
Also read: Flu 2026: Symptoms To Watch For As New Season Begins
How Could Flu And COVID Affect Alpha-Synuclein?
Flu and COVID viruses contain RNA, which is their genetic material. The researchers found that parts of this viral RNA can fold into unusual shapes called RNA G-quadruplexes (rG4s).
These RNA structures can interact with a protein called alpha-synuclein. Alpha-synuclein normally exists in brain cells, but in Parkinson’s disease it can clump together and form abnormal deposits.
The researchers found that viral RNA structures may encourage alpha-synuclein to clump together more easily.
Also read: WHO Sets 2027 Flu Vaccine Strains; US States Can Now Order Free COVID Shots For Kids
Body Has Its Own Defense Mechanism
The researchers also identified a protein called DDX39A, which counters both viral multiplication and alpha-synuclein aggregation.
Normally found inside the cell nucleus, DDX39A moves into the cytoplasm during an RNA viral infection. There, it can interact with both viral RNA structures and alpha-synuclein.
DDX39A acts as an RNA “unwinding” protein. It breaks apart the rG4 structures in viral RNA, making it harder for the virus to replicate. At the same time, this process appears to slow the formation of alpha-synuclein amyloids.
Study first author Aanchal said, “The virus fails to replicate with its RNA structures dismantled, and thus, the viral load in the cells decreases. At the same time, the unwinding of viral RNA’s secondary structure effectively slows down α-Synuclein amyloid formation.”
Viral Infections Do Not Cause Parkinson’s: Researchers
The researchers caution against making that conclusion. Not every viral infection will increase amyloid formation, and not everyone who gets influenza or COVID-19 will develop Parkinson’s.
The study suggests that the outcome depends on a complex balance between the virus, viral RNA, alpha-synuclein, and the cell’s defence mechanisms.
There have been previous studies reporting an association between certain viral infections and an increased risk of neurodegenerative diseases. But the biological mechanism behind such associations has remained unclear.
The CCMB researchers are now investigating what happens to these molecular interactions over longer periods.
The concern is that repeated exposure to viral infections could alter the balance between protective cellular mechanisms and protein aggregation. However, this remains an area of investigation and cannot currently be used to predict an individual's Parkinson’s risk.
Antibiotic Costing ₹86 Carries MRP Of ₹4,528: Karnataka FDA Flags Massive Drug Price Gaps

Credit: AI
During a recent sweep of cancer hospitals in Karnataka where high-cost drugs are used, the Karnataka's Food Safety and Drug Administration (FSDA) found massive price disparity between institutional (landing) prices and the maximum retail price (MRP).
The Karnataka Government urged Union Ministry of Health and Family Welfare and the National Pharmaceutical Pricing Authority (NPPA) to intervene and curb the large gaps between prices hospitals pay and what they charge patients.
The concern is significant for patients admitted to hospitals who may have limited time and opportunity to compare and opt for cheaper alternatives.
Difference Between Landing Costs & MRPs
Also read: US To Face Nearly 28,000-Surgeon Shortfall By 2038: What Could This Mean For Patients?
The food and drug regulator has spotted pricing discrepancies of 256 medicines, medical devices and hospital consumables and has asked the National Pharmaceutical Pricing Authority (NPPA) and the Department of Pharmaceuticals to intervene.
It involves Gufipol, that has an institutional acquisition cost was ₹86, while its MRP was ₹4,528, making the MRP about 52.6 times the reported acquisition cost.
Another example is Guficycline-50 injection, reportedly acquired for ₹160 but carrying an MRP of ₹7,110, or about 44 times the acquisition cost.
The gap was also seen with expensive medicines. Taxocare 120 mg, a cancer drug, had a reported acquisition cost of ₹1,000 against an MRP of about ₹21,618.
Across the 256 products examined, the average MRP-to-acquisition-cost multiple was 9.23 times, while the median was 7.58 times. Seventy-three products had MRPs at least 10 times their reported acquisition costs.
The FSDA said, “MRP operates as a ceiling on retail sale to a consumer, but it does not by itself ensure that the MRP is a fair patient-facing price in an institutional setting.”
The regulator added, “The issue is not merely a commercial discount. It is an information-asymmetry and captive-patient problem. The patient, who is generally unable to obtain an immediate substitute during admission, bears the entire benefit of the manufacturer-hospital discount being retained within the supply chain. The patient neither knows the institutional acquisition cost nor possesses an effective choice at the point of use.”
This becomes relevant in emergency care, intensive care, cancer treatment, and other situations where patients may need medicines or medical consumables immediately.
Also read: Chewing Tobacco Linked To 2.5 Lakh Deaths Globally: India Among Top 10 Worst-Hit Countries
What Has The State Proposed?
The state has suggested a framework under which the amount charged to a hospital patient would take into account the actual net acquisition cost, a prescribed service margin and applicable taxes.
It has also proposed that hospital bills disclose details like the MRP, institutional acquisition cost, permitted service margin, taxes and final amount charged to the patient.
The proposal would also consider discounts, rebates, credit notes, free supplies, and other benefits when calculating the hospital's actual acquisition cost.
AHPI Backs Comprehensive And Holistic Approach To Hospital Medicine Pricing
The Association of Healthcare Providers of India (AHPI) has called for a comprehensive assessment of medicine and consumable pricing in hospitals, saying the cost of drugs should be considered alongside other aspects and expenses involved in delivering quality patient care.
AHPI also said hospital expenses also include healthcare staff, diagnostics, medical equipment, nursing, infrastructure, infection control and patient monitoring. It said hospitals also operate with high costs and capital investments, with operating margins for many hospitals typically ranging between 8% and 12%.
Dr Girdhar Gyani, Director General, AHPI, said hospitals incur costs beyond dispensing medicines, including stocking, preparation, quality checks and safe administration.
Dr Gyani said, “Hospitals are not merely selling medicines; they are delivering comprehensive, round-the-clock clinical services, which includes stocking, preparation, quality checks and safe and timely administration of the drugs thereby ensuring desired clinical outcomes for every patient. Medicines and consumables are an important part of this continuum, but their price cannot be viewed in isolation from the overall cost and responsibility of delivering safe and effective patient care.”
On medicine pricing, AHPI stated that hospitals often receive bundled payments under private insurance and government schemes. For patients who pay directly, it said hospitals and retailers generally dispense medicines at the MRP set by manufacturers, subject to regulations.
The association also opposed the uniform 16% margin, saying medicines have different procurement, storage and supply-chain requirements. Pharmacies also incur costs related to inventory, expiry, working capital, manpower, storage and regulatory compliance.
AHPI said oncology medicines in particular vary widely in their procurement, cold-chain, storage, handling and wastage requirements, and a flat margin could make some products commercially unattractive to stock.
Dr Gyani added, “Affordability and transparency in healthcare are important objectives, but they must be pursued without compromising patient safety or overlooking the actual cost of delivering quality care. A meaningful discussion on healthcare affordability must examine the entire delivery and supply chain rather than isolating the price of medicines from the wider services and responsibilities undertaken by hospitals.”
Current Drug Pricing Rules In India
Drug prices in India are regulated under the Drugs (Prices Control) Order, 2013. The NPPA fixes ceiling prices for medicines listed under the National List of Essential Medicines and monitors drug prices.
Manufacturers cannot increase the MRP by more than 10% over the previous 12 months for formulations not covered by price control.
The government also says no person can sell a formulation above the applicable current price or labelled MRP, whichever is lower.
- Follow Us :


© $2026 Times Horizon Private Limited